


 Close
 31st October 2023
Philosophy and Ethics of Psychiatry
Philosophy of Psychiatry
The philosophy of psychiatry is mainly concerned with the way that we conceptualise mental disorders. Some people experience sadness, fear, erratic behaviour, unusual perceptions or elation and these experiences may be considered as symptoms of mental illness. By viewing them as symptoms, we apply a medical concept to the facts. The experiences may also be viewed as a moral failing, religious phenomena, normal response to a life situation or a criminal issue. Philosophy, in this sense, is about examining how we make sense of the world around us.
The mind and the body
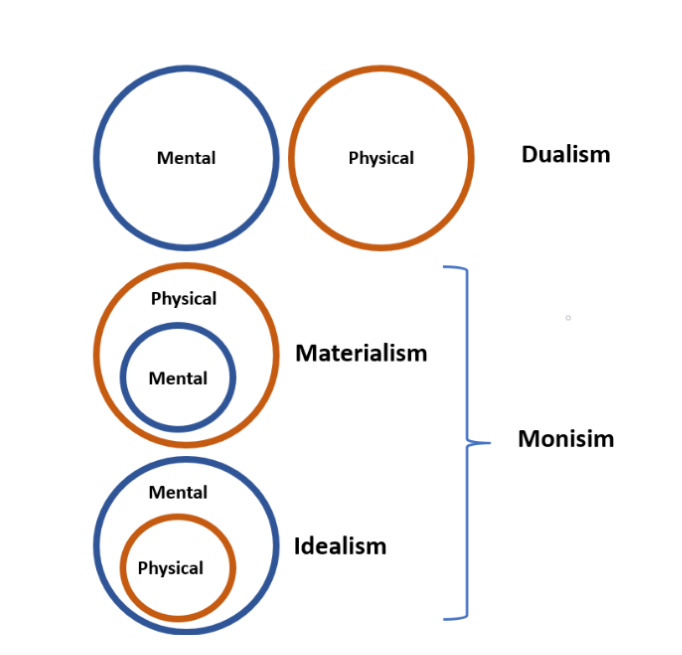
The relationship between the non-material mind and the material body is key to a branch of philosophy known as the philosophy of mind. The main schools of thought are dualism and monism. Philosophy of mind exists as a form of phenomenology, which is about exploring and understanding our consciousness and how we perceive the world in the first person. Whereas phenomenology is about our experience itself, empiricism is concerned with what can be learned from these experiences.
Within phenomenology, there are two ideas that are important to know. Intentionality is the way an experience is directed towards the self. Qualia is the subjective way that we individually feel something. An example is seeing the colour green – as much as you can describe it, you cannot know that another person is seeing the same colour as you.
Dualism
Dualism is the understanding of the mind as something categorically separate from the physical brain and body. The functions and experiences of the mind are non-physical in being. Rene Descartes is credited with being the first philosopher to clearly identify that the mind is distinct from the brain in that it is associated with consciousness. Intuitively, many of us non-philosophers would have a dualist way of seeing the world.
Substance dualism (also known as Cartesian dualism) – Argues that the mind and body are qualitatively different and separate. The mind has no physical projection in space, and the body does not think. Descartes argued that immortal souls live in a separate existence from the physical world.
Property dualism – The mind arises from the brain. Therefore, the properties of the mind are independent of the brain, but they are both the same substance. If you have the right substance (the neural cells that make up the brain, then mental properties emerge.
Predicate dualism – Claims that mental predicates cannot be reduced to physical predicates. A predicate here means the way in which we describe or talk about the mental and physical processes.
Monism
This is the position that the mind and the brain are not two distinct entities. Monism is generally split into two schools of thought: Materialistic and Idealism.
Materialistic – The mind is entirely arising from the physical brain, and eventually, it will be understood and explained by physical science. It is also known as physicalism.
Idealism – All that exists is the mental (or ‘ideas’ – hence the name). The brain, body and physical world are all constructs or illusions of the mind.
What is a mental illness?
The medical model (such as viewing the above experiences as symptoms of mental illness) implies that there is a value-free science of psychiatry that relies only on cold, hard facts. Many philosophers of the 20th century have argued that psychiatry is inherently value-laden.
Thomas Szasz
Szasz believed that medicine was over-reaching by applying the models of illness used in physical disease to mental distress. What we call mental illness, Szasz referred to as ‘problems of living’. In his 1960 essay ‘The Myth Of Mental Illness’, he argues several points as to why mental illness does not exist.
He examines the assumption that underlying mental illness, there is always a (perhaps yet undiscovered) neurological lesion and suggests that social factors (and the daily struggle of life) are more important. This is contrasted with diseases of the brain, which fall under the remit of neurology. He also argues that psychiatric diagnosis is based on a subjective understanding of a patient. For example, a patient may believe he is Napoleon but will only receive a diagnosis of delusional disorder if the clinician believes he is not Napoleon.
Robert Kendell
Kendell is a psychiatrist who critiqued Szasz’ opposition to the validity of mental illness in his 1974 essay ‘The Concept of Disease and its Implications for Psychiatry’. Instead of constructing the idea of disease around the need for an identifiable ‘lesion’, he drew on previous work that proposed diseases were:
Deviations from normal – This means that an illness is a state in which the individual is – by some perimeter – statistically different from the rest of the population. An intuitive example of this is hypertension. Of course, Kendell points out; some deviations can be neutral (foot size) or advantageous (intelligence – to a point).
Biologically disadvantageous – Meaning that the disease state leads to either reduced fertility or increased mortality. Kendell identifies that this criterion eliminates conditions that are abnormal but not harmful (such as syndactyly or stage 1 hypertension) but excludes conditions such as psoriasis or post-herpetic neuralgia, which do not shorten life or reduce fertility.
Kendell goes on to examine contemporary data about fertility rates in people with severe mental illness (reduced, especially among those with schizophrenia) and the mortality rates (raised). This argument is further complicated by discussion around whether these disadvantages are innate to the mental illness or rather exist as a result of the stigma and social exclusion faced by people with mental illness.
Christopher Boorse
Boorse’s conceptualisation of disease is that the human body has innate ways in which it can function, and deviations away from these reference ranges can be harmful to the organism. Therefore, Boorse is most often associated with the ‘harmful dysfunction’ model of disease. Of course, there is a subjective element to making a judgement about what is harmful.
When this dysfunctional state is deemed to be harmful, then the condition can be considered to be an illness, which comes along with special treatment, the sick role and (sometimes) excuses for bad behaviour.
In order to be able to identify deviations from natural functioning, there has to be a well defined reference group. Critics of Boorse’s theory claim that there is no value-free way to choose these reference groups. The natural functioning of the pancreas in a reference group of diabetics would be entirely different to a sample of people without diabetes. Kingma’s 2007 article uses the example of homosexuality. This is a difference that leads to reduced fertility, but it would only be a deviation from natural functioning if the chosen reference group consisted of heterosexual people. The choosing of a heterosexual reference group is itself a value laden judgement.
Jerome Wakefield
Wakefield follows Boorse by continuing the idea that there is a species-typical design. He argues that this is a product of natural selection. Wakefield expands the concept of harmful dysfunction to mental illness; they are the result of malfunctioning psychological processes, causing harm (distress) to the individual. Looking at the natural function of a thing (in this case, its purpose, evolutionarily) falls under the philosophical branch of teleology.
Naturalism and Constructivism
The above examples point to illness, specifically mental illness, arising as a result of a deviation from an inherent ‘healthy’ way of functioning. The disease would continue to exist even if it were not classified as such. This is known as a naturalist conception of disease. Schizophrenia, in this understanding, would exist even if it were not grouped within the category of ‘mental illness’.
Constructivists would argue that schizophrenia would not exist if it were not within human interest to define it. Diseases of any sort, in a constructivist understanding, cannot be identified independently of human values. Disease labels might be considered as a way of exerting social control.
A disease that exists in isolation from human values and is not changed by labelling it such would be known as a natural kind. Mental illnesses tend to change with time and in response to human understanding, perception and diagnosis of them, a process referred to as ‘looping’. This instability means many argue they cannot be natural kinds.
Michel Foucault and antipsychiatry
A criticism of the validity of psychiatry diagnosis would not be complete without a nod to the work of Michel Foucault. Foucault is associated with post-modernism and post-structuralism. These movements argue that truth and meaning are inconsistent; subjective truth results from individual experience, oppression and roles. Foucault’s take on psychiatry can be understood as a way for those in power to exert control over the freedom and behaviour of those labelled mentally ill.
Changes in the way mental illness is treated, including de-institutionalisation, occurred in the 1960s and 1970s alongside a movement known as antipsychiatry. Antipsychiatry is a movement that believes a medical model of mental illness (and associated medications and compulsory treatment) does more harm than good. Scottish psychiatrist RD Laing, like Szasz, rejected the notion that so-called mental illnesses could be understood and treated in a comparable way to physical illness. He took issue with the fact that mental disorders are diagnosed through observable behaviours and yet treated biologically.
References
- Bracken, P. and Thomas, P. (2010) “From Szasz to Foucault: On the Role of Critical Psychiatry,” Philosophy, Psychiatry, & Psychology, 17(3).
- Fulford, B., Thornton, T. and Graham, G. (2006) “Chapter 2,” in Oxford Textbook of Philosophy of Psychiatry. Oxford: Oxford University Press, pp. 2–20.
- Kendell, R.E. (1975) “The concept of disease and its implications for psychiatry,” British Journal of Psychiatry, 127(4), pp. 305–315. Available online at: https://doi.org/10.1192/bjp.127.4.305. [Accessed Feb 2023]
- Kingma, E. (2007) “What is it to be healthy?” Analysis, 67(2), pp. 128–133. Available Online at: https://doi.org/10.1093/analys/67.2.128. [Accessed Feb 2023]
- Murphy, D. (2020) Concepts of disease and health, Stanford Encyclopedia of Philosophy. Stanford University. Available online at: https://plato.stanford.edu/entries/health-disease/ [Accessed April 2023]
- Philosophy of mind (no date) Philosophy of Mind – By Branch / Doctrine – The Basics of Philosophy. Available online at: https://www.philosophybasics.com/branch_philosophy_of_mind.html [Accessed April 2023]
- Szasz, T.S. (1974) “The myth of mental illness,” Perspectives in Abnormal Behavior, pp. 4–11. Available Online at: https://doi.org/10.1016/b978-0-08-017738-0.50007-7. [Accessed March 2023]
- Wakefield, J.C. (1992) “The concept of mental disorder: On the boundary between biological facts and social values.” American Psychologist, 47(3), pp. 373–388. Available online at: https://doi.org/10.1037/0003-066x.47.3.373. [Accessed March 2023]
Ethics of Psychiatry
Underlying principles
This chapter will provide an overview of the key ethical concepts we encounter in Paper A. Broadly speaking, ethics can be divided into schools: Duty based and utilitarianism.
Duty based ethics
Duty based ethics are the rules imposed on us from above; a ‘top down’ approach such as GMC guidance, Department of Health framework and guides from the RCPsych. Duty based ethics are also called deontology. A criticism of duty based ethics is that they can feel inflexible.
A distinct area of deontology is Kant’s moral theory, which claims that the ultimate principle of morality is goodwill. This can only be achieved through reason. Kant describes the idea of a categorical Imperative, which is a rule to live by that is entirely unrelated to the outcome and only informed by what a person ‘ought’ to do.
Utilitarianism
Utilitarian schools of thought find that the best outcome is one that promotes the most happiness, pleasure, and the absence of pain. This is included under the broader category of consequentialism, which in itself is seen as part of teleology. As already discussed in this chapter, teleology is about the purpose something serves. In this case, it is concerned with achieving the greatest good for the greatest number, focusing on the collective above the individual.
Rule consequentialism: A combination of the above
Consequentialism at its core in promoting maximum good, but with certain fundamental rules that are seen as being important to follow. However, such rules that are chosen to follow will be based on the consequences that the selected rules will have.
Virtue theory
Virtue theory differs from the above ethical schools in that its focus is on striving for the individual rather than following rules (duty based) or attending to positive outcomes (utilitarianism). Virtue theory posits that in order to lead a good life, virtues should be identified and aligned with. Aristotle was a philosopher whose works focused on achieving a state of ‘human flourishing’, also known as eudemonia. Virtue systems are often subjective and influenced by the prevailing utilitarian or rule based thinking within a society.
A history of medical ethics
Hippocratic oath
The Hippocratic oath dates from approximately 400 BCE, and it is still required for many newly qualified doctors to recite. The oath outlines a moral code that physicians should apply to their practice and includes striving to do good and avoid causing harm, not performing surgery (leave this to surgeons), maintaining solidarity with other health professionals, not assisting in abortion or suicide, and not to seduce patience.
Declaration of Helsinki – 1964
This is a statement that came from the Assembly of the World Medical Association and is developed from the Nuremberg Code and the Declaration of Geneva. It outlines ethical principles for medical research on human participants. The important themes from the Declaration of Geneva are that the priority of any medical research should be the wellbeing of the participants and that accepted scientific principles should be adhered to.
Nuremberg Code of Ethics – 1947
The Nuremberg Code of Ethics came into being following trials of doctors who had committed crimes in the name of human experimentation and murder in 1930s and 1940s Germany. As well as sentencing, the trials led to the development of 10 principles to prevent such crimes from occurring again. These principles, including the importance of informed consent in experiments, are collectively known as the Nuremberg Code.
Declaration of Geneva – 1948
Another response to the medical crimes of the Second World War, the Declaration of Geneva, is an oath for medical professionals. It highlights the humanitarian goals of physicians and their commitment to human rights.
Applied ethics in the context of the legislation of England
The four principles of biomedical ethics
Within medical ethics, there are a few other theories to consider. Notably, there are the four principles that make up the biomedical ethics framework (Beauchamp and Childress, 1979). The four principles approach suggests that when faced with a dilemma, a clinician should formulate their decision based on the autonomy of the patient, the capacity to benefit the patient (beneficence), the avoidance of harm to the patient (non-maleficence) and justice. Justice can be either in regard to what is just for the patient or what is just for the greater good of society with regard to the distribution of resources.
These four principles can themselves be in conflict. For example, autonomy and justice can be in conflict whereby the clinician must weigh up the wishes of the patient versus what is fair for all of society. A patient may request admission to a hospital, which is an expression of their autonomy, but they may not be admitted due to being less unwell than other patients in a community (this relates to justice).
Another example is examining the balance between beneficence and non-maleficence. In the case of clozapine treatment for resistant schizophrenia, the benefits (reduction in positive symptoms and distress) must be weighed against the risks (metabolic syndrome, myocarditis, agranulocytosis).
Informed consent and the Mental Capacity Act 2005
Informed consent is a key concept within medicine. It derives from the principle of autonomy, as described above. By providing a treatment or procedure on a patient without their permission, a doctor’s actions could legally be considered battery.
The following criteria must be fulfilled for consent to be valid informed consent:
- Given voluntarily (with no coercion or deceit).
- Given by an individual who has capacity.
- Given by an individual who has been fully informed about the issue.
In order to give valid consent, a patient must have the capacity to make this decision. Capacity is dynamic and must be reassessed regularly and taking into context the nature of the decision in question. According to the Mental Capacity Act 2005, a person is deemed to have capacity if they can:
- Understand the information given to them (when reasonable measures have been taken to give the information in a way that is understandable to that person).
- Retain the information.
- Weigh up the information.
- Communicate their decision (again, reasonable measures must be taken to help a patient with difficulty with communication).
If a patient does not have the capacity to make the decision in question, efforts must be taken to find the least restrictive option in the patient’s best interest. There may be an appointed lasting power of attorney (LPA), an adult with legal permission to make decisions in the best interest of the patient. This has to be registered at the Office of the Public Guardian and can be revoked if the LPA is deemed to not be acting with the patient’s best interest in mind. The key principles involved here are beneficence and non-maleficence.
Compulsory treatment and the Mental Health Act – 1983
The Mental Health Act covers the assessment and treatment of mental disorders. As of 2007, the Mental Health Act defines a mental disorder as ‘any disorder or disability of the mind’. There are no longer exclusions for sexual deviancy, nor a ‘treatability’ prerequisite – this means it is easier to justify detaining sex offenders in hospital.
Drug and alcohol misuse alone is not deemed to be a mental disorder.
For someone to be detained in hospital, the following three criteria should be fulfilled:
- The patient has a disorder of the mind.
- The disorder is of sufficient severity to require treatment in hospital.
- The health and/or safety of the patient or the general public’s protection requires hospital detention.
The Mental Health Act overrides the MCA 2007 in the sense that even a patient with the capacity to consent to treatment may be given treatment without their consent if the Mental Health Act covers that treatment. For example, a patient detained under sections 2, 3, 35 or 36 can be given treatment for their mental illness without their consent. A common pitfall is the belief that section 2 is only for assessment; it is for both assessment AND treatment.
Detained patients can also be given treatment for physical illness that is a consequence of their mental illness (such as severe malnutrition in the case of a patient with anorexia nervosa or an infected bed sore in the case of a patient with a depressive stupor).
Key exceptions to this are ECT and psychosurgery. These treatments can only be given with the consent of the patient, or else a second opinion must be sought. In practice, ECT can be given an emergency treatment if either of the following are fulfilled:
- It will be immediately life saving.
- It will prevent deterioration in a patient’s health and not have irreversible physical or psychological sequelae.
| Section | Reason for Detention | Who can do this? | Comments |
|---|---|---|---|
| 2 | Assessment + Treatment (Max 28 days). | Nearest relative or AMHP
2 x registered medical professionals |
S2 ends when the patient is informal or converted to S3. |
| 3 | Treatment (Max 6 months). | Nearest relative or AMHP
2 x registered medical professionals |
It can be extended for a further 6 months and then annually. |
| 4 | Emergency assessment (Max 72 hours). | One registered medical professional | Should be converted to S2 as soon as possible. |
| 5(2) | Doctors holding section (Max 72 hours). | Covering doctor or nominated deputy | Must be used onwards.
Cannot be used in A+E. |
| 5(4) | Nurses holding section (Max 4 hours). | Registered nurse | Must be used on wards.
Cannot be used in A+E. |
| 136 | Removal from a public place to a place of safety (maximum 24 hours). | Police officer | Place of safety can be a section 136 suite, emergency department or police cells.
This section can be extended to up to 36 hours if an MHA cannot be carried out in the first 24 hours (say, for physical health concerns). |
Human Rights Act – 1998
The Human Rights Act 1998 incorporates the European Convention of Human Rights into the law of England, Wales and Northern Ireland. A key feature of the Human Rights Act is the significance it places on proportionality.
The Human Rights Act has been used when contesting detention under the Mental Health Act. The detention of someone against their will is in contravention of their human rights, but the Mental Health Act can be seen as an exception, provided the violation of human rights is to the minimum extent possible.
Ethics in the treatment of children
The Children Act – 1989
This legislation is aimed at court cases involving children. It is used to uphold the welfare of children and ensure their views are appropriately considered. It defines who has parental responsibility and allows anyone with parental responsibility to act alone to give consent.
Although it is mostly aimed at legal cases, there are some aspects relevant to medical settings, as considering the views, feelings and understanding of children is important when decisions about medical treatment are being made.
Consent in under 18s
Although a patient is not a legal adult until the age of 18, their ability to consent to treatment is assessed on a sliding scale related to their understanding, maturity, and the nature of the treatment.
According to the Family Law Reform Act of 1969, a child aged 16 or older has the same right to consent to medical treatment as an adult, even without consent from their guardian.
Gillick competence – 1985
Relates to the 1985 legal case of Gillick vs West Norfolk and Wisbech Area Health Authority. This case examined the matter of doctors prescribing contraception to those under 16. When medical professionals are deciding whether a child under the age of 16 has the capacity to consent, they are assessing Gillick competence.
Factors involved include the chronological age of the child, their level of maturity, their understanding of the problem, its risks, consequences and course, the risks and benefits of the treatment, their understanding of alternative ways forward, and their ability to weigh up and communicate their decision.
Gillick competence is related to any healthcare decision in a minor.
Fraser guidelines
Within the Gillick Case, Judge Ian Fraser laid down criteria specifically related to doctors’ responsibilities when prescribing contraceptives to those under 16 without parental consent. When prescribing, the professional must be satisfied that:
- The young person understands the advice being given.
- The young person cannot be convinced to involve parents/carers.
- It is likely that the young person will begin or continue having intercourse with or without treatment/contraception.
- Unless he or she receives treatment/contraception, their physical or mental health is likely to suffer.
- The young person’s best interests require contraceptive advice, treatment or supplies to be given without parental consent.
Medical negligence
An important case relating to medical negligence is that of Bolam vs Friern Barnet Management Committee 1957. Bolam was a patient undergoing electroconvulsive therapy who suffered severe injury as muscle relaxants were not administered. He claimed that his doctor was negligent for not giving him muscle relaxants, restraining him during the procedure, or informing him of the risks. The judge in this case ruled that Bolam’s doctor had not been negligent, as restraint and muscle relaxants were not common practice at that time. What’s more, the risk of injury was not disclosed to patients unless they asked.
The Bolam test means a doctor must be able to show that any medical professional who was in the same position as them would have done the same. If this is true, then they’re not guilty of negligence.
References
- Ackroyd, M. (2021) Ethics and philosophy in psychiatry, TrOn (Trainee Online). RCPsych. Available online at: https://elearninghub.rcpsych.ac.uk/product?catalog=51_TRON_Eth_phil_psych. [Accessed Feb 2023]
- Beauchamp and Childress. 1979 The Principles of Biomedical Ethics.
- Decision Making and Consent – Ethical Guidance (no date) General Medical Council. Available at: https://www.gmc-uk.org/ethical-guidance/ethical-guidance-for-doctors/decision-making-and-consent [Accessed April 2023]
- Declaration of Geneva (no date) The World Medical Association. Available at: https://www.wma.net/policies-post/wma-declaration-of-geneva/ [Accessed April 2023]
- Declaration of Helsinki – Ethical Principles for Medical Research Involving Human Subjects (no date) The World Medical Association. Available at: https://www.wma.net/policies-post/wma-declaration-of-helsinki-ethical-principles-for-medical-research-involving-human-subjects/ [Accessed April 2023]
- GP Mythbuster 8: Gillick Competency and Fraser Guidelines (2022) Care Quality Commission. Available at: https://www.cqc.org.uk/guidance-providers/gps/gp-mythbusters/gp-mythbuster-8-gillick-competency-fraser-guidelines [Accessed April 2023]
- Mental Health Act 1983, Available at: http://www.legislation.gov.uk/ukpga /1983/20/contents [Accessed April 2023]
- The BMA (2020) Key Principles of Ethics for Medical Students, The British Medical Association is the trade union and professional body for doctors in the UK. BMA. Available at: https://www.bma.org.uk/advice-and-support/ethics/medical-students/ethics-toolkit-for-medical-students/key-principles-of-ethics-for-medical-students [Accessed April 2023]
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

