


 Close
 29th December 2023
Retinal vascular disorders
Diabetic retinopathy
Background
Diabetic retinopathy (DR) is the most common sight-threatening retinal vascular disease and is one of the leading causes of visual impairment in the working-age population. Risk factors for the development of diabetic retinopathy include a longer duration of diabetes, hyperglycaemia, hypertension, hyperlipidaemia, pregnancy, and renal disease.
The National Institute of Health and Care Excellence (NICE) recommends that all adult patients with diabetes should be referred to the local community diabetic retinopathy screening service at the point of diagnosis and should continue to be screened at least once a year. These patients are then referred to the hospital eye services if they develop sight-threatening retinopathy.
Clinical Features
Diabetic retinopathy can be categorised into the ‘non-proliferative’ and ‘proliferative’ stages.
Patients tend to be asymptomatic until they develop maculopathy (blurred central vision), proliferative retinopathy with vitreous haemorrhage, or fibrovascular proliferation, which may develop into tractional retinal detachment (floaters, blurred vision).
There are various classification systems used for diabetic retinopathy. The following grading system is used by the Diabetic Screening Programme and is based on the UK National Screening Committee (NSC) criteria:
| NSC Grading | Severity | Clinical Features | Management |
|---|---|---|---|
| R0 | No diabetic retinopathy | No retinopathy | Annual screening |
| R1 | Mild non-proliferative diabetic retinopathy | Microaneurysms and intraretinal haemorrhages only | Annual screening |
| R2 | Moderate to severe non-proliferative diabetic retinopathy | Extensive microaneurysms, intraretinal haemorrhages, and hard exudates. Venous beading, venous reduplication, multiple blot haemorrhages, intraretinal microvascular abnormalities | Refer to hospital eye services |
| R3A | Active proliferative diabetic retinopathy | New vessel formation at the disc or elsewhere on the retina, inadequately treated cases, or reactivation of proliferative or potentially sight-threatening change from fibrous proliferation. | Refer urgently to hospital eye services within 2 weeks |
| R3s | Stable-treated proliferative diabetic retinopathy | Evidence of peripheral laser treatment without active new vessels | Annual screening |
| M0 | No maculopathy | No maculopathy | Annual screening |
| M1 | Maculopathy | Microaneurysms, exudates, or retinal thickening affecting the macula can be classified into mild, moderate, severe, or clinically significant versus non-clinically significant. | Refer to hospital eye services within 13 weeks |
| U | Unclassifiable | Screening photographs, such as a cataract, cannot be graded due to media opacity. | Refer to hospital eye services |
| P | Photocoagulation | Evidence of previous photocoagulation scars (focal or grid laser to macula or peripheral scatter laser) | Nil |
Complications
People with proliferative diabetic retinopathy may develop vitreous haemorrhage and tractional retinal detachments, which may require surgery. Other causes of visual loss include macular ischaemia and neovascular glaucoma.
People with low vision due to diabetic retinopathy (or other common causes such as glaucoma and age-related macular degeneration) can develop Charles Bonnet syndrome, a condition in which they experience visual hallucinations but retain insight that their hallucinations are not real.
Management
Systemic Management:
Blood pressure and glycaemic control should be optimised for all patients. Patients should be assessed and treated for dyslipidaemia, particularly if significant macular exudation is present.
Ocular Management:
Non-proliferative diabetic retinopathy should be closely monitored at appropriate intervals depending on the stage of retinopathy.
For patients with proliferative diabetic retinopathy, urgent pan-retinal photocoagulation should be considered, particularly if there are high-risk features such as vitreous haemorrhage, new vessels on the disc >1/3 disc diameter in size, or new vessels elsewhere on the retina associated with vitreous haemorrhage.
For patients with diabetic maculopathy, management depends on the extent and location of macular oedema. Non-centre involving macular oedema is asymptomatic and can be observed; alternatively, macular laser can be considered in discussion with the patient. Intravitreal anti-vascular endothelial growth factor (anti-VEGF) injections such as Ranibizumab (Lucentis) are licensed for the treatment of diabetic macular oedema if the central retinal thickness is 400 microns. Aflibercept (Eylea) is another option. Intravitreal steroid implants such as Ozurdex can be used for pseudophakic patients. Intravitreal injections carry a low (0.024-0.265%) risk of acute postoperative endophthalmitis, which can have a devastating impact on the patient’s vision and, hence, quality of life. Clinicians should, therefore, have a low threshold of suspicion in patients presenting with loss of vision and/or severe eye pain after injections.

Image Source: Wikimedia Commons (2006). Fundus photo showing focal laser surgery for diabetic retinopathy EDA10, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Fundus_photo_showing_focal_laser_surgery_for_diabetic_retinopathy_EDA10.JPG (Accessed on: 18 June 2022).

Image Source: Wikimedia Commons (2006). Fundus Proliferative retinopathy EDA01, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Fundus_Proliferative_retinopathy_EDA01.JPG (Accessed on: 18 June 2022).

Image Source: Wikimedia Commons (2006). Fundus photo showing scatter laser surgery for diabetic retinopathy EDA09, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Fundus_photo_showing_scatter_laser_surgery_for_diabetic_retinopathy_EDA09.JPG (Accessed on: 18 June 2022).
Retinal vein occlusion
Background & Epidemiology
Retinal vein occlusions (RVO) are a common form of retinal vascular disease second only to diabetic retinopathy in frequency.
RVOs can be classified into central retinal vein occlusions (CRVO), branch retinal vein occlusions (BRVO), and hemi-retinal vein occlusions (HRVO), depending on the affected vein(s). RVOs can be further classified into the ischaemic and non-ischaemic forms based on the size of the area of capillary non-perfusion.
CRVOs occur due to central retinal vein thrombosis at the level of the lamina cribrosa. BRVOs occur when systemic hypertension causes sclerosis of the retinal arterioles: as retinal arterioles and venules share a common adventitial sheath, the sclerosed arteriole compresses the lumen of the retinal venule, causing turbulent blood flow and thereby thrombosis.
The risk of developing RVO increases with age, with over 50% of cases occurring in patients aged 65 years and above. Other common risk factors include systemic hypertension, diabetes (for CRVO), increased body weight (for BRVO), renal failure, and hypercoagulable states, including dehydration, multiple myeloma, polycythaemia, oral contraceptive pill use, protein C and S deficiency, Factor V Leiden etc. Inflammatory diseases associated with occlusive periphlebitis, such as Behcet’s disease, sarcoidosis, or systemic lupus erythematosus, may occasionally cause RVOs.
Clinical features
Patients may be asymptomatic or describe a painless blurring of vision, depending on the area of retina affected and whether macular oedema is present. Macular oedema typically occurs when the superotemporal retinal vein or central retinal vein is affected.
The affected vein(s) is dilated and tortuous, with flame-shaped haemorrhages and dot or blot haemorrhages in the area of the retina drained by the affected vein. In CRVO, haemorrhages are present in all 4 quadrants of the retina, thereby producing the characteristic ‘blood and thunder’ fundoscopic appearance. Optic disc oedema may be present in CRVO. Cotton wool spots may be present. Signs of hypertension, such as arteriovenous nipping, may also be visible.
Management
Systemic Management:
Recommended investigations include blood pressure, serum glucose, and blood tests for ESR and CRP. Further assessment of potentially associated systemic conditions should be considered based on the patient’s age and medical history.
Underlying risk factors such as hypertension and hyperglycaemia should be addressed. The decision to continue oestrogen-containing treatments should be considered on an individual basis. It is important to note that there is conflicting evidence on whether patients with RVOs are at increased risk of stroke and cardiovascular disease. It may be that these conditions may share underlying risk factors such as hypertension and diabetes.
Ocular Management:
Patients should be monitored closely for sequelae such as macular oedema, which can be treated by close monitoring (if asymptomatic) or anti-vascular endothelial growth factor (VEGF) injections such as Ranibizumab or Aflibercept, or intravitreal steroid implants such as Ozurdex. Patients with ischaemic RVOs should also be closely monitored for retinal and anterior segment neovascularisation, which may be due to tissue hypoxia and subsequent release of VEGF and inflammatory mediators. Anti-VEGF injections can serve as a temporising measure, but patients will often require panretinal photocoagulation to reduce the VEGF drive. If this is not adequately treated, neovascular glaucoma can result. Intravitreal steroid implants such as Ozurdex are a second-line treatment option.

Image Source: Wikimedia Commons (2012). Branch retinal vein occlusion, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Branch_retinal_vein_occlusion.jpg (Accessed on: 20 May 2022).
Retinal artery occlusion
Background & Epidemiology
Retinal artery occlusion (RAO) occurs due to blockage of blood flow through a retinal artery, either from a thrombus, embolus, or vascular inflammation or spasm.
RAOs tend to occur in the elderly population and are predominantly due to atherosclerotic emboli from the carotid bifurcation, with giant cell arteritis comprising a smaller proportion of these cases (<5%). Multiple studies have reported an association between RAO and concurrent silent ischaemic stroke and/or subsequent stroke risk. Both share similar risk factors and patient demographics, including older age, male gender, smoking, systemic hypertension, diabetes, obesity, and dyslipidaemia.
Systemic associations should be considered in younger patients (particularly those aged <50 years), including migraine, trauma, hypercoagulable states, exogenous emboli such as talc in intravenous drug users, cardiac abnormalities producing emboli (endocarditis, valvular disease, cardiac myxoma), infections, and autoimmune disorders (e.g. systemic lupus erythematosus, polyarteritis nodosa, Susac syndrome),
Any artery supplying the eye may be affected. Depending on the affected artery(s), RAOs can be classified into central retinal artery occlusion (CRAO), branch retinal artery occlusion (BRAO), cilioretinal artery occlusion (CLRAO), or ophthalmic artery occlusion. The central retinal artery supplies the inner two-thirds of the retina, while the ophthalmic artery supplies the retina and choroid.
Clinical Features
CRAOs present with acute onset painless loss of vision. A relative afferent pupillary defect may be present. A ‘cherry red spot’ may be seen on fundoscopic examination – this is the fovea, which is the thinnest part of the retina and retains relative transparency, in contrast to the surrounding retina, which develops oedema and opacification of the inner retinal layers and therefore appears pale. The arteries are attenuated and demonstrate segmental blood flow (‘box-carring’ or ‘cattle-trucking’ of the blood column within it). Up to 25% of patients may retain preserved central vision due to the presence of a cilioretinal artery supplying the papillomacular bundle; this is supplied by the posterior ciliary artery and, therefore, unaffected by CRAO.
BRAO presents with acute onset visual defect corresponding to the area of retina supplied by the affected artery, which tends to appear pale due to intracellular oedema in the acute phase. The affected artery may be attenuated with ‘box-carring’ or ‘cattle-trucking’ of the blood column within it. Emboli may be visible within the relevant retinal arteries in up to two-thirds of cases, appearing as yellow refractile plaques (Hollenhorst plaques), whitish non-refractile calcified particles, or greyish elongated fibrin-platelet aggregates. Cotton wool spots may be present.
Ophthalmic artery occlusion should be suspected in patients with profoundly reduced vision (no perception of light) because it affects both the inner and outer retina as well as choroidal perfusion. There is, therefore, retinal pallor, albeit without a ‘cherry red spot’ due to absence of choroidal perfusion. A relative afferent pupillary defect may be present.
Management
Acute management:
RAOs represent one of the few ophthalmic emergencies, particularly as there is a short treatment window before irreversible vision loss sets in. Experiments on animal models have demonstrated irreversible retinal damage after 100 minutes of retinal arterial occlusion. Ocular massage is often undertaken in an attempt to dislodge the thrombus/ embolus, as are measures to reduce the intraocular pressure, such as intravenous Acetazolamide, anterior chamber paracentesis, and paper bag rebreathing to produce hypercarbia. Thrombolysis is performed in some centres as well. However, none of these options have been proven to reliably treat RAO.
Management of associated risk factors:
Clinical features of giant cell arteritis (GCA) (new onset headache, amaurosis fugax, temporal tenderness and absent pulse, jaw claudication, anterior ischaemic optic neuropathy, etc.) should be evaluated, and blood tests such as FBC, ESR, CRP should be requested as a matter of urgency, with high-dose systemic steroids started to protect the fellow eye if the degree of suspicion is high. Temporal artery ultrasound and/or biopsy should then be considered as appropriate. GCA is more relevant in CRAO and CLRAO, in contrast to BRAO, which only occurs very rarely in the context of GCA.
Patients should then be referred to a specialist stroke clinic for further workup due to the high risk of stroke (2.2% risk of symptomatic stroke in the 15 days preceding and following the RAO). Underlying risk factors such as hypertension and atrial fibrillation should be sought and addressed. Carotid Doppler ultrasound is often undertaken, and carotid endarterectomy may be indicated in patients with severe (70-99%) carotid stenosis.
Monitoring for complications:
Close monitoring for the sequelae of RAO (retinal and anterior segment neovascularisation) should follow. This occurs less commonly than in patients with RVOs.
Differentials
Differentials of a cherry-red spot in the macula include metabolic storage disorders such as Tay-Sachs disease and Niemann-Pick disease and drug toxicity from methanol poisoning, carbon monoxide poisoning, or intravitreal administration of Gentamicin.
Differentials of retinal pallor include infective retinitis, such as progressive outer retinal necrosis or commotio retinae from blunt trauma.
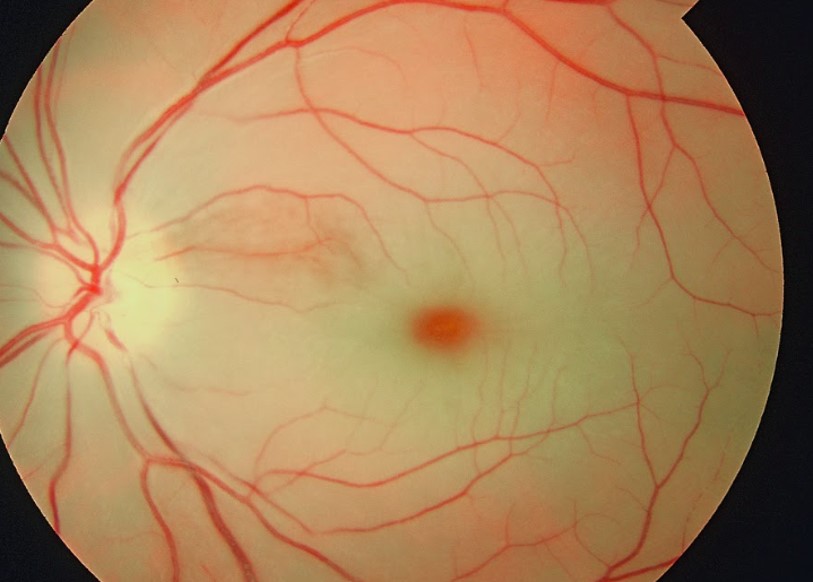
Image Source: Wikimedia Commons (2019). Cherry red spot in patient with central retinal artery occlusion (CRAO), Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Cherry_red_spot_in_patient_with_central_retinal_artery_occlusion_%28CRAO%29.jpg (Accessed on: 27 May 2022).
Hypertensive retinopathy
Background & Epidemiology
Systemic hypertension is the leading modifiable risk factor for cardiovascular disease worldwide, with a global age-adjusted prevalence of 31%. Risk factors include older age, male gender, and Afro-Caribbean origin. The vast majority of cases are chronic, although ‘malignant’ hypertension may sometimes occur if there is an acute severe elevation of blood pressure associated with end organ damage. Both types may be essential (idiopathic) or secondary to other underlying causes, such as renal artery stenosis and phaeochromocytomas.
Hypertension can affect various end organs, including the heart, brain, kidney and eyes. Both acute and chronic ocular abnormalities may result. These can be classified according to the ocular structure affected: retinopathy, choroidopathy, and optic neuropathy. Risk factors for developing hypertensive retinopathy include older age, duration of hypertension, and elevated systolic blood pressure levels.
Clinical Features
The Keith-Wagener-Barker classification is one of the most common grading systems in use:
| Grade | Description |
|---|---|
| Grade 1 | Mild, generalised constriction of retinal arterioles |
| Grade 2 | Focal narrowing of retinal arterioles with arteriovenous nipping |
| Grade 3 | Grade 2 + flame-shaped haemorrhages + cotton wool spots + hard exudates |
| Grade 4 | Severe Grade 3 + optic disc swelling |
Hypertensive retinopathy presents with retinal arteriolar constriction or focal narrowing, with arteriovenous nipping, ‘silver-wiring’ of arterioles, flame-shaped haemorrhages, and cotton wool spots. Hard exudates and macular oedema may be present. Hypertensive optic neuropathy presents with optic disc swelling with or without macular star formation; disc swelling tends to reflect malignant hypertension.
Hypertensive choroidopathy may rarely occur due to malignant hypertension. This may manifest as Elschnig spots (small black spots representing focal choroidal infarcts), Siegrist streaks (streaks indicating fibrinoid necrosis along choroidal vessels), or exudative or serous retinal detachment such as that seen in some patients with pre-eclampsia.
Patients tend to be asymptomatic, except in cases where serous retinal detachment or macular oedema affect the macula. These patients may report blurred vision or scotomas.

Image Source: Wikimedia Commons (2009). Hypertensiveretinopathy, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Hypertensiveretinopathy.jpg (Accessed on: 27 May 2022).
Management
Blood pressure optimisation is key to reducing excess mortality and cardiovascular disease.
In patients with chronic hypertension, a blood pressure of < 140/90 mmHg is appropriate for the majority of patients under 80 years of age and < 150/90mmHg for those 80 years old and above. A lower target of < 130/80 mmHg is ideal for diabetic patients. The target blood pressure should be individualised according to the patient’s clinical circumstances, taking frailty and multi-morbidity into account. Management includes lifestyle changes (diet, exercise, smoking cessation) and antihypertensive treatment according to NICE guidelines.
Patients with malignant hypertension also require urgent intervention to reduce their blood pressure. However, their blood pressure should not be lowered too rapidly or significantly due to the risk of severe multi-organ dysfunction and ischaemia. Antihypertensives should, therefore, be carefully titrated to achieve this. An underlying cause should be sought and managed appropriately.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

