


 Close
 10th January 2024
Pneumothorax
Background
Pneumothorax refers to air within the pleural cavity. There are several definitions to be aware of when considering pneumothorax:
- Primary spontaneous pneumothorax. Refers to the development of a pneumothorax in the absence of an external event without the presence of underlying lung disease.
- Secondary spontaneous pneumothorax. Refers to the development of a pneumothorax in the absence of an external event, with the presence of underlying lung disease, e.g. asthma or chronic obstructive pulmonary disease (COPD).
- Traumatic pneumothorax. Refers to the development of a pneumothorax following an external event. This can further be subdivided into iatrogenic (secondary to a medical procedure) and non-iatrogenic (secondary to blunt or penetrating chest injury).
The focus of this is going to be on primary and secondary spontaneous pneumothorax.
Epidemiology
Primary and secondary spontaneous pneumothoraces are common pathologies that emergency physicians, respiratory physicians and intensive care physicians encounter. Combined hospital admission rates are quoted at 16.7/100,000 for men and 5.8/100,000 for women. Both primary and secondary pneumothoraces are seen at a higher incidence in the male population, with risk factors such as being tall, with low BMI, and cigarette smoking identified.
Primary spontaneous pneumothoraces are seen in a younger population demographic (typically 20-30 years old), whereas secondary spontaneous pneumothoraces are seen in an older population (typically 60-65 years old), reflecting the development of underlying lung disease.
Pathophysiology
In normal breathing, air does not enter the pleural cavity at any point. Therefore, The presence of air signifies the development of pathology from communication between the alveolar spaces and pleura, from communication between the outside atmosphere and the pleural space, or from the presence of gas-producing organisms within the pleural space.
Primary Spontaneous Pneumothorax (PSP)
The mechanism which results in a primary spontaneous pneumothorax is not currently fully understood; however, it has been identified that the majority of patients who present with PSP do have an underlying anatomical abnormality, even in the absence of known lung disease. These “anatomical abnormalities” are typically described as subpleural blebs and bullae, more commonly found at the lung apex. Risk factors for the development of these anatomical abnormalities include cigarette smoke, poor nutritional status with low BMI, connective tissue disease (including Marfan’s syndrome) and hereditary predisposition. It is thought that these subtle anatomical differences, when combined with the appropriate precipitating factor, result in the development of the primary spontaneous pneumothorax. Lung inflammation and oxidative stress are also likely to play an important role in the development of PSP.
Smoking is one of the biggest implicating factors for spontaneous pneumothorax (with BTS quoting a healthy smoking male having a 12% lifetime risk of pneumothorax development, whereas the same demographic non-smoking male is just 0.1%).
Secondary Spontaneous Pneumothorax (SSP)
Secondary spontaneous pneumothorax (SSP) is pneumothorax associated with underlying lung disease, and many underlying chronic lung diseases have been recognised to increase the risk of pneumothorax development. The most common association is with airways disease: chronic obstructive pulmonary disease (COPD), severe asthma and cystic fibrosis. Infections such as pneumocystis carinii can also increase the risk of SSP development.
Tension Pneumothorax
A tension pneumothorax is a potentially life-threatening medical emergency that occurs as a result of the development of a one-way valve system in the pleural space. This one-way system allows air in during inspiration but fails to let air out in expiration, causing progressively larger volumes of air within the pleural space. This raises intrapleural pressures, impairing venous return to the heart, which eventually results in hypotension, tachycardia and, ultimately, cardiovascular collapse.
Presentation
The classical presentation of a spontaneous pneumothorax is sudden-onset ipsilateral pleuritic chest pain, associated shortness of breath and hypoxia. However, these symptoms in PSP can be relatively minor, so patients may not present at the exact time of onset. Patients who have underlying lung disease are typically more symptomatic, with dyspnoea the most commonly reported symptom due to the already damaged underlying lung parenchyma. This can result in patients with SSP reporting symptoms out of proportion to the size of pneumothorax identified on diagnostic imaging (see diagnosis).
An important clinical distinction to make is between the ‘simple’ spontaneous pneumothorax and the tension pneumothorax. Tension pneumothoraces are medical emergencies that are more commonly seen among the most unwell patients: in major trauma, in the critical care environment, but they can also be seen in the medical on-call take environment. The typical symptoms of simple pneumothorax are present (dyspnoea, chest pain), but these are more frequently accompanied by respiratory distress, with or without cardiovascular collapse. Tension pneumothorax is also an important reversible cause of respiratory and cardiac arrest with prompt treatment (see management).
Signs
Simple spontaneous pneumothorax (primary or secondary)
In the very small pneumothorax, there may be little to no clinical findings to appreciate on examination. When a larger pneumothorax has developed, clinical findings that can be elicited include:
- Asymmetrical chest expansion. Due to air building up within the pleural space, the lung itself becomes gradually more compressed. This results in reduced lung expansion on inspiration on the affected side.
- Hyper-resonant percussion.
- Diminished breath sounds.
- Central trachea.
- Evidence of respiratory distress. This includes high respiratory rate, use of accessory muscles of respiration and hypoxia. Patients who have secondary spontaneous pneumothoraces are more likely to present in this way.
Tension pneumothorax
A tension pneumothorax is an uncommon clinical condition but should ideally undergo diagnosis based on clinical history and examination. Prompt recognition and treatment of the below features can result in rapid resolution of respiratory distress and dramatic clinical improvement for patients.
- Asymmetrical chest expansion.
- Hyper-resonant percussion.
- Diminished breath sounds.
- Tracheal deviation away from the side of the above clinical findings.
- Hypotension and tachycardia – suggestive of impending cardiovascular collapse.
- Respiratory distress.
Diagnosis
A diagnosis of a pneumothorax can be made clinically with the identification of appropriate clinical signs; however, these signs are not always present. In any patient presenting with sudden onset dyspnoea and pleuritic chest pain pneumothorax should remain as part of the differential diagnosis. The mainstay of confirming a pneumothorax diagnosis comes from imaging.
A subset of patients with large pneumothoraces or tension pneumothoraces are haemodynamically unstable, and quick diagnosis is required. In this setting, if available, bedside ultrasound can be utilised to confirm the diagnosis with subsequent rapid initiation of management (see management section). However, the majority of patients who present are haemodynamically stable, and it is these patients who can undergo less urgent, non-bedside imaging.
PA Chest X-ray

Image Source: Wikimedia Commons (2017). Spontaneous pneumothorax, Licensed under a creative commons licence. Available for free at: https://upload.wikimedia.org/wikipedia/commons/b/b1/Spontanpneumothorax.jpg (Accessed on: 21 June 2022).
The posterior-anterior (PA) erect chest x-ray is the mainstay of diagnostic imaging in stable patients (and can also be utilised in unstable patients at the bedside if ultrasound is not available). It allows identification of the pathology and size of the pneumothorax, which is important in considering subsequent management strategies.
Features that can be seen on a PA erect chest x-ray are:
- Visible lung edge
- Lung markings absent beyond visible lung edge (and the absence of lung markings to the chest wall should prompt the clinician to look for pneumothorax evidence)
- Radiolucent space beyond visible lung edge, i.e. darker, from increased air without lung parenchyma.
- Increased distance between rib spaces on affected hemithorax.
- Mediastinal shift and tracheal shift away in cases of tension pneumothorax.
- Subcutaneous emphysema.
A “simple” pneumothorax on PA chest x-ray is the presence of pneumothorax without mediastinal shift. A tension pneumothorax is diagnosed when mediastinal shift is identified either clinically or on diagnostic imaging.
In order to measure the size of pneumothorax present, 2 methods can be used: the American method and the British method. In the American method, it is the distance between the apex and top of the lung (cupola). The British method, and the method utilised in BTS guidelines, is the measurement of the interpleural distance at the level of hilum between the visible collapsed lung edge and chest wall. A “small” pneumothorax is typically referred to as a pneumothorax that is <2cm in size and a large pneumothorax one that is >2cm in size. However, it is important to clinically assess and correlate patients (especially those with secondary spontaneous pneumothoraces) as size of pneumothorax does not always correlate with clinical symptomatology and distress.

Flowchart adapted from guidance available at – Maskell N. British Thoracic Society pleural disease guidelines – 2010 update. Thorax. 2010;65(8):667–9.
Gary Lee Y. Clinical presentation and diagnosis of pneumothorax [Internet]. UpToDate. 2021 [cited 2022 Jun 1]. Available from: https://www.uptodate.com/contents/clinical-presentation-and-diagnosis-of-pneumothorax?search=pneumothorax &source=search_result&selectedTitle=2~150&usage_type=default&display_rank=2#H3647761918
CT Thorax
CT Thorax can be utilised when there is diagnostic uncertainty following a PA chest x-ray or in the diagnosis of a small pneumothorax, where it should be considered the “gold standard” for evaluation of size and the underlying anatomy. CT Thorax can not only easily identify a pneumothorax, but it can also alert the clinician to any underlying changes, e.g. emphysematous lung disease or bullae, which may be related to the aetiology of the pneumothorax.
CT remains superior to chest x-ray and ultrasound in terms of accurately identifying a pneumothorax; however, it is not as readily available and exposes patients to a significant dose of radiation.
Ultrasound
Bedside pleural ultrasound can provide rapid diagnosis of pneumothorax in the unstable patient, but it is also highly sensitive for identification of small pneumothoraces.
In the normal lung utilising the straight linear array high-frequency probe, pleural ultrasound shows the lung ‘sliding’ as the patient respires. Alongside the sliding pleural ‘Z lines’ can be seen, which are vertical comet tails (artefacts) running down from the pleura. By switching the probe into M-mode in the normal lung, the “seashore” sign can be visualised, which represents the sliding pleura moving on a motionless chest wall. Several signs on ultrasound can suggest the presence of a pneumothorax:
- Absence of lung sliding.
- On M mode – this can be referred to as the “barcode” sign.
- Absence of comet tail artefacts. These artefacts are lost due to the build-up of air within the pleural space.
- Lung point sign. This nearly 100% specific sign for pneumothorax refers to identifying the junction between sliding lung and non-sliding lung. This is useful in small pneumothoraces as in larger-sized pneumothoraces, entire lung collapse can occur, and therefore, global absence of lung sliding is noted.
- This sign can also be helpful in estimating size of the pneumothorax if present.
- Absence of lung pulse.
Differential Diagnosis
The differential diagnosis of pneumothorax is wide and relates to any condition that can present with acute-onset chest pain and dyspnoea. Clinical history and examination findings are key to establishing the underlying diagnosis, as many cardiac and respiratory conditions can present similarly. The table below summaries some common differential diagnoses of this presentation to be aware of.
| Diagnosis | Clinical History Points | Clinical Examination Findings |
|---|---|---|
| Respiratory | ||
| Pulmonary Embolism | VTE risk factor identified: active malignancy, combined oral contraceptive pill, recent travel >4 hours or surgery.
Pleuritic chest pain. Haemoptysis associated. |
Clinical examination in PE is typically normal in uncomplicated PE.
In large PE – signs of right heart failure may be present: peripheral oedema, raised JVP, pulsatile hepatomegaly. Chest x-ray: normal. |
| Acute asthma exacerbation | Acute shortness of breath + wheeze.
Increased use of PRN salbutamol inhaler. Cough +- sputum production +- fever. Trigger prior to onset. |
Bilateral wheeze.
Often young patient demographic. Chest x-ray: normal, or consolidation if infective exacerbation. |
| Acute COPD exacerbation | Acute shortness of breath.
Wheeze +- cough +- sputum production history. Not associated with chest pain typically. |
Bilateral wheeze.
Prolonged expiratory phase +- tar staining. Type 2 respiratory failure in some cases. Chest x-ray: hyper-inflated lung fields, flattened hemidiaphragms. |
| Cardiac | ||
| Acute myocardial infarction | Crushing, central chest pain.
Sweating, nausea/ vomiting and dizziness associated. Other cardiac risk factors: type 2 diabetes, smoking, alcohol, increased BMI. |
In acute myocardial infarction – grey, sweaty appearance.
Respiratory examination normal. Raised BMI, tar staining may be noted. Chest x-ray: normal or acute pulmonary oedema. |
| Aortic dissection | ‘Tearing’ central chest pain through to the back.
Pre-syncopal/ syncopal episode. |
Difference in blood pressure between 2 arms.
Radial-radial delay. Acute aortic regurgitation (early diastolic murmur) Chest x-ray: mediastinal widening. |
| Acute pulmonary oedema | Cough with pink frothy sputum
Progressive dyspnoea followed by sudden onset nature. Orthopnoea and paroxysmal nocturnal dyspnoea. |
Respiratory distress
Bilateral crackles throughout both lung fields. Chest x-ray: bilateral pleural effusions, pulmonary congestion. |
Table 5: Differential diagnosis of pneumothorax with key history and clinical examination characteristics.
Table adapted from –
Gary Lee Y. Clinical presentation and diagnosis of pneumothorax [Internet]. UpToDate. 2021 [cited 2022 Jun 1]. Available from: https://www.uptodate.com/contents/clinical-presentation-and-diagnosis-of-pneumothorax?search=pneumothorax &source=search_result&selectedTitle=2~150&usage_type=default&display_rank=2#H3647761918
UpToDate. Evaluation of the adult with chest pain in the emergency department [Internet]. 2022 [cited 2022 Jun 1]. Available from: https://www.uptodate.com/contents/evaluation-of-the-adult-with-chest-pain-in-the-emergency-department?search=chest pain&source=search_result&selectedTitle=3~150&usage_type=default&display_rank=3#H18
UpToDate. Evaluation of the adult with dyspnea in the emergency department [Internet]. [cited 2022 Jun 1]. Available from: https://www.uptodate.com/contents/evaluation-of-the-adult-with-dyspnea-in-the-emergency-department?search=shortness of breath&source=search_result&selectedTitle=2~150&usage_type=default&display_rank=2#H4
Management
Several pieces of information are key to the management of a spontaneous pneumothorax. The first is the question of haemodynamic stability. If haemodynamic instability is noted, urgent management is required (see Management: Tension Pneumothorax). If the patient, like in the majority of cases, is haemodynamically stable, then an important distinction between primary and secondary pneumothorax needs to be made. These distinctions are important as secondary pneumothoraces are often tolerated much less well and, therefore, may require more significant management, e.g. intercostal drainage. The third question to ask is how symptomatic is that patient’s pneumothorax? Patients who are significantly dyspnoeic are likely to need more active intervention than those who are asymptomatic. The fourth and final question to consider is the size of the pneumothorax, which can be assessed on the PA chest x-ray or CT Thorax.
What defines a secondary pneumothorax? ‘Secondary’ simply means there is either a known history of underlying lung disease or there is evidence to suggest this:
- Age >50 with significant smoking history.
- Clinical examination consistent with evidence of chronic lung disease.
- Radiological evidence of chronic lung disease.
Tension Pneumothorax
Tension pneumothorax is a life-threatening medical emergency that requires prompt treatment to avoid cardiovascular collapse. If identified either clinically or radiologically, it should be treated with high-flow oxygen and urgent needle decompression with a large-bore needle into the 2nd intercostal space, midclavicular line. This initial life-saving treatment releases some air to decrease risk of progress to cardiovascular collapse but is not definitive management in itself and should be followed by prompt insertion of an intercostal drain for drainage of the pneumothorax. The needle decompression should remain in place until the full procedure for intercostal drain insertion is completed.
Primary Spontaneous Pneumothorax
In small (<2cm) primary spontaneous pneumothoraces which are asymptomatic, a conservative approach to management can be utilised, providing the patient is able to seek medical attention again should they become more unwell at home. Lifestyle advice on smoking cessation should be provided to reduce the risk of recurrence with early review in clinic to ensure resolution of the pneumothorax.
In PSP that is symptomatic with dyspnoea or considered large (>2cm using British measurements), an initial trial of needle aspiration should be utilised alongside high-flow oxygen. Needle aspiration, in the context of PSP, has been shown to have equal success in management of the pneumothorax as insertion of chest drain. It involves the use of a needle and 50mL syringe to drain up to 2.5L of air from the chest. If this fails to improve the patient symptomatically or radiologically (considered to be pneumothorax <2cm), then proceeding to chest drain is the recommendation.
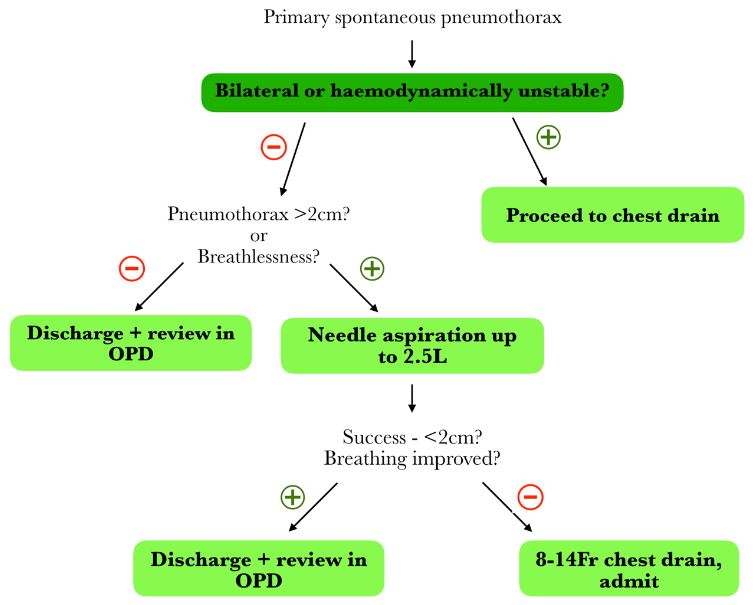
Flowchart adapted from guidance available at – Maskell N. British Thoracic Society pleural disease guidelines – 2010 update. Thorax. 2010;65(8):667–9.
Secondary Spontaneous Pneumothorax
Patients with secondary spontaneous pneumothorax (SSP) tolerate pneumothoraces less well due to their underlying chronic lung disease, which significantly alters the management strategy for this set of patients. In addition to increased symptomatology, SSPs are less likely to spontaneously resolve, meaning active management with insertion of intercostal drainage is more frequently needed.
Given the above, in any SSP that is symptomatic of their pneumothorax, you should proceed immediately to intercostal drainage with a small-bore intercostal drain (8-14Fr), with admission and early input from the respiratory specialist team. In the setting where the patient is asymptomatic, the size of the pneumothorax determines the ongoing management. Pneumothoraces 1-2cm can undergo a trial of needle aspiration up to 2.5L of air with response assessed afterwards. If the pneumothorax is subsequently <1cm, then no further intervention is required other than high-flow oxygen (with caution in those with known hypercapnic respiratory failure) and admission to hospital for at least a 24-hour monitoring period. If needle aspiration fails to create a pneumothorax <1cm in size, then proceeding to drainage is the most appropriate next step.
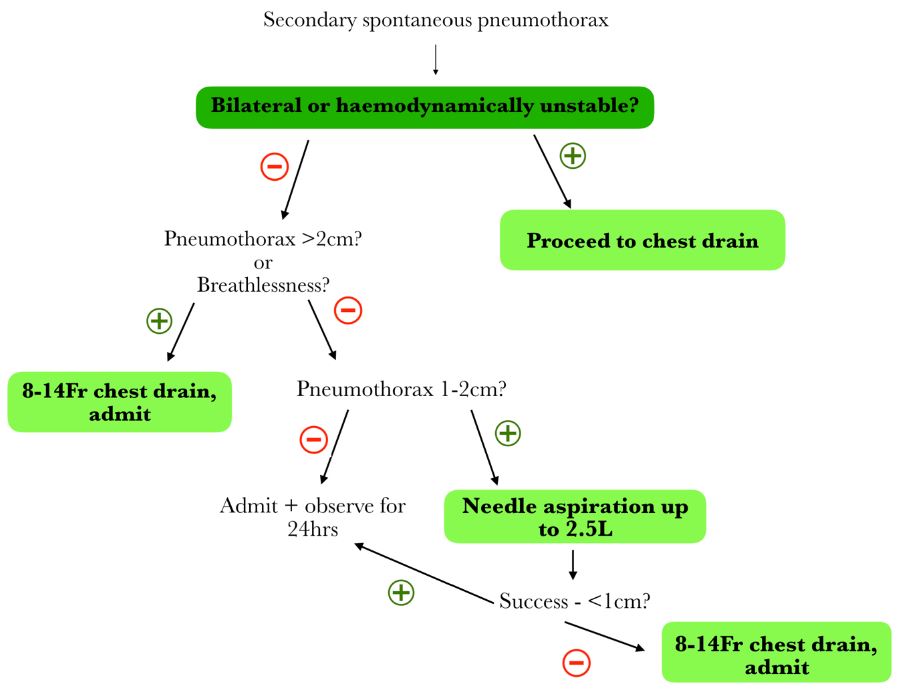
Flowchart adapted from guidance available at – Maskell N. British Thoracic Society pleural disease guidelines – 2010 update. Thorax. 2010;65(8):667–9.
Persistent Air Leak Management in Primary and Secondary Spontaneous Pneumothorax
In some cases, pneumothoraces fail to resolve despite initial management as guided by the algorithms above. This is seen more frequently in secondary spontaneous pneumothorax than primary but is possible in both subtypes. A persistent air leak is usually defined as a failure for the pneumothorax to fully resolve despite 24-48 hours of appropriate management. There are some management options available:
- Suction. Low-grade suction can be considered in patients with a persistent leak at 24-48 hours to help with re-expansion of the lung. The recommendation is to start with low rates of suction, approximately -10cm H20, which can be increased to -20cmH20 dependent on resolution and how well the patient tolerates the added pressure.
- Referral to cardiothoracic surgeons for consideration of surgical management. Consideration of early referral to cardiothoracic surgeons (with persistent air leak at 3-5 days) for surgical management is important in patients fit for surgical procedure and can provide patients with definitive management. This is especially important in patients with SSP.
- Chest drainage with ambulatory drainage device. In selected patients with persistent air leak, a chest drain can remain in situ with a drainage device attached. This drainage device can allow ongoing drainage of air in the community. Decisions to utilise this lie with specialised respiratory colleagues.
- Pleurodesis.
Preventing Recurrence
Patients who present with their first episode of PSP do not typically require definitive treatment, e.g. surgical management unless they have a persistent air leak at the initial presentation or they have a repeat episode.
On the other hand, patients who present with SSP are at high risk of recurrence. As such, in SSP, consideration of definitive management during their initial admission should be completed. In patients considered fit for surgery, surgical methods for definitive management are the preferred option. In those where surgery is not an option or not the patient’s preferred course of action, then chemical pleurodesis with sterile talc pleurodesis or tetracycline pleurodesis can be used (BTS recommends tetracycline pleurodesis over talc if available). Talc or tetracycline pleurodesis results in pleural inflammation and formation of adhesions to cause pleural effusion and prevention of further episodes of pneumothorax.
Management of Recurrent Pneumothorax Episodes
Recurrent pneumothoraces are a common clinical event with an estimated recurrence rate of around 30% in PSP and 50% in SSP, although data on this varies. In PSP, recurrence is thought to be related to some risk factors: being tall, low BMI, smoking and anatomical changes identified on CT (small blebs or bullae). The key risk factor for a further pneumothorax, though, is having had one previously.
In the initial setting, recurrent pneumothoraces should be managed with insertion of an intercostal drain. Recurrent pneumothoraces should prompt the clinician to consider early discussion with cardiothoracic surgical colleagues for definitive management. The agreed criteria for referral, as per BTS guidelines, are the following:
- Second ipsilateral pneumothorax.
- First contralateral pneumothorax.
- Synchronous bilateral spontaneous pneumothorax.
- Persistent air leak at 5-7 days despite intervention, or failure of lung re-expansion.
- Spontaneous haemothorax.
- At risk Profession, e.g. pilots, divers
- Pregnancy.
In patients not suitable for surgery, chemical pleurodesis can be completed (see Management: Preventing Recurrence).
Special Circumstances
Air Travel following Pneumothorax
The British Thoracic Society provided guidance on air travel and history of pneumothorax in 2022. It recommends that any patient with a current, unresolved pneumothorax should not travel by air. In those who have a resolved pneumothorax, they should wait for 7 days after full resolution is confirmed on a chest x-ray before travelling.
Diving following Pneumothorax
The British Thoracic Society published specific recommendations for diving and respiratory disease in 2003. It recommends that anyone with evidence of bullae on CT imaging should not dive due to the increased risk of barotrauma during the activity. In addition, any previous spontaneous pneumothorax is a contraindication to diving (unless specifically treated with bilateral pleurectomy and subsequent normal lung function and imaging following the procedure).
If a patient has had a previous traumatic pneumothorax, this is not a contraindication to diving, providing they have been left with normal lung function and imaging.
References
- BMJ Best Practice. Pneumothorax [Internet]. 2022 [cited 2022 Jun 1]. Available from: https://bestpractice.bmj.com/topics/en-gb/3000083
- Bobbio A, Dechartres A, Bouam S, Damotte D, Rabbat A, Régnard JF, et al. Epidemiology of spontaneous pneumothorax: Gender-related differences. Thorax. 2015;70(7):653–8.
- British Thorax Society Fitness to Dive Group. British Thoracic Society guidelines on respiratory aspects of fitness for diving. Thorax. 2003;58:3–13.
- Carroll D. Pneumothorax (Ultrasound) [Internet]. Radiopedia. 2021 [cited 2022 Jun 1]. Available from: https://radiopaedia.org/articles/pneumothorax-ultrasound-1?lang=gb
- Coker RK, Armstrong A, Church AC, Holmes S, Naylor J, Pike K, et al. BTS Clinical Statement on air travel for passengers with respiratory disease. Thorax. 2022;77(4):329–50.
- Gary Lee Y. Clinical presentation and diagnosis of pneumothorax [Internet]. UpToDate. 2021 [cited 2022 Jun 1]. Available from: https://www.uptodate.com/contents/clinical-presentation-and-diagnosis-of-pneumothorax?search=pneumothorax &source=search_result&selectedTitle=2~150&usage_type=default&display_rank=2#H3647761918
- Gary Lee Y. Pneumothorax in adults: Epidemiology and etiology [Internet]. UpToDate. 2022 [cited 2022 May 31]. Available from: https://www.uptodate.com/contents/pneumothorax-in-adults-epidemiology-and-etiology?search=pneumothorax&source=search_result&selectedTitle=1~150&usage_type=default&display_rank=1#H23
- Gary Lee Y. Pneumothorax: Definitive management and prevention of recurrence [Internet]. UpToDate. 2021 [cited 2022 Jun 1]. Available from: https://www.uptodate.com/contents/pneumothorax-definitive-management-and-prevention-of-recurrence?search=pneumothorax&source=search_result&selectedTitle=6~150&usage_type=default&display_rank=6#H2851443018
- Gary Lee Y. Treatment of primary spontaneous pneumothorax in adults [Internet]. UpToDate. 2020 [cited 2022 Jun 1]. Available from: https://www.uptodate.com/contents/treatment-of-primary-spontaneous-pneumothorax-in-adults?search=pneumothorax&source=search_result&selectedTitle=4~150&usage_type=default&display_rank=4#H1914656627
- Gary Lee Y. Treatment of secondary spontaneous pneumothorax in adults [Internet]. UpToDate. 2021 [cited 2022 Jun 1]. Available from: https://www.uptodate.com/contents/treatment-of-secondary-spontaneous-pneumothorax-in-adults?search=pneumothorax&source=search_result&selectedTitle=3~150&usage_type=default&display_rank=3#H1
- Husain, Lubna F et al. “Sonographic diagnosis of pneumothorax.” Journal of emergencies, trauma, and shock vol. 5,1 (2012): 76-81. doi:10.4103/0974-2700.93116
- Maskell N. British Thoracic Society pleural disease guidelines – 2010 update. Thorax. 2010;65(8):667–9.
- McKnight CL, Burns B. Pneumothorax. [Updated 2022 May 4]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2022 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK441885/
- Niknejad M. Pneumothorax [Internet]. Radiopedia. 2022 [cited 2022 Jun 1]. Available from: https://radiopaedia.org/articles/pneumothorax?lang=gb#nav_radiographic-features
- Noppen M. Spontaneous pneumothorax: Epidemiology, pathophysiology and cause. Eur Respir Rev. 2010;19(117):217–9.
- Roberts DJ, Leigh-Smith S, Faris PD, Blackmore C, Ball CG, Robertson HL, et al. Clinical presentation of patients with tension pneumothorax: A systematic review. Ann Surg. 2015;261(6):1068–78.
- UpToDate. Evaluation of the adult with chest pain in the emergency department [Internet]. 2022 [cited 2022 Jun 1]. Available from: https://www.uptodate.com/contents/evaluation-of-the-adult-with-chest-pain-in-the-emergency-department?search=chest pain&source=search_result&selectedTitle=3~150&usage_type=default&display_rank=3#H18
- UpToDate. Evaluation of the adult with dyspnea in the emergency department [Internet]. [cited 2022 Jun 1]. Available from: https://www.uptodate.com/contents/evaluation-of-the-adult-with-dyspnea-in-the-emergency-department?search=shortness of breath&source=search_result&selectedTitle=2~150&usage_type=default&display_rank=2#H4
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

