


 Close
 13th February 2025
Diplopia
Overview of diplopia
Diplopia, or double vision, is the separation of images horizontally, vertically or obliquely.
Diplopia can be monocular whereby the abnormality persists when the unaffected eye is closed. This is typically associated with local ocular causes such as refractive error or media abnormalities.
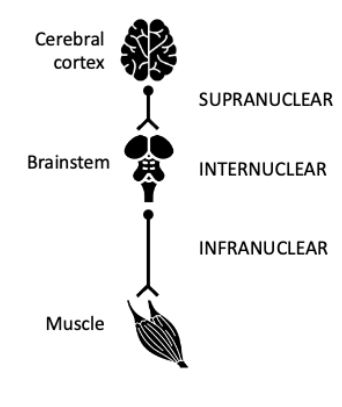
Binocular diplopia is the result of dysfunction of the extraocular muscles which leads to ocular misalignment, preventing fusion of the two images produced by each eye. The aetiology of binocular diplopia can be classified according to the segment of the efferent oculomotor pathway that is involved.
The following will be discussed:
| Location | Example | |||
|---|---|---|---|---|
 |
Supranuclear | Progressive supranuclear palsy | ||
| Nuclear and internuclear | Internuclear ophthalmoplegia | |||
| Infranuclear | Cranial nerves | Third nerve palsy
Fourth nerve palsy Sixth nerve palsy |
||
| Muscles and neuromuscular junction | Myasthenia gravis
Thyroid eye disease Miller Fisher syndrome |
|||
Table 5 Causes of binocular diplopia
Figure adapted from icons through The Noun Project, CC BY 3.0
Cerebral cortex – VectorsLab https://thenounproject.com/icon/brain-4224212/
Brainstem – Tezar tantular https://thenounproject.com/icon/brainstem-3656737/
Muscle – Amethyst Studio https://thenounproject.com/icon/muscle-4666756/
Progressive supranuclear palsy
Progressive supranuclear palsy (PSP) is an uncommon, atypical Parkinsonian disorder characterised by akinesia, postural instability, cognitive decline and ocular dysmotility. The latter typically consists of vertical gaze palsy or slow vertical saccades.
Internuclear ophthalmoplegia
Internuclear ophthalmoplegia (INO) is an ocular movement disorder caused by pathology of the medial longitudinal fasciculus (MLF) within the brainstem. It results in impaired adduction of the ipsilateral eye and nystagmus during abduction of the contralateral eye (Figure 6).
Neuroimaging in the form of an MRI brainstem is useful to identify a lesion. The underlying causes are:
- ⅓: infarction
- ⅓: demyelinating disorder, such as multiple sclerosis
- ⅓: other causes, e.g. trauma, infections, vasculitis
Treatment depends on the underlying cause. Approximately half of all cases of INO will resolve within 1 year.
Important differential diagnoses to consider include myasthenia gravis and sixth nerve palsy.
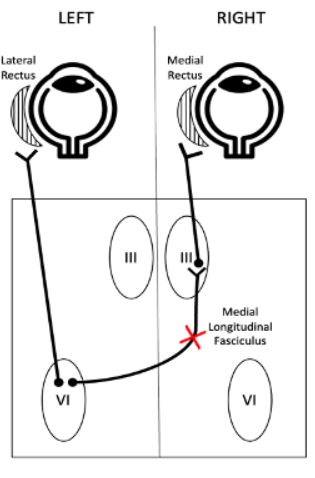
Image Source: Wikimedia Commons (2021). eyeball-4303894, Licensed under a creative commons licence. Available for free at: https://thenounproject.com/icon/eyeball-4303894/ (Accessed: 18 January 2024).
Cranial nerve palsy
| Cranial nerve | Third (oculomotor) | Fourth (trochlear) | Sixth (abducens) |
|---|---|---|---|
| Cause | Intracranial aneurysm: posterior communicating artery most common
Microvascular disease Trauma: significant injury Malignancy |
Congenital
Trauma: can occur following mild injury Microvascular disease: but less commonly affects CN IV compared to III and VI |
Microvascular disease
Malignancy Trauma: significant injury, e.g. basal skull fracture Increased intracranial pressure |
| Symptoms | Horizontal, vertical or oblique diplopia
Pain at the onset of symptoms is common |
Vertical diplopia and/or torsional diplopia which is worse at gaze towards the paretic superior oblique muscle
Head tilt towards the unaffected side reduces diplopia |
Horizontal diplopia which is worse at distance and at gaze towards paretic lateral rectus muscle
Head turned towards the affected side reduces diplopia |
| Examination | 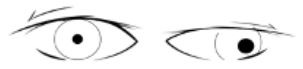
Primary position ipsilateral abduction, depression and intorsion. Fixed dilated pupil and ptosis may also be present if a complete palsy |
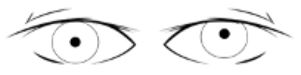
Primary position ipsilateral hypertropia and extorsion, more pronounced in ipsilateral head tilt |
Primary position esotropia with an ipsilateral abduction deficit |
| Prognosis | Most will recover over weeks to months
Lack of pupil involvement suggests a benign cause which can be observed |
Patients are often observed for several months before treatment is considered as symptoms may improve | Majority will recover spontaneously (3-6 months), more common if unilateral and non-traumatic |
Table 6 Summary of cranial nerve palsies
Figures adapted from icons through The Noun Project, CC BY 3.0
Eyes – Alone forever https://thenounproject.com/icon/eye-1436483/
Cranial nerve palsies are often investigated with neuroimaging, ideally MRI, to identify an underlying cause. This is essential in third nerve palsies with pupillary involvement to exclude an underlying intracranial aneurysm.
Management of cranial nerve palsies includes addressing the underlying cause as well as managing symptoms of diplopia with patching, prisms, strabismus surgery and/or botulinum toxin.
Muscular and neuromuscular junction
Myasthenia gravis
Myasthenia gravis (MG) is an autoimmune disease affecting the neuromuscular junctions of skeletal muscles. Pathophysiology includes the presence of autoantibodies to acetylcholine receptors (AChR).
MG typically presents with fatigable weakness and often affects the extraocular muscles. Patients can present with a spectrum of symptom severity from mild blurred vision to variable ptosis to severe diplopia. Examination characteristically reveals a fatigable muscle weakness not confined to a specific muscle or nerve and which is variable and asymmetrical in nature. Importantly, there is no associated eye pain and no pupil involvement. The tongue can also be affected, resulting in atrophy and a rare but distinctive ‘triple-groove’ appearance.
Occasionally, manifestations of MG are limited to the levator palpebrae superioris, orbicularis oculi and extraocular muscles, which is known as ‘ocular MG’. Unlike generalised MG where more females are affected, males are more likely to be affected by ocular MG. Furthermore, patients with ocular MG are more likely to be seronegative for AChR antibodies than those with generalised MG.
Diagnosis can be confirmed through various tests:
| Category | Test | Positive findings |
|---|---|---|
| Clinical | Lid fatigability test | Ptosis increases following prolonged upgaze. |
| Cogan’s lid twitch | Brief overshooting of upper lid retraction on returning to primary gaze after looking in downgaze. | |
| Ice test | Ptosis improves by ≥2 mm following an ice pack placed over the eyelid for 2-5 minutes. Cool temperature results in reduced acetylcholinesterase (AChE) activity. | |
| Pharmacological | Tensilon test (a.k.a. edrophonium test) | Improvement in clinical signs 1 minute after injection of IV edrophonium, a rapid-acting AChE.
Serious side effects include bradycardia and syncope, therefore atropine should be available during testing. Notably, up to 25% of patients with ocular MG may experience a paradoxical worsening of symptoms due to a depolarising block caused by excess ACh (acetylcholine). |
| Electrophysiological | Repetitive nerve stimulation | The number of individual muscle fibre action potentials and the amplitude of action potentials reduce with repeated electrical stimulation of the nerve. |
| Single fibre electromyography | Neuromuscular ‘jitter’ is recorded, which represents fluctuations in the time for end plate potentials at neuromuscular junctions to reach the threshold to produce an action potential.
More sensitive for MG than repetitive nerve stimulation. |
Table 7 Investigations to confirm a diagnosis of myasthenia gravis
Treatment with AChE inhibitors, such as pyridostigmine, improves symptoms but does not alter disease activity. Tapering courses of corticosteroids and immunosuppressants, such as azathioprine, are also used.
Thyroid eye disease
Thyroid eye disease is an autoimmune disorder. It is most commonly associated with thyrotoxicosis secondary to Graves’ disease and occurs due to shared autoantigens between the thyroid and the orbit. However, rarely, the patient can be euthyroid or hypothyroid. Common symptoms include altered periocular appearance, eye surface discomfort or lacrimation and diplopia at extremes of gaze. Diplopia occurs due to inflamed extraocular muscles and connective tissues and affects the inferior rectus, medial rectus and superior rectus in that order. The diplopia is worse in the direction opposite the affected muscle. Hence, hypertropia occurs if the inferior rectus is affected.
Diagnosis can be made clinically, but if required CT or MRI are the most valuable tests. Imaging demonstrates enlarged extraocular muscles with tendon sparing.
Management options include:
- Conservative: controlling exacerbating factors, e.g. smoking cessation, correction of thyroid dysfunction, lubricants, prisms
- Medical: steroids
- Surgical: orbital decompression
The natural course of thyroid eye disease is progression for 1-2 years, followed by a stable chronic phase. Complications include corneal ulceration precipitated by impaired eyelid closure and optic nerve compression.
Differential diagnoses include myasthenia gravis, allergic conjunctivitis and orbital tumours.
Miller Fisher syndrome
Guillain-Barré syndrome is an acute inflammatory demyelinating polyneuropathy which can affect extraocular muscles, when it is known as Miller Fisher syndrome (MFS). It is characterised by a triad of ophthalmoplegia, ataxia and areflexia. Approximately 85-90% of patients are positive for GQ1b antibodies. Pathophysiology includes a T-cell-mediated inflammatory response and destruction of myelin.
References
- Bienfang DC. Overview of diplopia. In: Brazis PW, Wilterdink JL, editors. UpToDate. [Internet]. Waltham (MA): UpToDate Inc; 2021 [updated September 9 2021; cited May 3 2023]. Available from: https://www.uptodate.com/contents/overview-of-diplopia
- Suleiman AO. Basic Approach to Diplopia. American Academy of Ophthalmology, EyeWiki. [Internet]. February 2023 [cited May 3 2023]. Available from: https://eyewiki.aao.org/w/index.php?title=Basic_Approach_to_Diplopia&oldid=89879
- Factor SA, Esper CD. Progressive Supranuclear Palsy (PSP). In: Hurtig HI, Eichler AF, editors. UpToDate. [Internet]. Waltham (MA): UpToDate Inc; 2022 [cited May 12 2023]. Available from:
- https://www.uptodate.com/contents/progressive-supranuclear-palsy-psp-clinical-features-and-diagnosis
- Feroze KB, Wang J. Internuclear Ophthalmoplegia. [Updated 2022 Jun 27]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2023 Jan. Available from: https://www.ncbi.nlm.nih.gov/books/NBK441970/
- Nair AG, Patil-Chhablani P, Venkatramani DV, Gandhi RA. Ocular myasthenia gravis: a review. Indian J Ophthalmol. 2014 Oct;62(10):985-91. doi: 10.4103/0301-4738.145987. PMID: 25449931; PMCID: PMC4278125.
- Perros P, Neoh C, Dickinson J. Thyroid eye disease. Bmj. 2009 Mar 6;338.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

