


 Close
 4th May 2025
Cardiac Arrhythmias
Supraventricular Tachycardia
The term Supraventricular Tachycardia (SVT) refers to any tachycardia that is not ventricular in origin. SVT is an umbrella term which includes Atrioventricular Nodal Reentry Tachycardia (AVNRT) and Atrioventricular Reentry Tachycardia (AVRT). AVNRT is used synonymously with the term SVT.
Atrioventricular Nodal Reentry Tachycardia (AVNRT)
AVNRT typically occurs in younger people. It is usually paroxysmal and may occur spontaneously. It may have a trigger such as alcohol intoxication, nicotine, stress, concurrent illness, caffeine or stimulants such as amphetamines.
Brief pathophysiology of ‘Slow-Fast AVNRT’
AVNRT results from having dual AV nodal pathways within the AV node itself. There is a fast pathway which conducts rapidly but has a long refractory period, and there is a slow pathway which conducts slowly but a short refractory period. During normal sinus rhythm, electrical impulses travel down both pathways simultaneously and cancel each other out.
However, a premature atrial contraction disrupts this as while the fast pathway is still in a refractory period, electrical impulses would then have to solely travel down the slow pathway as it is no longer in refractory period. By the time the premature impulses reach the distal end of the slow pathway, the fast pathway is no longer in a refractory period which allows impulses to travel retrogradely up the fast pathway.
Hence, a ‘re-entrant’ circuit is created as impulses are now continuously cycling around both pathways activating the bundle of His anterogradely and the atria retrogradely.
Clinical manifestations
Symptoms arise from the tachycardia generated and they include:
- Palpitations
- Chest pain
- Light-headedness or dizziness
- Syncope or presyncope
- Breathlessness
- Anxiety
ECG features
- P waves hidden within QRS complexes
- Late P waves resulting in Pseudo R wave/second R wave
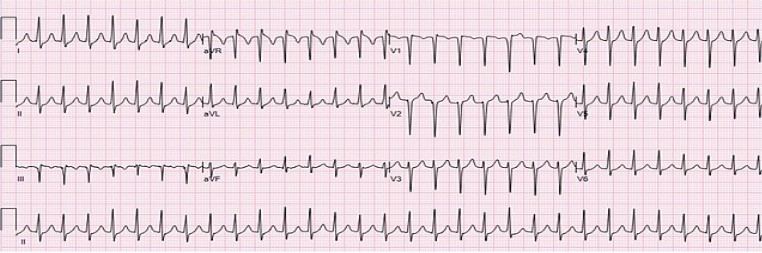
Image Source: Wikimedia Commons (2020), ECG AVNRT, Licenced under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:ECG_AVNRT_181_bpm.jpg (Accessed: 1 May 2025).
Medical management
The principle in managing AVNRT is inhibiting AV nodal activity as this is the driver for the tachycardia. This can be achieved via vagal manoeuvres and medication. Vagal manoeuvres work by increasing vagal parasympathetic tone. DCCV is rarely required unless the patient is haemodynamically unstable or refractory to medical cardioversion.
1st line therapy: Vagal manoeuvres:
- Blowing into an empty 10ml syringe
- Carotid sinus massage (contraindicated in carotid disease due to the risk of stroke)
- Modified Valsalva Manoeuvre: head down, legs up
2nd line therapy: Adenosine
- This is given IV 6mg, then 12mg and then followed by 18mg
- Contraindicated in asthma due to bronchoconstriction
- Safe to give in pregnancy as does not significantly cross the placenta
- Dipyridamole enhances the effect of adenosine, whereas Theophylline is a potent adenosine receptor antagonist
3rd line therapy: Beta blockers or Calcium channel blockers
- IV Metoprolol or Verapamil
- If 3rd line treatment ineffective, DCCV should be attempted with appropriate sedation and anaesthetic support
Accessory Pathways
Background
Wolff-Parkinson-White (WPW) Syndrome is caused by an accessory conduction pathway between the atria and the ventricles leading to an atrioventricular reentry tachycardia (AVRT). This accessory pathway is also called the bundle of Kent which allows electrical impulses generated by the Sino-atrial node to bypass the AV node. This accessory pathway allows electrical impulses to be conducted quicker than the AV node, resulting in a shorter PR interval which brings about the characteristic Delta wave seen in ECGS. WPW has an incidence of 0.1-0.3 per 1000.
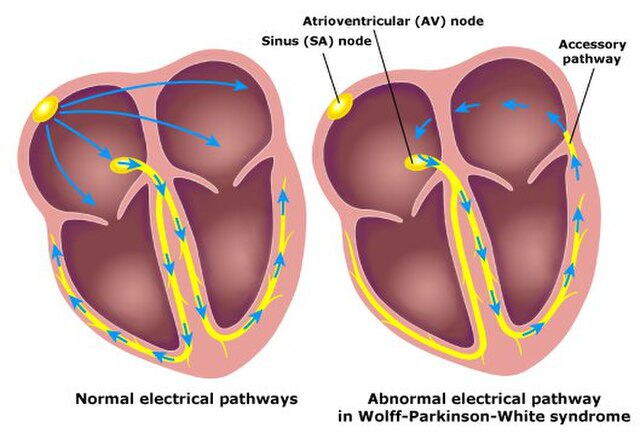
Image Source: Wikimedia Commons (2011). Wolf, Parkinson and White. Licenced under a creative commons licence. Available for free at: https://commons.wikimedia.org/w/index.php?search=wolf+parkinson+white&title=Special:MediaSearch&go=Go&type=image (Accessed: 1 May 2025).
Associations with WPW syndrome
- Hypertrophic Cardiomyopathy (HCM)
- Mitral valve prolapse
- Ebstein’s Anomaly
Clinical manifestations
Most patients who present with an arrhythmia will present with one or more of the following symptoms:
- Palpitations
- Chest pain
- Light-headedness or dizziness
- Syncope or presyncope
- Sudden cardiac death
ECG features in WPW
- Short PR interval <120ms
- Slurred upstroke of a wide QRS complex – ‘delta wave’
- Prolonged QRS >110ms
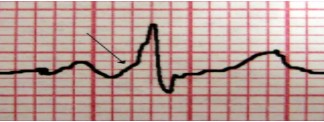
Image Source: Wikimedia Commons (2020). Delta Wave, Licensed under a creative commons licence. Available for free at: https://upload.wikimedia.org/wikipedia/commons/thumb/e/e9/DeltaWave09.JPG/640px- DeltaWave09.JPG (Accessed: 1 May 2025).
Arrhythmias associated with WPW
Atrial Fibrillation is seen in about 10-30% of patients with WPW syndrome. The presence of an accessory pathway in WPW allows the rapid conduction of atria signals to the ventricles as it bypasses the AV node. This results in rapid ventricular rates that may result in VT or VF.
Medical management
The general principle in managing patients with WPW is to prevent electrical impulses from travelling through the accessory pathway. Hence any AV nodal blocking drugs such as Adenosine, Beta blockers and Calcium channel blockers are contraindicated as blocking the AV node will allow uncontrolled electrical impulses down the accessory pathway potentially leading to VT/VF and cardiac arrest.
Drugs used to treat WPW include
- Flecainide (In the absence of structural heart disease)
- Amiodarone
- Procainamide
Surgical management
Definitive treatment options include Catheter ablation or Surgical ablation. Efficacy of catheter- based ablation is around 85%to 95% but this is mainly dependent on the location of the accessory pathway.
Wide QRS Complex Tachycardias
Ventricular Tachycardia
Background
Ventricular tachycardia (VT) is a broad complex tachycardia originating from the ventricles. It is also defined by having a cardiac rhythm with a rate >100bpm and a QRS width >120ms.
VT occurs as there are regions of slowed conduction in the ventricle allowing the opportunity to develop reentrant arrhythmias. This process can be caused by any structural abnormality in the ventricle. In post myocardial infarction patients, ventricular scars from infarction or fibrosis provide a substrate for this process.
Risk factors for developing Monomorphic VT
- Coronary ischaemic heart disease (especially prior MI)
- Hypertrophic cardiomyopathy
- Dilated cardiomyopathy
- Arrhythmogenic right ventricular cardiomyopathy
ECG features
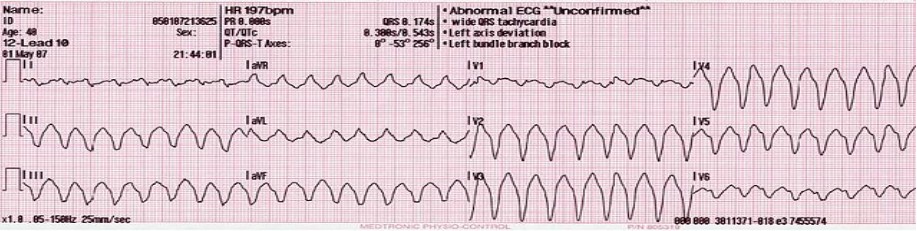
Image Source: Wikimedia Commons (2020). Lead Generated Ventricular Tachycardia, Licensed under a creative commons licence. Available for free at: https://upload.wikimedia.org/wikipedia/commons/thumb/4/45/12_lead_generated_ventricular_tachycardia.JPG/640px-12_lead_generated_ventricular_tachycardia.JPG (Accessed 1 May 2025).
Features suggestive of VT rather than SVT with aberrancy
- RSR’ complexes with a taller “left rabbit ear”
- Very broad QRS complex >160ms
- AV dissociation
- Positive or negative concordance in precordial leads
- Fusion or capture beats
- Marked left axis deviation
- Absence of typical RBBB or LBBB morphology
Even with the use of algorithms, differentiating VT vs SVT with aberrancy can still be challenging. Therefore, in an emergency, broad complex tachycardias are to be treated as ventricular in origin.
* Verapamil should NOT be given in a broad complex Tachycardia, as it may precipitate Ventricular Fibrillation in patients with VT * As this may precipitate electrical impulses travelling down an aberrant pathway in SVT’s with a bundle branch block.
Medical management
Unstable patients
- Synchronised DCCV
Stable patients
- Amiodarone
- Lidocaine
- Procainamide
Polymorphic VT
Background
Polymorphic VT is defined as an unstable rhythm with a continuously varying QRS complex morphology. A subtype of polymorphic VT is Torsades de Pointes (Twisting of the points) and is often precipitated by prolongation of the QT interval. Torsades de Pointes if left untreated can lead to Ventricular fibrillation.
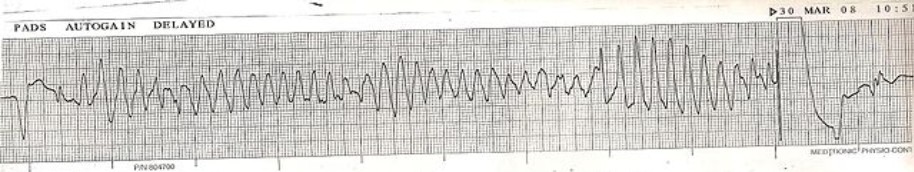
Image Source: Wikimedia Commons (2011). Torsades converted by AICD ECG Strip Lead, Licensed under a creative commons licence. Available for free at: https://upload.wikimedia.org/wikipedia/commons/thumb/e/ed/Torsades_converted_by_AICD_ECG_strip_Lead_II.JPG/640px-Torsades_converted_by_AICD_ECG_strip_Lead_II.JPG (Accessed: 1 May 2025).
Causes of Long QT interval
Congenital
- Jervell-Lange-Nielsen syndrome (deafness)
- Romano-Ward syndrome (no deafness)
- Long QT syndrome
Drugs
- Sotalol, Amiodarone
- SSRIs (Citalopram)
- Tricyclic antidepressants (Amitriptyline)
- Antipsychotics (Haloperidol, Quetiapine, Risperidone)
- Azithromycin
- Ondansetron
- Methadone
Other
- Subarachnoid haemorrhage
- Hypokalaemia
- Hypomagnesaemia
- Hypocalcaemia
- MI
- Myocarditis
Medical management
- Unstable patients (haemodynamic compromise) need urgent shocking as for patients with monomorphic VT
- Pharmacological management is the same as that of monomorphic VT
- Correct underlying cause
- IV Magnesium Sulphate
Ventricular Fibrillation
VF is defined as rapid disorganised ventricular activity. This results in no uniform ventricular contractions and as a result leads to loss of cardiac output.
ECG shows a rapid ventricular rate of 300-400bpm. Over time, the amplitude of these irregular deflections decreases. (Coarse VF to fine VF).
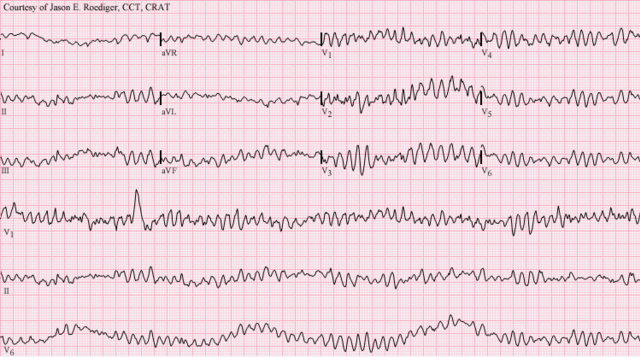
Image Source: Wikimedia Commons (2020). Ventricular Fibrillation, Licensed under a creative commons licence. Available for free at: https://upload.wikimedia.org/wikipedia/commons/thumb/f/f1/Ventricular_fibrillation.png/640px-Ventricular_fibrillation.png (Accessed 1 May 2025).
Management
- Prompt defibrillation
- Reversal of underlying cause * Tricyclic Antidepressant overdose is treated with Sodium Bicarbonate solution*
Cardiac Arrest
In cardiac arrest situations, following a systematic approach is crucial. Resuscitation council UK has given clear Advanced Life Support guidelines in cardiac arrest situations.
Once VF/Pulseless VT is identified on the monitor, the treatment would be delivering an immediate shock of 150-200J for the first shock. After 3 shocks via the defibrillator, Amiodarone 300mg IV and Adrenaline 1mg IV is given alongside cardio-pulmonary resuscitation.
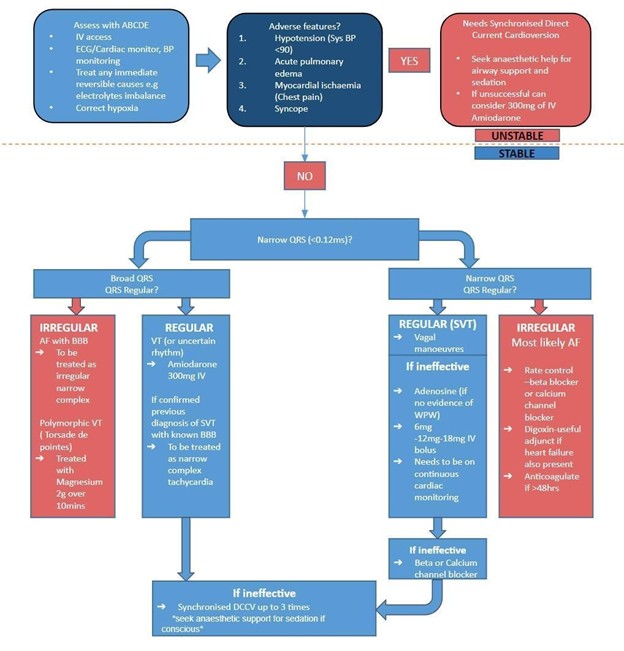
Tachyarrhythmia algorithm *(adapted from Resus UK ALS algorithm 2021)*
References
- https://www.uptodate.com/contents/wolff-parkinson-white-syndrome-anatomy-epidemiology-clinical-manifestations-and-diagnosis?search=wpw&source=search_result&selectedTitle=1~132&usage_type=default&display_rank=1
- https://www.uptodate.com/contents/treatment-of-arrhythmias-associated-with-the-wolff-parkinson-white-syndrome?search=wpw&source=search_result&selectedTitle=2~132&usage_type=default&display_rank=2
- https://www.uptodate.com/contents/atrioventricular-nodal-reentrant-tachycardia?search=avnrt&source=search_result&selectedTitle=1~73&usage_type=default&display_rank=1
- https://bnf.nice.org.uk/treatment-summaries/arrhythmias/#ventricular-tachycardia
- https://www.uptodate.com/contents/sustained-monomorphic-ventricular-tachycardia-in-patients-with-structural-heart-disease-treatment-and-prognosis?search=vt&source=search_result&selectedTitle=2~150&usage_type=default&display_rank=2
- https://www.uptodate.com/contents/sustained-monomorphic-ventricular-tachycardia-clinical-manifestations-diagnosis-and-evaluation?search=vt&source=search_result&selectedTitle=4~150&usage_type=default&display_rank=4
- https://bestpractice.bmj.com/topics/en-gb/409/treatment-algorithm
- https://bestpractice.bmj.com/topics/en-gb/537
- https://bestpractice.bmj.com/topics/en-gb/400
- https://www.uptodate.com/contents/ventricular-arrhythmias-during-acute-myocardial-infarction-incidence-mechanisms-and-clinical-features?search=vf&source=search_result&selectedTitle=1~150&usage_type=default&display_rank=1
- https://lms.resus.org.uk/modules/m25-v2-als-algorithm/11118/resources/chapter_6.pdf
- https://www.resus.org.uk/sites/default/files/2021-04/Tachycardia%20Algorithm%202021.pdf
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

