


 Close
 7th May 2025
Congenital Heart Disease
Congenital Heart Disease
Introduction
Although somewhat rare, congenital heart disease (CHD) represents the commonest congenital disability, occurring in 0.8% of all live births. Detection rates remain low, despite antenatal and post-natal screening processes. However, early recognition of CHD is imperative, as it can often present with a sudden clinical deterioration and even death before an established diagnosis is given. Despite this, much progress has been made over the past 50 years in these conditions’ medical and surgical management. Let us first review the normal anatomy and physiology of the foetal circulatory system.
Normal Foetal Circulatory System
To understand CHD, it is important first to appreciate the typical foetal circulatory system. In pregnancy, foetal gaseous exchange occurs within the placenta, not the lungs. Therefore, the placenta receives deoxygenated blood from the foetus via the umbilical arteries and returns oxygenated blood via the umbilical veins. The circulatory system is designed to preferentially ensure the delivery of richly oxygenated blood to the foetal myocardium and brain. This is achieved through “shunts”, i.e., a passage that allows blood movement from the arterial and venous circulation. Therefore, the foetal circulatory system is a “shunt-dependent system”. The key features of the circulatory system are described in Table One. The flow of blood in the foetal circulatory system can be appreciated.
| Feature | Overview |
|---|---|
| Umbilical Vein | Provides oxygenated blood from the placenta to the foetus |
| Umbilical Artery | Transports deoxygenated blood from the foetus to the placenta |
| Ductus venosus | Allows oxygenated blood to bypass the foetal liver
Shunts blood from the umbilical vein to the inferior vena cava |
| Ductus Arteriosus | Allows oxygenated blood to bypass the foetal lungs
Shunts blood from the pulmonary artery to the aorta |
| Foramen Ovale | Allows oxygenated blood to bypass the foetal lungs
Shunts blood from the right atrium to the left atrium |
Table 1: This table identifies the key features unique to the foetal circulatory system. Sourced and adapted from Haeffner, Fetal Circulation: TeachMePhysiology; 2022.
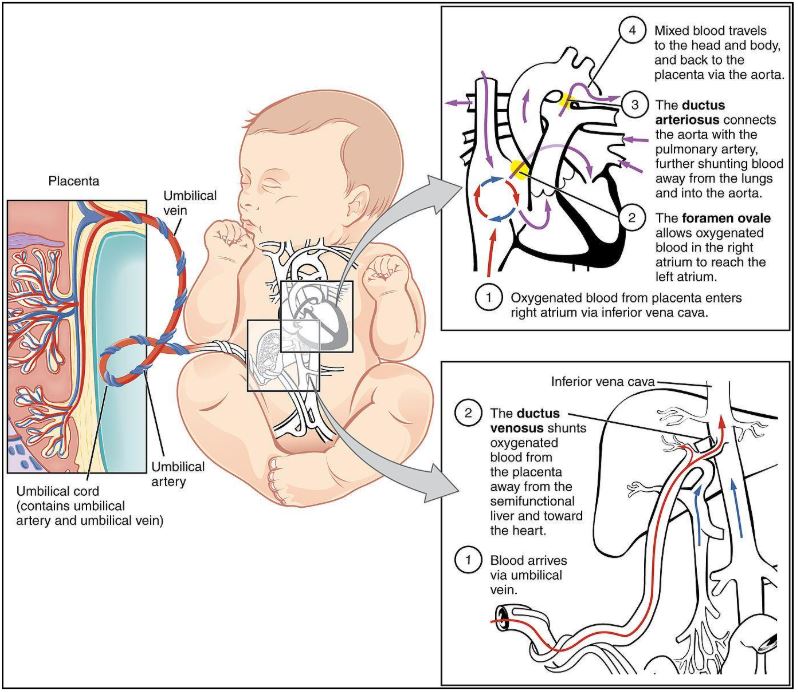
Image Source: Wikimedia Commons (2008). Foetal Circulatory System. Licensed under a creative commons licence. Available for free at: https://en.wikipedia.org/wiki/Fetal_circulation#/media/File:2916_Fetal_Circulatory_System-02.jpg (Accessed 16 June 2025).
CHD Classification
There are a variety of classification systems that exist to categorise CHD. This resource has utilised the classification of left-to-right shunt, right-to-left shunt, and obstructive valvular and non-valvular lesions.
Left-to-right Shunt
In CHD with a left-to-right shunt, there is anomalous blood flow from the systemic arterial circulation (“left side”) to the deoxygenated pulmonary circulation (“right side”) via an abnormal connection. These are often referred to as acyanotic lesions, as there is adequate blood oxygenation, but it is abnormally pumped through the body.
Examples include atrial septal defect, ventricular septal defect, atrioventricular septal defect, patent ductus arteriosus and partial anomalous pulmonary venous connection.
Right-to-Left Shunt
In CHD with a right-to-left shunt, there is blood flow from the deoxygenated pulmonary circulation (“right side”) to the systemic arterial circulation (“left side”). These are called cyanotic lesions, resulting from suboptimal blood flow and oxygenation in the pulmonary circulation. This causes reduced oxygenation of the systemic arterial blood.
Examples include tetralogy of Fallot, pulmonary valve atresia with or without a VSD, truncus arteriosus, Ebstein’s anomaly, hypoplastic left heart syndrome, and d-Transposition of the great arteries.
Obstructive valvular and non-valvular lesions
This term refers to a lesion resulting in obstruction, which impedes blood flow and causes a pressure gradient across the obstruction. These are also often acyanotic, in that blood oxygenation is not impacted, but the flow is. These can be due to a heart valve defect (valvular) or narrowing in the circulatory system (non-valvular).
Examples include coarctation of the aorta, aortic valve stenosis, pulmonary stenosis and left ventricular outflow tract obstruction.
Left-to-Right Shunt
Atrial Septal Defect
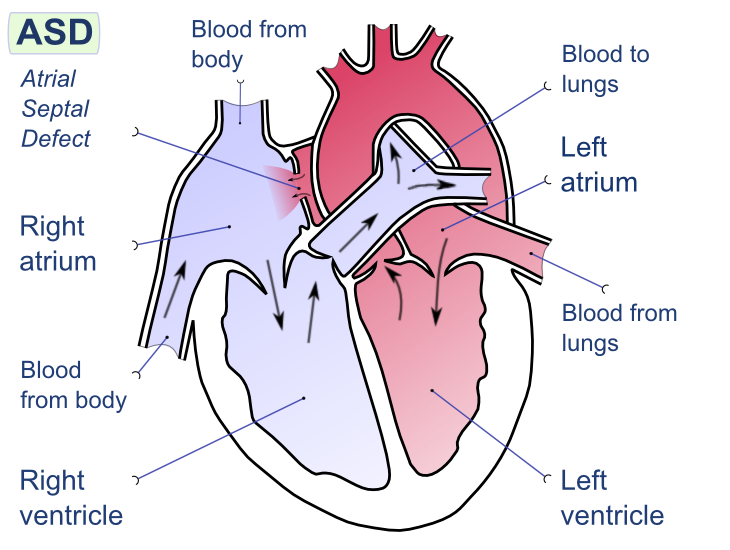
Image Source: Wikimedia Commons (2008). Atrial Septal Defect, Licensed under a creative commons licence. Available for free at:
https://upload.wikimedia.org/wikipedia/commons/9/92/Atrial_septal_defect-en.png?20080221094223 (Accessed 2 May 2025).
Atrial septal defects (ASD) refer to an intra-arterial connection that often results from the incomplete separation of the right and left atrium during foetal development. The result is a shunt between the two atria. The key features can be seen in Table Two. There are five types of ASD, from most common to least, they are patent foramen ovale, ostium secundum defect, ostium primum defect, sinus venous defect and coronary sinus defect.
| Feature | Summary |
|---|---|
| Epidemiology | 1 to 2 per 1000 live births
Most common CHD in adults |
| Aetiology | Most occur sporadically, with no prior family history
Associated with some genetic syndromes, e.g. Noonan, trisomy 21 More likely in females than males. |
| Classification |
|
| Clinical History | Adults can be asymptomatic
Often symptomatic after 4th decade: palpitations, dizziness (an atrial arrhythmia), shortness of breath, dyspnoea, fatigue, reduced exercise tolerance |
| Clinical Examination | Dependent on the size of the ASD
Most common:
Uncommon:
|
| Diagnostic Investigations | Echocardiogram: allows direct visualisation of the ASD
ECG: typically normal in small ASD but tall P waves and large R waves in V1 (moderate to severe) Chest X-ray: normal if small ASD, possible cardiomegaly (moderate to severe) |
| Management | Dependent on the calculation of the ratio of pulmonary vascular to systemic blood flow (Qp:Qs)
Qp:Qs <1.5 – observation, may resolve spontaneously Qp:Qs ≥ 1.5 or enlargement of the right atrium – corrective surgical or transcatheter closure Pulmonary Vascular Resistance >5
|
| Follow Up | For small ASD, observation should include signs of arrhythmias.
If there is no evidence of pulmonary vascular obstructive disease, there is an excellent prognosis. The older the age of the patient at the point of repair, the increased risk of adverse events. |
Table 2: The above table details the key areas regarding atrial septal defects. Sourced and adapted from Haller, Intra-atrial Communications (Atrial Septal Defects): BMJ Best Practice; 2023.
Eisenmenger Syndrome
This rare syndrome results from a congenital heart defect and a large shunt, which impacts both the heart and lungs. Initially, there is an acyanotic left-to-right shunt, which leads to increased vascular resistance and severe pulmonary arterial hypertension. Over time, the increased pulmonary resistance eventually reverses the blood flow, resulting in a cyanotic right-to-left shunt. A summary of the key features is detailed in Table Three.
| Feature | Summary |
|---|---|
| Epidemiology | A rare condition typically presents in areas with poor access to healthcare resulting in late presentation. |
| Aetiology | It can develop from any CHD where pulmonary arterial hypertension results. For example, ASD, ventricular septal defects, patent ductus arteriosus, and unrepaired tetralogy of Fallot. |
| Clinical History | A patient with known CHD presenting with worsening exertional dyspnoea
Other symptoms can include palpitations, haemoptysis, syncope, progressive cyanosis and swelling. Also, due to chronic hypoxaemia, the patient can develop symptoms related to polycythaemia. These include headache, dizziness, stroke and visual changes. |
| Clinical Examination | Signs of pulmonary hypertension
Signs related to the underlying CHD
Signs of right-to-left shunt and chronic hypoxaemia
|
| Diagnostic Investigations | Echocardiogram
ECG Chest X-ray Bloods, including full blood count and iron studies |
| Management | The ideal management is preventative, i.e. correcting the potentially causative CHD prior to the development of Eisenmenger syndrome.
Once Eisenmenger syndrome has developed, reversal of the high pulmonary arterial pressure is not possible, and a cardiopulmonary transplant is needed. This is not always possible and is associated with high mortality. Supportive treatment options can include:
|
| Follow Up | Patients with Eisenmenger have a reduced life expectancy and high mortality in the 3rd/4th decade of life.
The most common cause of death is stroke, haemoptysis, ventricular failure and pregnancy complications. Management is required from a multidisciplinary team, including cardiologists. |
Table 3: This table describes the key areas of Eisenmenger Syndrome. Sourced and adapted from Basit et al, Eisenmenger Syndrome: StatPearls Publishing; 2023 and Watchman, Eisenmenger Syndrome: Zero to Finals; 2019.
Ventricular Septal Defects
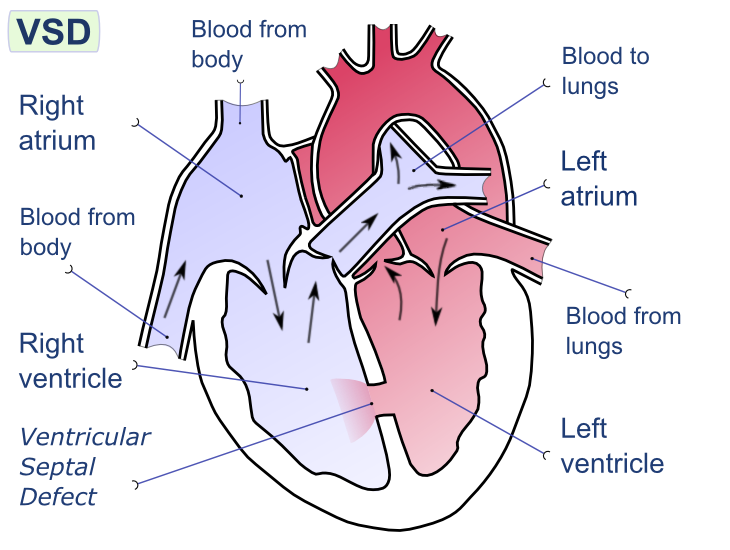
Image Source: Wikimedia Commons (2008). Ventricular Septal Defect, Licensed under a creative commons licence. Available for free at:
https://upload.wikimedia.org/wikipedia/commons/e/e1/Ventricular_septal_defect-en.png?20080222192725 (Accessed 2 May 2025).
Ventricular Septal Defects (VSD) are often congenital abnormalities in the development of the interventricular septum. These anomalies result in an abnormal conduit between the left and right ventricles, which results in an often acyanotic left-to-right shunt. It is important to note that an untreated VSD can result in Eisenmenger syndrome, which results in a cyanotic right-to-left shunt. The key details of VSD are detailed in Table Four.
| Feature | Summary |
|---|---|
| Epidemiology | The most common CHD in infants and children
Isolated VSD occurs in 3.5 per 1000 live births but often close spontaneously. VSD can accompany other congenital defects, not just in isolation Acquired VSD secondary to trauma or myocardial infarction is rare Unusual for VSD to present in adults. |
| Aetiology | Multiple classification systems exist, but the easiest is to think of them as congenital vs acquired.
Congenital
Acquired
|
| Clinical History | Failure to thrive in infancy
Shortness of breath on exertion Risk factors: Maternal alcohol use in pregnancy, Down’s syndrome, family history of CHD Repeated pulmonary infections: in shunt reversal associated with large defects |
| Clinical Examination | Holosystolic Systolic Murmur
Loud pulmonary component of the second heart sound
|
| Diagnostic Investigations | Echocardiogram – to visualise the VSD and confirmation of the left-to-right shunt.
Chest x-ray – may be normal or show cardiomegaly. ECG – dependent on the size of the VSD, not diagnostic but supportive. In medium VSD can show signs of left ventricular hypertrophy. |
| Management | Once a diagnosis has been made utilising an echocardiogram, the pulmonary-systemic blood flow ratio (Qp:Qs) is calculated.
Prophylactic antibiotics should be considered in all VSDs to prevent endocarditis. Congenital Small VSD (Qp:Qs <1) – monitoring and observation, they may spontaneously close. Medium/Large VSD (Qp:Qs ≥1.5)
Acquired Surgical repair |
| Follow Up | Annual follow-up of asymptomatic patients to monitor for development of complications.
Patients who have corrective closure require monitoring for the development of heart block or arrhythmia. Potential complications include aortic regurgitation, heart block, arrhythmia and infective endocarditis. The prognosis is dependent on the size of the VSD.
|
Table 4: This table describes the key features of ventricular septal defects. Sourced and adapted from Aggarwal, Ventricular septal defects: BMJ Best Practice; 2022.
Patent Ductus Arteriosus
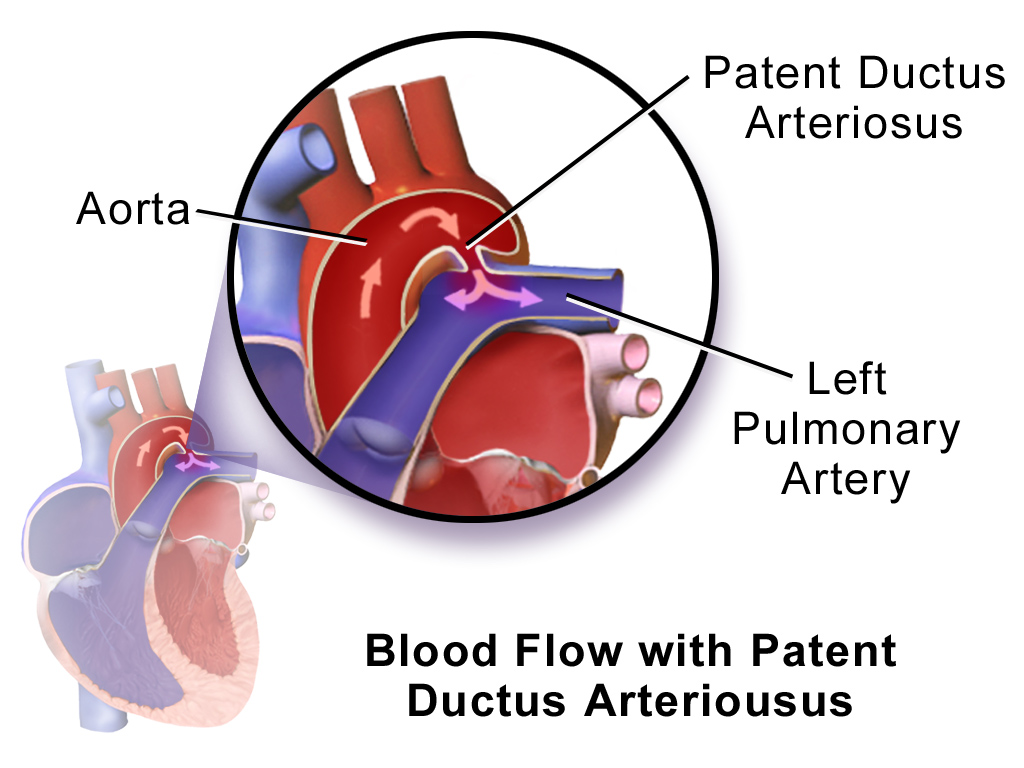
Image Source: Wikimedia Commons (2014). Blausen 0707 Patent Ductus Arteriousus, Licensed under a creative commons licence. Available for free at:
https://upload.wikimedia.org/wikipedia/commons/a/a0/Blausen_0707_PatentDuctusArteriosus.png?20140528155004 (Accessed 2 May 2025).
Patent Ductus Arteriosus (PDA) refers to the persistence of the ductus arteriosus after the first 48 hours of life. The ductus arteriosus is a foetal vascular structure that allows blood passage from the pulmonary artery to the aorta in utero, thus bypassing the foetal lungs. Therefore, PDA describes the CHD where the ductus arteriosus fails to close postnatally, allowing blood to flow from the aorta to the pulmonary artery. This is down a pressure gradient. The details of PDA are summarised in Table Five.
| Feature | Summary |
|---|---|
| Epidemiology | Incidence of 3-8 per 10,000 live births
2:1 female-to-male ratio May be present with other congenital heart defects It can present in some genetic syndromes, e.g. Noonan, Downs, DiGeorge |
| Aetiology | In utero, patency is maintained by hypoxaemia and circulating prostaglandins (PGE2 and PG12).
In the post-natal period, increased oxygen saturations and reduced circulating prostaglandin secondary to placental loss result in the closure of the ductus. The pathology of PDA is due to the left-to-right shunting of blood from the aorta to the pulmonary artery. |
| Clinical History | This varies depending on the age of the initial presentation and the size of the PDA.
An older child or adult can present with shortness of breath and exercise intolerance. |
| Clinical Examination | Small PDA
Moderate PDA
Large PDA
|
| Diagnostic Investigations | Echocardiogram – visualisation of the defect and shunt.
Chest X-ray – normal if PDA is small, slight cardiomegaly if moderate, left heart enlargement if large. Ecg – normal if PDA is small, biventricular hypertrophy and left atrial anomaly if large. |
| Management | In adults, closure is often warranted if there is sizeable left-to-right shunting and/or pulmonary arterial hypertension. Often percutaneous closure is utilised with prophylactic antibiotics for six months. However, closure is contraindicated if the pulmonary vascular resistance is too high. In some cases, surgical ligation is used in larger PDAs. |
| Follow Up | Patient monitoring is required until the definitive closure of the PDA is attained. There are several complications which include congestive cardiac failure, pulmonary hypertension, and endarteritis. |
Table 5: This table details the main features of patent ductus arteriosus. Sourced and adapted from Johnson et al. Patent Ductus Arteriosus: BMJ Best Practice 2022 and Doyle et al. Clinical manifestations and diagnosis of patent ductus arteriosus (PDA) in term infants, children, and adults.: UpToDate; 2022.
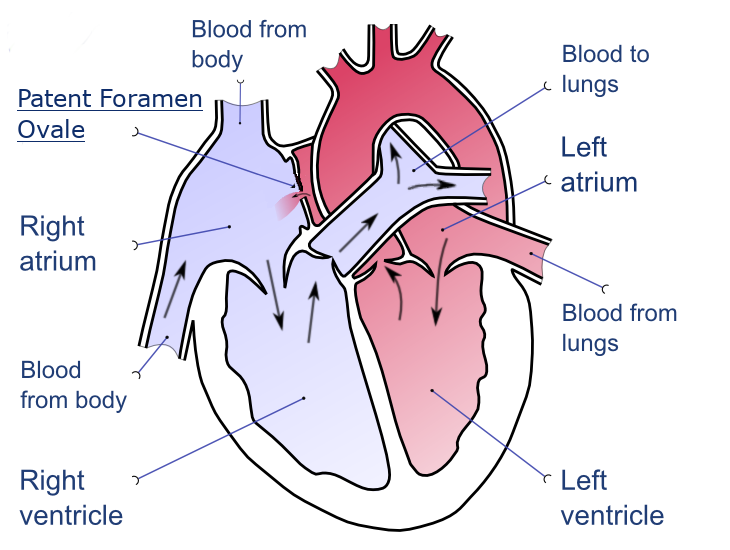
Image Source: Wikimedia Commons (2020). Patent Foramen Ovale, Licensed under a creative commons licence. Available for free at: https://upload.wikimedia.org/wikipedia/commons/0/0a/Patent-foramen-ovale-en.png?20201209214228 (Accessed 2 May 2025).
Patent Foramen Ovale (PFO) is a CHD in which the foramen ovale, located within the atrial septum, remains open into adulthood. Typically, in those without PFO, the foramen ovale closes due to raised left atrial pressure during the first breath after birth. PFO is often asymptomatic but can cause a cerebrovascular accident due to paradoxical embolism, i.e., venous to arterial transit of emboli. The key summary of PFO can be reviewed in Table Six.
| Feature | Summary |
|---|---|
| Epidemiology | Present in around 10% of patients having contrast echo. The incidence of PFO declines with age, suggesting that spontaneous closure can result in adulthood. |
| Aetiology | Idiopathic |
| Clinical History/Examination | Most patients are asymptomatic. However, one should exclude PFO in those under sixty and presenting with a cryptogenic stroke, sudden onset pain and coldness in any limb, transient ischaemic attack and where no obvious embolic source is identified.
Risk factors include atrial septal aneurysms and congenital heart defects. |
| Clinical Examination | In some instances, second heart sound splitting and a systolic murmur are noted on auscultation. |
| Diagnostic Investigations | A transthoracic echo with contrast and colour Doppler is used to visualise the passage of microbubbles from the right atrium into the left atrium. This is often when there is low clinical suspicion of PFO.
A trans-oesophageal echo with contrast and colour Doppler is used when a definitive diagnosis is required. |
| Management | If the individual is asymptomatic, then observation is often the main treatment. However, is it best to think of patients categories as per below:
Asymptomatic
Cryptogenic stroke or transient ischaemic attack Patient selection based on a MDT approach involving neurology and cardiology
High-risk professions, e.g. astronauts, pilots and deep-sea divers
|
| Follow Up | In small PFOs which are asymptomatic, then no long-term follow-up is required. In those with TIA or CVA, routine follow-up is required. A 6-month echo is required in patients who have undergone a percutaneous closure to confirm sufficient closure and rationalisation of antiplatelet treatment.
Prognosis is variable, dependent on the category of patient. In most, however, PFO is not correlated with a higher risk of death or stroke if medically treated. In those with CVA and/or TIA, the risk of a reoccurrence of CVA and/or TIA is 3x higher in PFO, and this increases to 6x higher in those with a concurrent atrial septal aneurysm. |
Table 6: This table provides an overview of patent foramen ovale. Sourced and adapted from Aggarwal, Patent Foramen Ovale: BMJ Best Practice 2022 and Hara, Patent Foramen Ovale: UpToDate; 2022.
Right-to-Left Shunt
Tetralogy of Fallot
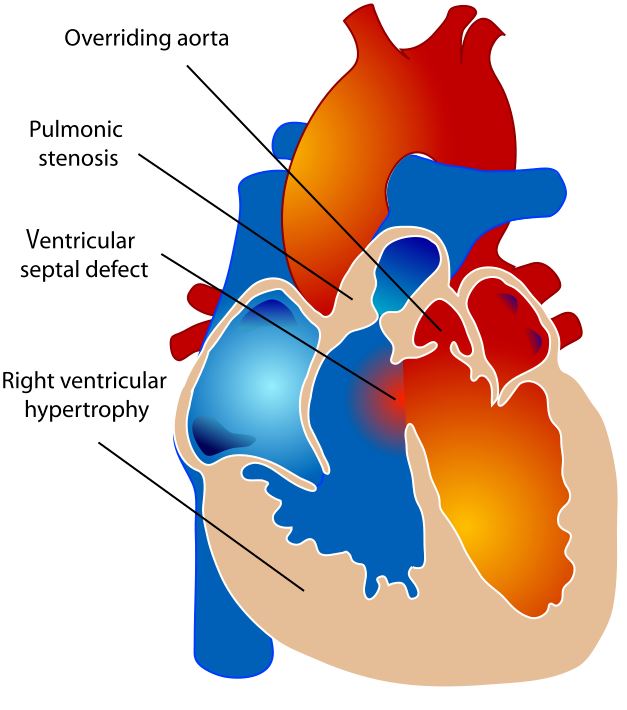
Image Source: Wikimedia Commons (2016). Tetralogy of Fallot, Licensed under a creative commons licence. Available for free at:
https://upload.wikimedia.org/wikipedia/commons/thumb/e/e6/Tetralogy_of_Fallot.svg/1228px-Tetralogy_of_Fallot.svg.png?20160125111000 (Accessed 2 May 2025).
Tetralogy of Fallot (TOF) refers to a cyanotic type of CHD in which four structural abnormalities coexist and most often present within the neonate. These are pulmonary stenosis (narrowing of the right ventricular outlet), right ventricular hypertrophy (due to increased pulmonary resistance), ventricular septal defect (shunt between both ventricles) and an overriding aorta (expansion of the aorta due to increased blood flow from both ventricles via the VSD). The main features are summarised in Table Seven.
| Feature | Summary |
|---|---|
| Epidemiology | 7-10 % of all CHD patients and is the most common cyanotic CHD. |
| Aetiology | Epigenetics
Genetic syndromes, e.g. Trisomy 21, 18 and 13, DiGeorge Maternal risk factors, e.g. diabetes, retinoic acid or trimethadione ingestion |
| Clinical History | Often in the newborn with cyanosis and a murmur noted on auscultation.
If present later, then increasing cyanosis, murmur and hypercyanotic episodes (crying with deep rapid breathing and increased cyanosis). |
| Clinical Examination | Variable, depending on the level of right ventricular outlet obstruction. But very often, a harsh systolic ejection murmur loudest at the left sternal edge, tachypnoea and variable degree of cyanosis. |
| Diagnostic Investigations | Pulse oximetry (pre and post-ductal readings show low oxygen saturations).
Echocardiogram (visualisation of pulmonary stenosis, ventricular septal defect, right ventricular hypertrophy and an overriding aorta). ECG (may show signs of right ventricular hypertrophy). Chest X-ray (“boot” shaped heart) Hyper-oxygenation Testing (no significant increase noted in PaO2) |
| Diagnostic Criteria | Evidence of the following on echocardiogram:
|
| Management | Acute Setting Hypercyanotic Episodes
Non-remitting severe cyanosis (due to severe pulmonary obstruction)
Severe cyanosis and limited pulmonary blood flow
Ongoing Complete Surgical Repair
Monitoring and potential pulmonary valve replacement
Antimicrobial Prophylaxis
|
| Follow Up | Lifelong Follow-Up, including those with surgical repair for complication surveillance.
Pre-conception counselling, including monitoring during pregnancy. Complications include progressive right ventricular failure and pulmonary regurgitation, arrhythmias (ventricular and atrial), sudden cardiac death and heart failure. After surgical repair, the prognosis is individual, based on the patient’s anatomy and the occurrence of any complications. Overall, long-term survival rates are improving. |
Table 7: This table details the main features of Tetralogy of Fallot. Sourced and adapted from Doyle T, Kavanaugh-McHugh A. Management and outcome of tetralogy of Fallot: UpToDate; 2023 and Gossett J, Kamp A. Tetralogy of Fallot: BMJ Best Practice; 2022.
Obstructive Valvular and Non-Valvular Lesions
Coarctation of the Aorta
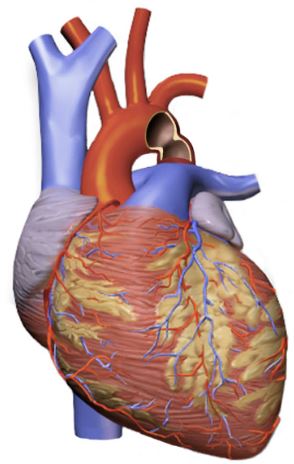
Image Source: Wikimedia Commons (2016). Coarctation Of Aorta, Licensed under a creative commons licence. Available for free at:
https://upload.wikimedia.org/wikipedia/commons/3/30/Coarctation_Of_Aorta.png?20160926151738 (Accessed 2 May 2025).
Coarctation of the aorta (CoA), or aortic coarctation, describes a vasculature abnormality with a narrowing of the descending aorta. Most often, this lesion is located distal to the left subclavian artery, i.e., the insertion site for the ductus arteriosus. A consequence of CoA is increased left ventricular pressure due to increased left ventricular outflow resistance. This syndrome is described in Table Eight.
| Feature | Summary |
|---|---|
| Epidemiology | Mostly sporadic
Prevalence of 4 in 10,000 live births and is more common in males Often associated with VSD and bicuspid aortic valve |
| Aetiology | Congenital manifestation is still not fully understood. However, two theories exist.
Genetics, e.g. Turner syndrome, DiGeorge Acquired presentation is rare but can be related to Takayasu arteritis |
| Classification | Several strategies exist, but they are commonly based on location
|
| Clinical History | In mild or moderate cases, patients are often asymptomatic. In severe cases, these present in the neonate when the ductus arteriosus closes and presents with shock, hypotension and cyanosis.
Potential features within a clinical history include:
|
| Clinical Examination | Reduced palpable pulses in the lower limbs
Difference in the upper and lower limb blood pressure Ejection systolic murmur – heard loudest in the left upper sternal border or back Male |
| Investigations | ECG – often normal, or may show left or right ventricular hypertrophy
CXR – features depend on the severity and age. It can be normal, have posterior rib notching (collateral vessel enlargement) or cardiomegaly (pulmonary venous congestion) Echocardiogram – definitive and will show a discrete thoracic aortic narrowing with a pressure gradient. |
| Diagnostic Criteria | This criterion allows for the deduction of the clinical severity of the CoA.
|
| Management | The main goal is a complete repair of the coarctation with no residual pressure gradient. The choice depends on the clinical presentation and severity.
Severe coarctation in the neonate requires prostaglandin E1 to maintain ductus arteriosus patency and then emergency surgical repair. Non-critical coarctation repair is dependent on the age of the patient. If less than one year, then surgical repair is often used. If older than one year, then surgical or percutaneous repair is utilised. If there is recurrent coarctation, then stent or balloon angioplasty is utilised. |
| Follow Up | Patients will require indefinite follow-ups with a suitable cardiologist.
Complications include treatment resistant hypertension resulting in coronary artery disease, cerebral aneurysm, aortic dissection, aortic pseudoaneurysm or coarctation recurrence. Prognosis is often excellent in those with isolated CoA but often will require life-long antihypertensive treatment and cardiology follow-up. In the context of other abnormalities, there is a higher risk of long-term complications. |
Table 8: The above table details the main findings regarding coarctation of the aorta, sourced and adapted from Gossett, Coarctation of the Aorta: BMJ Best Practice; 2023 and Hijazi, Clinical manifestations and diagnosis of coarctation of the aorta: UpToDate; 2023.
Pulmonary Stenosis
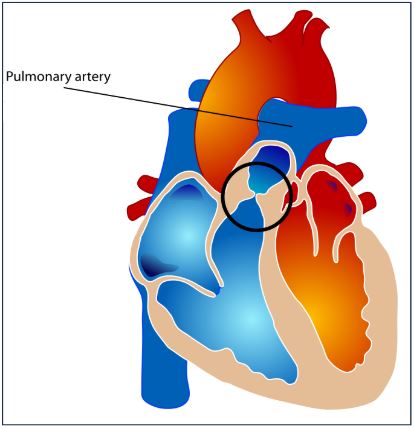
Image Source: Wikimedia Commons (2016). Pulmonary Valve Stenosis, Licensed under a creative commons licence. Available for free at:
https://upload.wikimedia.org/wikipedia/commons/thumb/7/7f/Pulmonary_valve_stenosis.svg/1232px-Pulmonary_valve_stenosis.svg.png?20070716043327 (Accessed 2 May 2025).
Pulmonary stenosis (PS) is an obstruction of blood flow from the right ventricle into the pulmonary vasculature. The obstruction results in a pressure gradient across the pulmonary valve of over 10mmHg during systole. Around 80% of cases are due to the pulmonary valve, but other variants can arise distally and proximal, and it is most commonly present in the context of other CHDs. The clinical picture is variable, ranging from asymptomatic to extreme cyanosis and even death. The main features associated with PS can be reviewed in Table Nine.
| Feature | Summary |
|---|---|
| Epidemiology | Present in 7% of all children with CHD
Occurs in more females |
| Aetiology | Most are congenital in nature
The key consequence of PS is increased right ventricular strain and pressure. In mild-to-moderate cases, patients are often acyanotic and without cardiac signs. However, in severe cases, right ventricular failure can result. |
| Classification | Often this is via the location of the obstruction
|
| Clinical History | Even without intervention, survival into adulthood is typical, but this can result in calcification and fibrotic changes of the pulmonary valve.
Mild-to-moderate cases are often asymptomatic. However, severe PS may report syncope on exertion, chest pain, exertional dyspnoea and fatigue. |
| Clinical Examination | Common examination findings include:
Dysmorphic features, e.g. Noonan, Williams |
| Investigations | ECG – normal (mild), right ventricular conduction delay and right axis deviation (moderate), right atrial enlargement and extreme right axis deviation (severe)
Chest X-ray – normal (mild or moderate), cardiomegaly/right ventricular or atrial enlargement (severe) Echocardiogram with Doppler – visualisation of valvular pathology and systolic pressure gradient |
| Management | Treatment of PS depends on the severity of the disease
|
| Follow Up | Outpatient monitoring for signs of progression (mild PS), but more frequent follow-up is needed in patients who have undergone a procedure.
Potential complications include pulmonary valve insufficiency after valvuloplasty, right-sided heart failure, and risk associated with valvuloplasty procedure. The prognosis is related to PS severity. In mild PS, even if untreated, survival is similar to that of the general population. In critical PS, if there is no intervention, then it is a terminal presentation in the neonate. In PS requiring surgical intervention, the outcome is impacted by younger age at the point of intervention, a higher initial pressure gradient and a high residual gradient. |
Table 9: The above table outlines the main features relating to pulmonary stenosis, sourced and adapted from Asnes and Keesham, Pulmonary Stenosis: BMJ Best Practice 2022 and Stout, Clinical manifestations and diagnosis of pulmonic stenosis in adults: UpToDate; 2021.
References
- Wren C, Richmond S, Donaldson L. Presentation of congenital heart disease in infancy: implications for routine examination. Arch Dis Child Fetal Neonatal Ed. 1999;80(1):F49-53.
- Khambadkone S. Congenital Heart Disease. BMJ Best Practice. 2019.
- Murphy PJ. The fetal circulation. Continuing Education in Anaesthesia Critical Care & Pain. 2005;5(4):107-12.
- Haeffner A. Fetal Circulation: TeachMePhysiology; 2022 [6th June 2023]. Available from: https://teachmephysiology.com/reproductive-system/fetal-physiology/fetal-circulation/.
- Kung GC, Triedman, J. K. Pathophysiology of left-to-right shunts: UpToDate; 2022 [Available from: https://www.uptodate.com/contents/pathophysiology-of-left-to-right-shunts#H852076582.
- Cleaveland Clinic. Acyanotic Heart Disease 2021 [Available from: https://my.clevelandclinic.org/health/diseases/21725-acyanotic-heart-disease.
- Beerman LB. Pathophysiology of Congenital Heart Anomalies MSD Manual Professional Version,; 2023 [Available from: https://www.msdmanuals.com/en-gb/professional/pediatrics/congenital-cardiovascular-anomalies/overview-of-congenital-cardiovascular-anomalies.
- Haller C. Intraatrial Communications (Atrial Septal Defects): BMJ Best Practice; 2023 [Available from: https://bestpractice.bmj.com/topics/en-gb/1099.
- Menillo AM, Lee LS, Pearson-Shaver AL. Atrial Septal Defect: StatPearls; 2022 [Available from: https://www.ncbi.nlm.nih.gov/books/NBK535440/.
- Basit H, Wallen TJ, Sergent BN. Eisenmenger Syndrome: StatPearls Publishing; 2023 [Available from: https://pubmed.ncbi.nlm.nih.gov/29939577/.
- Watchman T. Eisenmenger Syndrome: Zero to Finals; 2019 [Available from: https://zerotofinals.com/paediatrics/cardiology/eisenmengersyndrome/.
- Aggarwal K. Ventricular septal defects: BMJ Best Practice; 2022 [Available from: https://bestpractice.bmj.com/topics/en-gb/1100.
- Kitterman JA, Edmunds LH, Jr., Gregory GA, Heymann MA, Tooley WH, Rudolph AM. Patent ducts arteriosus in premature infants. Incidence, relation to pulmonary disease and management. N Engl J Med. 1972;287(10):473-7.
- Johnson JT, Nelangi MP. Patent Ductus Arteriosus: BMJ Best Practice 2022 [Available from: https://bestpractice.bmj.com/topics/en-gb/766.
- Doyle T, Kavanaugh-McHugh A. Clinical manifestations and diagnosis of patent ductus arteriosus (PDA) in term infants, children, and adults.: UpToDate; 2022 [Available from: https://www.uptodate.com/contents/clinical-manifestations-and-diagnosis-of-patent-ductus-arteriosus-pda-in-term-infants-children-and-adults.
- Hara H. Patent Foramen Ovale: UpToDate; 2022 [Available from: https://www.uptodate.com/contents/patent-foramen-ovale.
- Aggarwal KK, PR Patent Foramen Ovale: BMJ Best Practice 2022 [Available from: https://bestpractice.bmj.com/topics/en-gb/951.
- Tetralogy of Fallot: Great Ormond Street Hospital for Children NHS Foundation Trust; 2023 [Available from: https://www.gosh.nhs.uk/conditions-and-treatments/conditions-we-treat/tetralogy-fallot/.
- Doyle T, Kavanaugh-McHugh A. Management and outcome of tetralogy of Fallot: UpToDate; 2023 [Available from: https://www.uptodate.com/contents/management-and-outcome-of-tetralogy-of-fallot.
- Gossett J, Kamp A. Tetralogy of Fallot: BMJ Best Practice; 2022 [Available from: https://bestpractice.bmj.com/topics/en-gb/701.
- Gossett J. Coarctation of the Aorta: BMJ Best Practice; 2023 [Available from: https://bestpractice.bmj.com/topics/en-gb/698.
- Hijazi ZM. Clinical manifestations and diagnosis of coarctation of the aorta: UpToDate; 2023 [Available from: https://www.uptodate.com/contents/clinical-manifestations-and-diagnosis-of-coarctation-of-the-aorta.
- Asnes J, Keesham B. Pulmonary Stenosis: BMJ Best Practice 2022 [Available from: https://bestpractice.bmj.com/topics/en-gb/475.
- Stout K. Clinical manifestations and diagnosis of pulmonic stenosis in adults: UpToDate; 2021 [Available from: https://www.uptodate.com/contents/clinical-manifestations-and-diagnosis-of-pulmonic-stenosis-in-adults.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

