


 Close
 7th May 2025
Atrial Septal Defect
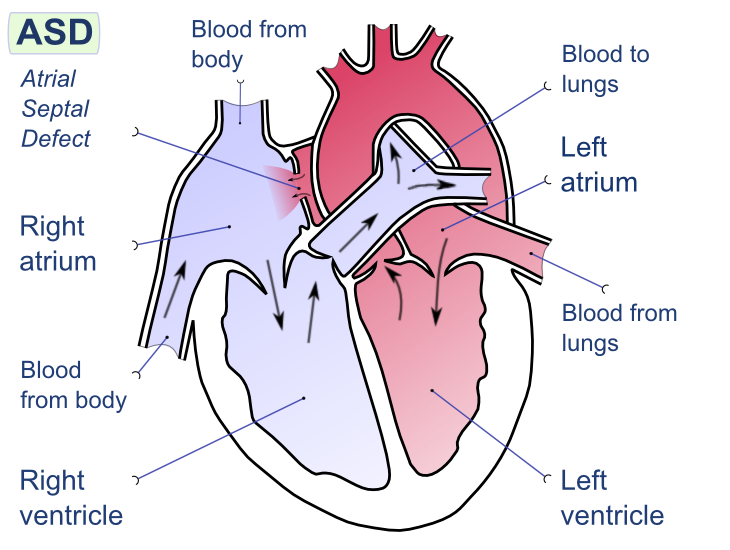
Image Source: Wikimedia Commons (2008). Atrial Septal Defect, Licensed under a creative commons licence. Available for free at:
https://upload.wikimedia.org/wikipedia/commons/9/92/Atrial_septal_defect-en.png?20080221094223 (Accessed 2 May 2025).
Atrial septal defects (ASD) refer to an intra-arterial connection that often results from the incomplete separation of the right and left atrium during foetal development (Figure Two). The result is a shunt between the two atria. The key features can be seen in Table Two. There are five types of ASD, from most common to least, they are patent foramen ovale, ostium secundum defect, ostium primum defect, sinus venous defect and coronary sinus defect.
| Feature | Summary |
|---|---|
| Epidemiology | 1 to 2 per 1000 live births
Most common CHD in adults |
| Aetiology | Most occur sporadically, with no prior family history
Associated with some genetic syndromes, e.g. Noonan, trisomy 21 More likely in females than males. |
| Classification |
|
| Clinical History | Adults can be asymptomatic
Often symptomatic after 4th decade: palpitations, dizziness (an atrial arrhythmia), shortness of breath, dyspnoea, fatigue, reduced exercise tolerance |
| Clinical Examination | Dependent on the size of the ASD
Most common:
Uncommon:
|
| Diagnostic Investigations | Echocardiogram: allows direct visualisation of the ASD
ECG: typically normal in small ASD but tall P waves and large R waves in V1 (moderate to severe) Chest X-ray: normal if small ASD, possible cardiomegaly (moderate to severe) |
| Management | Dependent on the calculation of the ratio of pulmonary vascular to systemic blood flow (Qp:Qs)
Qp:Qs <1.5 – observation, may resolve spontaneously Qp:Qs ≥ 1.5 or enlargement of the right atrium – corrective surgical or transcatheter closure Pulmonary Vascular Resistance >5
|
| Follow Up | For small ASD, observation should include signs of arrhythmias.
If there is no evidence of pulmonary vascular obstructive disease, there is an excellent prognosis. The older the age of the patient at the point of repair, the increased risk of adverse events. |
Table 2: The above table details the key areas regarding atrial septal defects. Sourced and adapted from Haller, Intra-atrial Communications (Atrial Septal Defects): BMJ Best Practice; 2023.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

