


 Close
 16th May 2025
Therapeutic drug monitoring
Therapeutic drug monitoring
Therapeutic drug monitoring (TDM) is the practice of measuring a specific chemical parameter at designated time intervals, that with appropriate medical interpretation, will influence the prescribing of a medication. TDM is mainly focused on medications that have a narrow therapeutic index i.e., the difference between a therapeutic dose and a toxic dose is small.
Narrow therapeutic index medications
The therapeutic index of a medication is the relationship between the therapeutic and toxic dose of a medication and is calculated by the following formula:
Therapeutic Index = TD₅₀ / ED₅₀
ED50 = dose required to produce a therapeutic effect in 50% of the population
TD50 is the dose required to produce a toxic effect in 50% of the population.
Narrow therapeutic index medications can often be difficult to manage in practice and often require regular monitoring of plasma levels to prevent toxicity. A visual representation of the therapeutic index is provided in figure 1 below.
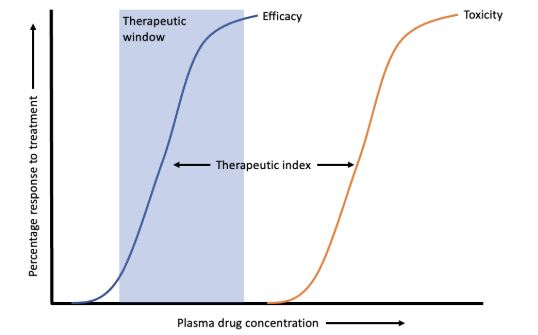
Figure 1: Diagram demonstrating the therapeutic index.
Adapted from the ‘Handbook of Pharmacogenomics and Stratified Memory’ chapter 18, pages 365-383
Half-life
Elimination half-life is the time required for the concentration of a particular substance or medication to decrease by half of its starting dose in the body. Different medications have different half-lives, but all medications follow the same following rule: after one half-life 50% of the initial drug amount is removed from the body. There are two commonly followed patterns for drug elimination – first order and zero order kinetics. First order kinetics occur when the rate of elimination is proportional to the amount of drug in the body i.e. the higher the concentration the greater the rate of elimination. Most medications follow first order kinetics. A few medications follow zero order kinetics, most notably phenytoin, ethanol, and salicylates (at high doses). Zero order kinetics occur when a constant amount of drug is eliminated per unit time.
Enzyme inducers and inhibitors
Cytochrome P450 (CYP450) are a group of enzymes encoded by P450 genes that are responsible for the metabolism of many drugs that are used in clinical practice. Most drugs (approximately 90%) are metabolised by CYP1A2, CYP3A4, CYP3A5, CYP2C9, CYP2C19, CYP2D6, of these CYP3A4 AND CYP2D6 are the most significant.
There are several substrates that bind to and are metabolised by the CYP450 enzymes. Common substrates include:
- Amitriptyline
- Caffeine
- Codeine
- Phenytoin
- Selective serotonin reuptake inhibitors
- Statins
- Theophylline
- Warfarin
There are many medications that can increase the expression (induce) or reduce the rate (inhibit) of CYP450 enzyme catalysed reactions; respectively called enzyme inducers and inhibitors. In the case of enzyme inducers, they will increase the metabolism of substrates resulting in a reduction in circulating plasma levels, the contrary is true of inhibitors. Common enzyme inducers and inhibitors can be found in table 1.
| Enzyme inducers | Enzyme inhibitors |
|---|---|
| Alcohol | Antibiotics – chloramphenicol, ciprofloxacin, isoniazid, macrolides, metronidazole, sulphonamides |
| Antibiotics – griseofulvin, rifampicin | Azoles – fluconazole, ketoconazole |
| Anticonvulsants – carbamazepine, phenobarbitone, phenytoin | Cimetidine |
| Cigarette smoke | Grapefruit juice |
| Nicotine | Omeprazole |
| St John’s Wort | Sodium valproate |
| Table 1: Common enzyme inducers and inhibitors | |
Medications that require therapeutic drug monitoring
There are several medications that require TDM, and this section will cover some of the common ones encountered in clinical practice.
Aminoglycosides
Aminoglycosides are broad spectrum antibiotics with activity against some gram-positive and many gram-negative organisms. They are bactericidal and exhibit concentration dependent bacterial killing. These antibiotics exhibit a post-antibiotic effect meaning that there is a continued suppression of bacterial growth even when drug concentration falls below the minimum inhibitor concentration.
Aminoglycosides are hydrophilic in nature which can lead to changes in volume of distribution in certain conditions such as sepsis, resulting in lower drug plasma concentrations. They are primarily excreted through the kidneys, therefore patients with acute kidney injury or chronic kidney disease may accumulate the medication.
Empiric therapy with aminoglycosides should usually be limited to 48 hours, if treatment extends beyond this point levels should be monitored due to the increased risk of adverse effects. The main adverse effects are ototoxicity and nephrotoxicity. Ototoxicity occurs in 2-45% of adults and can be categorised as vestibular or cochlear. Vestibular damage is often reversible whereas hearing loss is not. Gentamicin and tobramycin are more likely to cause vestibular damage whereas amikacin is more likely to cause cochlear damage. Nephrotoxicity occurs in 10-25% of patients and the mechanism is thought to be due to proximal tubular dysfunction. Aminoglycoside toxicity is often reversible.
Gentamicin
Gentamicin is the most used aminoglycoside in the UK, but others include tobramycin and amikacin. It was traditionally dosed through multiple daily dosing but extended once daily dosing has been found to be as effective, no more nephrotoxic, and less complex to administer. Multiple daily dosing is still commonly used in endocarditis.
Dosing is usually based on actual body weight unless patients are obese where adjusted body weight is used (actual body weight >20% of ideal body weight). Monitoring for once-daily dosing can differ from trust to trust so trust guidelines should be consulted, but two common methods are taking ‘trough’ levels and using a nomogram. In the first method mentioned, pre-dose ‘trough’ levels are usually required to ensure the drug is being sufficiently cleared (<1mg/L) from the body. The second method involves a level that is taken 6-14 hours post dose which is then evaluated with a Hartford nomogram. This nomogram is shown below:
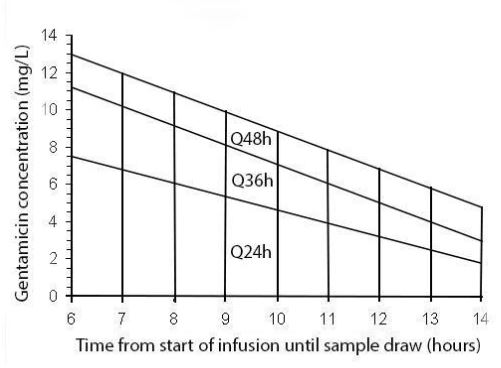
Figure 2: Hartford Nomogram
Image Source: Wikimedia Commons (2017). Detail, Licensed under a creative commons licence. Available for free at: http://www.lhp.leedsth.nhs.uk/detail.aspx?id=1944 (Accessed 12 May 2025).
If the level falls within the Q24h, Q35h, or Q48H the dosing interval should be changed correspondingly. If the level falls on the line, the longer dosing interval should be used. If the level falls above Q48h treatment should be held and serial levels taken until the level falls below <1mg/L). In multiple day dosing samples should be taken one hour post dose (‘peak’ level) and pre-dose (‘trough’ level). If the trough concentration is high, the interval between doses must be increased. If the peak concentration is high, the dose must be decreased. Ensure that you consult local guidance regarding dosing and monitoring of gentamicin.
Glycopeptides
Glycopeptide antibiotics have bactericidal activity against aerobic and anaerobic gram-positive bacteria. Similarly to aminoglycoside antibiotics, common adverse effects include ototoxicity and nephrotoxicity. For this reason, it is important to monitor serum drug concentrations and limit the duration of therapy where appropriate.
Vancomycin
Vancomycin has activity against many gram-positive bacteria and its mechanism of action is through targeting bacterial cell wall synthesis. Initial vancomycin dosing is usually based on actual body weight, subsequent dose adjustments should be based on serum concentrations to achieve target therapeutic concentrations. Regular monitoring of vancomycin levels is indicated in high dose treatment and long-term therapy especially in those with renal impairment. Serum vancomycin levels are taken as a pre-dose ‘trough’ and the concentration is normally between 10-20mg/L; in those with severe infections, trough concentrations of 15-20mg/L are preferred.
Teicoplanin
Teicoplanin has a similar spectrum of activity and mechanism of action to vancomycin. It is associated with less ototoxicity and nephrotoxicity and has a longer half-life allowing for once daily dosing. Due to having a longer half-life teicoplanin requires a loading dose to rapidly achieve satisfactory serum levels. Monitoring of drug levels is required if prolonged therapy is indicated. A trough level should be taken on day 5 and adjustments should be made to subsequent doses based on local guidelines. Alongside drug levels both full blood count and urea & electrolytes should be regularly monitored due to the risk of myelosuppression and nephrotoxicity respectively.
Warfarin
Warfarin is an anticoagulant that acts by inhibiting the synthesis of vitamin K dependent clotting factors. The therapeutic action of warfarin is monitored through an International Normalised Ratio (INR). The INR is derived from prothrombin time (PT) which is calculated as the ratio of the patient’s PT to a standardised PT. The INR which is required and is dependent on the indication with most requiring a target of 2.5 (range 2-3) e.g., atrial fibrillation (AF), deep vein thrombosis. (DVT), and pulmonary embolism (PE). Those with recurrent DVT or PE whilst anticoagulated with an INR above 2 require a higher target of 3.5 (range 3-4). Patients with mechanical heart valves also require anticoagulation, the recommended INR can depend on the location of the valve and patient risk factors (e.g. AF, previous arterial thromboembolism, and mitral stenosis). Those with risk factors and valves in mitral, tricuspid, or pulmonary positions require higher INR targets.
When initiating warfarin therapy INR should be monitored daily or on alternate days, once the INR has stabilised it can be monitored at longer intervals. Closer INR monitoring may be required if there are changes in a patient’s condition, particularly associated with hepatic dysfunction, concurrent illness, or additions of new medications.
It is worth noting that several medications and foods interact with warfarin which may require a change in warfarin dose and INR monitoring frequency. Medications can either increase or decrease the therapeutic effectiveness of warfarin through interactions with cytochrome P450 enzymes or through synergistic pharmacological effects. Food and drugs that increase the effect of warfarin include alcohol, amiodarone, antidepressants, antiplatelets, cranberry juice, and non-steroidal anti-inflammatory drugs. Those that decrease the effect of warfarin include antiepileptics, rifampicin, St John’s Wort, and vitamin K containing complexes e.g., certain enteral feeds and green vegetables.
Lithium
Lithium is a mood stabiliser often used in the management of bipolar disorder, the mechanism of which is not fully understood. It exists as two salts, lithium carbonate and lithium citrate, which are not dose equivalent. For this reason, it is important to ensure that lithium is prescribed by brand.
When initiating treatment, levels are normally measured one week after starting, one week after any dose change, and every week until levels are stable. Lithium levels should be taken 12 hours post dose and once levels are stable it is usually monitored every three months. The target for someone newly initiated on lithium should be between 0.6-0.8mmol/L. Higher serum levels of 0.8-1mmol/L may be desired in those who have relapsed whilst on treatment or who continue to have symptoms with functional impairment whilst on lithium. Alongside drug levels it is advised to monitor body mass index (BMI), urea and electrolytes, estimated glomerular filtration rate (eGFR), calcium, and thyroid function every 6 months.
An important reason for monitoring plasma lithium levels is the risk of lithium toxicity. Lithium toxicity may occur at normal serum levels, but it tends to occur at levels greater than 1.5mmol/L, and severe toxicity may occur at levels greater than 2mmol/L. Signs of lithium toxicity can be stratified into mild, moderate, and severe:
- Mild toxicity: Nausea, vomiting, diarrhoea, tremor, fatigue, light headedness, muscular weakness, and drowsiness.
- Moderate toxicity: Confusion, agitation, hypertonia, myoclonic jerks, choreoathetoid movements, urinary or faecal incontinence, and hypernatraemia.
- Severe toxicity: Coma, seizures, cerebellar signs, hypotension, and cardiac dysrhythmias
There is no antidote for lithium toxicity. In the event of lithium toxicity, the medication should be discontinued, and supportive treatment should be given. For further information on the management of lithium toxicity please refer to the ‘Poisoning, emergency treatment’ summary in the BNF.
Digoxin
Digoxin is a cardiac glycoside which increases contractility of the myocardium by direct activity. Its primary action is through inhibition of adenosine triphosphatase, and thus sodium-potassium exchange activity. This results in augmentation of calcium ion influx allowing for increased calcium availability at the time of excitation-contraction coupling. A similar effect is exerted on the autonomic nervous system which results in reduced sympathetic tone thereby reducing ventricular rate. If rapid digitalisation is required, intravenous (IV) administration of a loading dose of digoxin produces a pharmacological effect within 5-30 minutes, whilst the oral route occurs in 0.5-2 hours.
Routine monitoring of digoxin levels is not usually indicated unless there is suspicion of toxicity, change in renal function, or there is a possible lack of compliance. Digoxin levels should be taken at least 6 hours post dose. There are no set guidelines stating what range of serum digoxin levels is most efficacious but analysis by the Digitalis Investigation Group trial suggested that levels between. 0.5-1 nanogram/mL could be efficacious.
Digoxin toxicity can occur at low digoxin concentrations, but it is more commonly associated with levels above 2 nanogram/mL. The signs of digoxin toxicity are often non-specific and include nausea, vomiting, diarrhoea, lethargy, confusion, visual disturbance, and arrhythmias. Cardiac arrhythmias account for many deaths due to digoxin toxicity. In case of suspected or known life-threatening digoxin toxicity Digibind antidote can be administered.
Tacrolimus
Tacrolimus is a highly potent immunosuppressant that works via the inhibition of calcineurin which reduces the production of cytokine genes for proteins such as interleukin-2, tumour necrosis factor-alpha and interferon gamma, ultimately reducing the proliferation of T-lymphocytes.
Before initiating tacrolimus therapy, a number of baseline investigations should be performed including:
- Blood pressure
- Blood tests – full blood count, urea & electrolytes, renal function, liver function, clotting screening, plasma proteins
- Fasting blood glucose
- ECG – to look for hypertrophic changes
- Hepatitis and HIV screening if patients are at risk of infection
Once therapy has begun, whole blood trough tacrolimus levels should be taken twice each week and once stable, they should be monitored if there are changes to dose, interacting medications are prescribed, or in the event of unexplained graft dysfunction. In the early post-transplant period trough levels are usually between 5-20 nanograms/mL for liver transplant recipients and 10-20 nanograms/mL for kidney and heart transplant patients. For maintenance therapy levels are usually between 5-15 nanograms/mL for liver, kidney, and heart transplant recipients. In the case of patients with severe hepatic dysfunction levels should be monitored closely due to reduced clearance and therefore prolonged half-life of the drug.
Alongside monitoring whole drug levels, the following should be monitored routinely at clinic visits:
- Blood pressure
- Blood tests – full blood count, urea & electrolytes, renal function, liver function, clotting screening, plasma proteins
- Fasting blood glucose
- Visual acuity
- Skin examination – twice a week for the first 5 years, then annually
- Lipids & Hepatitis surface antibodies annually
Theophylline
Theophylline is a medication used in the treatment and prophylaxis of bronchospasm associated with asthma, chronic obstructive pulmonary disease, and chronic bronchitis. It works to relax smooth muscle located in the bronchial airways and pulmonary vessels. This works in two ways: (1) it competitively inhibits type III and IV phosphodiesterase, reducing the breakdown of cyclic AMP, leading to bronchodilation, (2) it binds to adenosine A2B receptors preventing adenosine mediated bronchoconstriction.
Monitoring of theophylline is required 5 days after initiation or 3 days after any dose change and a level should be taken 4-6 hours post dose in the case of oral modified release theophylline. Therapeutic bronchodilation occurs at levels between 10-20 mg/L, although lower levels of 5-15mg/L may be used. The frequency and severity of side effects increase at concentrations >20mg/L. Signs of theophylline toxicity include vomiting, agitation, restlessness, dilated pupils, sinus bradycardia, and hyperglycaemia. More severe signs can include haematemesis, convulsions, arrhythmias (supraventricular and ventricular). Alongside this severe hypokalaemia may develop rapidly. The ‘Poisoning, emergency treatment’ summary in the BNF includes information on the management of theophylline overdose.
It is worth noting that theophylline is a substrate for cytochrome P450 enzymes, therefore there are several medications that can affect the concentration of theophylline in the blood. CYP P450 inhibitors such as amiodarone, fluconazole, and sodium valproate can cause an increase in theophylline levels. Inducers of CYP450 enzymes such as carbamazepine, rifampicin, St John’s Wort can cause a decrease in theophylline levels. Concomitant use of these medications should be avoided, if this is not possible close monitoring of theophylline levels is advised. Other notable interactions include beta-agonists, diuretics, and corticosteroids which can potentiate hypokalaemia. A significant reaction between lithium and theophylline can result in a potentiation of lithium therapy.
Prescribing in renal impairment
The kidneys perform a vital role in the metabolism of the kidneys. In patients with renal impairment several problems can occur:
- Reduced renal excretion of a medication or its metabolite causing toxicity e.g. morphine
- Increased toxicity of a medication even if its elimination is not altered e.g. statins, warfarin
- Many medication side effects are poorly tolerated by patients with renal impairment e.g. NSAIDs
- Effectiveness of some drugs are reduced in renal impairment e.g. diuretics, nitrofurantoin
Many of these problems can be mitigated by reducing drug dosage or frequency or using an alternative medication.
Estimating renal function
The gold standard for measuring glomerular filtration rate (GFR) is by directly measuring the plasma or urinary clearance of an exogenous filtration marker, however this is difficult in practice. In practice GFR can be estimated with equations that use serum creatinine and other variables. Estimated glomerular filtration rate (eGFR) can be commonly calculated based on the Modification of Diet in Renal Disease (MDRD) equation or Chronic Kidney Disease Epidemiology Collaboration (CKD-EPI) equation. Creatinine clearance (ClCr) which is calculated from the Cockcroft-Gault formula is also commonly used to estimate renal function.
In patients with extremes of muscle mass eGFR should be used with caution. Reduced muscle mass can lead to overestimation of GFR, and increased muscle mass will result in an underestimation. In patients of average height and weight eGFR can be used to dose medications as opposed to ClCr. In toxic drugs, elderly patients, and extremes of muscle mass ClCr is recommended.
Medication dosing in renal impairment
Many drugs are eliminated via the kidneys and in chronic kidney disease (CKD) or acute kidney injury (AKI) these medications can accumulate increasing the risk of adverse drug reactions. If CKD or AKI is suspected a review of medications is indicated. Medications that cause or can exacerbate renal impairment should be avoided, examples of these can be found in table 2. If changes are needed to the total daily dose of a medication can be altered by reducing individual doses or by increasing the time interval between doses. Information regarding the use of medications in renal impairment can be found in the appropriate drug monograph in the BNF or in a manufacturers summary of product characteristics (SPC).
| Medication | Effect on the kidney | Action during AKI |
|---|---|---|
| NSAIDs | Altered haemodynamics within the kidney leading to hypoperfusions | Avoid |
| Aminoglycosides | Tubular cell toxicity | Avoid if possible. If use is unavoidable, reduce dose &/or increase dosing interval |
| Glycopeptides | Acute interstitial nephritis | Reduce dose / increase dose interval |
| ACE inhibitors/ARBs | Altered haemodynamics. Can impair kidney’s ability to maintain GFR when perfusion is compromised | Avoid unless in certain circumstances where they may be beneficial. |
| Thiazide and loop diuretics | Over diuresis leading to hypoperfusion of the kidneys can cause or exacerbate AKI. | Loop diuretics preferred as thiazides less effective if GFR < 25ml/min. Higher doses may be needed to achieve a diuresis in patients with fluid overload. |
| Methotrexate | Crystal nephropathy | Use with caution, avoid in severe impairment |
| IV bisphosphonates | Can cause impaired renal function – especially when given in high doses and short duration infusions | Reduce dose and infuse at correct rate |
| Table 2: Nephrotoxic medications | ||
In patients with CKD or AKI some medications may accumulate increasing the risk of toxicity and adverse side effects. Product literature should be consulted, and doses should be adjusted, or the medications should be temporarily held. Examples of these are highlighted in table 3.
| Medication | Effect on medication during renal impairment | Action during AKI |
|---|---|---|
| Opioid analgesics | Risk of accumulation leading to toxicity | Reduce dose or consider alternatives that are not renally excreted e.g. oxycodone, fentanyl |
| Metformin | Increased risk of lactic acidosis | Avoid if GFR <30mL/min |
| Methotrexate | Risk of accumulation leading to toxicity | Use with caution, avoid in severe impairment |
| Digoxin | Risk of accumulation leading to bradycardia and toxicity | Consider reducing dose and monitoring digoxin level |
| Lipid lowering agents | Possible increased risk of rhabdomyolysis | Monitor for unexplained/persistent muscle pain. Stop if AKI due to rhabdomyolysis. |
| Lithium | Risk of accumulation leading to toxicity | Avoid where possible Monitor lithium levels Seek advice for alternative |
| Low molecular weight heparins | Risk of accumulation which can increase bleeding risk | Consider reducing dose or switching to alternative medication as per hospital guidance |
| Warfarin | Acute rise in urea may displace warfarin from binding site causing a rise in INR | Monitor INR and consider adjusting dosage |
| Table 3: Medications requiring adjustment in AKI | ||
Prescribing in hepatic impairment
The liver plays an important role in the pharmacokinetic and pharmacodynamic properties of drugs. This can be directly through metabolism of medications or indirectly through impairment of other functions of the liver. Some of these will be discussed in turn:
Impairment of absorption
Lipophilic drugs require the presence of bile salts to aid their absorption from the gut e.g. fat soluble vitamins. In cholestatic liver disease there is impairment to bile production or flow, resulting in less bile reaching the gut, which in turn may reduce drug absorption.
Impairment of drug distribution
One of the synthetic functions of the liver is the production of plasma proteins, many drugs are bound to these proteins to allow for transport of drug molecules around the body. The proportion of a drug bound to plasma proteins is not free to bind to receptors and exert a pharmacological effect.
In liver disease this synthetic function can become impaired resulting in reduced circulating plasma proteins (hypoalbuminaemia). This can lead to an increase in the unbound fraction of drugs leading to more drugs to be available. In medications that are highly protein bound (e.g. phenytoin and prednisolone) this can result in increased adverse effects and a reduction in dose may be indicated.
Complications of oedema and ascites are driven by low levels of circulating plasma proteins. Medications which cause fluid retention may exacerbate this e.g. NSAIDs and corticosteroids.
Impairment of drug metabolism
The liver is the main site of drug metabolism in the body. Many drugs that are taken orally undergo a first pass metabolism, which reduces the concentration of the active drug reaching its site of action. In liver disease first pass metabolism is diminished which can result in increased circulating levels of active drugs in the body.
Other drugs are administered as a prodrug (e.g. clopidogrel, enalapril, and oxcarbazepine) which are inactive until they undergo metabolism in the liver. If the liver isn’t functioning correctly there may be decreased activity of these medications as less of the prodrug will be converted to its pharmacologically active form.
It is worth noting that routine liver function tests are not a reliable marker of the ability of the liver to metabolise drugs, it can be difficult to predict the extent that a drug’s metabolism may be impaired in an individual patient.
Impairment of drug elimination
Certain medications are excreted in bile and therefore their elimination from the body can be impaired in people with hepatic impairment e.g. rifampicin and fusidic acid.
Reduction in clotting factors
Another aspect of the liver’s synthetic function is the production of clotting factors, which will be shown by prolonged prothrombin time. This may exacerbate the effects of oral anticoagulant medications.
Hepatic encephalopathy
Hepatic encephalopathy is a reversible cause of impaired brain function which occurs in patients with severe liver disease. Drugs that cause sedation (e.g. opioid analgesics, benzodiazepines, Z-drugs) may exacerbate or precipitate hepatic encephalopathy.
Hepatotoxic drugs
Hepatotoxicity is the injury or damage to the liver caused by drug exposure and may be dose related or idiosyncratic. Patterns of idiosyncratic drug induced liver injury include hepatocellular, cholestatic, or mixed. Drug induced liver injury should be considered in acute liver injury or jaundice without any evidence of obstruction. In the presence of impaired liver function those drugs that cause dose-related damage may do so at lower doses, and those that produce idiosyncratic reactions may occur at an increased frequency. These drugs should be avoided or used with caution in patients with liver disease. Examples of hepatotoxic drugs include:
- Co-amoxiclav
- Nitrofurantoin
- Infliximab
- Azathioprine
References
- https://www.ncbi.nlm.nih.gov/pmc/articles/PMC2687654/
- https://www.cambridge.org/core/books/abs/essential-equations-for-anaesthesia/therapeutic-index/27E61005A78572680A45D4F4DB943960
- https://www.ncbi.nlm.nih.gov/books/NBK554498/
- https://www.ncbi.nlm.nih.gov/books/NBK557698/
- https://bnf.nice.org.uk/treatment-summaries/aminoglycosides/
- https://bnf.nice.org.uk/drugs/gentamicin/
- https://www.uptodate.com/contents/aminoglycosides
- https://www.uptodate.com/contents/vancomycin-parenteral-dosing-monitoring-and-adverse-effects-in-adults?search=vancomycin&source=search_result&selectedTitle=1~150&usage_type=default&display_rank=1
- https://bnf.nice.org.uk/drugs/teicoplanin/#monitoring-requirements
- https://www.medicines.org.uk/emc/product/2927/smpc
- https://bnf.nice.org.uk/drugs/warfarin-sodium/#monitoring-requirements
- https://www.uptodate.com/contents/warfarin-and-other-vkas-dosing-and-adverse-effects
- https://www.uptodate.com/contents/bipolar-disorder-in-adults-and-lithium-pharmacology-administration-and-management-of-adverse-effects?search=lithium&source=search_result&selectedTitle=1~150&usage_type=default&display_rank=1
- https://www.uptodate.com/contents/lithium-poisoning?search=lithium&source=search_result&selectedTitle=2~150&usage_type=default&display_rank=2
- https://bnf.nice.org.uk/drugs/lithium-carbonate/
- https://bnf.nice.org.uk/drugs/digoxin/#indications-and-dose
- https://www.uptodate.com/contents/treatment-with-digoxin-initial-dosing-monitoring-and-dose-modification
- https://www.uptodate.com/contents/digitalis-cardiac-glycoside-poisoning
- https://www.uptodate.com/contents/pharmacology-of-cyclosporine-and-tacrolimus?search=tacrolimus&source=search_result&selectedTitle=1~150&usage_type=default&display_rank=1
- https://www.ncbi.nlm.nih.gov/books/NBK544318/
- https://www.sps.nhs.uk/monitorings/tacrolimus-monitoring/
- https://bnf.nice.org.uk/drugs/theophylline/
- https://www.medicines.org.uk/emc/product/14509/smpc
- https://www.uptodate.com/contents/theophylline-use-in-asthma#:~:text=Theophylline%20salts%20%E2%80%94%20Several%20so%2Dcalled,(pKa%20%3D%208.8).
- https://www.uptodate.com/contents/theophylline-poisoning
- https://bnf.nice.org.uk/medicines-guidance/prescribing-in-renal-impairment/
- https://www.thinkkidneys.nhs.uk/aki/wp-content/uploads/sites/2/2016/03/Guidelines-for-Medicines-optimisation-in-patients-with-AKI-final.pdf
- https://bnf.nice.org.uk/medicines-guidance/prescribing-in-hepatic-impairment/
- https://www.uptodate.com/contents/drugs-and-the-liver-metabolism-and-mechanisms-of-injury
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

