


 Close
 23rd May 2025
Parathyroid
The parathyroid glands are responsible for the regulation of calcium concentration in the body. When calcium levels are low parathyroid hormone (PTH) is released which increases calcium absorption from the gut and kidney and increases renal phosphate loss and vice versa.
Hyperparathyroidism
Primary hyperparathyroidism is a disorder in which autonomous overproduction of parathyroid hormone (PTH) leads to hypercalcaemia.
Primary hyperparathyroidism
The causes of primary hyperparathyroidism are:
- Parathyroid adenoma (over 80% of cases)
- Hyperplasia (15-20%)
- Carcinomas (<1%)
- Familial cases can occur as part of multiple endocrine neoplasia syndrome (MEN 1 or MEN 2a) or familial isolated hyperparathyroidism (FIHPT)
Pathophysiology
In normal physiology, low serum calcium levels stimulate PTH secretion whereas high calcium suppresses PTH secretion. In primary hyperparathyroidism PTH secretion is not suppressed by high calcium, resulting in hypercalcaemia, as well as raised PTH levels.
Most of the symptoms associated with hyperparathyroidism are due to hypercalcaemia. Hypercalcaemia can cause symptoms such as “bones, stones, abdominal groans and psychiatric moans”. These are expanded on below. Chronic excessive PTH leads to over-stimulation of bone resorption resulting in osteopenia. In severe cases this can result in osteitis fibrosa cystica which presents with subperiosteal resorption of distal phalanges, salt-and-pepper appearance of the skull and brown tumours of the long bones.
Chronic increased excretion of the calcium in urine can result in renal stones.
Presentation
- Asymptomatic
- Hypercalcaemia
- Bone pain, muscle weakness, pseudogout, chondrocalcinosis, osteitis fibrosa cystica
- Renal stones
- Polyuria and polydipsia
- Abdominal groans: nausea and vomiting, peptic ulcer disease, constipation, anorexia, acute pancreatitis
- Neuropsychiatric manifestations: depression, anxiety, fatigue, memory problems.
- Cardiovascular manifestations: hypertension, bradycardia, Hypercalcaemic changes on ECG include: shortened QT interval, Osborn waves (J waves), Ventricular irritability and VF arrest.
- Physical examination of the neck is usually normal.
Investigations
Diagnosis of primary hyperparathyroidism is confirmed with repeated measures of serum calcium and intact serum PTH.
Certain conditions must be accounted for:
- Thiazide diuretics should be stopped 2 weeks before the calcium measurements.
- Serum calcium should be adjusted for the serum albumin concentration. Ionised calcium levels can be a more accurate measure.
- 25-hydroxyvitamin D level should also be measured in the evaluation of primary hyperparathyroidism.
Bloods may show the following:
- elevated intact PTH level
- elevated ionised serum calcium level
- on more than one occasion
Other laboratory findings include
- Mild hyperchloremic acidosis
- Hypophosphatemia
- Mild to moderate increase in urinary calcium excretion rate.
Other investigations include radiographic studies. These are often used as a guide (not for diagnosis purposes) for surgeons should the patient wish to proceed with a parathyroidectomy. Tc-99m sestamibi scanning is often used with ultrasonography.
Management
Parathyroidectomy is the definitive treatment for primary hyperparathyroidism.
Indications for surgery in an asymptomatic patient are the following:
- Age <50 years
- Inability to ensure appropriate follow-up
- Serum calcium >0.25 mmol/l (>1 mg/dl) above normal range
- Creatinine clearance <60mL/minute
- Bone mineral density T-score <-2.5 at lumbar spine, total hip, femoral neck, or distal third of radius and/or vertebral fracture by x-ray, CT, MRI or vertebral fracture assessment using dual-energy x-ray absorptiometry.
- 24-hour urinary calcium >400 mg/day and increased stone risk by biochemical stone risk analysis
- Nephrolithiasis or nephrocalcinosis by x-ray, ultrasound, or CT.
If the patient is symptomatic, surgery should be considered regardless of the above criteria.
If the patient declines surgery or is an unsuitable surgical candidate, serum calcium and creatinine levels should be measured annually and bone density be measured every 1-2 years. Vitamin D should be given to those who are deficient.
Bisphosphonates or cinacalcet are adjunctive therapies for those who do not undergo surgery.
Secondary hyperparathyroidism
Secondary hyperparathyroidism occurs when there is chronic hypocalcaemia, often caused by chronic kidney disease or vitamin D deficiency. This leads to an overproduction of parathyroid hormone.
Any disorder that results in hypocalcaemia will elevate parathyroid hormone level and can cause secondary hyperparathyroidism.
Causes
- Vitamin D deficiency
- Chronic kidney disease
- Fat malabsorption (this can contribute to reduced absorption of vitamin D and dietary calcium) e.g., in Crohn’s disease, Coeliac disease, chronic pancreatitis, Whipple’s disease, post-gastric bypass surgery
- Diminished dietary intake of calcium
- Increased calcium loss or increased metabolic requirements e.g. after pregnancy and breastfeeding, bisphosphonate treatment, loop diuretics, rhabdomyolysis, sepsis.
Presentation
The clinical features of secondary hyperparathyroidism depend on the underlying cause.
Severe vitamin D deficiency and hypocalcaemia present with neuromuscular irritability such as:
- Numbness or paraesthesia in fingers, toes, peri-orally
- Muscle cramps
- Laryngospasm
- Tetany
- Seizures
Vitamin D deficiency can cause Rickets in children and Osteomalacia in adults which presents with muscle weakness and diffuse bone pain.
Signs of hypocalcemia:
- Chvostek’s sign: percussion over the facial nerve leads to abnormal contraction of the ipsilateral facial muscles
- Trousseau’s sign: often found when taking the patient’s blood pressure, inflation of the blood pressure cuff for a few minutes leads to involuntary contraction of the muscles of the hand and wrist
Investigations
Diagnosis is based on clinical picture, metabolic derangement (low/normal serum calcium and high parathyroid hormone).
First line investigations:
- Serum Calcium to be taken at the same time as iPTH.
- Either total or ionised calcium levels can be used.
- Serum calcium levels may be normal or <2.10mmol/L
- Intact parathyroid levels are often >88 nanograms/L
- Renal function should be checked for CKD.
Other investigations:
- Phosphate: elevated phosphate levels in addition to elevated serum urea and creatinine can point towards a diagnosis of chronic kidney disease.
- If phosphate levels are low the diagnosis points towards vitamin D deficiency.
- Serum 25-hydroxyvitamin D levels should be measured.
- Serum magnesium: High or low levels of magnesium can cause tissue resistance to PTH or reduced PTH production resulting in hypocalcaemia.
Management
Management of secondary hyperparathyroidism is by optimising medical management of the underlying condition.
If the cause is lack of sunlight and vitamin D patients should be advised on safe sun exposure +/- vitamin D supplements.
If the cause is malabsorption-related, the underlying disorder should be treated (for example a gluten-free diet for coeliac disease or lactose-free diet in those who are lactose intolerant). Protease and lipase supplements for pancreatic insufficiency or corticosteroids and anti-inflammatory agents in inflammatory bowel disease. Vitamin D and calcium supplements can also be used.
If the secondary hyperparathyroidism is secondary to CKD, the first line management is dietary phosphate restriction (800-1000 mg/day). Serum phosphate levels should be monitored monthly in stage 5 CKD and every 3 months in stage 3-4 after initiation of the restriction.
A phosphate binder such as calcium acetate or Sevelamer can also be used with vitamin D supplementation if levels are low or vitamin D analogues if levels are normal.
In refractory secondary hyperparathyroidism in late-stage CKD, parathyroidectomy can be considered.
Tertiary hyperparathyroidism
Tertiary hyperparathyroidism occurs after a longstanding state of secondary hyperparathyroidism. The parathyroid gland may become hypertrophied leading to autonomous hypersecretion of parathyroid hormone. It is mostly seen in patients who have chronic secondary hyperparathyroidism and have been on dialysis for years. This leads to hypercalcaemia and very high parathyroid hormone levels.
Presentation
- Symptoms of hypercalcaemia
Investigations
- Bone profile: may show hypercalcaemia and hyperphosphataemia
- Elevated urea and creatinine as seen in CKD are seen on blood tests.
Treatment
Medical management is usually with Cinacalet. Surgical treatment involves a total parathyroidectomy.
Summary
| Main Causes | Calcium | Parathyroid hormone | Phosphate | |
| Primary hyperparathyroidism | Parathyroid adenoma | High | High/Normal | Low |
| Secondary hyperparathyroidism | CKD Vitamin D deficiency | Low/Normal | High | High/Low |
| Tertiary hyperparathyroidism | Hypertrophied parathyroid gland due to long standing secondary hyperparathyroidism | High | Very High | High |
Table 1: Summary
References
- https://emedicine.medscape.com/article/127351-overview
- Clinical Endocrinology and Diabetes at a Glance by Aled Rees, Miles Levy, Andrew Lansdown, April 2017 ISBN: 978-1-119-12871-7
- https://bestpractice.bmj.com/topics/en-gb/133?q=Primary%20hyperparathyroidism&c=recentlyviewed
- https://www.nice.org.uk/guidance/ng132/resources/hyperparathyroidism-diagnosis-visual-summary-pdf-6782711869
- https://bestpractice.bmj.com/topics/en-gb/1107/investigations
- https://emedicine.medscape.com/article/127351-overview#a4
- https://emedicine.medscape.com/article/127351-overview#a5
- https://www.sciencedirect.com/topics/medicine-and-dentistry/tertiary-hyperparathyroidism
- https://litfl.com/hypercalcaemia-ecg-library/
Hypoparathyroidism
Hypoparathyroidism is a condition of parathyroid hormone deficiency. It often occurs after surgery to the thyroid, parathyroid or laryngeal malignancies. Without appropriate PTH levels the ionised calcium concentration falls hence this condition presents with low serum calcium, high serum phosphate and a low PTH.
Causes
- Post-surgical (80% in adults)
- Extensive irradiation to the face, neck or mediastinum.
- Autoimmune hypoparathyroidism. Riedel’s thyroiditis. Type 1 autoimmune polyglandular syndrome.
- Genetic e.g., DiGeorge syndrome, Kearns-Sayre syndrome
- Rare: secondary aetiologies e.g., infiltrative disease from haemochromatosis, Wilson’s disease.
- Hypomagnesemia and hypermagnesemia are both functional states of hypoparathyroidism.
Presentation
Symptoms of hypocalcaemia
- Muscle twitching or spasm, muscle cramps, abdominal cramps
- Laryngospasm, stridor, wheezing
- Periorbital numbness, tingling, intermittent or persistent paraesthesias
- Palpitations
- Lethargy, confusion, disorientation
- Seizures or coma
Investigations
- Hypocalcaemia is severe if <1.88mmol/L. A low albumin can give falsely low total serum calcium as the calcium ion is highly bound to protein.
Ionised calcium is not affected by plasma albumin so can be a more accurate reflection of calcium levels. - Plasma intact PTH will be low or normal.
- Hypomagnesemia can cause PTH deficiency and subsequent hypocalcaemia. Exclude in patients with suspected primary hypoparathyroidism.
- ECG changes: Prolonged QTc, irregular heartbeat, tachyarrhythmias
Management
In severe symptomatic hypocalcaemia 1st line management is IV Calcium Gluconate.
If hypomagnesemia is present give IV Magnesium or oral replacement with continuous ECG monitoring.
Asymptomatic temporary postoperative hypocalcaemia is treated with routine oral calcium replacement.
Chronic hypoparathyroidism is managed with oral calcium, calcitriol, vitamin D +/- Magnesium.
Human recombinant parathyroid hormone replacement can be used as an adjunct if unsatisfactory response to calcium supplements. It is given as a daily injectable therapy.
Pseudohypoparathyroidism
Pseudohypoparathyroidism is caused by insensitivity of target tissue to the action of PTH in the background of normal renal function. This results in hypocalcaemia, hyperphosphataemia and increased PTH concentration.
Causes
Pseudohypoparathyroidism is a rare disorder caused by genetic mutations. There different types are as follows:
- Type 1a has an autosomal dominant inheritance, inherited from the mother. It presents with hormone resistance and a characteristic skeletal phenotype.
- Type 1b is usually less severe, and it may be due to a sporadic mutation, or inherited in an autosomal dominant fashion.
- Type 1c is like type 1a with hormone resistance and Albright’s hereditary osteodystrophy.
- Type 2’s cause has not yet been identified.
Pseudo-pseudohypoparathyroidism is caused by the same mutation as type 1a and 1b but the mutations are inherited from the paternal side rather than maternal. Paternal inheritance leads to no hormone resistance but presents with the same skeletal phenotype.
Presentation
- Asymptomatic
- Signs of hypocalcaemia
- Muscle cramps
- Paraesthesia lips, fingers, toes – common early symptoms
- Muscle twitches, spasms, or tetany – severe hypocalcaemia
- Stridor
- Lethargy and anxiety
- Confusion, convulsions, arrhythmias
- Clinical signs: Chvostek’s sign and Trousseau’s sign
- Hyperphosphataemia
- Nephrolithiasis
- Cataracts because of calcium phosphate deposition in the eye
- Types 1a and 1c have characteristic skeletal phenotype of Albright’s hereditary osteodystrophy
- Short stature (height <10th percentile)
- Round face
- Dental hypoplasia
- Brachymetacarpals
- Brachymetatarsals
- Developmental delay
- Soft tissue calcification/ossification
- Diagnostic sign: metacarpal shortening classically affecting III, IV and V metacarpals which produces dimpling over the knuckles
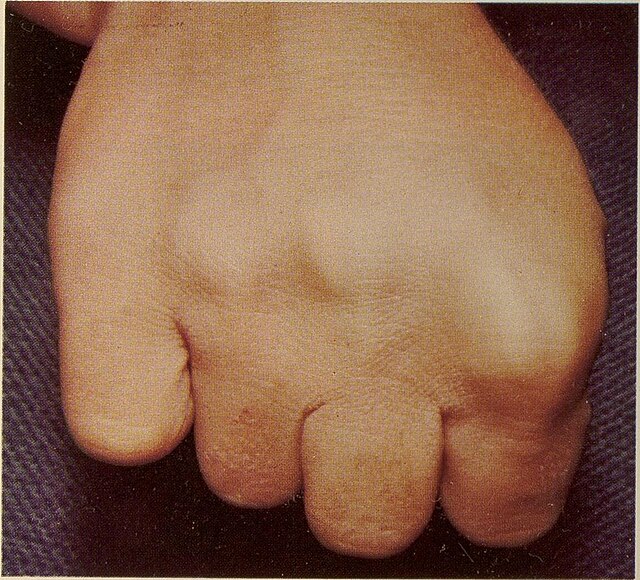
Hands of an adult with Albright’s hereditary osteodystrophy showing knuckle dimpling with clenched fists
Investigations
- Hypocalcaemia, hyperphosphatemia and elevated PTH concentrations with normal Vitamin D strongly point towards pseudohypoparathyroidism.
- Magnesium should be checked to exclude hypomagnesaemia.
- Imaging such as plain radiograph of the hands to reveal metacarpal shortening if skeletal phenotype of Albright’s hereditary osteodystrophy is suspected
- Genetic testing and analysis of GNAS1 gene can confirm diagnosis
Management
The main management involves normalising levels of calcium and phosphate.
Symptomatic hypocalcaemia should be treated as a medical emergency with IV calcium gluconate and ECG monitoring.
Long-term management of hypocalcaemia is with oral calcium supplements such as calcium carbonate or calcium acetate.
References
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

