


 Close
 4th June 2025
Diagnosis
Lymphoedema is a clinical diagnosis based on history and examination. Occasionally laboratory tests will be required if an infective cause (filariasis) is suspected.
History
- Progressive painless swelling (initially distal, then moves proximal)
- Frequently unilateral limb affected
- 90% of cases – lower limb
- Family history – ?primary lymphoedema
- Past travel to filariasis endemic areas
- Malignancy
- Radiotherapy
- Surgical history (especially lymph node biopsy/dissection or surgery in high-risk areas of the axilla/groin)
- Trauma or penetrating injuries to axilla and/or groin
Examination:
- Non-tender swelling and oedema of an extremity
- In early lymphoedema, there may be pitting oedema.
- In late-stage lymphoedema, oedema is usually non-pitting (due to fat hypertrophy and fibrosis of tissue).
- Positive Stemmer’s sign: the examiner is unable to pinch the skin on the dorsum of the patient’s second toe. However a negative Stemmer’s sign doesn’t rule out lymphoedema.
- Skin changes: papillomatosis (projection of dermal papillae in the skin, producing a rough texture) and hyperkeratosis (thickening of the outer skin layer – stratum corneum).
- In advanced lymphoedema, the chronic skin changes can lead to poor wound healing and skin breakdown.

Investigations
- If the diagnosis is unclear, lymphoscintigraphy is an imaging modality that can be used to visualise the lymphatic system and identify abnormalities.
- Lymphoscintigraphy is 96% sensitive and 100% specific for lymphoedema.
- Blood smear (for microfilariae) if lymphatic filariasis is suspected.
- Primary lymphoedema – genetic testing may be performed if syndromic or familial causes are suspected.
Management
Lymphoedema is best managed in a specialist centre with a multi-disciplinary team approach. The mainstay of lymphoedema management is conservative management:
- Elevation of the affected area (although results are limited and effect is usually temporary)
- Exercise – particularly strength training.
- Skin care, such as regular cleaning and moisturising, to maintain healthy skin and reduce the likelihood of infection.
- Protective clothing and shoes to prevent damage to skin.
- Static compression garments or bandaging can help reduce swelling. Garments can be tightened over time, and have been shown to reduce the volume of upper-limb lymphoedema by up to 47%.
- Intermittent pneumatic compression devices (as are used for VTEP in hospitals) may be used alongside static compression garments.
- Combined physical therapy (or CPT) performed by trained therapists; involves skin care, bandaging, manual lymph drainage and exercises
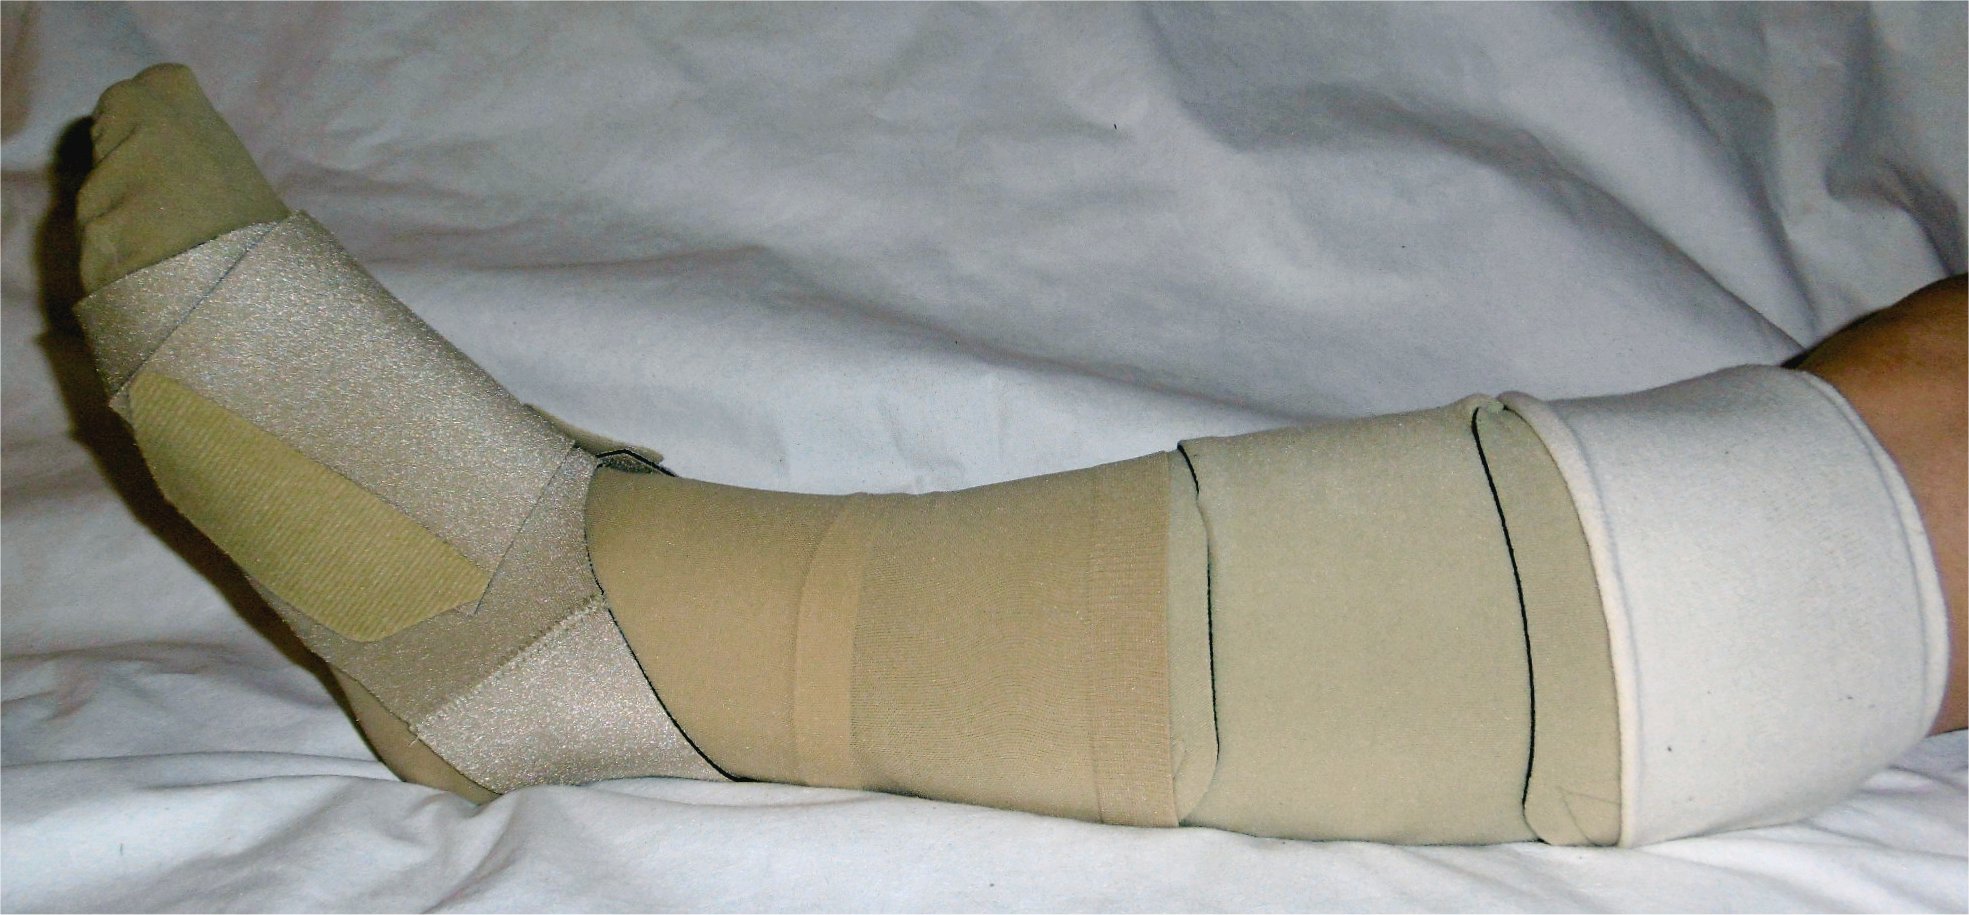
https://commons.wikimedia.org/wiki/File:Klettbandage_mit_Fu%C3%9Fteil.jpg
Medical management
Lymphatic filariasis is treated with combinations of antiparasitic drugs such as diethylcarbamazine and albendazole (depending on the patient’s country of origin), this should be under guidance from an infectious disease specialist.
Patients with underlying infection or cellulitis related to lymphoedema should be treated with antibiotics as for cellulitis, although often require longer courses (and may not be as effective).
Surgical management
In some patients, surgery may be performed if conservative techniques have not helped or they are experiencing severe morbidity associated with their lymphoedema. Surgery can be used to either remove diseased tissue, or repair damaged and/or create new lymph vessels. Surgery is not a curative option and patients will still need to wear compression garments for life.
Complications
- Anxiety and depression is frequently seen in patients with lymphoedema
- Cellulitis
- Impairment in activities of daily living
- Lymphangiosarcoma (a rare malignancy seen in 0.5% lymphoedema patients)
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

