


 Close
 5th June 2025
Hyperpigmentation
Acanthosis Nigricans
Cause and presentation
Acanthosis Nigricans is a cutaneous disorder characterised by velvety plaques of hyperpigmented, papillomatous, hypertrophic skin found on the neck, flexural and intertriginous surfaces. Less commonly, it can also affect the cheeks and dorsal hands. The disorder can be present at birth or early childhood with a familial association. However, it is commonly associated with obesity along with an insulin-resistant state or diabetes. When acanthosis nigricans is associated with obesity, it tends to affect females and Hispanic or black ethnicities. It can also occur with other metabolic, autoimmune, or genetic syndromes, or malignancies such as gastric adenocarcinoma.
Diagnosis
A diagnosis using history and examination is sufficient for Acanthosis Nigricans.
Patients present with darkening and thickening of affected skin. If it is caused by a malignancy, it can have a rapid onset with weight loss. If it is caused by obesity, it may follow weight gain. If it is unilateral or benign then there may be a positive family history.
On physical examination, the lesions are usually found on flexural surfaces as symmetric, hyperpigmented plaques that range in colour from yellow to dark brown. They may be accompanied by skin tags and patients may be overweight. Commonly affected sites include the posterior neck, axilla, vulva, umbilicus, inner thighs, and groins. In malignant Acanthosis Nigricans, there may be mucosal involvement and hyperkeratosis of the palms and soles.
Patients should be checked for type 2 diabetes mellitus (such as fasting glucose and insulin tests) if they are overweight.
They should also be investigated for malignancy if no cause with rapid onset and involvement of mucosal surfaces and palms. The patients usually affected by malignant Acanthosis Nigricans are thin and over 40 years of age. They may also present with generalised pruritus and sudden appearance of multiple seborrheic keratoses. After history and examination an abdominal CT may be needed to check for intra- abdominal malignancy.
A skin biopsy is helpful when the diagnosis of acanthosis nigricans is uncertain. With a skin biopsy epidermal acanthosis with papillomatosis and hyperkeratosis may be seen, which is the cause for the dark clinical appearance.
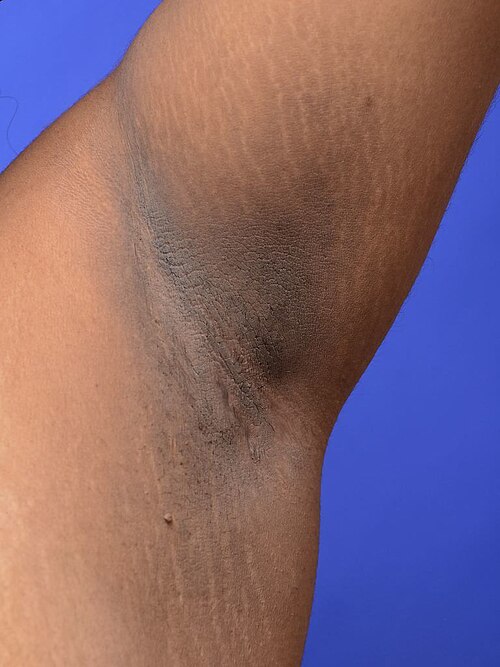
Image Source: Wikimedia Commons (2019). Acanthosis Nigricans, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Acanthosis_nigricans.jpg (Accessed 20 May 2025).
Management
- Treatment of the underlying cause such as obesity, diabetes mellitus or malignancy
- Stop medications that promote hyperinsulinemia
- When hereditary, idiopathic or unresolved after treatment of underlying cause then topical agents used as first line
- First line agents: ammonium hydrate, vitamin D analogues and retinoic acid
- Second-line agents: oral medications such as isotretinoin, metformin, octreotide and acitretin
- Laser therapy if extensive or disfiguring and not responsive to topical or oral therapy
- However, in darker skin types, there is a significant risk of post treatment hypopigmentation
- The last resort is surgical excision when large, disfiguring lesions are not responsive to other treatments.
Drug induced pigmentation
Pigmentation can be triggered by a range of different drugs: the main ones include non-steroidal anti-inflammatory drugs, phenytoin, antimalarials, amiodarone, antipsychotic drugs, cytotoxic drugs, tetracyclines and heavy metal.
Some drugs cause a fixed drug eruption where there is a cutaneous allergic reaction at the area of medication exposure which is followed by localised hyperpigmentation that gradually fades.
Causes
The mechanism involved in drug induced hyperpigmentation varies depending on the drug;
- Heavy metals (iron, silver and gold) may be deposited in the dermis following destruction to dermal vessels and can cause skin colour changes.
- Drug-pigment complexes can form with certain drugs that react with melanin. These complexes form by a trigger such as sunlight.
- Some medication will cause an increase of melanin from non-specific post-inflammatory change in predisposed individuals. This can be aggravated by sunlight.
- Other medications may cause pigmentation from accumulating and/or reacting with other substances found in the skin.
Clinical features
The clinical presentation will vary depending on causative drug;
- Heavy metals- iron can cause dark brown pigmentation, gold can cause diffuse golden-brown pigmentation, silver can cause diffuse greyish pigmentation. The pigmentation can be permanent.
- Tetracycline (minocycline)- blue pigmentation affecting nails, skin, and scars. Older patients with higher doses of tetracycline are likely to experience these skin changes. Can take many years once a drug is discontinued for pigmentation to clear.
- Antipsychotic (chlorpromazine and related phenothiazines)- blue-grey pigmentation on sun exposed sites and conjunctiva of eyes.
- Phenytoin/ anticonvulsants- Symmetrical dark brown patches like melasma that clear a few months after drug discontinued. Found on the neck and face usually.
- Antimalarials (chloroquine/ hydroxychloroquine)- blue-grey pigmentation found on face, neck, lower leg and forearms. With prolonged use of medication, blue black patches on sun-exposed areas. May also develop changes on nail bed, cornea and retina.
- Cytotoxic drugs (busulfan/cyclophosphamide/bleomycin/Adriamycin)- hyperpigmentation on nails usually that is banded or diffuse.
- Amiodarone- Blue-grey pigmentation on sun exposed sites. It reverses on discontinuation of the drug, but this can take up to a year.
- NSAID- Demarcated erythematous lesions from fixed drug eruptions that resolve leaving a brown pigment and are normally found on the face, extremities and genitalia.
Management
The mainstay of management is discontinuing the offending drug so the hyperpigmentation fades. However, the improvement in pigmentation can take months, years or it may be permanent. Sun protection is also advised as medication that causes skin pigmentation may cause photosensitivity reactions. In amiodarone-induced skin pigmentation laser treatment has been successful.
Post inflammatory hyperpigmentation
Post inflammatory pigmentation is the transient pigmentation that occurs from various triggers such as injury or inflammatory disorder of the skin. It causes melanosis of the epidermal or dermal layer of the skin. It is typically seen in darker skinned individuals.
Causes:
- Inflammatory skin disorders- eczema, psoriasis, lichen planus, acne, systemic lupus erythematosus, dermatitis, cutaneous T-cell lymphoma
- Injury to skin like thermal burn
- Allergic reactions
- Phototoxicity
- Iatrogenic causes- treatment with a fully ablative laser on dark skinned patients
- Drugs- chlorpromazine, chloroquine, arsenic, tetracycline, bleomycin, doxorubicin, 5 – fluorouracil, busulfan, antimalarial drugs and hormones (oestrogen)
- Ultraviolet light exposure
- Exposure to chemicals- silver, gold, and arsenic
- Idiopathic- No cause identified
Presentation
Hyperpigmented patches occur at the site of the original exposure or insult, presenting as light brown to black macules or patches with poorly irregularly defined borders with minimal surface change. The patches can darken when exposed to sunlight.
Diagnosis
Usually, a history and examination are enough to diagnose post inflammatory hyperpigmentation. When diagnosis is not clear a skin biopsy may be done with histopathology showing patchy epidermal melanosis and/or dermal melanosis.
A Wood’s lamp can also be used to distinguish dermal from epidermal hyperpigmentation however post inflammatory hyperpigmentation can be dermal or epidermal. Epidermal lesions are generally easier to treat than dermal pigmentation.
Treatment
Usually, the pigmentation resolves without any treatment. However, it is slow to resolve even with treatment. To prevent further hyperpigmentation, avoiding sun exposure is advised using a high- factor sun cream. If an underlying cause is identified, then treating this will help. Medications that can be used include retinoids, azelaic acid, topical steroid, and hydroquinone. However, there are safety concerns for hydroquinone including carcinogenesis and ochronosis- which is the development of blue-black discolouration of tissues.
Nutritional causes of hyperpigmentation
Pellagra
This is caused by vitamin B3 (niacin) deficiency that leads to a systemic disease. Vitamin B3 is vital for maintaining cell function including energy production, metabolism, and DNA repair. Pellagra is more common in developing countries as it is associated with poverty and malnutrition. It is rarely seen in developed countries as many foods are fortified with niacin. However, it may be seen with chronic alcohol abuse, gastrointestinal malabsorption, anorexia nervosa, self-imposed diets, or medications such as isoniazid and antidepressants.
When there is a deficiency, it leads to the primary symptoms of dermatitis, diarrhoea, dementia and even death if not treated. Cutaneous features vary and include symmetrical, bilateral, photosensitive, well-defined erythematous rash on sun-exposed areas. These can progress to becoming hyperpigmented, bullous lesions with desquamation. It is described as Casal necklace when there is a hyperpigmented band around the neck and as pellagrous glove and boot when there are hyperpigmented plaques and fissuring of hands and feet. In some instances, there may be pruritus, nasolabial seborrhoea and vulvovaginitis. Patients may present with associated gastrointestinal symptoms, such as loss of appetite, vomiting, abdominal pain and diarrhoea. Neuropsychiatric features may be seen as a late presentation of pellagra, and include weakness, headache, confusion, irritability, tremor, depression, dementia, and encephalopathy.
It is diagnosed clinically and a quick response to a course of niacin supplementation confirms diagnosis. Findings on skin biopsy include non-specific dermatitic changes, perivascular lymphohistological infiltrates in upper dermis, mild oedema in papillary dermis, capillary dilatation, and dermal fibrosis. Epidermal changes include early subcorneal blisters, pallor of upper epidermis, hyperkeratosis, parakeratosis, epidermal atrophy, detachment, and necrosis. Photosensitivity testing can also be used to check for reactions such as erythema, swelling, blistering and pruritus. The cause will also need to be investigated and if dietary deficiency is unlikely other causes need to be identified. Concomitant nutritional deficiency including checking iron, thiamine, riboflavin, pyridoxine, cyanocobalamin, and folic acid. To check for chronic alcohol use liver function tests should be done. For malnutrition examination of the stool and doing full blood count to check for types of anaemia is useful.
Treatment of pellagra includes niacin therapy and the course is dependent on severity of presenting features. Nicotinic acid (niacin) replacement therapy in the form of nicotinamide is preferred because nicotinic acid causes nausea and vomiting, skin flushing and tingling of tongue or lower jaw. However, improvement in cutaneous and neurological features is seen within the first 48 hours of treatment. Other vitamins should also be replaced if the patient is found to be deficient in these including riboflavin and pyridoxine.
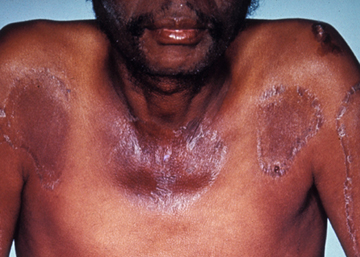
Image Source: Wikimedia Commons (2010). Pellagra, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Pellagra3.jpg (Accessed 20 May 2025).
Vitamin B12 deficiency
Vitamin B12 (cobalamin) is an essential vitamin important for DNA synthesis and cell metabolism. When there is a deficiency, it presents with neurological, psychiatric, and haematological disorders. Vitamin B12 deficiency occurs due to lack of dietary intake or inadequate absorption. The most common cause is pernicious anaemia where there is a loss of intrinsic factor from autoimmune atrophic gastritis. Other causes include patients with chronic malabsorption, vegan diet, patients with history of gastric bypass and certain medications such as metformin and proton pump inhibitors.
Symptoms and signs include:
- Neurological- depression, cognitive impairment, dementia, sensory deficit, gait abnormalities, peripheral neuropathy, spastic paraparesis, paraesthesia, sub-acute degeneration of the spinal cord. Early signs and symptoms can be subtle but severe deficiency can cause permanent neurological damage.
- Cutaneous- pallor, jaundice, and hyperpigmentation. The hyperpigmentation can occur in the palms or on the tongue
- Other- fatigue/ dyspnoea (megaloblastic anaemia)
Investigations:
- Full blood count- look for anaemia
- Peripheral blood smear- check for macro-ovalocytes and hyper segmented neutrophils
- Vitamin b12 levels
- Serum folate
Management:
- Identify and treat underlying cause
- Vitamin b12 replacement (cyanocobalamin)
- Route (oral or intramuscular) and treatment course depends on symptom severity
- When intramuscular is preferred (such as in severe anaemia/neurological disease), hydroxocobalamin is used in the UK over cyanocobalamin as it is retained longer in the body
Kwashiorkor
Kwashiorkor is also referred to as oedematous malnutrition. It generally happens when receiving a monotonous cereal-based diet. Marasmic kwashiorkor is the presence of severe wasting with oedema. It normally occurs in children from the time of weaning to 5 years of age but can present later when associated with HIV or tuberculosis.
There is no confirmed cause for Kwashiorkor, however a corn-based diet, recent weaning, measles, or diarrhoeal illness have been associated with the disease. It is usually seen in food insecure regions of the world and if it is seen in the developed world it is associated with an underlying disease such as tuberculosis, HIV, or severely restricted diet.
It is a clinical diagnosis and oedema is the defining characteristic. The oedema starts in the feet and can spread if not treated. The oedema is usually bilateral and pitting. Skin manifestations are also seen in this disease. Hyperpigmentation starts as spots that become hard, scaly, and then fuse, followed by desquamation and cracking of skin. It can also present as dry, thin, shiny, or wrinkled skin from atrophy of the basal layers of the epidermis with hyperkeratosis. Ulceration may also appear in the genital, peri-anal, body creases and exposed surfaces.
Complications:
- Infections
- Hypoglycaemia
- Hypothermia
- Xerophthalmia
- Electrolyte disturbance
- Cardiac failure
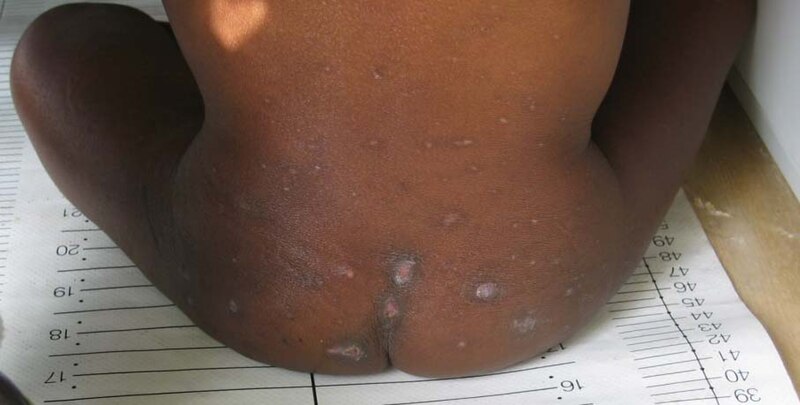
Image Source: Wikimedia Commons (2009). Kwashiorkor Dermatosis, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Kwashiorkor_dermatosis.jpg (Accessed 20 May 2025).
Treatment includes giving therapeutic food at home or in the hospital depending on the severity. The treatment goal is to resolve oedema and improve the patient’s weight. They may also have concomitant infections requiring treatment.
Endocrine causes of hyperpigmentation
Addison’s Disease
Addison’s disease (primary adrenal insufficiency) is the failure of the adrenal glands to synthesise enough hormones such as glucocorticoid (cortisol) and/or mineralocorticoid (aldosterone). Secondary insufficiency is where there is insufficient pituitary or hypothalamic stimulation of the adrenal glands. Addison disease affects more women than men and the commonest age of onset is 30-50 years old.
The most characteristic feature in Addison’s disease is the hyperpigmentation. There is generalised mucosal and cutaneous hyperpigmentation, which is more prominent in areas of increased friction like elbow, knuckles, knees, palms, and scars. The hyperpigmentation is as a result of high levels of adrenocorticotrophic hormone (ACTH), which stimulates dermal melanocortin receptors. It is only present in Addison’s disease and not in secondary adrenal insufficiency.
Other clinical features:
- Progressive fatigue
- Generalised weakness
- Weight loss
- (Postural) hypotension due to salt loss and dehydration
- Hyponatraemia
- Hyperkalaemia
- Gastrointestinal symptoms- nausea, vomiting, abdominal pain
- Changes in blood count (anaemia, eosinophilia and lymphocytosis)
- Hypoglycaemia
- Salt craving
- Loss of axillary and pubic hair in premenopausal women
- Life threatening adrenal crisis- hypotension, circulatory failure
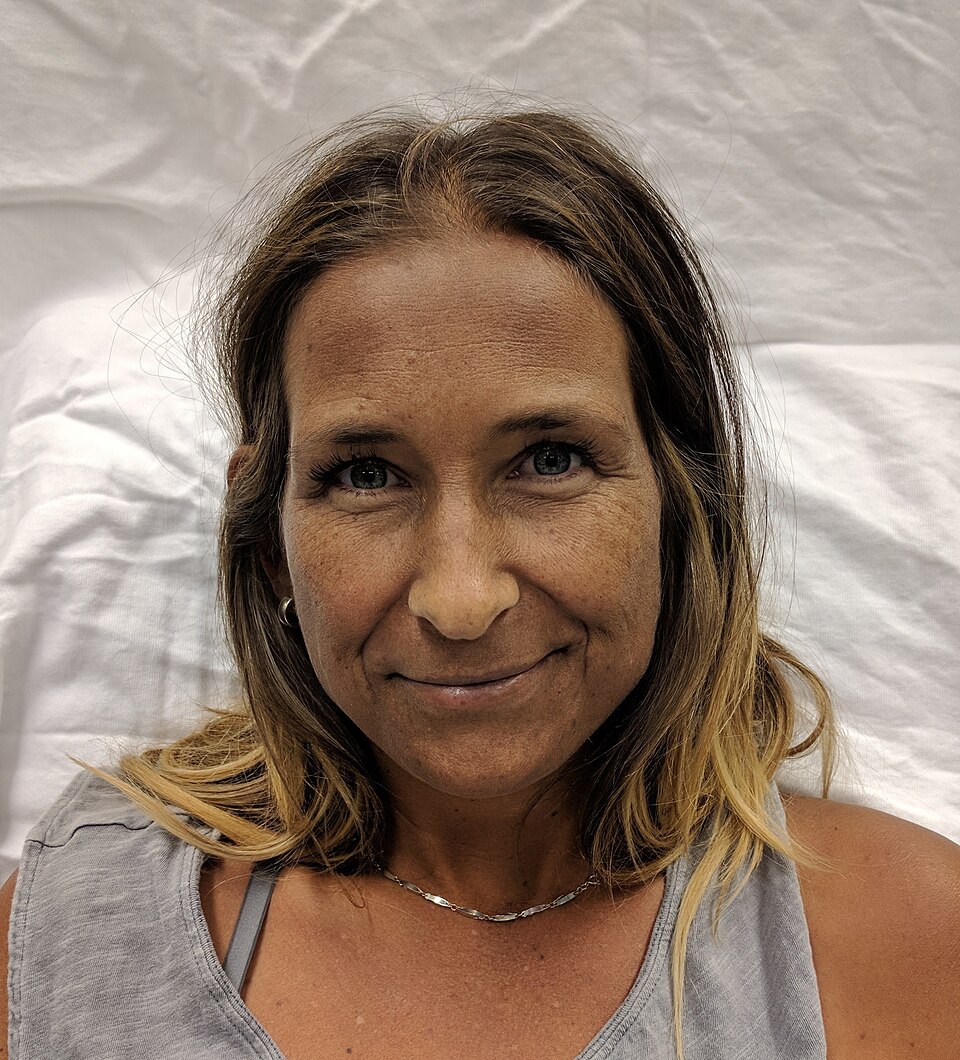
Image Source: Wikimedia Commons (20187). Women With Addison, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:WomenWithAddison.jpg (Accessed 20 May 2025).
Investigations for Addison’s disease include measuring serum cortisol and ACTH, an ACTH stimulation chest, and imaging of the adrenal glands.
First line treatment includes mineralocorticoid and glucocorticoid replacement therapy to mimic endogenous hormonal secretions, which are given for life.
Cushing Syndrome
Cushing syndrome is caused by prolonged multiorgan exposure to elevated levels of endogenous or exogenous glucocorticoids.
The most common cause of Cushing syndrome is exogenous corticosteroid exposure.
Cushing syndrome can cause skin pigmentation, but this is only seen in ACTH- dependent causes. More common cutaneous manifestations include skin thinning, violaceous striae and easy bruising.
Other clinical features:
- Weight gain with central obesity
- Facial rounding and plethora
- Unexplained fractures (premature osteoporosis)
- Hirsutism
- Menstrual irregularities
- Proximal muscle weakness
- Supraclavicular and dorsocervical fat pad
- Deep vein thrombosis and pulmonary embolism (due to hypercoagulable state)
- Metabolic complications- diabetes mellitus, dyslipidaemia, metabolic bone disease, hypertension
To confirm Cushing syndrome, check for elevated cortisol levels in urine, blood, or saliva. The dexamethasone suppression test can also be done. Then investigations for determining the cause of Cushing syndrome should be done.
The hyperpigmentation and skin changes that are associated with Cushing syndrome can be treated by targeting the underlying cause. This may include surgical or medical management.
Nelson’s syndrome
Nelson’s syndrome is a rare but potentially life-threatening condition. It is when an ACTH secreting tumour develops after total bilateral adrenalectomy for Cushing’s disease. The pathophysiology is poorly understood but risk factors include rapid rise in ACTH following trans-sphenoidal surgery, longer duration of Cushing’s disease, younger age, and lack of cortisol suppression on high dose dexamethasone test before a trans-sphenoidal surgery.
The most common and early symptom of Nelson’s syndrome is noticeable hyperpigmentation due the action of ACTH on the melanocytes. Pigmentation can occur in scars, areolae, and creases of hands. A dark line from the pubis to umbilicus may also be visible which is called linea nigra. Some patients that develop hyperpigmentation after bilateral adrenalectomy may not fully develop Nelson syndrome.
Other clinical features:
- Visual field defects
- Headaches
- Testicular pain
- Delayed puberty
- Diplopia and cranial nerve lesions
- Papilloedema
- Hypopituitarism: diabetes insipidus, hypothyroid, galactorrhoea, amenorrhoea, erectile dysfunction
To confirm Nelson’s syndrome, increasing levels of ACTH with an enlarging pituitary mass after total bilateral adrenalectomy is needed. The mass can be identified by pituitary imaging. Other hormones such as thyroxine, thyroid-stimulating hormone and sex hormones may be low, but prolactin may be high.
Nelson’s syndrome is managed by trans-sphenoidal resection of the pituitary tumour. Adjunctive irradiation will improve prognosis and reduce recurrence of the tumour. In the long-term hormone replacement may be needed.
Pregnancy
During pregnancy there may be changes to the skin due to alteration in sex hormones, immune system, and cardiovascular system. The cutaneous features in pregnancy are common and considered physiological.
Hyperpigmentation is a common feature in pregnancy due to the synergistic increases in oestrogen and progesterone which stimulates melanogenesis. Linea nigra, darkening of pigmented areas (i.e., nipples, areolae, genitals) and generalised pigmentation usually presents in the first trimester and is more common in Fitzpatrick skin types IV-VI. Melasma is more typical in the second half of pregnancy and in darker skinned individuals. In Melasma the lesions are irregular, symmetrical, and sharply marginated on the face.
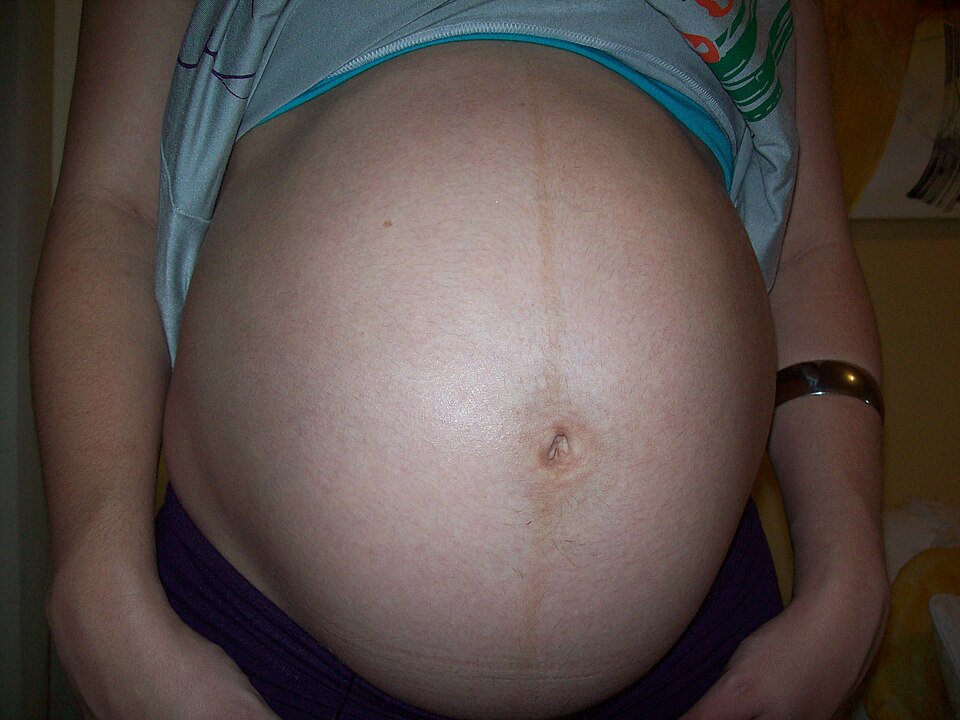
Image Source: Wikimedia Commons (2007). Giovana, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Giovana.jpg (Accessed 20 May 2025).
Pre-existing melanocytic naevi may darken in pregnancy due to increased circulating melanocyte stimulating hormone. With changing pigmented lesions, melanoma should be investigated for early referral, skin biopsy and with the use of dermoscopy.
Hyperpigmentation may also be seen in the nails as benign, uniform, and symmetrical across multiple nails. However, they should be investigated for melanoma when there is irregular pigmentation with cuticle involvement.
Management is not usually required as the physiological skin changes during pregnancy improve postpartum. However, the hyperpigmentation may take many months and sometimes may not be completely clear. With melasma, sun protection is advised.
Metabolic causes of hyperpigmentation
Cirrhosis
Cirrhosis is the diffuse pathological process characterised by fibrosis and change of normal liver architecture into structurally abnormal nodules.
Hyperpigmentation is a common clinical manifestation of cirrhosis. Skin changes that may be seen in some patients include a grey complexion and black discolouration in distal extremities, the pathogenesis of this is not fully understood and may be multifactorial due to bilirubinaemia, hormone changes associated with cirrhosis, or association with haemochromotosis. Also, due to extravasation of red blood cells and deposition of hemosiderin from lower extremity oedema and obstruction of venous reflux, pigmentation may be seen on the tibia.
In patients presenting with hyperpigmentation that may be suggestive of cirrhosis, investigations including blood tests, imaging and referral to gastroenterology for ongoing management should be considered. Management of hyperpigmentation related to cirrhosis requires the underlying causes of cirrhosis to be treated and managed. For patients with pruritus, non-sedating antihistamines, topical ammonium lactate and cholestyramine may be helpful.
Haemochromatosis
Haemochromatosis is a multisystem autosomal recessive disorder caused by a defect in the ability to downregulate iron absorption leading to iron overload and deposition in multiple body tissues.
It is most commonly due to a genetic condition from gene mutations but other causes include iron loading anaemias, parenteral iron overload, chronic liver disease and dysmetabolic iron overload syndrome.
It can lead to hyperpigmentation of the skin, but this is a rare and late finding. The pigmentation that occurs is distinctive and looks like skin bronzing. The finding can be confused with a tan.
Other clinical features include:
- Fatigue, depression, poor memory
- Arthralgia
- Loss of libido, impotence, early menopause, changes to menstrual cycle
- Loss of body hair
- Cardiomyopathy
- Diabetes
- Liver dysfunction
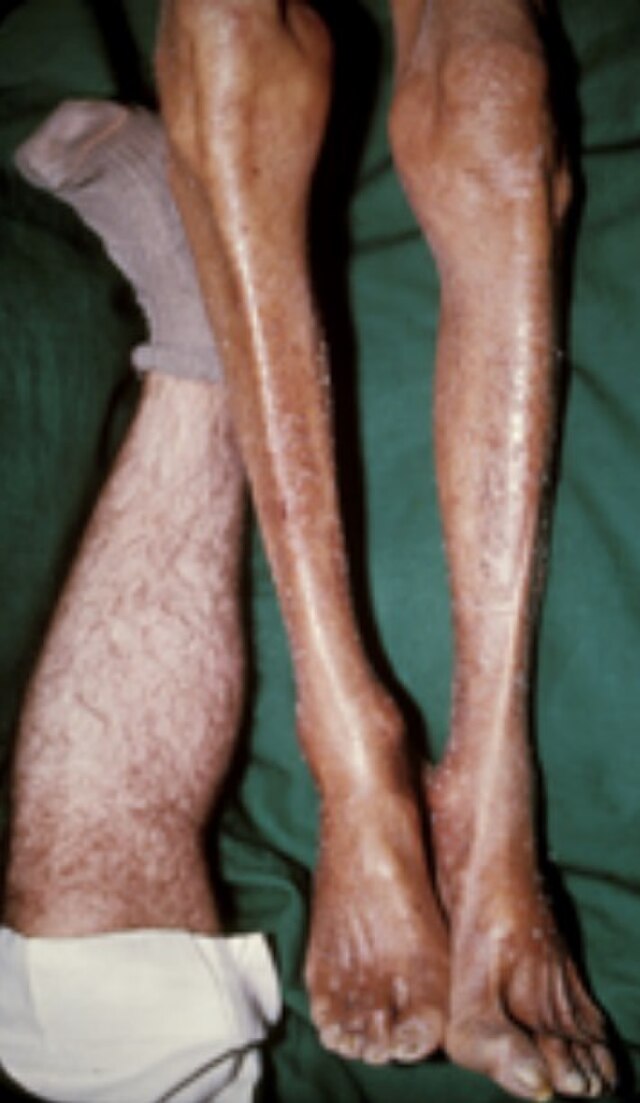
Image Source: Wikimedia Commons (2008). Hemochromatosis Skin, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/w/index.php?search=HemochromatosisSkin.jpg&title=Special:MediaSearch&type=image (Accessed 20 May 2025).
Haemochromatosis is suggested by raised transferrin saturation and ferritin on blood tests. Other tests include liver MRI, liver biopsy, LFT, fasting blood glucose, ECG, echocardiogram, bone densitometry and measuring sex hormones.
Management involves preventing iron overload in early- stage disease and removing excess iron from body stores in late-stage disease. Treatment includes:
- Phlebotomy regimen- removal of blood
- Avoid iron/ iron containing supplements
- Avoid vitamin C/ vitamin C containing supplements
- Prevention of worsening liver disease: Avoid excess alcohol, hepatitis vaccination/treatment, liver transplant
Complications include cirrhosis, hepatocellular cancer, arthropathy, diabetes and heart disease.
Porphyria Cutanea Tarda
Porphyria cutanea tarda is an acquired metabolic disorder of haem biosynthesis. It can be inherited but this is rarer. It occurs when there is significant deficiency of the enzyme uroporphyrinogen decarboxylase in the liver. The substrates of the deficient enzyme, which are porphyrinogens, accumulate in the liver and are oxidised to porphyrins and transferred to the skin causing cutaneous symptoms and signs. It is usually seen in middle-aged men and women.
Factors that contribute to susceptibility of porphyria cutanea tarda include hepatitis C, alcohol use, haemochromatosis, oestrogen treatment, HIV, smoking and uroporphyrinogen decarboxylase (UROD) mutations.
Signs and symptoms:
- Skin hyperpigmentation
- Photosensitivity
- Blistering and crusted skin lesion on sun exposed sites
- Hypertrichosis
- Sclerodermatous thickening
- Dark/ reddish urine
- Skin fragility
- Blister formation from minor trauma
- Liver damage
Investigations to confirm porphyria cutanea tarda involves finding significant increase in porphyrins and other related haem precursors in the urine, blood, and faeces. Genetic testing can be considered for UROD and haemochromatosis mutations for genetic counselling and treatment options too.
Treatment depends on the cause. In iron overload, regular phlebotomy is advised. Management options may also include reducing sun exposure, alcohol, smoking, oestrogen treatment and iron supplements. Specifically in iron overload or haemochromatosis regular venesection is advised. If there is no haemochromatosis or in those who cannot tolerate phlebotomy, low dose hydroxychloroquine or chloroquine is an option.
Renal Failure
Renal failure is defined as abnormalities in kidney structure or function. The most common causes for renal failure include diabetes mellitus and hypertension. Other causes include cystic kidney disorders, obstructive uropathy, glomerular nephrotic and nephritic syndrome.
Hyperpigmentation on the skin and nails is a feature in renal failure and is due to increase in skin melanin from excessive beta-melanocyte stimulating hormone. The hyperpigmentation may also be persistent and progressive despite dialysis as beta-melanocyte-stimulating hormones are poorly dialysed. Hyperpigmentation may also be from causes of renal failure such as diabetes mellitus complications. In diabetes mellitus, acanthosis nigricans may be present which is thickened, velvety, hyperpigmented plaques found on neck folds, axillae, and groin. Another cause of renal failure is neurofibromatosis which leads to renal artery stenosis, infarction, and aneurysm. The hyperpigmentation of this disease include café au lait macules which are flat hyperpigmented macules.
Other signs and symptoms:
- Haematuria
- Proteinuria
- Reduced GFR with elevated serum creatinine
- Pulmonary oedema- dyspnoea and orthopnoea
- Uraemia- fatigue, anorexia, nausea, vomiting, restless leg, pruritus, cognition abnormalities, seizures, coma
- Hypertension
- Peripheral oedema (from sodium retention and hypoalbuminaemia)
- Pallor due to anaemia
- Diabetic or hypertensive retinopathy
The following investigation are used in renal failure:
- Urea and electrolytes
- Urinalysis and protein/creatinine ration or albumin/creatinine ratio
- Full blood count
- Renal ultrasound with duplex, MRI
- Renal biopsy
The mainstay management of the dermatological manifestation of renal failure treatment of the underlying renal failure, with adjuncts such as antihistamines and topical creams being useful for some patients.
Genetic causes of hyperpigmentation
Peutz-Jeghers Syndrome
Peutz-Jeghers syndrome is a rare, autosomal dominant disorder characterised by multiple intestinal hamartomatous polyps caused by a germline mutation in the STK11 gene.
Symptoms and signs:
- Characteristic pigmented macules of lips and gum. Can also be seen on hands, feet, anus, and genitals. With macules on the lips they cross the vermillion border and compared to freckles they are darker and densely clustered. Pigmentation presents in infancy and fades with time however buccal pigmentation may persist.
- Polyp growth leading to bleeding, abdominal pain, intussusception, obstruction, iron deficiency anaemia and fatigue
- Abdominal pain in young patient from obstruction or intussusception
- Unexplained intestinal bleeding or iron deficiency anaemia in a young patient
- Rectal prolapse, precocious puberty or nasal/bronchial/biliary tract/ uterine/ bladder polyps
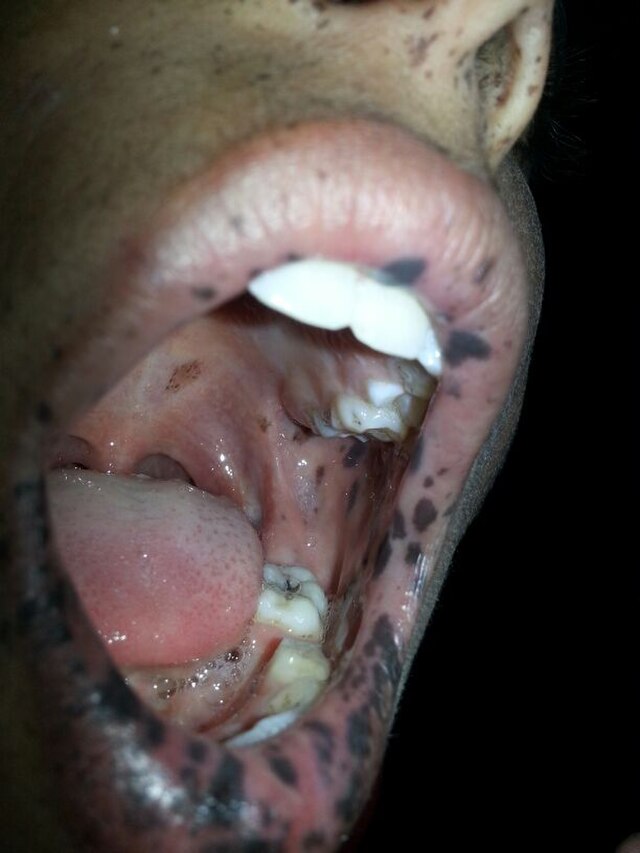
Image Source: Wikimedia Commons (2013). Peutz-Jeghers Syndrom, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/w/index.php?search=Peutz-Jeghers-Syndrom.JPG&title=Special:MediaSearch&type=image (Accessed 20 May 2025).
There is a high cancer risk (up to 93%) including gastro-oesophageal, colorectal breast, small bowel, and pancreas cancers.
It is diagnosed if a person satisfies one from the clinical criteria:
- Two or more histologically confirmed Peutz-Jeghers-type hamartomatous polyps
- Any number of Peutz-Jeghers-type polyps with a family history of Peutz-Jeghers syndrome in a first degree relative
- Characteristic mucocutaneous pigmentation with a family history of Peutz- Jeghers syndrome
- Any number of Peutz-Jeghers-type polyps and characteristic mucocutaneous pigmentation
If the above is met, then the individual should also undergo genetic evaluation for mutations in STK11 gene. Endoscopic evaluation can also be done as surveillance in these patients. It can show diffuse hamartomatous polyposis.
Management includes surgical excision of the lesion and gene counselling for affected family members.
Xeroderma Pigmentosum
This is a rare, autosomal recessive genetic disorder characterised by a DNA repair defect which consequently prevents the response to DNA damaged by UV radiation.
It presents as photophobia, blistering or persistent erythema after sun exposure, or the development of facial freckle-like pigmentations (lentigos) within the first few years of life. This is due to the severe sensitivity to sunlight and ultraviolet radiation. Patients are also at increased risk of developing hearing loss, neurologic impairment, and cutaneous cancers.
It is diagnosed clinically from presentation and family history. It can also be confirmed by genetic testing by identifying the pathogenic gene mutation.
The mainstay of management is reducing exposure to ultraviolet radiation. Premalignant and malignant skin lesions should also be treated depending on the type. These patients should have regular follow up assessment for skin, eyes, and neurologic development. Genetic counselling may also be beneficial to patients.

Image Source: Wikimedia Commons (2008). Xeroderma Pigmentosum, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/w/index.php?search=Xeroderma_pigmentosum_02.jpg&title=Special:MediaSearch&type=image (Accessed 20 May 2025).
McCune-Albright Syndrome
McCune-Albright syndrome is a rare condition caused by a spontaneous mutation in the GNAS1 gene occurring in the development of an embryo. It only affects a subset of the patient’s cells.
These are the following clinical characteristics for McCune-Albright syndrome:
- Cutaneous features such as café au lait macules seen in birth or infancy. The macules are large and have irregular margins.
- Polyostotic fibrous dysplasia of bone affecting craniofacial, axial and/or appendicular skeleton
- Precocious puberty
- Hyperparathyroidism and hyperthyroidism
The diagnosis is based on the above clinical manifestations and genetic sequencing can be used to confirm diagnosis in ambiguous cases.
There are no specific treatments for the dermatological lesions associated with McCune-Albright syndrome, and treatment focuses on the management of skeletal lesions and precocious puberty.
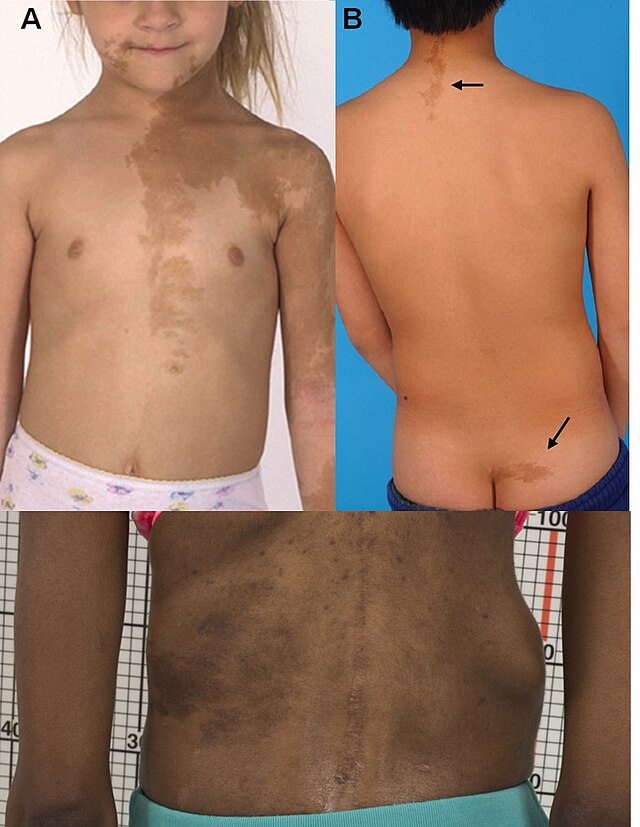
Image Source: Wikimedia Commons (2008). Mccune-Albright Syndrome, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/w/index.php?search=Mccune-albrightsyndrome1.jpg&title=Special:MediaSearch&type=image (Accessed 20 May 2025).
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

