


 Close
 29th July 2026
Cutaneous drug reactions and allergic skin disorders
Erythema Multiforme
Background
Erythema Multiforme (EM) is an immune-mediated hypersensitivity reaction affecting cutaneous and mucosal membranes. The condition is characterised by typical targetoid lesions with concentric rings that develop in a symmetrical acral distribution with mucosal involvement in a small number of patients. The majority of cases are triggered by herpes simplex virus (HSV), but other triggers exist including drugs and vaccinations. It is self-limiting but has a tendency to recur in 30% of affected patients. Although historically believed to be part of the same disease process that causes Steven-Johnsons Syndrome(SJS)/Toxic Epidermal Necrolysis (TEN) , emerging research has provided evidence to suggest EM is its own disease entity.
Epidemiology
The condition is relatively rare with an estimated annual incidence of 1%. EM has a male predominance of 3:2 and most commonly presents in the second and third decade of life. No association with race has been found. Specific HLA allotypes such as HLA-DQB1*0301 are thought to also increase risk of developing EM, particularly triggered by HSV.
Aetiology
The exact pathogenesis of EM remains unclear but the underlying mechanism is proposed to be a type IV hypersensitivity reaction caused by cytotoxic T cells. A number of different causes exist, summarised in the table below.
| Infectious | Medication-related | Other |
| HSV type 2 | Antibiotics | Inflammatory Bowel Disease |
| SARS-CoV-2 | Anti-epileptics | Hepatitis C |
| Orf | NSAIDS | Leukaemia |
| Vulvoginal candidiasis | Vaccinations | Lymphoma |
| Influenza virus | Malignancy | |
| Epstein-Barr Virus | ||
| Cytomegalovirus | ||
Table 1: Causes of erythema multiforme
Diagnosis
Classification
| EM Minor | EM Major |
|---|---|
| Affects < 10% of Total Body Surface Area | Affects > 10% of Total Body Surface Area |
| Acral distribution | Acral distribution |
| Target lesions | Target lesions |
| No mucocutaneous involvement | Involvement of 1 or more mucocutaneous sites |
Table 2: Classification of Erythema Multiforme
Clinical features
Target lesions eruption over 72 hours over the distal, extensor surfaces. Prodromal symptoms are rare.
Mucosal involvement includes oral blistering and genital ulceration. Symptoms usually heal within 2-3 weeks with minimal scarring although hyperpigmentation has been reported.
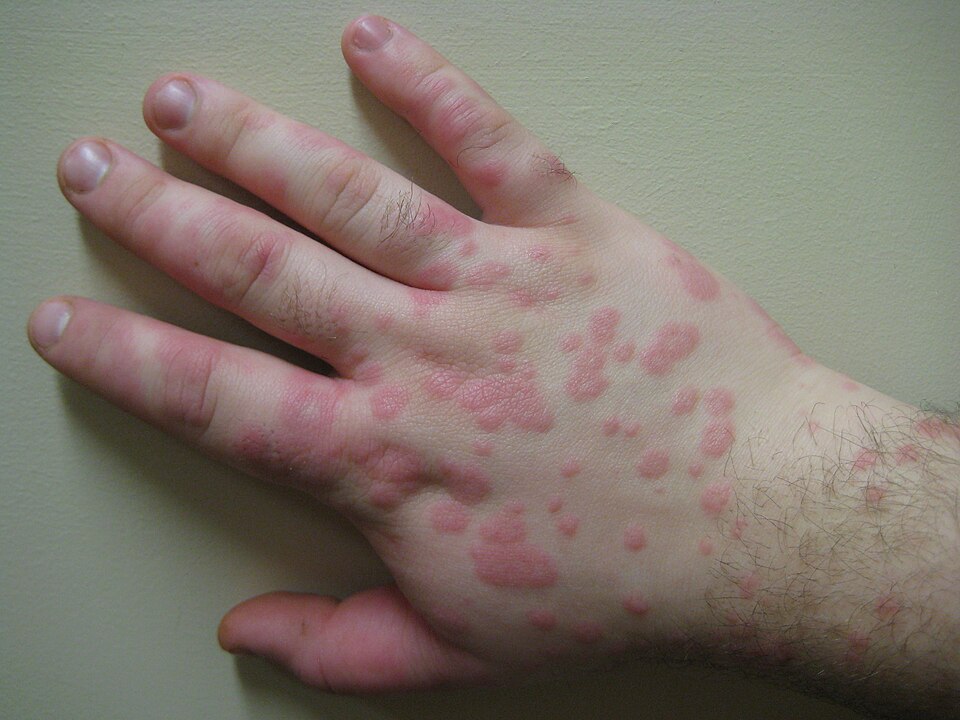
Target lesion on the dorsum of the hand.
Image Source: Wikimedia Commons (2009). Erythema Multiforme Minor of the Hand, Licensed under a creative commons licence. Available for free at https://commons.wikimedia.org/wiki/File:Erythema_multiforme_minor_of_the_hand.jpg (Accessed 19 May 2025)
Differential Diagnosis
- Rowell’s syndrome (targetoid lesions in Systemic Lupus Erythematosus)
- Pemphigus Vulgaris
- Urticaria
- Polymorphous light eruption
- Steven Johnson’s syndrome/Toxic Epidermal Necrolysis
- Paraneoplastic pemphigus
Investigations
- Full blood count
- Urea & electrolytes
- Liver function tests
- HSV serology and other infectious disease serology
- Chest X-ray: to look for evidence of mycoplasma pneumoniae as a cause of EM
- Skin biopsy: upper dermal oedema and epidermal keratinocyte necrosis.
- Biopsy is not usually required however may be considered to differentiate from other serious skin reactions.
Medical management
- Omit offending agent or treat the underlying cause
- Emollient
- Prednisolone/methylprednisolone
- Analgesia
- Ocular involvement requires ophthalmology review
- Recurrent disease: 6 months of anti-fungal treatment (vanciclovir/aciclovir) whether or not a clear trigger has been identified.
Complications
- Microstomia secondary to lip scarring
- Secondary bacterial infection
Stevens-Johnsons syndrome/Toxic Epidermal Necrolysis
Background
Steven-Johnson’s Syndrome (SJS) and Toxic Epidermal Necrolysis (TEN) are severe skin reactions affecting both cutaneous and mucosal tissue. The two conditions are a continuum of the same disease process differentiated by the total body surface area (TBSA) affected. Although rare, SJS/TEN are associated with a high mortality rate, 10% and 30% respectively. The main causative factor is medication however infection and malignancy can also trigger the reaction.
Epidemiology
Both SJS and TEN are relatively rare with an estimated incidence of between 4 to 7 cases per million per year. The conditions have a female predominance, affect all ages and are twice as common in Asian and black populations. Several HLA allotypes, in particular, HLA-B*1502 in Han Chinese, Thai, Malaysian and South Indian patients taking anticonvulsants and Europeans with HLA-B*5701 allotype taking abacavir or HLA-A*3101 taking carbamazepine have been associated with an increased risk of SJS/TEN.
Aetiology
Medications remain the most common cause of SJS/TEN. The commonest causes are summarised in the table below:
| Medications | Other causes |
|---|---|
| Anti-convulsants e.g. lamotrigine, carbamazepine, phenytoin, sodium valproate) | Epstein Barr Virus |
| Antibiotics e.g. minocycline, penicillin, cephalosporin quinolones | Herpes Simplex Virus |
| Aciclovir | Cytomegalovirus |
| Retinoids | Mycoplasma pneumonia |
| Anti-cancer drugs | Cancer |
| Biologic drugs | Vaccinations |
| Corticosteroids | |
| Allopurinol | |
| Contrast media | |
| Sulfasalazine | |
| Azathioprine | |
| Non-steroidal anti-inflammatory drugs (NSAIDS) | |
| Anti-HIV medications in particular nevirapine | |
| Antifungals | |
| Antimalarials |
Table 3: Summary of causes of SJS/TEN
The exact mechanism of SJS/TEN is unknown but it is theorised to be an immunological reaction mediated by cytotoxic T-cells (CD8). The condition leads to the separation of the epidermis and papillary dermis at the epidermal-dermal junction with keratinocyte apoptosis.
Diagnosis
Definition
- SJS: <10% TBSA (total body surface area) affected
- SJS/TEN overlap: 10%-30% TBSA (total body surface area) affected
- TEN: >30% body surface area TBSA (total body surface area) affected
Classification may change as the presentation evolves in the earlier phases.
Routine drug testing is not recommended but may be considered in circumstances where the trigger is unknown, or accidental exposure to the drug is possible.
Clinical manifestations
Diagnosis is largely clinical and with presentation evolving in the initial phases of the disease.
Non-specific symptoms include sore throat, fever, headache, arthralgia, vomiting/diarrhoea, and lethargy. These are followed by mucocutaneous disease which peaks at 4 days.
Skin lesions include erythema, blistering which coalesces to form large areas of skin detachment, and macules or purpuric spots.
Mucosal lesions may cause conjunctivitis, oral ulceration and crusted lips, genital ulceration and urinary symptoms, dysphagia and diarrhoea (due to GI tract ulceration), and respiratory symptoms.
Investigations
- Full blood count: anaemia, leucopenia
- Urea and electrolytes
- Liver function tests: mildly raised liver enzymes
- Coagulation profile
- Skin biopsy: histopathology shows epidermal necrosis, keratinocyte necrosis, minimal lymphocytic infiltrate in the dermis.
- Serum granulysin: elevated in initial phase
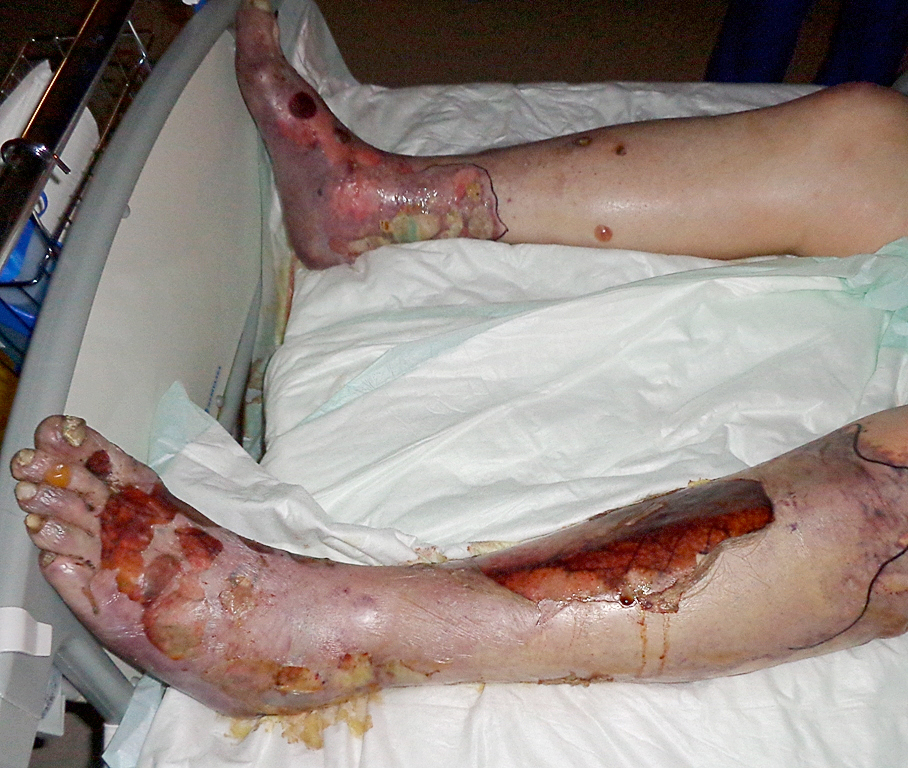
Skin detachment in the lower limbs secondary to TEN.
Image Source: Wikimedia Commons (2017). Necrolysis Epidermalix Toxica, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Necrolysis_epidemalis_toxica_02.JPG (Accessed 19 May 2025).
Prognostic criteria
Two prognostic models exist, the SCORTON (SCORe of Toxic Epidermal Necrolysis) score and the ABCD 10 score. Both scores predict in-hospital risk of mortality.
SCORTON score
A score of 1 point is given for each of the following criteria:
- Age > 40 years
- Malignancy
- Heart rate > 140 beats per minute
- Body surface area detachment is > 10% at presentation
- Serum urea level > 10mmol/L
- Serum glucose > 14mmol/L
- Serum bicarbonate < 20mmol/L
| Score | Percentage risk of mortality (%) |
|---|---|
| 0 – 1 | 3.2 |
| 2 | 12.1 |
| 3 | 35.3 |
| 4 | 58.3 |
| 5 | > 90 |
Table 4: SCORTON scoring and associated mortality
ABCD 10 score
Points are allocated based on the following criteria:
- A: age > 50 years (1 point)
- B: bicarbonate > 20mmol/L
- C: cancer present and active (2 points)
- D: dialysis prior to admission (3 points)
- 10: epidermal detachment > 10% of BSA (1 point)
| Score | Percentage risk (%) |
|---|---|
| 0 | 2.3 |
| 1 | 5.4 |
| 2 | 12.3 |
| 3 | 25.5 |
| 4 | 45.7 |
| 5 | 67.4 |
| 6 | 83.6 |
Table 5: ABCD10 score and associated risk mortality
Differential diagnosis
- Drug related eosinophilia and systemic symptoms (DRESS) syndrome
- Other severe cutaneous adverse reactions (SCARs)
- Erythema multiforme major
- Staphylococcal scalded skin syndrome
- Pemphigus vulgaris or paraneoplastic pemphigus
Medical management
The mainstay of treatment is aimed at adequate wound management to maintain the skin barrier and reduce fluid loss.
Other steps in management include:
- Stop suspected causative agent
- VTE prophylaxis
- Adequate analgesia using validated pain scores/tools
- Wound management
- Strict barrier nursing to reduce infection risk
- Wound swabs from three areas regularly throughout the acute phase of infection
- Wound cleansing with saline +/- antimicrobial such as chlorhexidine
- Emollient use over all epidermis
- Topical anti-microbial to sloughy areas
- Decompression of blisters either by piercing or aspiration of fluid
- Transfer to burns unit if >30% of BSA affected and:
- Clinical deterioration
- Extension of epidermal detachment
- Sub-epidermal pus
- Local sepsis
- Wound conversion
- Delayed healing
- Surgical management
- Removal of necrotic tissue and cleaning under general anaesthetic
- Surgical debridement of wounds
- Closure of wounds using allograft/xenograft of biobrane
- Fluid management
- Fluid input/output
- Replacement as appropriate
- Nutrition
- Continuous enteral nutrition of 20-25kcal/kg/day in the acute phase and 25-30kcal/kg/day in the recovery phase
- Ocular involvement
- Ophthalmologic review
- Ocular hydration drops +/- topical corticosteroid drops
- Prophylactic topical antibiotic
- Urogenital involvement
- Daily urogenital review
- Wound management with white soft paraffin ointment
- Urinary catheter
- Mouth involvement
- Wound management with white soft paraffin ointment
- Anti-inflammatory +/- steroid mouthwash
- Daily saline mouthwash
- Airway involvement
- Transfer to ICU/burn unit
- Fibre-optic bronchoscopy if there is respiratory involvement
Complications
Acute phase complications are responsible for the high mortality rate associated with SJS/TEN (10% and 30% respectively).
- Infection
- Dehydration
- Acute respiratory distress syndrome
- Gastrointestinal: perforation, intussusception, ulceration
- Multi-organ failure
- Disseminated intravascular coagulation
- Venous-thromboembolism
- Malnutrition
Drug-Induced Lupus Erythematosus
Background
Drug induced Lupus is a reaction resembling lupus that occurs after exposure to a drug.
The time between drug exposure can range anywhere between 1 month and 10 years, often leading to difficulty identifying the offending agent.
Drug induced Lupus (DIL) is categorised into three subtypes:
- Drug induced systemic lupus erythematosus (DSLE)
- Drug induced subacute cutaneous lupus erythematosus (SCE)
- Drug induced chronic cutaneous lupus erythematosus (CCLE)
The focus of this chapter will be cutaneous manifestations of drug-induced lupus e.g. SCE, CCLE.
Epidemiology
Drug induced Lupus erythematosus is more common in older age, likely due to the increased use of medications, and shows no gender predominance in contrast to systemic lupus erythematosus (SLE), which affects females 9:1. Additionally, DIL affects patients with lighter skin compared with darker skin types. Risk of development of DIL varies based on the culprit medication. Cutaneous manifestations are not as common in DIL as they are in systemic lupus erythematous.
Aetiology
The pathophysiology of DIL differs based on the offending agent but likely a number of risk factors contribute to genetic risk such as HLA-DR4, HLA-DR0301 and complement C4 null allele. A large number of drugs have been associated with the development.
Drug induced subacute cutaneous lupus erythematosus (SCE)
Associated drugs
- Anti-hypertensive medications e.g. ACE inhibitors, calcium-channel blockers
- Hydrochlorothiazide
- Statins
- Oral anti fungal such as terbinafine
- Biologic agents
- Anti-epileptic medications
- Proton pump inhibitors
- Non-steroidal anti-inflammatory drugs
Clinical manifestations
Symptoms in DIL are milder than idiopathic SLE
- Non-scarring
- Ring shaped or scaly rash in sun-exposed regions of the body
- Widespread
- Blistering at the edges of the rash
Investigations
Bloods:
- ANA: positive
- antiRo/SSA and/or anti-La/SSB: positive
- antihistone: positive
- anti-dsDNA antibodies: absent
- FBC/U&Es/LFTs: normal
Drug induced chronic cutaneous lupus erythematosus (CCLE)
Associated drugs
- Fluorouracil
- TNF inhibitors
- Non-steroidal anti-inflammatory drugs
- Tumour necrosis factor antagonists: infliximab, etanercept
- Voriconazole
Clinical manifestations
CCLE is extremely rare, with an average incubation period reported of around 8 months after exposure to the culprit medication. The mean age of onset is the 6th decade of life. Most commonly CCLE presents similarly to discoid lupus, however, other presentations can occur: Lupus erythematosus timidus, lupus profundus, chilblain lupus erythematosus and Lichenoid cutaneous lupus erythematosus-lichen planus overlap syndrome.
Discoid lupus presents as red patches which evolve to form red scaly plaques. The rash progresses, leading to atrophic scarring with hyper or hypopigmentation. It most commonly occurs on the face or the ear lobes.
Investigations
- ANA: positive
- Anti-histone antibody: negative
- ENA: negative
- Anti-dsDNA: negative
- FBC/U&Es/LFTs: normal
Medical management SCE and CCLE
- Discontinue the offending drug
- Sun protection
- Topical corticosteroids/topical calcineurin inhibitors if required
- Hydroxychloroquine/oral corticosteroids if systemic involvement
Contact Dermatitis
Allergic Contact Dermatitis
Background
Contact dermatitis also known as contact eczema, is an exogenous inflammatory skin disorder. The two main subtypes of the condition are Irritant contact dermatitis (ICD) and allergic contact dermatitis (ACD). ACD is a T-cell mediated type 4 hypersensitivity reaction triggered by exposure to an allergen hosts are previously sensitised to. It is a relatively common disease
Epidemiological data on ACD is sparse and thus the incidence and prevalence is not known.
Aetiology
Allergens act as haptens (small hydrophobic chemicals) and bind to form a hapten-protien complex to become antigenic and penetrate the stratum corneum. The complex in engulfed by langarhans cells which migrate to lymph nodes, and present the antigen to naive CD4 T cells that proliferate into memory and effector T cells, causing sensitisation to the allergen. Re-exposure will lead to an inflammatory reaction after approximately 48-72 hours, presenting as a dermatitis.
Risk factors
- Occupation: e.g. hairdressing, construction, chemical industry, healthcare professionals
- Age: sensitisation occurs early in childhood
- History of atopy
Common allergens include: nickel, neomycin, myroxylon pereira, fragrance mx, thimerosal, sodium gold thiosulfate. Poison ivy is also a common cause.
Clinical manifestations
Acute ACD
- Initially confined to site of contact, but diffuse reactions may occur
- Erythematous lesion
- Itch is the predominant symptom
- Burning in some cases
- Oedema
- Blistering
Chronic ACD
- Dry, thick scale
- Hyperkeratosis
- Lichenification
- Fissures (cracking)
Differential diagnosis
- Irritant contact dermatitis
- Atopic dermatitis
- Palmoplantar psoriasis
- Contact urticaria
- Fungal infections e.g. Tinea corporis
Investigations
Patch testing: help differentiate between ACD and ICD
Medical management
- Identification of trigger
- Avoidance of future exposure
- Education
- Minimise contact with allergen
- Use of gloves
- Treatment of existing dermatitis
- Emollients: reduce transepidermal water loss and restore the skin barrier
- Topical corticosteroids
- Topical/oral antibiotics for secondary infection
- Phototherapy/photochemotherapy
- Calcineurin inhibitors
- Systemic immunosuppressants e.g. azathioprine
Complications
- Disseminated secondary eczema
- Lichenification
- Secondary bacterial infection
Irritant Contact Dermatitis
Background
Contact dermatitis also known as contact eczema, is an exogenous inflammatory skin disorder. The two main subtypes of the condition are irritant contact dermatitis (ICD) and allergic contact dermatitis (ACD). Irritant contact dermatitis is a skin reaction that occurs upon exposure to environmental substances or factors which damage the skin barrier. Mainstay treatment involves avoidance of the irritant and emollients to maintain the skin barrier function. Prognosis is good if the irritant is avoided with restoration of healthy skin in 4 weeks.
Epidemiology
ICD accounts for approximately 80% of occupation related contact dermatitis and is the more common subtype. Prevalence of ICD ranges between 0.4 to 4% of the population, however this is likely an underestimate as a large proportion of patients do not seek medical attention. The condition has a female predominance.
Aetiology
The exact pathogenesis of the condition is unknown, however there appears to be disruption of the epidermal layer by the irritant which leads to increased skin permeability and transepidermal water loss allowing the chemical/irritant to penetrate. Keratinocyte injury with cytokine release e.g. interleukin 1-alpha, interleukin-1-beta, IL-6 and TNF-alpha triggers an inflammatory response.
Risk factors
- Young age
- Female
- Atopy
Common irritants
| Physical irritants | Chemical Irritants |
|---|---|
| Wood | Detergents |
| Fiberglass | Acids/alkalis |
| Plants | Wet work |
| Paper | Solvents |
| Dust or soil |
Table 6: Common irritants in ICD
Environmental factors such as temperature and humidity can also have an impact.
Clinical manifestation
Areas commonly affected are the face, dorsum of the hands and finger webs due to relatively thinner stratum corneum.
Acute ICD: singular exposure to the offending agent
- Burning/pain
- Localised erythema (redness)
- Vesicles (blistering)
- Oedema (swelling)
Chronic ICD: multiple exposures to irritant
- Erythema (redness)
- Scale
- Lichenification
- Hyperkeratosis
- Fissures (cracking of the skin)
Diagnosis is largely clinical, based on a history of exposure to the irritant followed by the development of dermatitis.
Investigations
- Patch testing: help differentiate between ICD and ACD
- Histological examination: useful to differentiate from other inflammatory dermatoses
Differential diagnosis
- Allergic contact dermatitis
- Atopic dermatitis
- Psoriasis
- Tinea
- Scabies
Medical/surgical management
- Identification of trigger
- Avoidance of future exposure
- Minimise contact with irritants
- Use of gloves
- Lukewarm water
- Small amounts of soap-free skin cleansers
- Drying hands thoroughly
- Treatment of existing dermatitis
- Emollients: reduce transepidermal water loss and restore the skin barrier
- Topical corticosteroids
- Calcineurin inhibitors
- Phototherapy
Complications
- Disseminated secondary eczema
- Lichenification
- Secondary bacterial infection
Fixed drug eruption
Background
Fixed drug eruptions (FDE) are a type of skin reaction which occurs upon exposure to a drug, with reoccurrence in the same location when re-exposed to the offending agent. Often patients develop a singular lesion, which is self-limiting but leaves an area of post-inflammatory hyperpigmentation. Initial development of the reaction may occur months to years after exposure, with later eruptions occurring more acutely.
Epidemiology
Estimates on incidence vary and range between 2-6% of patients taking medications. No gender or age preference has been found.
Aetiology
FDE is a delayed type IV hypersensitivity reaction with CD8 T cell mediation at the dermo-epidermal layer, causing keratinocyte and melanocyte damage. CD8 T-cells remain quiescent but primed in the resolved lesion until the offending agent is reintroduced.
Drugs most commonly associated with FDE include:
- Antibacterial agents: trimethoprim – sulfamethoxazole, tetracyclines, penicillin, quinolones, dapsone)
- NSAIDS
- Paracetamol
- Barbiturates
- Antimalarials
- Carbamazepine
FDE can uncommonly occur with food and food additives. There are also some reports of patients developing FDE secondary to COVID-19 vaccinations.
Clinical manifestations
- Well-demarcated rash
- Solitary or small number of lesions
- Round or oval
- Colour varies between red to black
- Post-inflammatory hyperpigmentation
- Pruritus or burning is sometimes present
- Common areas affected: lips, anogenital regions, hands and feet. If mucosal surfaces are affected, ulcers may develop.
- Systemic symptoms are rare
A number of clinical variants exist:
- Generalised fixed drug eruption: multiple disseminated lesions affected the trunk and extremities.
- Generalised bullous fixed drug eruption: usually occurs within 24 hours of the drug exposure with blistering rash affecting < 10% of the skin surface. Mucosal surfaces are not affected. Some systemic issues may occur such as fever, malaise and arthralgia but this is rare. Prognosis is good with resolution of symptoms shortly after discontinuation of the offending drug.
- Non-pigmenting fixed drug eruption: symmetrical lessons that improve without post-inflammatory hyperpigmentation.
Investigations
Diagnosis is clinical, based upon the history and examination, but if there is diagnostic uncertainty, the following investigations may be considered:
- Skin biopsy: necrotic keratinocytes in the epidermis, lympho-eisinophilic cells in the dermis with dermal oedema
- Oral provocation test: low dose of the offending agent is administered. It is contraindicated with patients with generalised bullous fixed drug eruption.
- Patch testing: application of the offending agent to area of recurring lesion to elicit a reaction.
Differential diagnosis
- Erythema multiforme
- SJS/TEN
- Bullous pemphigoid
- Aphthous stomatitis
Medical management
The following principles are followed:
- Stop the suspected offending drug
- Avoid drug in future
- Symptom relief e.g. topical or systemic steroids as appropriate
- Generalised bullous fixed drug eruption may need ITU/burns unit referral
Complications
- Blistering
- Post-inflammatory hyperpigmentation
- Cross-reaction with other agents
- Fluid loss and infection in bullous disease
Photosensitivity
Background
Photosensitivity also known as photodermatoses relate to abnormal skin reactions secondary to sun exposure. Photodermatoses can be split into the following major categories: idiopathic, endogenous/exogenous, photoexacerbated dermatoses and photosensitive genodermatoses.
Idiopathic photodermatoses refer to photodermatoses where the underlying pathology is unknown. The most significant endogenous dermatoses is porphyria where there is an abnormality in one of the eight enzymes involved in haem biosynthesis. Exogenous photosensitivity refers to an abnormal sun reaction secondary to exposure to drugs or chemicals. Photoexacerbated dermatoses are skin disorders that are worsened by sun exposure such as dermatomyositis or systemic lupus erythematosus and genodermatoses, are genetic conditions that also trigger a photosensitive reaction.
This chapter will focus on exogenous photosensitivity. They can be split into phototoxic or photoallergic reactions. The majority of drug reactions are phototoxic.
Epidemiology
Exogenous photosensitivity can be relatively common drug reaction, with one study noting it to be responsible for 20% of all adverse drug reactions in adults.
Aetiology
Phototoxic photosensitivity occurs due to ultraviolet irradiation of the agent leading to tissue damage, whereas photo allergy a delayed hypersensitivity reaction to a previously sensitised agent, with a similar pathophysiology to allergic contact dermatitis.
Clinical manifestations
Photoallergic reactions are uncommon and occur >24 hours after exposure to the agent. The reaction is categorised as a dermatitis and in most often affects exposed skin, but does have the potential to spread to unexposed areas also. Pigmentary changes are uncommon.
Common agents responsible for photoallergic reaction:
- Sunscreen
- Non-steroidal anti-inflammatory drugs
- Fragrances
- Phenothiazines
- Quinine
- Sulphonamides
- Quinidine
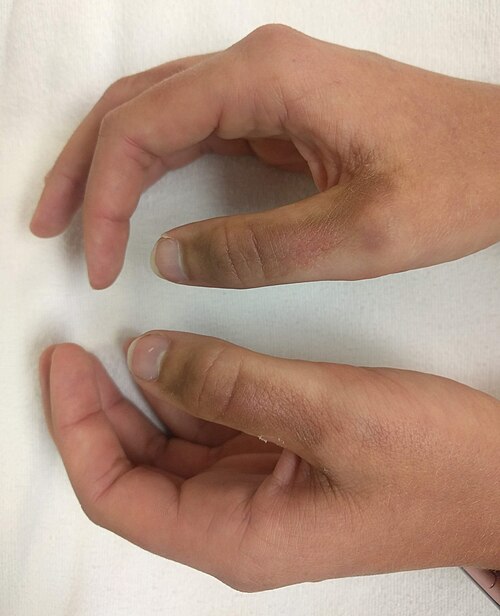
Photodermatitis secondary to lemons on both thumbs. Source: Wikipedia.
Image Source: Wikimedia Commons (2018). Photodermatitis, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Photodermatitis.jpg (Accessed 19 May 2025).
Phototoxic reactions are more common but require a large amount of exposure for the reaction to occur. The onset is shorter, occurring between minutes to hours from exposure. It is characterised by a typical sunburn rash only on exposure areas of the body and can also lead to pigmentary changes. Severe cases may develop bullae.
Common agents responsible for phototoxic reactions:
- Metformin
- Non-steroidal anti-inflammatory drugs (NSAIDs)
- Sulfonamides
- Vemurafenib
- Voriconazole
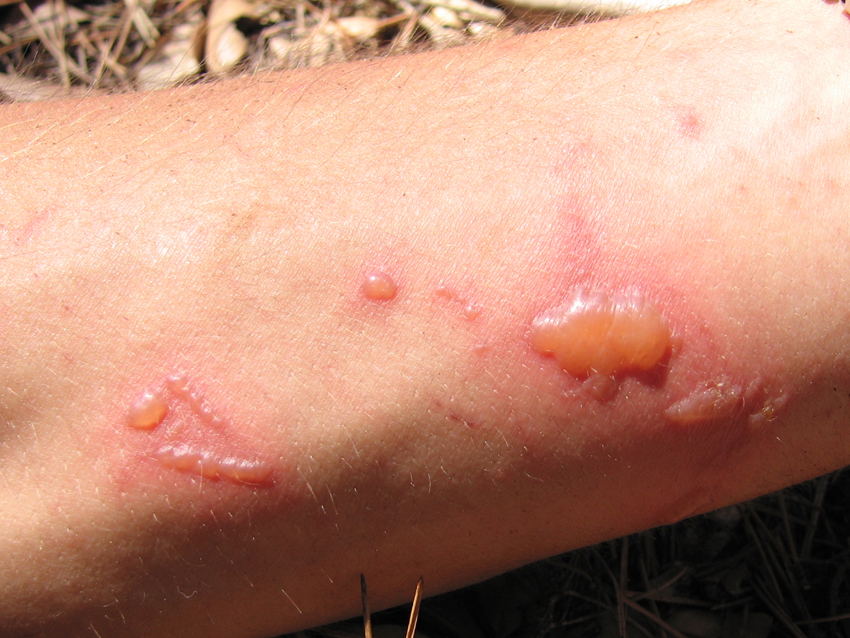
Phototoxic reaction secondary to commons rue on the forearm. Source: Wikipedia
Image Source: Wikimedia Commons (2006). Effet de la rue Officinale, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Effet_de_la_rue_officenale.jpg (Accessed 19 May 2025).
- Amiodarone
- Retinoids
- Psoralens
Investigations
- ANA, anti-dsDNA, anti-Ro, anti-La: if suspecting SLE
- Porphyrin studies: suspecting porphyria
- Skin biopsy
- Phototesting: test the minimal dose of UV radiation which causes as erythematous reaction
- Photopatch testing: suspecting a topical photo allergen
Medical management
- Stop offending agent
- Sun protection:
- Window films for windows
- Sun screen with UVA and UVB protection
- Sun avoidance at midday
- Protective clothing
- Phototoxic reaction: (treat as sunburn)
- Cool compress
- Emollients
- Analgesia
- Photoallergic reaction (treat as contact allergy)
- Topical/oral steroids
- Anti-histamine
References
- https://dermnetnz.org/topics/photosensitivity
- https://www.uptodate.com/contents/photosensitivity-disorders-photodermatoses-clinical-manifestations-diagnosis-and-treatment?search=photosensitivity&source=search_result&selectedTitle=1~150&usage_type=default&display_rank=1#H2
- https://www.uptodate.com/contents/overview-of-cutaneous-photosensitivity-photobiology-patient-evaluation-and-photoprotection
- https://www.uptodate.com/contents/fixed-drug-eruption#H1633148
- https://dermnetnz.org/topics/fixed-drug-eruption
- https://www.sciencedirect.com/topics/medicine-and-dentistry/fixed-drug-eruption
- https://www.bmj.com/content/353/bmj.i3299.fullackground
- https://dermnetnz.org/topics/contact-dermatitis
- https://bestpractice.bmj.com/topics/en-gb/90
- https://www.uptodate.com/contents/irritant-contact-dermatitis-in-adults
- https://dermnetnz.org/topics/contact-dermatitis
- https://bestpractice.bmj.com/topics/en-gb/90
- https://dermnetnz.org/topics/allergic-contact-dermatitis
- https://www.uptodate.com/contents/management-of-allergic-contact-dermatitis#H320159
- https://www.uptodate.com/contents/clinical-features-and-diagnosis-of-allergic-contact-dermatitis#H48321072
- https://dermnetnz.org/topics/drug-induced-lupus-erythematosus
- https://www.uptodate.com/contents/drug-induced-lupus
- https://www.uptodate.com/contents/overview-of-cutaneous-lupus-erythematosus
- https://cdn.bad.org.uk/uploads/2021/12/29200149/SJS-TEN-summary-of-treatment-2-pages.pdf
- https://www.ncbi.nlm.nih.gov/books/NBK459323/
- https://bestpractice.bmj.com/topics/en-gb/237
- https://dermnetnz.org/topics/stevens-johnson-syndrome-toxic-epidermal-necrolysis
- https://pubmed.ncbi.nlm.nih.gov/30840032/
- https://pubmed.ncbi.nlm.nih.gov/10951229/
- https://dermnetnz.org/topics/erythema-multiforme
- https://www.uptodate.com/contents/erythema-multiforme-pathogenesis-clinical-features-and-diagnosis
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

