


 Close
 26th January 2024
Management
The main aim of management of osteoporosis is prevention of fragility fractures, particularly hip, vertebral and radial.
General measures
All patients at risk of osteoporosis or with established disease should receive adequate supplementation with calcium and vitamin D. Vitamin D replacement should be prescribed to all patients; calcium should be prescribed in addition to this if oral intake of calcium is deemed inadequate. Eating a balanced diet and engaging in regular exercise is recommended to maintain bone strength. Smoking cessation and alcohol reduction advice should be given.
Pharmacological management
Post-menopausal women
Bisphosphonates
Bisphosphonates, e.g. alendronic acid, ibandronic acid, risedronate, and zoledronic acid, are used as first-line therapy for the prevention and treatment of osteoporosis in women. They are indicated for postmenopausal women with a history of an osteoporotic fracture and/or a T score of less than -2.5. Patients who have had a fragility fracture and are aged 75 years or over are presumed to have underlying osteoporosis and should be commenced on first-line therapy with an oral bisphosphonate, without the need for DEXA. Bisphosphonate acts by inhibiting osteoclast activity and, therefore, reducing the rate of bone resorption. They have been shown to reduce the risk of both vertebral and non-vertebral fractures, aside from ibandronic acid, which only reduces the risk of femoral fractures. Alendronate and risedronate can be given as once daily or once weekly oral preparations, whereas ibandronic acid is given orally once a month. Zoledronic acid is given by a single intravenous infusion once a year. The main adverse effects of oral bisphosphonates are related to gastrointestinal disturbance, including dysphagia, oesophagitis and gastric ulcers. Rare cases of atypical femoral fractures and osteonecrosis of the jaw have also been reported.
Patients in whom treatment with oral bisphosphonates is not tolerated or contraindicated, an intravenous preparation such as ibandronic acid or zoledronic acid can be tried. If this is not tolerated, NICE recommends referral to a specialist. Further treatment options include strontium ranelate, raloxifene, denosumab, and teriparatide. The exact choice of drug depends on numerous factors, including cost, patient choice, T score and presence of certain risk factors. Hormonal replacement therapy (HRT) can be considered for younger postmenopausal women to reduce the risk of osteoporotic fractures and alleviation of menopausal symptoms.
Denosumab
Denosumab should be considered as second-line therapy for postmenopausal women with osteoporosis. It is a human monoclonal antibody which works by inhibiting the receptor activator of nuclear factor-kappa B ligand (RANKL), to inhibit the formation and maturation of osteoclasts. It is delivered as a single subcutaneous injection every 6 months and is given in large doses to adults with bone metastases from solid tumours. Caution should be taken in prescribing denosumab to patients with pre-existing hypocalcaemia or those with severe renal disease. Potential adverse effects include increased risk of serious infection, osteonecrosis of the jaw, atypical femoral fractures and impaired fracture healing.
Raloxifene
Raloxifene is a selective oestrogen receptor modulator (SERM) which reduces the risk of vertebral fractures. It may increase the risk of thromboembolic events and exacerbate menopausal symptoms; however, unlike HRT, it decreases the risk of breast cancer.
Teriparatide
Teriparatide is a recombinant form of parathyroid hormone, given by subcutaneous injections daily for a maximum of two years. It is very effective at increasing BMD and has been shown to reduce the risk of vertebral fractures; however, its use is restricted due to cost. Possible adverse effects include nausea, dizziness and leg cramps.
Strontium ranelate
Strontium ranelate acts by promoting the production of osteoblasts and inhibiting osteoclasts. However, this was withdrawn by the manufacturer worldwide due to a number of adverse effects, including risk of cardiovascular and thromboembolic events and Steven Johnson syndrome.
Men
First-line treatment for men with osteoporosis is with oral bisphosphonates Alendronic acid or Risedronate. Second-line treatment includes teriparatide or denosumab, although specific guidelines are lacking.
Glucocorticoid-induced osteoporosis
Patients on long-term steroids, in particular a dose of 7.5mg daily for 3 or more months, are at a significant risk of osteoporosis. These patients should all be offered calcium and vitamin D supplementation, together with lifestyle advice. In addition, the Royal College of Physicians recommends that patients on steroids over the age of 65 or those who have a history of previous fragility fracture should be offered bone protection with alendronate. Those who are under the age of 65 years should be offered a DEXA scan with further management dependant on the result:
- T score greater than 0 = reassure
- T score between 0 and -1.5 = repeat bone density scan in 1-3 years
- T score less than -1.5 = offer bone protection.
Follow up
Patients at risk of fragility fracture should be followed up regularly to check adherence to medication or development of any adverse effects. For patients taking oral glucocorticoids, pharmacological treatment with bisphosphonates and/or calcium and vitamin D should continue until the course of treatment is complete and then reassessed to determine whether this needs to be continued in high-risk patients. For all other patients, the need for treatment with bisphosphonates should be reviewed after 3-5 years. Patients who remain at high risk should be offered Alendronic acid for up to 10 years and risedronate for up to 7 years. For other patients, a repeat DEXA scan should be performed – if the T score is less than -2.5, treatment should be continued, and BMD should be rechecked every 3-5 years. If T score is greater than -2.5, treatment should be stopped and BMD re-measured after 2 years.
Summary of management of osteoporosis
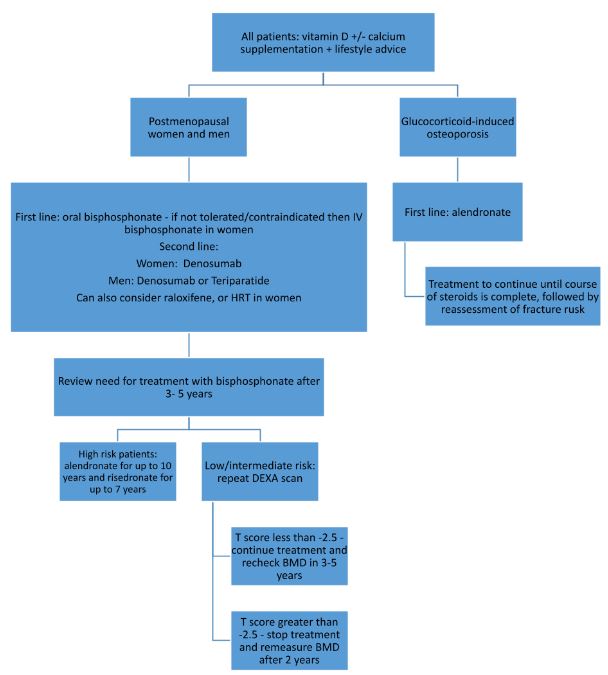
Adapted from NICE guidelines, Osteoporosis: assessing the risk of fragility fracture. National Institute for Health and Care Excellence (NICE); 2017.
References
- Mauck KF, Clarke BL. Diagnosis, screening, prevention, and treatment of osteoporosis. InMayo Clinic Proceedings 2006 May 1 (Vol. 81, No. 5, pp. 662-672). Elsevier.
- Chesnut III CH, Skag A, Christiansen C, Recker R, Stakkestad JA, Hoiseth A, Felsenberg D, Huss H, Gilbride J, Schimmer RC, Delmas PD. Effects of oral ibandronate administered daily or intermittently on fracture risk in postmenopausal osteoporosis. Journal of bone and mineral research. 2004 Aug;19(8):1241-9.
- National Institute for Health and Care Excellence (Great Britain). Osteoporosis: assessing the risk of fragility fracture. National Institute for Health and Care Excellence (NICE); 2017.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

