


 Close
 20th February 2024
Alcohol
Alcohol use and its impact
Epidemiology, aetiology, and pathophysiology
Alcohol use is common in the Western world, with approximately 80% of the UK population drinking alcohol during their lifetime. 20-25% of adults in the UK have also been known to drink over the recommended alcohol limits, with approximately 4% of the population reporting symptoms of alcohol dependence.
The UK Department of Health has stated that both males and females should not drink more than 14 units of alcohol per week. The 14 units of alcohol should also be spread across three days. Binge drinking can be defined as drinking over eight units of alcohol in a single session for males and six units of alcohol for females. One unit of alcohol is defined as 10ml/8g of ethanol. This can be calculated by the formula: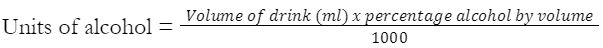 This is equivalent towards one standard measure of spirits or half a pint of average-strength beer.
Alcohol use has a multifactorial aetiology that combines social, psychological, and environmental factors. Research into the neurobehavioral effects of alcohol has shown the downregulation of GABA receptors and upregulation of glutamate and noradrenaline receptors. Dopaminergic pathways along the tegmental area and nucleus accumbens mediate the pleasure sensation from taking alcohol.
Diagnosis of alcohol dependence
Recognition of alcohol dependence is crucial as it is associated with increased morbidities and mortality from direct alcohol use and the co-morbidities it causes.
NICE recommends using the AUDIT score to screen and identify patients with alcohol issues. Screening should be performed routinely at any opportunity, including patients with physical or mental co-morbidities and those who display stigmata of alcohol misuse (abnormal GGT/MCV; signs of frequent alcohol use including dilated facial capillaries, tremors; high-risk associations including substance misuse). The AUDIT score can help identify hazardous drinking, harmful drinking, and alcohol dependence.
When alcohol dependence is picked up on the screening tool, clinicians can use the Severity of Alcohol Dependence Questionnaire (SADQ) score to quantify this. Patients should also be assessed for signs and symptoms of alcohol withdrawal with prompt treatment if identified.
Short and long-term impact of alcohol dependence
Alcohol dependence can be associated with many co-morbidities. Alcohol use is associated with co-morbidities, including accidents and injuries related to alcohol use, self-harm, and accidents. Alcohol withdrawal and Wernicke’s encephalopathy are also acute complications that carry high morbidity and mortality rates.
There are multiple long-term complications associated with alcohol use, and it affects many organ systems, including:
- Malignancy – There are associations with oral, oesophageal, bowel, stomach, liver and breast cancer.
- Cardiac – Associated with cardiomyopathy, hypertension, and cardiac arrhythmias.
- Liver and pancreas – Pancreatitis (acute and chronic) are both associated with alcohol use. Alcoholic liver disease (steatosis, hepatitis, and fibrosis/cirrhosis) and its associated complications (ascites, varices, infection, malignancy) are associated with significant morbidity and mortality.
- Psychiatric – Korsakoff’s syndrome is associated with memory loss, disorientation and confabulation.
- Pregnancy – Foetal alcohol syndrome is associated with alcohol use of over five units per day during pregnancy. This can result in dysmorphic facial features, microcephaly, fetal growth restriction, and the heart, skull, kidneys, brain, and bone malformation.
- Social – Domestic violence and child abuse can be attributed towards the use of alcohol.
References
- Bourke, J., & White, P. (2012). Psychological Medicine. In P. Kumar & M. Clark (Eds.), Kumar & Clark’s Clinical Medicine (12 ed.). Spain: Elsevier.
- Tetrault, J., & O’Connor, P. G. (2021 Jan 20). Risky drinking and alcohol use disorder: Epidemiology, pathogenesis, clinical manifestations, course, assessment, and diagnosis. Accessed on 2022 Mar 22. Available from: https://www.uptodate.com/contents/risky-drinking-and-alcohol-use-disorder-epidemiology-pathogenesis-clinical-manifestations-course-assessment-and-diagnosis?topicRef=108891&source=see_link.
- National Institute for Health and Care Excellence. (2011 Feb 23). Alcohol-use disorders: diagnosis, assessment and management of harmful drinking (high-risk drinking) and alcohol dependence. Accessed on 2022 Mar 23. Available from: https://www.nice.org.uk/guidance/cg115/resources/alcoholuse-disorders-diagnosis-assessment-and-management-of-harmful-drinking-highrisk-drinking-and-alcohol-dependence-pdf-35109391116229.
- Drummond, C. (2018). Alcohol-use disorder. Accessed on 2022 Mar 23. Available from: https://bestpractice.bmj.com/topics/en-gb/198.
Alcohol withdrawal and delirium tremens
Epidemiology, aetiology and pathophysiology
Up to 2-8% of patients who have alcohol-use disorders have symptoms suggestive of alcohol withdrawal, and this increases to 40-50% when looking at patients admitted to the Emergency department with trauma. Up to 25% of these patients have delirium tremens.
Abrupt cessation of alcohol use is often implicated as the cause of alcohol withdrawal cessation. Alcohol acts as a CNS depressant by inhibiting excitatory (glutamate) receptors while enhancing inhibitory (GABA) receptors. Removal of alcohol results in overexcitation of the CNS system, leading to withdrawal symptoms and delirium tremens.
Clinical presentation
Alcohol withdrawal symptoms exist within on a spectrum from mild symptoms up to delirium tremens. The patient usually presents with autonomic dysfunction, and symptom onset begins 6 hours after alcohol cessation. The condition’s progression depends on the overall amount of alcohol intake and period of alcohol dependence.
Mild symptoms typically present with anxiety, headaches, palpitations and GI symptoms (nausea, vomiting). Patients can be seen pacing around due to anxiety and heightened awareness. Patients may also experience diaphoresis and tremors.
Moderate symptoms typically include hallucinations and withdrawal seizures. Patients may experience auditory, tactile or visual hallucinations, which typically present 24-48 hours following cessation of alcohol. Seizures that occur in this context typically present as a generalised tonic-clonic seizure. The most severe presentation of alcohol withdrawal is delirium tremens. Delirium tremens is characterised by significant autonomic dysfunction with changes in vital observations. Patients typically experience tachycardia, hypertension, hyperthermia, agitation, diaphoresis, seizures and profound confusion.
Investigation and treatment
The diagnosis of alcohol withdrawal depends on taking a good history from the patient and identifying the physical signs of alcohol withdrawal and co-morbidities secondary to alcohol use. The Clinical Institute for Withdrawal Assessment for alcohol revised scale (CIWA-Ar) is the tool used to help clinicians identify and stratify the severity of a patient’s alcohol withdrawal syndrome. The scoring system utilises the following symptoms as part of their scoring system:
- Nausea and vomiting
- Tremor
- Sweats
- Anxiety
- Agitation
- Tactile disturbance
- Auditory disturbance
- Visual disturbance
- Headache/Fullness in the head
- Orientation
Points are given depending on the severity of each symptom, and a score is provided to indicate the severity of the withdrawal syndrome. Each hospital will have its cut-off for beginning treatment for alcohol withdrawal, and each clinician will refer to their local hospital guidance for the treatment threshold. A CIWA score of <8 typically represents mild symptoms, 9-15 for moderate symptoms and >15 for severe symptoms.
The main goal of treatment is to control the patient’s autonomic dysfunction and reduce the risk of seizures. The mainstay of treatment for alcohol withdrawal is benzodiazepines. The choice of benzodiazepine is dependent on local guidance, but typically, diazepam and chlordiazepoxide are commonly used. This can be administered on a fixed schedule, or the patient’s symptom burden can guide this. Refractory alcohol withdrawal and seizures can be managed with phenobarbital and propofol, but this requires support in an intensive care setting.
Basic supportive care for nutrition and hydration should also be provided. It is essential to watch for refeeding syndrome if there are suspicions that the patient may have had an inadequate diet for the days/weeks leading to readmission. Intravenous vitamin B complex is also given as a prophylaxis against Wernicke’s encephalopathy and patients are usually commenced on oral thiamine after completing their IV treatment. Follow-up with the substance misuse team, along with advice for abstinence from alcohol, should always be provided, and patients should be advised to reduce or stop their alcohol intake where possible.
References
- Drummond, C. (2018). Alcohol-use disorder. Accessed on 2022 Mar 23. Available from: https://bestpractice.bmj.com/topics/en-gb/198.
- Rahman A, Paul M. Delirium Tremens. [Updated 2021 Aug 27]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2022 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK482134/
- Newman RK, Stobart Gallagher MA, Gomez AE. Alcohol Withdrawal. [Updated 2021 Nov 13]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2022 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK441882/
- Hoffman, R., & Weinhouse, G. (2021 Nov 4). Management of moderate and severe alcohol withdrawal syndromes. Accessed on 2022 Mar 24. Available from: https://www.uptodate.com/contents/management-of-moderate-and-severe-alcohol-withdrawal-syndromes?topicRef=7809&source=see_link.
- Holt, S., & Tetrault, J. (2020 Jan 10). Ambulatory management of alcohol withdrawal. Accessed on 2022 Mar 23. Available from: https://www.uptodate.com/contents/ambulatory-management-of-alcohol-withdrawal?topicRef=7809&source=related_link.
Treatment of alcohol dependence
The goal for the treatment of alcohol dependence is to reduce the amount of alcohol intake or abstinence, and the patient guides this.
Psychological treatment
Psychosocial interventions are the 1st line intervention recommended by NICE, and this is often in the form of brief intervention. A brief intervention aims to guide patients through the impact of alcohol use and setting goals to reduce their alcohol intake. This is usually undertaken at a primary care level but can be done while a patient is an inpatient. The critical part of this intervention is allowing the patient to acknowledge the harm of drinking, identifying their barriers to change and setting realistic goals for change.
Patients should also be directed towards community networks or self-help groups, including Alcoholics Anonymous and SMART Recovery, which can help with the process. Other psychological therapies, including cognitive behavioural therapy, environmental-based therapy and motivational interviewing, have been shown to impact reducing alcohol use positively.
Pharmacological treatment
Pharmacological therapies are often used in the management of moderate-severe alcohol dependence along with patients with harmful drinking or mild alcohol dependence who have had limited benefit from psychosocial interventions.
The mainstay of treatment is with acamprosate, naltrexone and disulfiram. Prior to commencing treatment, it is essential to determine any co-existing substance misuse, medication history, including opioid use and baseline blood tests to assess for liver and renal impairment. Patients should also be under regular review while on treatment.
Naltrexone is a μ-opioid receptor antagonist and appears to affect the hypothalamus-pituitary-adrenal axis to suppress alcohol consumption. It is used as a first-line treatment alongside acamprosate, as it can be used while patients remain on alcohol. It appears to be helpful against craving symptoms. It is contraindicated in patients with hepatic failure or those on opioids. Common side effects include nausea, headaches, and dizziness. Liver function test monitoring is needed for the initial several weeks.
Acamprosate is an alternative 1st line treatment for alcohol dependence and is typically used on patients who have a contraindication towards naltrexone. Acamprosate works by modulating the glutamate receptors within the CNS. It effectively maintains abstinence and has increased efficacy in those who have stopped alcohol consumption. It is contraindicated in patients with impaired renal function (eGFR<30). Common side effects include diarrhoea, fatigue and nervousness.
Disulfiram is the last recommended medication and is usually used as an adjunct medication due to poor compliance. Disulfiram’s mode of action is blocking the metabolism of alcohol, resulting in the build-up of acetaldehyde in the body. This results in systemic symptoms, including flushing, nausea, diarrhoea, tachycardia and hypotension when alcohol is taken in conjunction with disulfiram. Patients should abstain from alcohol for at least 24 hours prior to commencing disulfiram, and this should usually be done under supervision. Patients should be warned of the reaction when taken with alcohol and the small risk of hepatotoxicity.
References
- National Institute for Health and Care Excellence. (2011 Feb 23). Alcohol-use disorders: diagnosis, assessment and management of harmful drinking (high-risk drinking) and alcohol dependence. Accessed on 2022 Mar 23. Available from: https://www.nice.org.uk/guidance/cg115/resources/alcoholuse-disorders-diagnosis-assessment-and-management-of-harmful-drinking-highrisk-drinking-and-alcohol-dependence-pdf-35109391116229.
- Drummond, C. (2018). Alcohol-use disorder. Accessed on 2022 Mar 23. Available from: https://bestpractice.bmj.com/topics/en-gb/198.
- Holt, S. (2022 Mar 14). Alcohol use disorder: Pharmacologic management. Accessed on 2022 Mar 25. Available from: https://www.uptodate.com/contents/alcohol-use-disorder-pharmacologic-management?topicRef=7810&source=see_link#H3866314010.
- Saxon, A. (2021 Oct 21). Alcohol use disorder: Psychosocial treatment. Accessed on 2022 Mar 25. Available from: https://www.uptodate.com/contents/alcohol-use-disorder-psychosocial-treatment?topicRef=14832&source=see_link.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

