


 Close
 26th June 2023
Brain Tumours
Classification of brain tumours
There are 3 common different ways to subdivide brain tumours:
- Intrinsic vs Extrinsic
- ‘Intrinsic’ tumours are classified as tumours arising from within the brain. Those that grow from structures around the brain, such as cranial nerves, spinal nerves and dura, are classified as ‘extrinsic’ tumours.
- Benign vs Malignant
- Slow-growing tumours such as schwannomas and meningiomas tend to be benign, however, tumours such as gliomas are usually malignant.
- Primary vs Secondary: Primary tumours are those that originate from the cranial tissues, whilst secondary tumours are metastatic and have spread from elsewhere in the body. A full body CT can help to establish whether there are any other tumours within the body. Metastatic (secondary) brain tumours are three times more common than primary brain tumours. A biopsy can determine the tissue of the tumour. Lung, breast, bowel, skin, and kidney tumours are the most common sites that metastasise to the brain.
Types of brain tumours
Glioma
Gliomas originate from glial cells. Glial cells are non-neuronal cells that have many functions involving neuronal pruning, producing myelin and modulating neuronal growth. Glial cells include astrocytes, oligodendrocytes, and ependymal cells. Tumours of these cells can give rise to astrocytomas or glioblastomas, oligodendrogliomas, or ependymomas, respectively. Astrocytomas are by far the most common type of glioma in both adults and children; they can be low grade (Grade 1 and 2 – slow-growing) or high grade (Grade 3 and 4 – fast-growing). Grade 4 astrocytomas are more commonly called glioblastoma multiforme (GBM). The imaging shows a ring enhancing lesion with central necrosis, typical of GBM. Prognosis for GBM is poor; the average survival time is just 12-18 months.

Glioma on MRI brain.
Image Source: Wikimedia Commons (2009). Glioma, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Glioma.gif (Accessed on: 30 January 2023).

Meningioma
Meningiomas are slow-growing tumours arising from the lining (meninges) that encapsulates the brain and spinal cord. This is a benign tumour that rarely metastasises and is usually monitored with surgical resection if impeding on neurological structures. Meningiomas account for 25% of all brain tumours.

Meningioma on CT.
Image Source: Wikimedia Commons (2007). Contrast enhanced meningioma, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Contrast_enhanced_meningioma.jpg (Accessed on: 11 January 2023).

Vestibular Schwannoma
These are slow-growing tumours that form along the vestibulocochlear nerve (CNVIII). These are benign tumours of vestibulocochlear Schwann cells. Patients may present with tinnitus, unilateral sensorineural hearing loss, vestibular dysfunction causing dizziness and rarely ipsilateral disturbances of facial pain (CNV) and facial weakness (CNVII). These tumours can be managed conservatively by MRI monitoring; however, if compressing adjacent structures, surgical resection and stereotactic radiosurgery are the main management options.

Vestibular Schwannoma on MRI brain
Image Source: Wikimedia Commons (2008). Vestibular-schwannoma-003, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Vestibular-schwannoma-003.jpg (Accessed on: 30 January 2023).

Medulloblastoma
Medulloblastomas are high-grade solid tumours located in the cerebellum, usually in children. Metastases can occur within the CSF to other parts of the brain and spinal cord; therefore, a full spine MRI is important as metastases are present in 1/3rd of children at presentation. Treatment is tumour-specific, often involving radiation, chemotherapy, and surgery.

Medulloblastoma on MRI brain
Image Source: Wikimedia Commons (2005). CT brain scan of child with medulloblastoma and resulting hydrocephalus, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:CT_brain_scan_of_child_with_medulloblastoma_and_resulting_hydrocephalus.jpg (Accessed on: 30 January 2023).

Craniopharyngioma
Arising from the pituitary stalk, these benign tumours can affect the production of hormones from the hypothalamus or pituitary glands and may even present as pituitary insufficiency. As the tumour site is situated above the optic chiasm, patients may develop a bitemporal inferior quadrantinopia, which may progress to a bitemporal hemianopia as the tumour grows. Clinical features may include headache, visual changes, excessive urination and dehydration (due to diabetes insipidus), delayed puberty in children or sexual dysfunction in adults, symptoms of hypothyroidism such as weight gain, or symptoms of adrenal insufficiency.

Craniopharyngioma on MRI brain.
Image Source: Wikimedia Commons (2011). Craniopharyngioma-t1sagkm-006, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Craniopharyngioma-t1sagkm-006.jpg (Accessed on: 11 January 2023).

Pituitary Adenoma
Pituitary adenomas are benign tumours arising from the pituitary gland (not to be confused with craniopharyngiomas which arise from the pituitary stalk, above the pituitary gland). They mostly affect the anterior lobe of the pituitary and are the most common cause of hypopituitarism. About half of pituitary adenomas do not secrete hormones and are called ‘non-functioning’ adenomas; however, they can still produce symptoms resulting from compression of surrounding structures, e.g. bitemporal hemianopia due to compression of the optic chiasm. Functioning adenomas secrete hormones and can result in symptoms of the following depending on the hormone secreted:
- Cushingoid symptoms
- Acromegaly
- Diabetes insipidus
- Hyperpituitarism
- Amenorrhoea/galactorrhoea/impotence
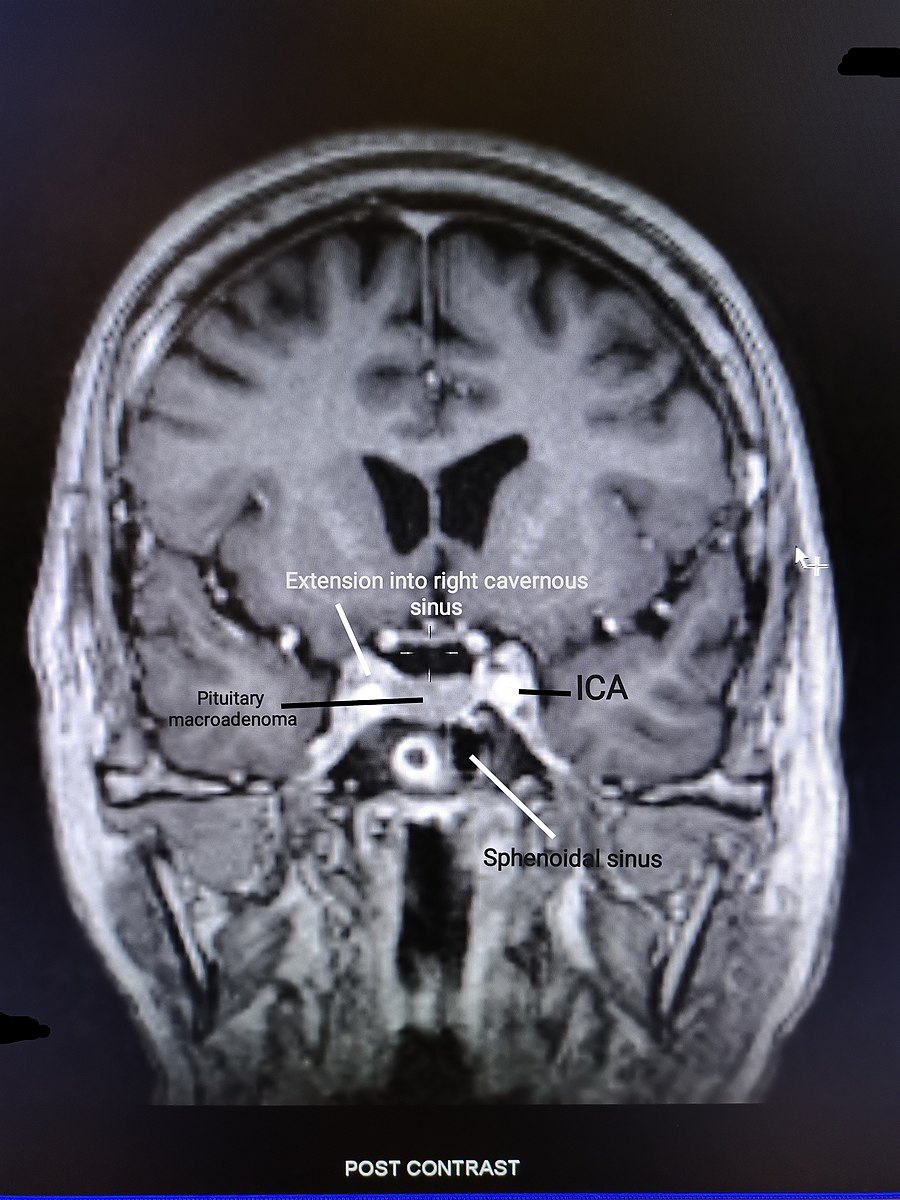
Pituitary adenoma on MRI brain
Image Source: Wikimedia Commons (2022). Coronal section of non-functioning pituitary adenoma, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Coronal_section_of_non-functioning_pituitary_adenoma.jpg (Accessed on: 30 January 2023).

Haemangioblastoma
Haemangioblastomas are slow-growing benign tumours of the vascular system; they predominantly affect the cerebellum but can occasionally affect other sites, including the spinal cord and cerebrum. Von Hippel-Lindau syndrome is a rare inherited condition which is characterised by the formation of tumours and visceral cysts; haemangioblastomas are characteristic of Von Hippel-Lindau syndrome.
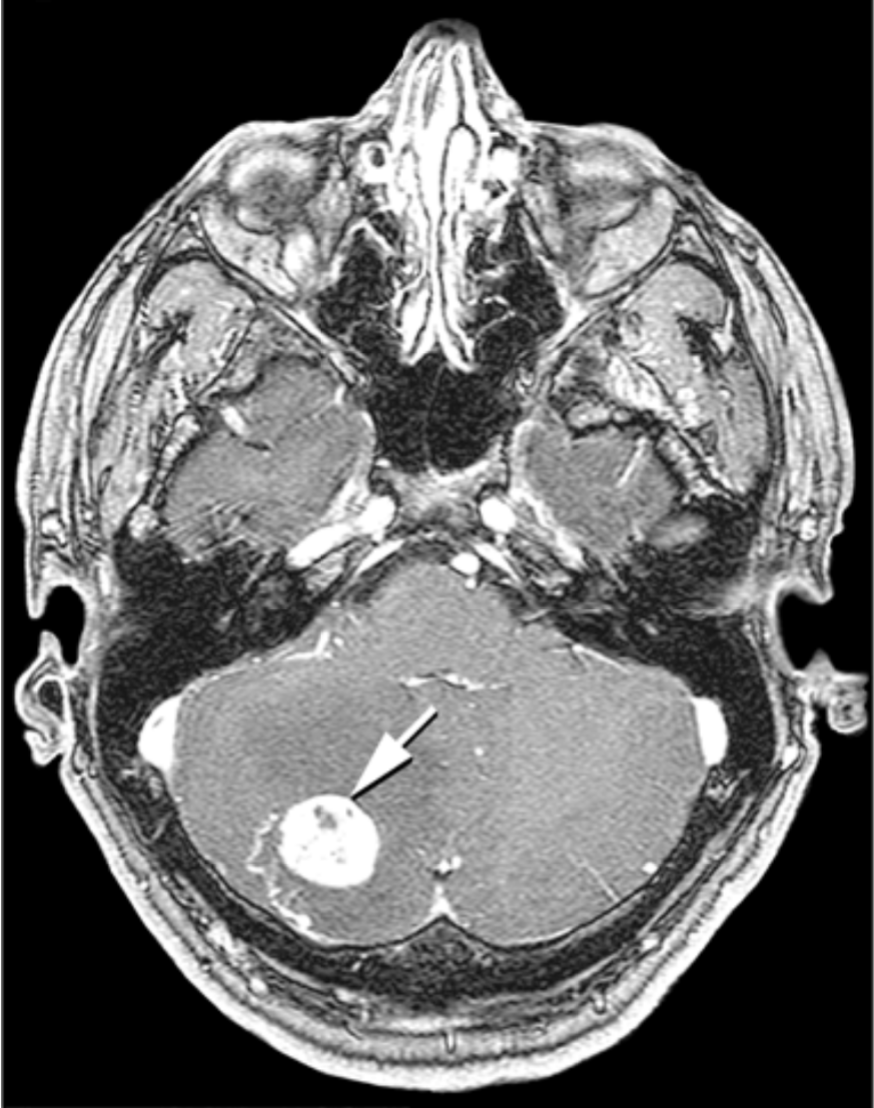
Cerebellar haemangioma on MRI.
Image Source: Wikimedia Commons (2007). Hippel Lindau, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Hippel_Lindau.gif (Accessed on: 30 January 2023).

Immunosuppressed Patients
Immunosuppressed states can significantly increase the risk of several brain lesions, outlined in this section. A brief understanding of these is important to be able to consider these diagnoses in clinical practice so that potential brain-sparing and life-saving treatments can be initiated early; they are also a common topic in MRCP questions.
Toxoplasmosis
Toxoplasmosis is caused by infection with the parasite Toxoplasma gondii, which is classically spread through infected meat that is inadequately cooked or through contact with oocysts from cat faeces.
Infection may cause symptoms such as headache, confusion, unsteady gait, seizures, and fevers in the immunosuppressed. Contrast CT features of cerebral toxoplasmosis include multiple ring-enhancing hypodense lesions in the basal ganglia and corticomedullary junction. Occasional mass effect and midline shift may be present due to the increasing size of the lesions. The treatment of acute toxoplasmosis in immunocompromised patients is with sulfadiazine and pyrimethamine. Prophylaxis with co-trimoxazole may be given to HIV-positive patients with low CD4+ counts.

Toxoplasmosis on MRI.
Image Source: Wikimedia Commons (2019). BrainToxoplasmosis MRI 4 11, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:BrainToxoplasmosis_MRI_4_11.png (Accessed on: 30 January 2023).

Primary CNS lymphoma
Primary CNS lymphoma (PCNSL) is a rare tumour confined to the central nervous system with no evidence of systemic spread. The risk of PCNSL is much higher in immunocompromised patients, particularly those with HIV/AIDS. PCNSL usually develops from B-cell lymphocytes; the most common subtype is diffuse large B-cell lymphoma and is associated with prior Epstein-Barr virus infection. The symptoms can include those of increased intracranial pressure (e.g. headache, vomiting), diplopia, behavioural changes, seizures, and focal neurological signs.
Radiological findings vary from well-circumscribed, solid, homogenous lesions in immunocompetent individuals, to peripheral enhancement with central necrosis of the lesion and vasogenic oedema in immunodeficiency-related CNS lymphomas. The majority of PCNSLs are solitary lesions, however, it can also present with multiple lesions.
Treatment options include steroids (to reduce the oedema surrounding the tumour), chemotherapy and radiotherapy. Neurosurgical resection may be considered for low grade tumours.

Primary CNS lymphoma on MRI brain
Image Source: Wikimedia Commons (2007). Tumor PrimaryCNSLymphoma T1Axial, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Tumor_PrimaryCNSLymphoma_T1Axial.JPG (Accessed on: 30 January 2023).

Progressive multifocal leukoencephalopathy
Progressive multifocal leukoencephalopathy (PML) is a manifestation of infection with the JC virus in immunocompromised individuals. It causes progressive, widespread demyelination due to JC virus infection of oligodendrocytes within the brain. The symptoms are slow and insidious, including behavioural changes, speech, motor, and visual impairment. It almost exclusively affects those who are severely immunosuppressed, however, increased incidence has been associated with the introduction of immunosuppressant monoclonal antibody therapies such as natalizumab, efalizumab, and rituximab for the treatment of various autoimmune disorders.
CT head can show single or multiple multifocal lesions which usually do not enhance. An MRI is the gold-standard imaging choice, revealing high-signal demyelinating white matter lesions.
Prognosis is very poor, associated with neurological disability and if left untreated, is usually fatal within one year. Treatment focuses on reversing the immune deficiency of the patient to slow or stop the progression of PML. In patients with HIV, treatment involves starting antiretroviral therapies (ART) to increase the patient’s CD4+ count to assist in halting the progression of the infection.

Progressive Multifocal Leukoencephalopathy on MRI brain.
Image Source: Wikimedia Commons (2008). Progressive multifocal leukoencephalopathy 002, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Progressive_multifocal_leukoencephalopathy_002.jpg (Accessed on: 30 January 2023).

Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

