


 Close
 24th June 2023
Haemodialysis
Mechanism
- During haemodialysis, blood is removed from the body via a form of vascular access and is exposed to dialysate fluid across a semipermeable membrane.
- Small molecules that are at a high concentration in blood will diffuse down their concentration gradient and into the dialysate fluid via the membrane pores. Blood and dialysate fluid flow in opposite directions to maintain these concentration gradients.
- Fluid removal is primarily via ultrafiltration, i.e. moves out of the blood due to a generated pressure gradient or the ‘transmembrane pressure (TMP)’. Some solutes are removed in addition to the fluid via convection, this process is known as ‘solute drag’.
- Haemodialysis clears small molecules well, however, is less effective for larger ‘middle’ molecules such as beta-2 microglobulin.
- Different related processes can be used in different clinical contexts:
- Haemofiltration – more frequently seen in critical care. Process relies on clearance via convection due to a generated TMP and movement down a pressure gradient. Favoured in haemodynamically unstable patients as it can be performed with slow pump speeds continuously over 24 hours. Fluid replacement is required to achieve solute clearance; a large amount of fluid must be filtered from the blood. Good at clearing larger molecules.
- Haemodiafiltration – this process combines clearance via diffusion and convection, therefore, requires both dialysate and replacement fluid. Benefits over haemodialysis alone include improved haemodynamic stability and better clearance of middle molecules.
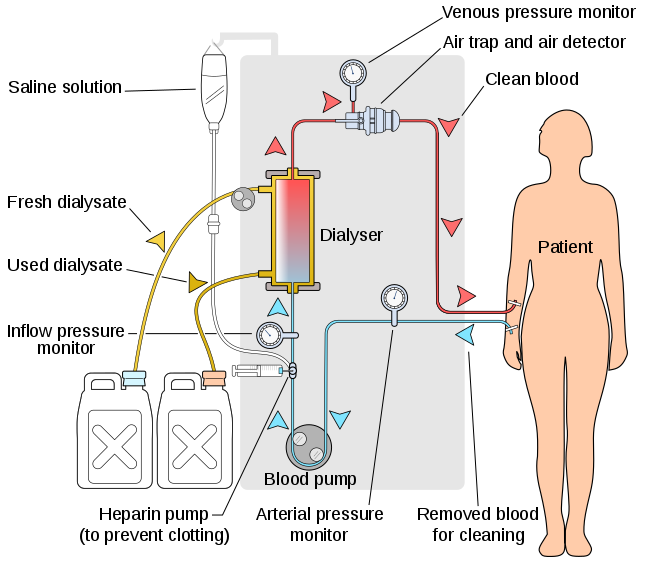
The process of haemodialysis.
Image Source: Wikimedia Commons (2008). Hemodialysis-en, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Hemodialysis-en.svg (Accessed on: 13 February 2023).
Requirements and process
- Vascular access – dialysis requires the fast removal and return of large volumes of blood.
- Arteriovenous fistula (AVF) – this is the preferred mode of vascular access, generally formed by the connection of the brachial or radial artery with the cephalic or basilic vein. Requires suitable anatomy and advance planning (an AVF will take at least 6-8 weeks to ‘mature’ and become usable).
- Polytetrafluoroethylene (PTFE) graft – used to create an anastomosis between an artery and vein if native anatomy is unfavourable.
- Tunnelled cuffed dialysis catheter – similar to temporary dialysis catheters but are tunnelled through subcutaneous tissue to a separate exit site and have a cuff that is located in the tunnel to reduce ascending infection.
- Temporary dialysis catheter – these are used for emergency renal replacement therapy and are for short-term use only. Commonly inserted into the internal jugular or femoral veins.
- Dialysis prescription – a minimum of twelve hours per week is recommended for most patients, this is generally split into three sessions. Patients will have a set ‘dry weight’ that acts as a target for fluid removal each session.
- Anticoagulation – required to prevent clotting in the dialysis circuit external to the body, usually heparin or citrate.
Complications
- Related to dialysis access:
- Bacteraemia – tunnelled and temporary dialysis lines are indwelling devices that carry a high risk of infection.
- Central venous stenosis or occlusion
- Fistula – thrombosis (risk if volume deplete, requires urgent declotting), infection (unusual), aneurysm, ‘steal’ (blood flow redirected through the fistula may reduce distant arterial supply and compromise fingers etc.).
- Related to the process:
- Intradialytic hypotension – can occur when fluid from the extracellular space does not replace that taken from the intravascular space during dialysis at a fast enough rate.
- Dialysis disequilibrium syndrome – a risk when a patient has high urea levels that are lowered too quickly.
- Clotting of the extracorporeal circuit.
- Accidental disconnection – risk of serious blood loss.
- Air embolism.
- Longer term risks:
- Vascular calcification and cardiovascular disease.
- Dialysis-related amyloidosis – beta-2 microglobulin is poorly cleared via haemodialysis, it can accumulate and deposit in various tissues. Risk is reduced by using haemodiafiltration or a high-flux membrane (larger pores).
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is
Clinical Genetics ST3

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru
Clinical Radiology ST3

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning
Paediatric Surgery ST3


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

