


 Close
 29th May 2023
Hodgkin’s lymphoma
Hodgkin’s lymphoma
Overview
Hodgkin’s disease is a B cell lymphoproliferative malignancy characterised by the presence of Reed Sternberg and Hodgkin cells surrounded by an inflammatory infiltrate. It has an incidence of 2.7 cases per 100,000 people per year in the UK. There is a bimodal distribution in Hodgkin’s with peaks in the 15-34 age group and over 70s.
The aetiology is not completely understood but is thought to be linked to infection, and 50% of cases show infection with EBV. HIV and immunosuppression are also risk factors.
Most people present with painless lymphadenopathy, typically in the lower neck or supraclavicular region. Mediastinal involvement is common and splenomegaly or distant lymphadenopathy is possible. B symptoms are present in only 25% (fevers, 10% weight loss in 6 months and drenching night sweats). Pruritus and alcohol induced lymph node pain is also possible.
Histological types of Hodgkin’s lymphoma
Hodgkin’s can be divided into classical and non-classical subtypes. Classical Hodgkin’s subtypes all show evidence of Reed Sternberg and Hodgkin cells and behave in a similar fashion. They are treated the same way and carry a similar prognosis.

Close up of tissue specimen showing a Reed-Sternberg cell.
Image Source: Wikimedia Commons (2008). Reed-sternberg cell, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Reed-sternberg_cell.jpg (Accessed on: 10 January 2023).

Classical subtypes include
- Nodular sclerosis (70%)
- Mixed cellularity (25%)
- Lymphocyte-rich (5%)
- Lymphocyte-depleted (<1%)
Nodular lymphocyte predominant HD (Non-classical) makes up 5% of all Hodgkin’s disease. It behaves quite differently to Classical Hodgkin’s and does not show evidence of Reed Sternberg cells. It tends to progress more slowly.
Diagnosis
- Bloods
- Full panel to look for cytopenias, renal and liver dysfunction pre-chemo
- HBV, HCV, HIV prior to chemo (risk of reactivation)
- Imaging – PET CT is first line now
- Biopsy – ideally excision biopsy, but at least core biopsy. No role for FNA.
Staging (Lugano system)
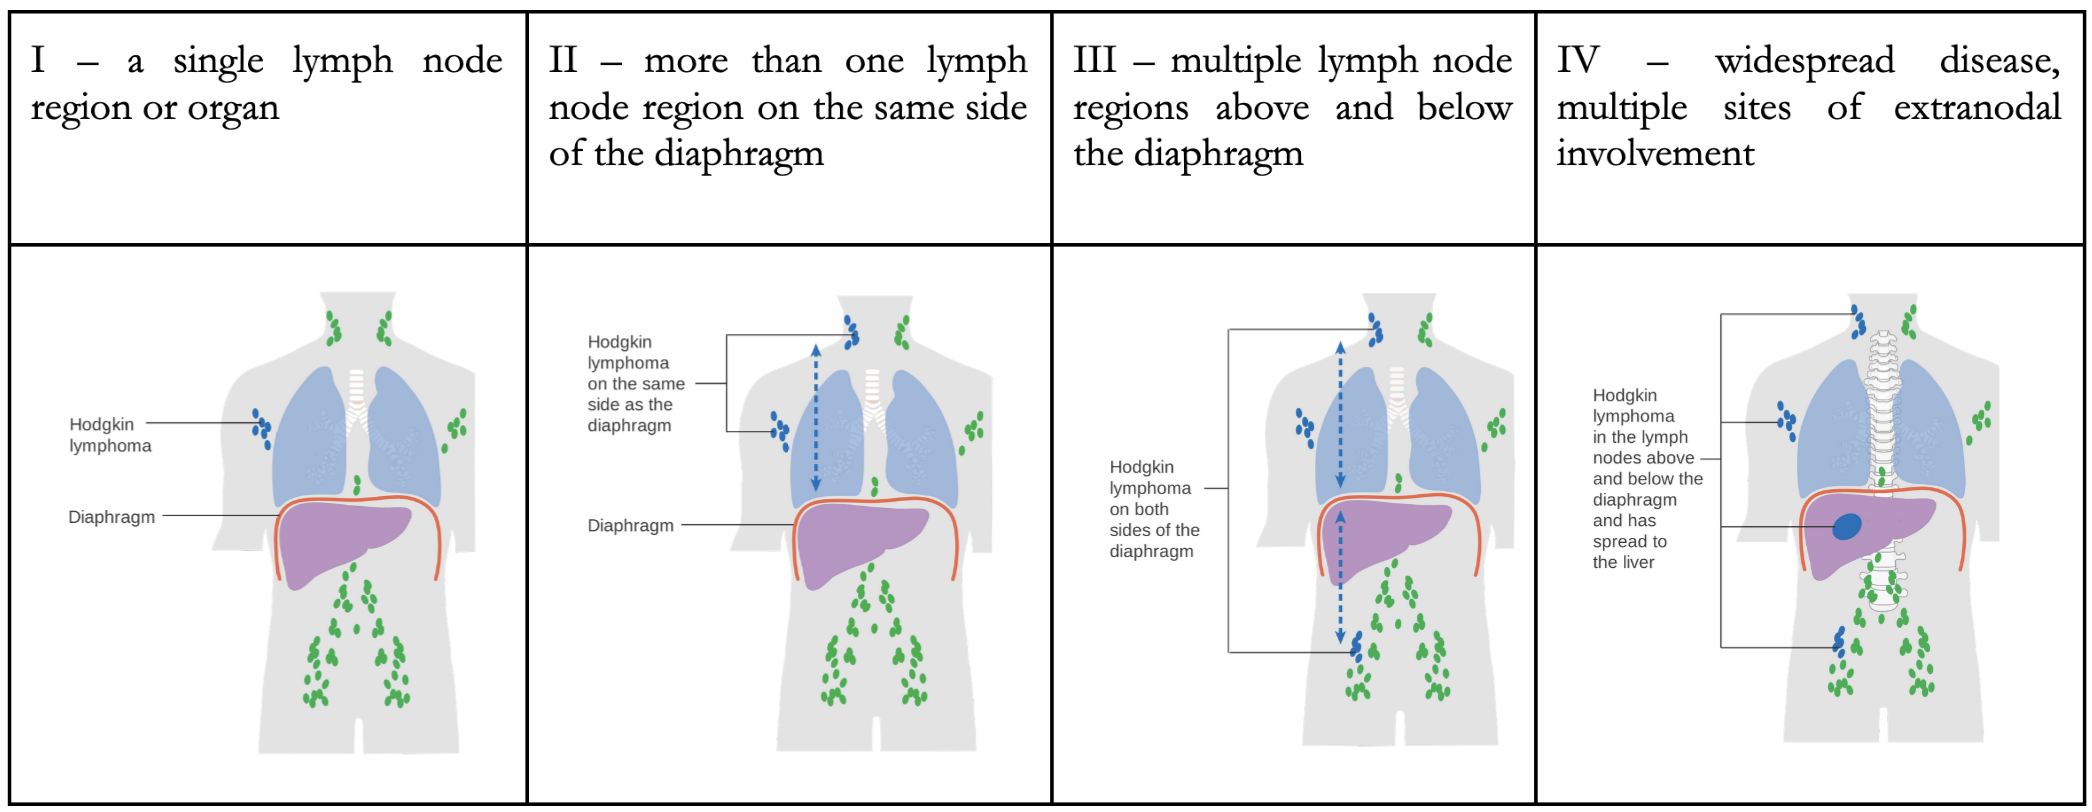
Adapted image of Lugano staging system.
Image Sources:
- Wikimedia Commons (2014). Diagram showing stage 1 Hogkin’s lymphoma CRUK 191, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Diagram_showing_stage_1_Hogkin’s_lymphoma_CRUK_191.svg (Accessed on: 10 January 2023).
- Wikimedia Commons (2014). Diagram showing stage 2 Hodgkin’s lymphoma CRUK 208, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Diagram_showing_stage_2_Hodgkin’s_lymphoma_CRUK_208.svg (Accessed on: 10 January 2023).
- Wikimedia Commons (2014). Diagram showing stage 3 Hodgkin’s lymphoma CRUK 221, Licensed under a creative commons licence. Available for free at: https://en.wikipedia.org/wiki/File:Diagram_showing_stage_3_Hodgkin’s_lymphoma_CRUK_221.svg (Accessed on: 10 January 2023).
- Wikimedia Commons (2014). Diagram showing stage 4 Hodgkin’s lymphoma CRUK 230, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Diagram_showing_stage_4_Hodgkin’s_lymphoma_CRUK_230.svg (Accessed on: 10 January 2023).


Treatment
Treatment for Hodgkin’s disease aims to achieve a balance between the risk of remission and the risk of long-term complications from toxicity from chemotherapy.
Treatment is determined by whether the disease is early or advanced.
Early disease (stage I or II) can be divided into favourable or unfavourable, based upon factors such as ESR, presence of B symptoms, age, and bulk of disease. Early-stage disease is usually treated with a combination of chemotherapy and radiotherapy and treatment can be escalated or de-escalated in intensity depending on the response to treatment, which is measured through interval PET-CT scan.
Advanced disease is treated with chemotherapy, which is more intense than with early disease.
A cure is possible for both early and advanced disease. Long term remission is achieved in around 90% of early-stage disease and 60-80% of advanced-stage disease.
One of the major complications of treatment for Hodgkin’s disease is the long-term sequelae of the treatment itself. This includes:
- Second malignancy – skin cancer, MDS, AML, breast cancer, thyroid cancer
- Cardiovascular disease – MI, angina, CHF, valvular disorders
- Pulmonary toxicity
- Impaired fertility
Patients with Hodgkin’s disease need irradiated blood products for life.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

