


 Close
 29th May 2023
Multiple myeloma
Overview
Multiple myeloma is the second most common type of haematological malignancy (after non-Hodgkin’s lymphoma). Nearly 6000 people per year are diagnosed with myeloma in the UK. The median age at presentation is 70 years of age. Overall, the risk for myeloma increases with age. It is slightly more common in men (57%) and in the Afro-Caribbean population.
Myeloma is a condition in which there is a malignant proliferation of plasma cells, which are terminally differentiated from B cells and produce antibodies. These malignant plasma cells invade and destroy the bone marrow and secrete a monoclonal protein/antibody called a paraprotein. Myeloma is subclassified by the subtype of antibody which they produce e.g. IgG or IgA. Together, the destruction of the bone marrow and release of paraprotein are responsible for the complications and symptoms seen in myeloma.
Presentation
Multiple myeloma classically presents with ‘CRAB’ symptoms; indeed these symptoms are considered a hallmark of the disease.
C – hypercalcaemia
R – renal impairment
A – anaemia
B – bone lesions
In order to establish a diagnosis of myeloma, there needs to be a myeloma-defining event plus evidence of a clonal population of plasma cells >10% in bone marrow.
Myeloma defining event:
- >60% plasma cells in bone marrow
- Light chain ratio >100
- Focal bone lesions on MRI/CT
- Hypercalcaemia >2.75
- Hb <100 without other causes
- Renal insufficiency CrCl <40 without other causes
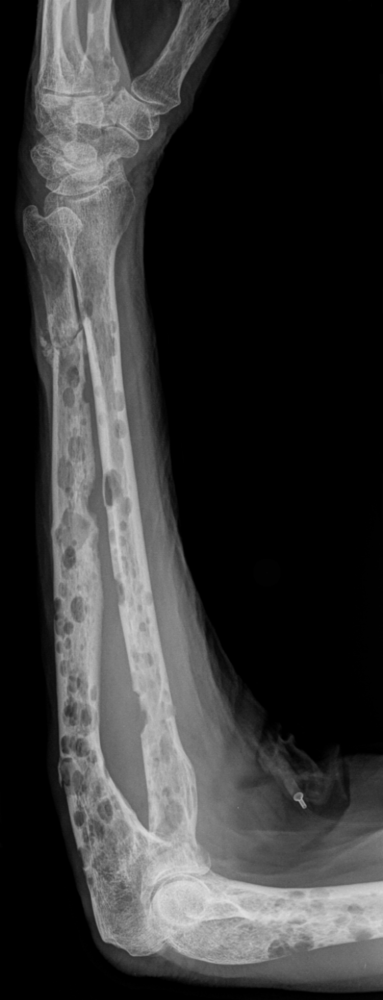
XR of forearm showing extensive lytic lesions in a patient with myeloma.
Image Source: Wikimedia Commons (2019). Multiple myeloma, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/Category:Multiple_myeloma (Accessed on: 10 January 2023).
Myeloma can affect multiple organ systems, most commonly the bones, blood, kidneys, and immune system. It can also be associated with cardiac impairment if there is concurrent AL-type amyloidosis, which is closely linked in a minority of myeloma presentations.
Standard investigations for myeloma include:
- Bloods
- FBC, renal function, calcium, serum Ig electrophoresis* and serum free light chains plus 𝛽-2-microglobulin
- Imaging – whole body MRI is the gold standard investigation to evaluate for bony lesions
- Bone marrow aspirate and trephine
*Interpretation of serum electrophoresis and serum free light chains – myeloma is a clonal disorder, and all clonal plasma cells will secrete an identical immunoglobulin which will be associated with either kappa or lambda light chains. The electrophoresis should show a monoclonal band if a paraprotein is present, which can be quantified. Polyclonal bands can be present during infection or inflammation and are normal. Likewise, a rise in both kappa and lambda light chains can occur in renal dysfunction or inflammatory conditions.
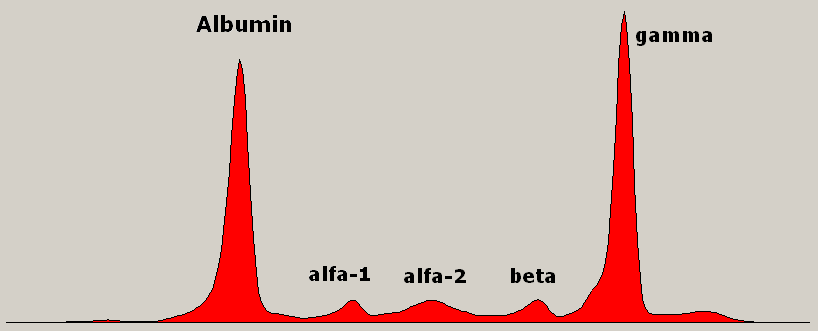
Serum immunoglobulin electrophoresis showing a monoclonal spike in gamma region.
Image Source: Wikimedia Commons (2009). Monoclonal gammopathy Multiple Myeloma, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Monoclonal_gammopathy_Multiple_Myeloma.png (Accessed on: 10 January 2023).

Treatment
Myeloma is not considered a curable condition, but treatment has improved significantly in the last few decades. The details of treatment are beyond the scope of knowledge required for MRCP Part 1. However, treatment strategies are generally divided based on whether a patient is fit enough to undergo an autologous stem cell transplant or not. Eligible patients will undergo induction therapy followed by autologous stem cell transplant with the aim being as long a period of disease-free interval as possible. Most treatment is based on triple therapy with a combination of targeted treatment, traditional chemotherapy drugs and steroids.
When patients relapse, there are multiple further lines of treatment available, if well enough to continue. The chance of achieving remission and the duration of this decreases with each line of therapy. Some patients will receive 4th or even 5th line therapy.
10% of people will die within one year of presentation but some will live > 20 years. Overall 5-year survival is just over 50%.
Prognostic factors
Previously based on ISS scoring system. This is not as useful with improved treatments as prognosis has changed. A revised scoring system incorporates cytogenetics.
| Stage | I | II | III |
| Criteria | 𝛽-2-microglobulin<3.5 and albumin >35 | Not fitting I or II | 𝛽-2-microglobulin >5.5 |
Increasing age and or frailty are also poor prognostic factors, although not formally incorporated into scoring systems.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

