


 Close
 25th June 2023
Cranial nerves of the face – V, VII
CN V – Trigeminal nerve
The trigeminal nerve is divided into ophthalmic (V1), maxillary (V2) and mandibular (V3) divisions which convey sensory impulses in the distribution outlined in the image below.
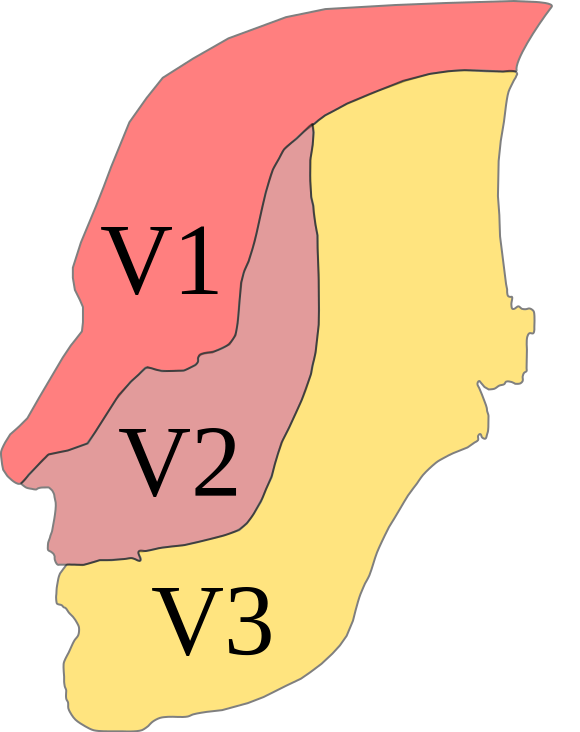
Dermatome distribution of the trigeminal nerve.
Image Source: Wikimedia Commons (2009). Trig innervation, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Trig_innervation.svg (Accessed on: 11 January 2023).

The ophthalmic V1 branch supplies the scalp and forehead, conjunctiva, cornea, to the nose. The maxillary V2 supplies the lower eyelid, lower nose, maxilla, palate, and maxillary teeth, while the mandibular V3 branch supplies the oral cavity, mandibular teeth, and gums. Of note, all branches have some sensory supply to the commensurate parts of the meninges and sinuses in their distribution. The mandibular (V3) division also carries motor fibres for mastication, supplying the masseter, temporalis muscle, lateral and medial pterygoids, as well as supporting muscles that help with the process of mastication like the tensor tympani, which dampens loud noises including from chewing, and the mylohyoid, anterior belly of the digastric and tensor veli palatini which assist in biting and swallowing.
Hutchinson sign
Hutchinson sign refers to the involvement of the nasociliary nerve, a branch of V1 the ophthalmic nerve which innervates the cornea, eyelid, and lateral dorsum and tip of the nose in herpes zoster infections. It is relevant in the manifestation of herpes zoster ophthalmicus, which can present as periorbital and temporal pain before developing herpes zoster skin lesions in the distribution of the nasociliary nerve and can develop into ocular inflammation with corneal denervation. Care should be taken to differentiate this from Hutchinson’s pupil, which is unrelated and refers to an oculomotor nerve lesion causing an ipsilateral fixed dilated pupil.
Loss of corneal reflex
The corneal blink reflex is a loop between the trigeminal and the facial nerves, where contact with the cornea induces both the blink reflex and tear production. Disorder or disruption of the trigeminal nerve can cause the loss of this reflex, leading to loss of corneal health and damage. This can happen in pontine stroke or progressive supranuclear palsy.
Trigeminal neuralgia
Trigeminal neuralgia is an intense sporadic neuropathic pain confined to and following the distribution of the trigeminal nerve, manifesting with unilateral, severe, shooting or burning episodic pain with each episode lasting seconds to minutes, starting and stopping suddenly. Intervals between each episode are unpredictable and can happen multiple times a day, with episodes occurring over weeks, months to years. It can be triggered by touch (even that of a draught or wind), mastication, changes in temperature, and some types of food, including caffeine-containing, spicy, acidic, or strong flavoured foods.
Trigeminal neuralgia can be primary or secondary. The aetiology of primary trigeminal neuralgia is not clear but is strongly suspected to be related to compression of the trigeminal nerve divisions from contact with normal vascular structures, where the issue is intrinsic to the structure of the nerve with physiological variation. This accounts for 75% of cases and is the most common cause of trigeminal neuralgia. Secondary trigeminal neuralgia arises when the trigeminal nerve is affected by another medical condition, for example, demyelination from multiple sclerosis, invasion from a tumour or abnormal compression from masses like an arteriovenous malformation.
Trigeminal neuralgia needs to be distinguished from trigeminal autonomic cephalalgias such as cluster headaches, paroxysmal hemicrania, short-lasting unilateral neuralgiform headache attacks with conjunctival injection and tearing (SUNCT) and short-lasting unilateral neuralgiform headache attacks with autonomic symptoms (SUNA). The trigeminal autonomic cephalalgias share many features with trigeminal neuralgia, presenting as severe unilateral headache in a trigeminal distribution with ipsilateral cranial autonomic symptoms, such as ptosis, conjunctival tearing, lacrimation, and rhinorrhoea. While there is debate on whether these are distinct entities or a continuum of disorders on the same spectrum, these conditions can be distinguished by attack duration and frequency, triggers, as well as response to treatment and treatment types. Trigeminal neuralgia is characterised by a trigger area, with attacks that tend to be shorter (seconds to a few minutes) but which have a refractory period, with a high variability in frequency in attacks which can happen multiple times in the day, milder to non-existent autonomic symptoms, and with a lack of response to high dose oxygen and triptans which are useful in cluster headaches or lidocaine which is useful in SUNCT.
Treatment is primarily divided into medical and surgical options, with medical options focused on anticonvulsants and nerve modulating analgesic agents. Carbamazepine is the first line treatment for trigeminal neuralgia, with second line treatment being other anticonvulsants including oxcarbazepine which is a structural derivative of carbamazepine (reduced risk of the known adverse effects of agranulocytosis and anaemia of carbamazepine), lamotrigine, gabapentin, and phenytoin. Carbamazepine should be avoided in pregnancy due to the risk of spina bifida and cleft palate, while lamotrigine has the least reported severe effects in pregnancy. Nerve modulating analgesic agents aim to provide symptomatic relief and include amitriptyline and duloxetine.
Surgical treatments are generally reserved for patients who have severe pain with a debilitating impact on quality-of-life refractory to pharmacological treatments. These are categorised as destructive (i.e. lesioning techniques) or non-destructive depending on whether trigeminal nerve function and integrity is intentionally targeted. Non-destructive interventions include microvascular decompression, while destructive interventions like percutaneous radiofrequency rhizotomy, percutaneous balloon compression and stereotactic radiosurgery treat trigeminal neuralgia through the use of electrocoagulation, mechanical compression or ionising radiation respectively to selectively destroy the part of the nerve suspected to cause pain.
CN VII – Facial Nerve
The facial nerve is a mixed nerve that travels through the internal acoustic meatus and splits into five major branches (frontal, zygomatic, buccal, marginal mandibular, and cervical) within the parotid gland, which then go on to supply the motor functions of facial expression, autonomic impulses to lacrimal and salivary glands, stapedius muscle innervation that protects against loud noises and sensory function to the anterior two-thirds of the tongue.
Disorders of the CN VII lower motor nucleus will result in an ipsilateral facial asymmetry, with absence of transverse wrinkles of the forehead, loss of nasolabial fold, drooped corner of the mouth and loss of tone of the orbicularis oculi leading to eversion of the lower eyelid on the affected side. There is also loss of the efferent part of the conjunctival reflex, leading to uncontrolled tearing and inability to close the eye, which can result in eventual corneal ulceration. Bell’s Palsy is a classic example of an ipsilateral lower motor neuron CN 7 disorder.
Contralateral and bilateral innervation
CN VII demonstrates the effects of bilateral innervation from upper motor neuron sources as it receives stimulation from both the ipsilateral and the contralateral corticobulbar tracts.
The upper muscles of facial expression receive stimulation from both the ipsilateral and the contralateral corticobulbar tracts while the lower muscles receive stimulation only from the contralateral corticobulbar tract. A pathology disrupting this stimulation, e.g. an upper motor neuron lesion such as stroke, would cause loss of function of the contralateral lower muscles of facial expression but sparing of the upper muscles of facial expression as they would still be receiving stimulation from the ipsilateral upper motor neuron component.
Bell’s Palsy
A Bell’s Palsy is the classic example of an isolated lower motor neuron cranial nerve palsy. It manifests as a unilateral complete paralysis of the facial muscles of one side of the face. While the aetiology of a Bell’s Palsy is not completely clear, it has been associated with several conditions, specifically diabetes mellitus, herpes simplex type 1 viral infection, pregnancy, herpes zoster viral infection (shingles), hypertension, Lyme disease and autoimmune disease.
Due to the unilateral complete palsy of the facial muscles with no forehead sparing, this leads to ocular complications due to loss of the ability to blink and protect the exposed eye, dysarthria drooling, and difficulty eating and drinking due to the loss of facial muscle actions, as well as loss of ancillary functions of the facial nerve which include loss of function of the stapedius muscle in the ear leading to tinnitus and hyperacusis and loss of taste as a result of the facial nerve’s innervation to the anterior two thirds of the tongue.
During the recovery from Bell’s palsy, abnormal connections can form during nerve regeneration where efferent fibres from the superior salivary nucleus synapse with parasympathetic fibres of the facial nerve, causing tears to be produced during salivation in what is known as Bogorad syndrome or “Crocodile tears syndrome.”. This is similar to, but distinct from Frey syndrome, where sweating occurs with salivation due to abnormal connections between sympathetic and parasympathetic nerves associated with the auriculotemporal nerve (branch of mandibular division V3 of Trigeminal nerve), usually with an iatrogenic aetiology, e.g. parotid surgery.
Treatment of a Bell’s Palsy is with high dose oral prednisolone (a 10-day tapering course starting at 60mg Prednisolone) to reduce facial nerve inflammation. Investigations for conditions associated with Bell’s palsy should be considered where clinically suspected, e.g. Hba1c testing for diabetes, Lyme disease antibody titres. Antivirals such as aciclovir may be considered but should not be used in isolation. Eye protection is very important to replace the functions that serve to protect the cornea; lubricating eye drops and eye patches with ophthalmology follow-up is typically indicated.
Ramsay Hunt Syndrome
Ramsay Hunt syndrome is the manifestation of the reactivation of dormant varicella-zoster virus (shingles) with spread to the facial nerve. It is more common in immunocompromised individuals, e.g. patients with HIV, patients on immunotherapy, chemotherapy, or radiotherapy. Clinically, it manifests as a vesicular, erythematous, painful rash, in or around one ear with an ipsilateral ‘Bell’s palsy’ and can affect CN 5 and CN 8 with symptoms such as vertigo, tinnitus and hearing loss. The vesicles can be confined only to the auditory canal with facial pain and otalgia; all patients with facial pain and palsy should have an otoscopic exam.
Treatment is focused on the following:
- Disease modifying: Antivirals, e.g. acyclovir, famciclovir, together with corticosteroids.
- Symptomatic: carbamazepine for neuralgia, antihistamines, and anticholinergics for vertigo
- Eye care as in the treatment of a Bell’s palsy
Parotid tumour
The extracranial motor branch of the facial nerve splits into 5 branches in the parotid gland – the temporal branch, zygomatic branch, buccal branch, marginal mandibular branch, and cervical branch. A lesion in the parotid gland, e.g. trauma/iatrogenic during surgery or a tumour, can result in a lower motor neuron facial nerve palsy.
Vestibular schwannomas
A vestibular schwannoma, also known as an acoustic neuroma, is a benign tumour developing from the vestibulocochlear nerve. It is the most common cerebellopontine angle tumour (85%).
Cerebellopontine angle (CPA) tumours are the most common tumours in the posterior cranial fossa, specifically in the triangular space in the posterior cranial fossa, which is bound by the tentorium superiorly, medulla posteromedially and petrous part of temporal bone posterolaterally, through which run the anterior inferior cerebellar artery, CNs 5, 6, 7, and 8. Tumours in this area can cause ipsilateral LMN signs in CN 7, with overlapping CN5, 8, and 9 palsies. Thus a patient presenting with such a collection of ipsilateral signs, including the loss of corneal reflex, should prompt suspicion of a CPA lesion. Bilateral vestibular schwannomas are associated with neurofibromatosis type 2.
Pontine lesions
The facial cranial nerve nuclei of CN7 lies in the pons and is closely associated with the nuclei of the abducens nerve (CN6). A lesion in the pons, e.g. infarct or tumour, can cause an ipsilateral CN 7 and CN 6 palsy, with contralateral hemiplegia due to being above the decussation of the corticospinal tracts.
Bilateral facial palsy
A rare manifestation of facial palsy, these can be sequential, i.e. unilateral progressing to bilateral facial palsy or concurrent. A wide range of causes of unilateral facial palsy can have bilateral facial palsy, albeit rarely. As noted above, bilateral CPA tumours, or large pontine lesions (stroke/tumour) or systemic disease with multi nerve affecting pathologies such as Lyme disease, syphilis, sarcoidosis, demyelinating disease like Guillain Barre syndrome, vasculitis, and diabetes mellitus can be a cause. Rarer causes include hereditary congenital facial palsy, Melkersson-Rosenthal Syndrome (recurrent antihistamine resistant oedema of lips, cheeks, and eyelids with recurrent facial palsy and cheilitis) and Moebius-Poland syndrome (congenital facial and abducens palsy with pectoral and limb deformities).
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

