


 Close
 9th September 2024
Diabetes Mellitus
Overview
Diabetes mellitus is a group of metabolic disorders characterised by persistent hyperglycemia caused by deficient insulin secretion, resistance to the action of insulin, or both. There are various classifications of diabetes. Broadly, it can be categorised into Type 1, Type 2, Type 3 (secondary diabetes), gestational diabetes, and genetic forms of diabetes (such as Wolfram syndrome, Maturity Onset Diabetes of the Young (MODY)), neonatal diabetes, and autoimmune diabetes (LADA). Type 3 diabetes occurs secondary to the destruction of the pancreas due to factors such as surgery, malignancy, alcohol, medications, or genetic diseases like cystic fibrosis.
Type 1 diabetes
Type 1 Diabetes Mellitus (T1DM) is primarily an autoimmune disorder (90% of cases), leading to the destruction of insulin-producing beta cells in the pancreas, resulting in an absolute deficiency of insulin and subsequent hyperglycaemia. In some patients, there may be no evidence of autoimmune destruction; this is referred to as idiopathic T1DM. T1DM is a polygenic heritable disease that arises when environmental factors trigger autoimmunity in genetically susceptible individuals (HLA-DR3 > DR4 haplotypes).
Diagnosis
T1DM is diagnosed when persistent hyperglycaemia (random plasma glucose > 11 mmol/L) is observed, caused by absolute insulin deficiency, a family history, and other symptoms traditionally associated with diabetes, such as fatigue, polyuria, polydipsia, and rapid weight loss. Older adults may present atypically. Diagnosis is confirmed by measuring C-peptide levels and/or diabetes-specific antibody titres.
Numerous antibodies are associated with a higher risk of developing T1DM, although their presence is not part of the diagnostic criteria. These autoantibodies include islet cell antibodies (ICA), glutamic acid decarboxylase (GAD), islet tyrosine phosphatase (IA-2), and zinc transporter 8 (ZnT8).
Management
Patients with T1DM fundamentally require insulin replacement. NICE favours starting with basal bolus regimens (twice daily long acting detemir). These patients need structured education on how to adjust insulin doses for the carbohydrate quantity of meals (DAFNE courses). Cardiovascular risk factors, as with T2DM, are important prognostically and should not be neglected. Metformin can be added if the patient has a BMI of above 25, but equally insulin can be uptitrated. Patients should measure their glucose levels 4 times a day. Sometimes, it is appropriate to measure more often (10 times a day), for instance, in acute illness, exercise, or when HbA1c targets are not met (aim for less than 6.5%/48mmol/mol). Poor glucose control can lead to Impaired hypoglycaemic awareness, which is a state that occurs when hypoglycaemia recurs so often that patients stop getting hypoglycaemic symptoms. Continuous glucose monitoring devices (Libre) measure glucose levels in the interstitium and are increasingly used. Blood glucose targets should not be increased to avoid hypo episodes. Continuous subcutaneous insulin infusions can be used in impaired hypo awareness or in patients with persistently high HbA1c levels.
Diabetic ketoacidosis
The combination of hyperglycaemia (>11 mmol/l), acidosis (bicarbonate <15 mmol/L; pH <7.3) and ketosis (blood ketones <3 mmol/l, urine ketones ≥++) leads to the diagnosis of DKA, which can often be the first presentation of T1DM. Alternatively, it can be provoked by infection or myocardial ischemia. Note that it is possible for “ketosis-prone” type 2 diabetics to develop DKA. Euglycaemic ketoacidosis can also occur with normal blood sugar levels, as a side effect of SGLT2 inhibitors (e.g., dapagliflozin). Management of DKA consists of fixed rate insulin infusion (FRII) at 0.1 units/kg/hr and rehydration. Basal insulin and insulin pumps should continue at all times. DKA patients are considerably dehydrated and potassium depleted. For potassium levels between 3.5 and 5.5 mmol/l, use 40 mmol KCl in addition to saline. Resolution of DKA occurs when serum ketones are <0.6 mmol/l and pH >7.3. When DKA resolves, switch the patient to their normal insulin regimen (if they are eating) or to a variable-rate insulin infusion (if not eating).
Hypoglycaemia
Hypoglycaemia is associated with all forms of diabetes, particularly when insulin is used. It is defined as a glucose level of <3.5 mmol/l and is more prone to occur in those with illnesses, diabetic patients on insulin therapy, medications with hypoglycemia risk such as sulfonylureas, missed meals or being nil by mouth, insulin dose errors, renal impairment in patients on insulin, recent changes to diet or weight while on insulin, Addison’s and coeliac disease (which can co-occur with T1DM), gastroparesis (a complication of diabetes and hyperglycemia, which can be treated with erythromycin/metoclopramide), liver disease, alcohol, and insulinomas. Symptoms of hypoglycemia include tremors, sweating, fatigue, and palpitations. This can progress to syncope, convulsions, and death. Impaired awareness is, therefore, exceedingly dangerous and is an indication for continuous subcutaneous insulin infusions. If refractory to treatment, impaired awareness can ultimately be treated with islet or pancreatic transplantation.
Other complications
The complications of persistent hyperglycemia are divided into macrovascular and microvascular. Macrovascular complications encompass the increased risk of stroke, MI, and peripheral arterial disease. Microvascular complications encompass neuropathy, nephropathy, and retinopathy. Retinopathy starts as early non-proliferative (aneurysms, exudates, and small haemorrhages) and progresses to proliferative, which can result in retinal detachment and vitreous haemorrhage (diabetes is the most common cause of acquired blindness in the UK). Nephropathy manifests as albuminuria initially and progresses to CKD. Neuropathy can be sensorimotor or autonomic (gastroparesis, erectile dysfunction, silent myocardial infarction).
DVLA
For Group 1 (cars and motorcycles) and Group 2 (large vehicles and lorries) licences, patients must inform the DVLA if they begin long-term insulin treatment. Episodes of severe hypoglycaemia (those that the patient cannot treat without assistance) can lead to the licence being revoked. For Group 1 licences, more than one episode of severe hypoglycaemia will result in the licence being revoked. For Group 2 licences, only one episode is required for revocation. Any single episode of severe hypoglycaemia while driving will result in the licence being revoked.
| Group 1 (cars and motorcycles) | Group 2 (bus and lorries) | |
|---|---|---|
| Requirements for driving licence | Adequate awareness of hypoglycaemia
(<2 episodes of severe hypoglycaemia in the last 12 months) |
Full awareness of hypoglycaemia
(No previous episode of severe hypoglycaemia in the last 12 months) |
References
- NICE CKS (2020) Type 1 Diabetes Guidelines, Available at: https://cks.nice.org.uk/topics/diabetes-type-1/
- Driver and Vehicle Licensing Agency. Assessing fitness to drive – a guide for medical professionals. https://www.gov.uk/government/publications/assessing-fitness-to-drive-a-guide-for-medical-professionals
- Sinclair AJ, Dunning T, Dhatariya K; an International Group of Experts. Clinical guidelines for type 1 diabetes mellitus with an emphasis on older adults: an Executive Summary. Diabet Med. 2020 Jan;37(1):53-70. doi: 10.1111/dme.14135. Epub 2019 Sep 23. PMID: 31498912.BMJ 2012 (Mobile App)
- Dhatariya KK; Joint British Diabetes Societies for Inpatient Care. The management of diabetic ketoacidosis in adults-An updated guideline from the Joint British Diabetes Society for Inpatient Care. Diabet Med. 2022 Jun;39(6):e14788. doi: 10.1111/dme.14788. Epub 2022 Feb 27. PMID: 35224769.
- Aune D et al (2015); “. Physical activity and the risk of type 2 diabetes: a systematic review and dose-response meta-analysis”.. Eur J Epidemiol. 2015 Jul;30(7):529-42. doi: 10.1007/s10654-015-0056-z. Epub 2015 Jun 20. PMID: 26092138.
- Misra S, Oliver NS. Diabetic ketoacidosis in adults. BMJ. 2015 Oct 28;351:h5660. doi: 10.1136/bmj.h5660. Erratum in: BMJ. 2015;351:h5866. PMID: 26510442.
- Polly J. Bingley, Clinical Applications of Diabetes Antibody Testing, The Journal of Clinical Endocrinology & Metabolism, Volume 95, Issue 1, 1 January 2010, Pages 25–33, https://doi.org/10.1210/jc.2009-1365
- Plewa MC, Bryant M, King-Thiele R. Euglycemic Diabetic Ketoacidosis. [Updated 2023 Jan 29]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2024 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK554570/
- Joint Formulary Committee. British National Formulary (online) London: BMJ and Pharmaceutical Press <http://www.medicinescomplete.com; https://bnf.nice.org.uk/treatment-summaries/diabetic-hyperglycaemic-emergencies/
- Katsarou, A., Gudbjörnsdottir, S., Rawshani, A. et al. Type 1 diabetes mellitus. Nat Rev Dis Primers 3, 17016 (2017). https://doi.org/10.1038/nrdp.2017.16
- The Hospital Management of Hypoglycaemia in Adults with Diabetes Mellitus; Joint British Diabetes Societies for inpatient care 4th Edition; January 2020; Esther Walden; Debbie Stanisstreet; Alex Graveling
- Type 1 diabetes in adults: diagnosis and Management; Nice guidance; August 2022; https://www.nice.org.uk/guidance/ng17/chapter/Recommendations
- Driving and diabetes; Diabetes UK; Found at: Driving when you have diabetes | Diabetes UK
Type 2 diabetes
Type 2 diabetes mellitus is a chronic progressive metabolic disorder, characterised by hyperglycaemia. The predominant problem is increased insulin resistance coupled with a relative deficiency of insulin. There is a slower beta cell loss compared to type 1. Although the aetiology of both differs, they both lead to hyperglycaemic states and share common macrovascular (heart disease, cerebrovascular and peripheral vascular disease) and microvascular (retinopathy, nephropathy, and neuropathy) complications.
Diagnosis
The diagnostic criteria for type 2 diabetes includes the following:
- A fasting plasma glucose of 7 mmol/l or greater
- A random blood sugar 11.1mmol/l or greater
- A HbA1c of 48 mmol/mol (6.5%) or greater
- A plasma glucose of 11.1mmol/l or greater after two hours of oral 75g glucose in the form of the tolerance test
If the patient is symptomatic, NICE advise that a single abnormal HbA1c or fasting plasma glucose result can be used for diagnosis, but it is sensible to repeat the test. In asymptomatic patients, do not diagnose based on a single abnormal result. Repeat testing is required. If the repeat test is normal, arrange for interval testing.
HbA1c is a minor haemoglobin component formed from the chemical condensation of glucose and haemoglobin. It forms slowly and is directly proportional to serum glucose concentration. The normal life of a red blood cell is 120 days. If a larger number of red cells survive for longer periods of time, then they will have more time to form HbA1c. Therefore, factors that reduce the destruction of red cells (such as splenectomy) will falsely increase the concentration of HbA1c. Factors that reduce red cell production (such as B12, folate, and iron deficiency anaemias, as well as aplastic anaemia) will reduce the number of new red cells without HbA1c, thus falsely increasing the concentration of HbA1c. Conversely, reticulocytosis (as seen in hemolytic anaemia or blood loss) and reduced red cell lifespan (as in splenomegaly or pregnancy) will falsely decrease HbA1c concentration. For unknown reasons, chronic alcohol consumption can also falsely increase HbA1c concentrations. Haemoglobinopathies cause unpredictable changes in HbA1c levels. In these circumstances, it might be better to use fructosamine levels or average glucose levels.
| Reduced erythrocyte lifespan (HbA1c increased) | Increased erythrocyte lifespan (HbA1c decreased) |
|---|---|
| Deficiencies of iron and vitamin B12 | Administration of iron, B12 and erythropoietin |
| Alcoholism | Chronic liver disease |
| Splenectomy | Splenomegaly (through destruction of RBCs) |
| Chronic large doses of aspirin (through acetylation of haemoglobin) | Antiretrovirals (ribavirin) and antibiotics (dapsone) |
| Haemoglobinopathies, increased foetal haemoglobin, methaemoglobin can both increase and decrease HbA1c | |
Management
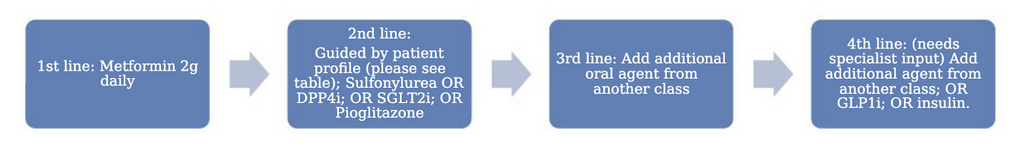
Prevention is the best strategy for diabetes management. High risk individuals should be screened and managed appropriately with structured educational programmes. Cardiovascular complications (myocardial infarctions and strokes) are the main cause of mortality amongst this group highlighting the importance of reducing risk and control of blood glucose. Management consists of a combination of drug treatment, education and lifestyle modifications including smoking cessation, reducing stress, exercise and change in diet. The main oral diabetic medications are shown below. Insulin can be considered instead of starting a third line medication.
Metformin
First-line drug treatment is metformin, a biguanide. The mechanism is not entirely clear, however it decreases hepatic gluconeogenesis and increases insulin sensitivity in the peripheral tissues. It can cause weight loss and rarely leads to hypoglycaemia, but it is known to cause gastrointestinal side effects. In view of this, the drug should be stepped up gradually over weeks, or clinicians can switch to a more tolerable modified release (MR) alternative. Contraindications include metabolic acidosis or a significantly reduced renal function (eGFR <30 or Creatinine >150).
Target HbA1c starts at 48 mmol/mol (6.5%) with lifestyle modifications and/or metformin. If, despite these measures, HbA1c rises to 58 mmol/mol (7.5%) or higher, drug treatment should be intensified. Dual and triple therapy agents include dipeptidyl peptidase-4 (DPP-4) inhibitors, thiazolidinediones, sulphonylureas, glucagon-like peptide 1 (GLP-1) agonists and sodium-glucose co-transporter-2 (SGLT2) inhibitors. If three agents fail to control HbA1c, insulin-based treatment should be considered.
DPP-4 inhibitors
Examples of DPP-4 inhibitors include sitagliptin, vildagliptin and linagliptin. During digestion, the gastrointestinal tract secretes incretin hormones (GLP-1, GIP) that stimulate insulin and inhibit glucagon. DPP-4 inactivates GLP-1 therefore inhibitors would enhance the incretin effect after meals and improve blood glucose control. There is a small risk of acute pancreatitis from DPP-4 inhibitors related to extra simulation of the pancreas though the full mechanism is unclear. These medications do not cause weight gain.
Thiazolidinediones
Pioglitazone, a thiazolidinedione, is an agonist of the peroxisome proliferator-activated receptor gamma (PPAR-γ). Agonism at this receptor induces changes that reduce peripheral insulin resistance. It can worsen heart failure, cause bladder cancer, lead to weight gain, and cause skeletal fractures due to reduced bone density.
Sulphonylureas
Sulphonylureas include gliclazide, glibenclamide and glipizide. They directly stimulate pancreatic beta cells to release insulin. The increased insulin can lead to the adverse effects of frequent hypoglycaemia and weight gain.
GLP-1 agonists
GLP-1 is an incretin secreted by intestinal L cells. GLP-1 agonists are mainly injectables; however, there are oral options as well. Similar to DPP-4 inhibitors, they enhance the incretin effect, stimulating insulin, inhibiting glucagon, and delaying gastric emptying. These agents do not typically cause hypoglycaemia and are well known to induce significant weight loss. Doctors can consider prescribing these when diabetes is not adequately treated with three medications. Furthermore, BMI must be above 35 kg/m², and reductions in HbA1c (1%) and weight (3%) must be observed after six months of treatment. GLP-1 agonists have been associated with acute pancreatitis, biliary disease, and hypersensitivity reactions.
SGLT2 inhibitors
These novel agents have been shown to be useful in those with elevated cardiovascular risks. SGLT are glucose transporter proteins found throughout the body, with SGLT2 located in the proximal tubule of the nephron. Inhibitors block glucose reabsorption in the kidney, leading to increased urinary glucose excretion. Examples of these agents are dapagliflozin and empagliflozin. Due to increased glycosuria, there is an increased risk of urinary tract infections, fungal infections, and DKA. These medicines should be used in addition to metformin in anyone who has pre-existing cardiovascular disease or is at high risk of developing cardiovascular disease.
Overview of the medications used to treat type 2 diabetes
| Drug class | Examples | Efficacy | CV benefit | Hypoglycemia risk | Effect on weight | Notes |
| Metformin | – | Moderate | Yes | Low | Reduction | |
| Sulphonylurea | Gliclazide | High | No | High | Gain | |
| SGLT2 inhibitor | Dapagliflozin | Moderate | Yes | Low | Loss | Indicated if QRISK >10% (in those 40 years and over), or if they have pre-existing cardiovascular disease |
| DPP4 inhibitor | Sitagliptin | Low/Moderate | No | Low | Gain | |
| TZD | Pioglitazone | Moderate | Probable (but fluid retention) | Low | Gain | Contraindicated in patients with a history of heart failure or significant cardiovascular disease |
| GLP-1 agonist | Dulaglutide | High | Yes | Low | Loss |
Consider reducing sulfonylurea Continue metformin, pioglitazone and SGLT2i |
| Insulin | Rapid acting (aspart), Intermediate acting (Humulin I), Long acting (glargine) | Very high | No | Highest | Gain | Reduce or stop sulfonylurea
Continue metformin, pioglitazone, DPP4i or SGLT2 |
Hyperosmolar hyperglycaemic state
In contrast to DKA, hyperosmolar hyperglycaemic state (HHS) develops over several days. It is characterised by profound fluid deficit, excessively high osmolality (2x Na + urea + glucose), and high glucose levels (>30 mmol/l) in the absence of ketosis or acidosis. Despite normal serum potassium concentrations, patients are often potassium-depleted. The treatment aims to rehydrate the patient using crystalloids and to reduce osmolality. Insulin therapy should not be routinely used as it can cause dangerously rapid reductions in osmolality, potentially leading to cerebral complications. However, in cases of mixed DKA/HHS syndromes, where acidosis and ketosis are present, insulin may be used. HHS has an extremely high mortality rate, up to ten times higher than that of DKA.
Non diabetic hyperglycaemia
Non-diabetic hyperglycaemia includes two conditions:
| Impaired fasting glycaemia (IFG): refers to a fasting glucose level of between 6.1mmol/L and 6.9mmol/L.
Impaired glucose tolerance (IGT): refers to a glucose level of between 7.8mmol/L and 11.1mmol/L after a 75g oral glucose tolerance test. |
References
- Recommendations: Type 2 diabetes in adults: Management: Guidance (2022) NICE CKS. Available at: https://www.nice.org.uk/guidance/ng28/chapter/Recommendations
- WHO (2011). Use of Glycated Haemoglobin (HbA1c) in the Diagnosis of Diabetes Mellitus (Abbreviated Report of a WHO Consultation). WHO/NMH/CHP/CPM/11.1
- DeSantis, A. and Dungan, K. (2024) Glucagon-like peptide 1-based therapies for the treatment of type 2 diabetes mellitus, UpToDate. Edited by D.M. Nathan and K. Rubinow
- Inzucchi, S.E. and Lupsa, B. (2022) Thiazolidinediones in the treatment of type 2 diabetes mellitus, UpToDate. Edited by D.M. Nathan and K. Rubinow
- Wexler, D.J. (2022) Sulfonylureas and meglitinides in the treatment of type 2 diabetes mellitus, UpToDate. Edited by D.M. Nathan and K. Rubinow
- DeSantis, A. (2024) Sodium-glucose cotransporter 2 inhibitors for the treatment of hyperglycemia in type 2 diabetes mellitus, UpToDate. Edited by D.M. Nathan and K.R. Rubinow
- Dungan, K. and DeSantis, A. (2023) Dipeptidyl peptidase 4 (DPP-4) inhibitors for the treatment of type 2 diabetes mellitus, UpToDate. Edited by D.M. Nathan and K. Rubinow. Available at: https://www.uptodate.com/contents/dipeptidyl-peptidase-4-dpp-4-inhibitors-for-the-treatment-of-type-2-diabetes-mellitus (Accessed: 19 February 2024)
- Management of diabetes Quick Reference Guide. (2010). Available at: https://www.sign.ac.uk/assets/qrg116.pdf
- Use of Glycated Haemoglobin (HbA1c) in the Diagnosis of Diabetes Mellitus: Abbreviated Report of a WHO Consultation. Geneva: World Health Organization; 2011. Annex 1, Some of the factors that influence HbA1c and its measurement. Available from: https://www.ncbi.nlm.nih.gov/books/NBK304266/
- Radin MS. Pitfalls in hemoglobin A1c measurement: when results may be misleading. J Gen Intern Med. 2014 Feb;29(2):388-94. doi: 10.1007/s11606-013-2595-x. Epub 2013 Sep 4. PMID: 24002631; PMCID: PMC3912281
- NICE Recommendations: Type 2 diabetes in adults: management; June 2022; available at Recommendations | Type 2 diabetes in adults: management | Guidance | NICE
- The Management of Diabetic Ketoacidosis in Adults; March 2023; Joint British Diabetes Societies; Prof Ketan Dhatariya, Norfolk and Norwich University Hospitals NHS Foundation Trust; available from: Joint British Diabetes Societies for Inpatient care | Diabetes UK
- Adeyinka A, Kondamudi NP. Hyperosmolar Hyperglycemic Syndrome. [Updated 2023 Aug 12]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2024 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK482142/
Maturity onset diabetes of the young
Maturity-Onset Diabetes of the Young (MODY) comprises a group of autosomal dominant disorders that typically present in adolescence or young adulthood (< 25 years of age). Indicators towards a diagnosis include:
- Young age at onset of diabetes
- Lack of ketosis at presentation
- Negative autoantibodies
- Strong family history of diabetes
young diabetic, lack of ketosis at presentation, negative autoantibodies and strong family history. Many patients with MODY are misdiagnosed and treated with low doses of insulin for extended periods until the true genetic diagnosis is made. Approximately 1-2% of diabetics in this country have MODY. Diagnosis is ultimately confirmed through genetic testing. Over six mutations have been linked to the development of MODY, with the most common being mutations in HNF1-alpha and glucokinase. The specific type of mutation dictates the treatment approach, and sulphonylureas are often effective.
References
- Balasubramanyam, A. (2024) Classification of diabetes mellitus and genetic diabetic syndromes, UpToDate. Edited by D.M. Nathan, J.I. Wolfsdorf, and K. Rubinow. Available at: https://www.uptodate.com/contents/classification-of-diabetes-mellitus-and-genetic-diabetic-syndromes#H403506088 (Accessed: 20 February 2024)
- Anık, Ahmet, Çatlı, Gönül, Abacı, Ayhan and Böber, Ece. “Maturity-onset diabetes of the young (MODY): an update” Journal of Pediatric Endocrinology and Metabolism, vol. 28, no. 3-4, 2015, pp. 251-263. https://doi.org/10.1515/jpem-2014-0384
Latent autoimmune diabetes of adults
LADA can be thought of as a slowly progressive variant of Type 1 Diabetes Mellitus (T1DM). It actually borrows pathophysiology from T1DM (it is an autoimmune condition and the same autoantibodies are present), and T2DM (there is some degree of insulin resistance). A diagnosis is likely if a patient fulfils the following three criteria:
- They are above 35 years old
- There are antibodies present (ICA, GAD, Ia-2, ZnT8)
- They remain insulin independent for at least 6 months from initial diagnosis.
C peptide can be helpful, as endogenous insulin production won’t initially be as low as in T1DM, so there will be residual C peptide production in the presence of autoantibodies. Insulin is the main therapy, but oral agents can also be used as for T2DM.
References
- Rajkumar V, Levine SN. Latent Autoimmune Diabetes. [Updated 2024 Mar 1]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2024 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK557897/
- Fourlanos, S., Dotta, F., Greenbaum, C.J. et al. Latent autoimmune diabetes in adults (LADA) should be less latent. Diabetologia 48, 2206–2212 (2005). https://doi.org/10.1007/s00125-005-1960-7
Type 3c diabetes
Type 3c diabetes encompasses all those causes of secondary diabetes, usually from pancreatic damage. The majority (>70%) are accounted for by chronic pancreatitis. Pancreatic cancer is another important cause, and NICE recommend considering a CT abdomen for those patients above 60 years old with new onset diabetes. Cystic fibrosis, hereditary hemochromatosis, and pancreatic resection are three other causes. Type 3c diabetes should be suspected in older patients who exhibit exocrine dysfunction (such as low fecal elastase or vitamin ADEK deficiency), have an identifiable cause, and lack Type 1 diabetes-associated antibodies. The treatment for Type 3c diabetes is similar to that for Type 2 diabetes, primarily involving oral agents.
References
- Ewald, N., Kaufmann, C., Raspe, A., Kloer, H. U., Bretzel, R. G., & Hardt, P. D. (2012). Prevalence of diabetes mellitus secondary to pancreatic diseases (type 3c). Diabetes/Metabolism Research and Reviews, 28(4), 338–342. https://doi.org/10.1002/dmrr.2260
- Diabetes mellitus secondary to pancreatic diseases (Type 3c) — Are we neglecting an important disease? Nils Ewald and Reinhard G. Bretzel; European Journal of Internal Medicine, 2013-04-01, Volume 24, Issue 3, Pages 203-206
Gestational diabetes
Pregnancy is a state of increased insulin resistance. Women with additional risk factors for insulin resistance—such as a BMI above 30, Afro-Caribbean or South Asian ethnicity, a first-degree relative with diabetes, or a history of previous macrosomia—are at an increased risk of developing gestational diabetes. Unlike type 1 or type 2 diabetes, gestational diabetes is only present during pregnancy. However, there is a slightly increased risk of developing type 2 diabetes post-pregnancy.
Women with the aforementioned risk factors will undergo an oral glucose tolerance test between 24 and 28 weeks of gestation. A diagnosis is made if their glucose level is above 7.8 mmol/L. Post-pregnancy, a fasting glucose level test is performed for the mother between 6 and 13 weeks to check for the development of Type 2 diabetes.
The risks associated with gestational diabetes include foetal macrosomia (resulting in potential shoulder dystocia), increased likelihood of C-section and induction of labour, stillbirth, preterm labour, neonatal hypoglycaemia, and a slightly increased risk of the baby developing diabetes later in life. Due to these risks, mothers with gestational diabetes (as well as those with Type 1 or Type 2 diabetes during pregnancy, which pose even greater risks to the foetus) will have more frequent ultrasounds to monitor foetal size and amniotic fluid volume.
Treatment for gestational diabetes may involve diet and exercise. If these measures do not achieve target blood sugar levels, metformin or insulin may be used (with insulin reserved for uncontrolled blood sugars). Other medications are not licensed for this condition.
| NICE thresholds for diagnosis of GDM | |
|---|---|
| Fasting | >5.6 mmol/L |
| 2 hours post OGTT | >7.8 mmol/L |
References
- National Institute for Health and Care Excellence (NICE). Diabetes in pregnancy: management from preconception to the postnatal period. Nice.org.uk. 2015
- Durnwald, C. (2023) Gestational diabetes mellitus: Screening, diagnosis, and prevention, UpToDate. Edited by D.M. Nathan, E.F. Werner, and V.A. Barss. Available at: https://www.uptodate.com/contents/gestational-diabetes-mellitus-screening-diagnosis-and-prevention?search=gestational+diabetes&source=search_result&selectedTitle=2~150&usage_type=default&display_rank=2 (Accessed: 20 February 2024)
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

