


 Close
 18th March 2024
Anaphylaxis
Anaphylaxis is a rapid-onset, severe, systemic hypersensitivity reaction characterised by airway or circulatory compromise often accompanied by cutaneous features. Approximately 1 in 1333 of the UK population experience anaphylaxes during their lifetime.
Anaphylaxis can result from a number of triggers, but the three largest common groups include food, drugs and venom. The significance of these varies from childhood to adulthood; food is particularly important in the paediatric population. Within food, nuts are the most common culprit but other significant groups include legumes and shellfish. Various classes of drugs are well-known to be associated with increased risk of anaphylaxis and these include antibiotics (notably penicillins and cephalosporins) and anaesthetic agents. Drug-induced anaphylaxis is associated with more rapid and severe reactions with higher mortality, especially when the medication is administered intravenously.
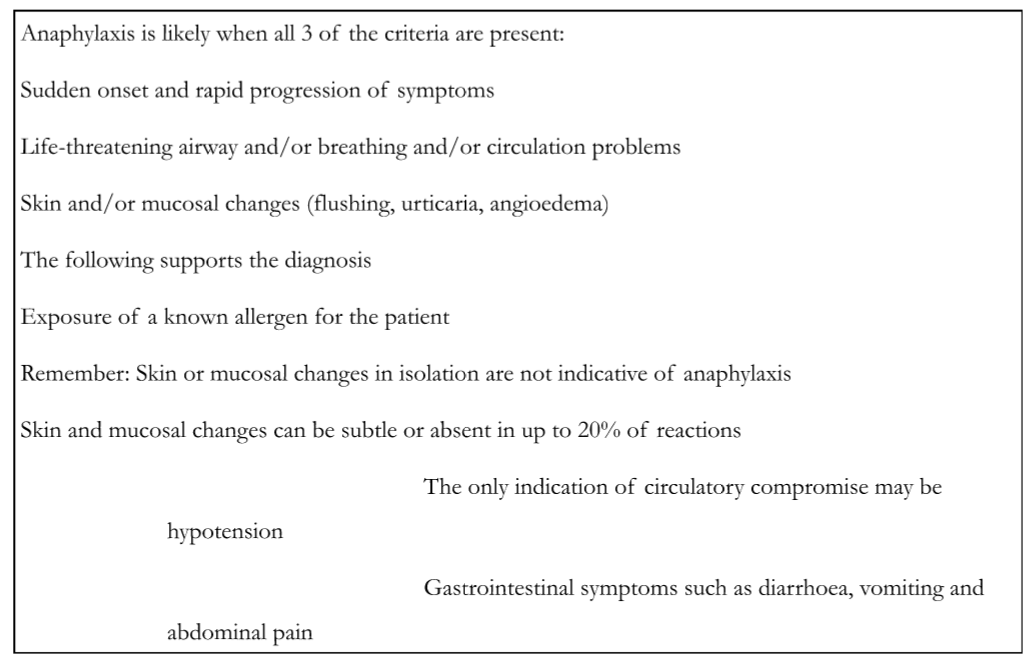
Adapted from: https://www.bsaci.org/wpcontent/uploads/2020/01/Emergencytreatmentofanaphylacticreactions2008.pdf
Pathophysiology of anaphylaxis
Symptoms of anaphylaxis are mediated by extensive release of histamine from mast cells and basophils. Degranulation of these cells is triggered by cross-linking of antigen-specific IgE binding to high affinity receptors expressed on the surface of the mast cells and basophils. Histamine released causes systemic symptoms, including vasodilation, tissue oedema and bronchoconstriction, resulting in hypotension, intravascular volume depletion and airway constriction. The cumulation of these features causes hypoxia, hypotension and shock with loss of organ perfusion.
It is important to note that a significant proportion of reactions result from mast cell and basophil activation independent from IgE; these reactions are termed anaphylactoid. Common causes include non-steroidal anti-inflammatories and contrast media. Vancomycin is a well-known cause of anaphylactoid reaction and is sometimes termed “Red Man Syndrome”. Presentation of anaphylactoid reactions and, therefore, their management is identical to that of anaphylaxis.
Treatment of anaphylaxis
Prompt recognition of symptoms is essential. Removal of the trigger is especially important, particularly in the context of medications, for example, disconnecting intravenous medications. Adrenaline and fluid replacement are central to the management of anaphylaxis. Acute management is defined by the emergency treatment of anaphylaxis guidelines produced by the UK Resuscitation Council. This was updated in 2021 and significant changes to previous guidance include:
- Emphasis on prompt administration of IM adrenaline with dose repeated at 5 minutes if symptoms persist
- Advice to avoid sudden postural changes and maintain a supine position
- Treatment of refractory anaphylaxis and early involvement of definitive airway support if appropriate
- Corticosteroids are no longer recommended in the management of emergency anaphylaxis
- Antihistamines are considered third-line agents and do not form part of the initial management
- Guidance relating to monitoring of patients following stabilisation and safe discharge
- Consideration of fast-track discharge following a two hour observation period may be appropriate in the context of: a good response to a single dose of adrenaline with complete resolution of symptoms in a patient in possession of unused auto-injectors, trained in their use with adequate supervision following discharge
Drug Induced Anaphylaxis (DIA)
Incidence of DIA is increasing with development of new medications and increased awareness and reporting of cases. As discussed above, medications are common causes of anaphylaxis and are associated with higher mortality than reactions caused by venom or food; drug-induced cases represent up to 58% of fatal anaphylaxis. Non-steroidal anti-inflammatory drugs are the most common culprits of DIA followed by beta-lactam antibiotics, particularly amoxicillin. Modern radiocontrast media is less frequently associated with DIA due to non-ionic, low osmolar agents. Proton pump inhibitors are increasingly frequently linked to DIA, most commonly lansoprazole. Additionally, it is important to recognise the risk of topical agents including chlorhexidine and latex. Excipients in vaccines such as egg lecithin and recently polyethylene glycols in COVID vaccines, as well as a variety of medications including proton pump inhibitors and laxatives, have been identified as anaphylaxis culprits.
Risk factors for increased severity of reactions include increasing age and intravenous administration. Co-factors are also known to influence DIA risks, such as co-morbidities (including asthma), alcohol, menstruation and psychological stress.
Immunologic anaphylaxis can result from both IgE dependent and IgE independent pathways. Certain drugs are more commonly associated with one pathway rather than the other (such as penicillin associated with IgE) and some, such as contrast media, can be associated with both. IgE dependent anaphylaxis requires sensitisation during which T helper cells are activated (in this case by the medication) and induce IgE production specific to the antigen. The IgE independent pathway is orchestrated by IgG or complement; the mechanism is not yet fully described in humans. Finally, as described above, an anaphylaxis reaction can result from direct activation of mast cells and basophils. The sensitisation process is not required in anaphylactoid reactions.
Latex-fruit syndrome
There is a significant crossover observed between allergic reactions to certain foods and latex. Up to 40% of patients with latex allergy demonstrate reactions to one or more fruits including strawberry, kiwi, banana and tomato. This is hypothesised to be due to structurally similar proteins on the surface of latex and specific foods. Although the term “latex fruit syndrome” is used, the phenomenon is not limited to fruit and is observed with a variety of vegetables, too. This syndrome demonstrates the importance of a careful allergy history as well as an awareness of cross-sensitivity.
Investigations for DIA
As in all allergic diseases, a careful and chronological history is essential. The temporal relationship between drug administration and symptoms is important, as in true anaphylaxis, the reaction is rapid (within minutes). In the acute setting, serial serum mast cell tryptase measurements may be useful to confirm mast cell activation and anaphylaxis. Levels may not rise until 30 minutes after the onset of symptoms and peak at 1-2 hours. Tryptase has a short half-life and timing of measurements must be carefully documented as levels may have normalised within 6 hours. It is important to remember that a normal tryptase level does not exclude anaphylaxis.
Despite thorough history-taking, identification of the causative medication can be difficult and, particularly in the case of polypharmacy, further investigations may be helpful. Skin prick testing (SPT) may be less informative than in the investigation of food and venom-induced anaphylaxis and is poorly validated except in specific examples. Intradermal testing can be used in the context of negative SPT using increasing concentrations of diluted medication and observing for symptoms. Similarly, specific IgE testing in the context of medications can be of limited use; therefore, often, direct oral challenge is required. While sometimes it is feasible to avoid certain medications for some patients, there are examples when it is important to definitively prove or disprove hypersensitivity. Examples of this may include concerns of antibiotic-induced anaphylaxis in patients requiring long-term or prophylactic antibiotics such as bronchiectasis or in patients requiring procedures under general anaesthetic.
References
- Resuscitation Council UK. Emergency treatment of anaphylaxis: guidelines for healthcare providers. May 2021 https://www.resus.org.uk/sites/default/files/202105/Emergency%20Treatment%20of%20Anaphylaxis%20May%202021_0.pdf
- Montañez MI, Mayorga C, Bogas G et al. Epidemiology, mechanisms, and diagnosis of drug-induced anaphylaxis. Front Immunol 2017;8:614
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

