


 Close
 30th August 2024
Drug Side Effects
Main classes of drugs and their adverse effects
An adverse drug reaction is a harmful, unintended consequence of taking medication. Drug reactions are classified into five groups which are summarised in the table below.
| Type | Description | Example |
|---|---|---|
| A | Dose-dependent and predictable reactions based on the pharmacological action of the drug. | Hypoglycaemia from insulin |
| B | Idiosyncratic, unpredictable reactions not related to the pharmacological action of the drug. | Anaphylaxis from penicillin |
| C | Reactions associated with long-term use of a drug and involve a cumulative dose. | Osteoporosis from corticosteroids |
| D | Delayed reactions that become apparent sometime after use of the drug. | Carcinogenesis from chemotherapy |
| E | Withdrawal reactions that occur when a drug is stopped abruptly. | Rebound hypertension from clonidine |
Anticoagulants
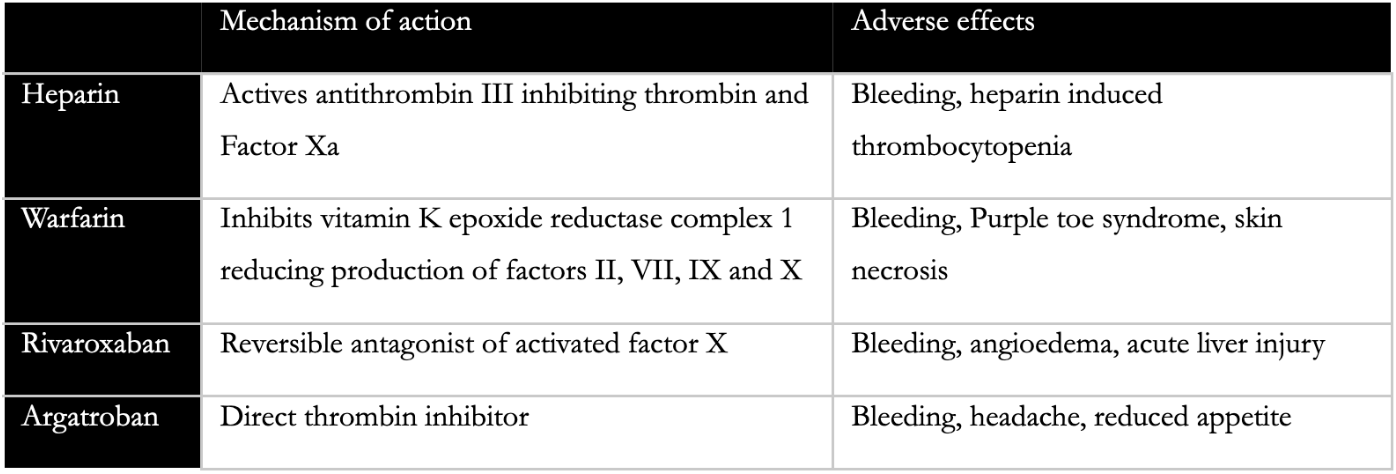
Anticoagulants are used for the prevention or treatment of thromboembolic events. The different types of anticoagulants are low molecular weight heparins, vitamin K antagonists (e.g., warfarin), direct oral anticoagulants (e.g., rivaroxaban), and direct thrombin inhibitors (e.g., argatroban). Their mechanisms of action are depicted in the image below.
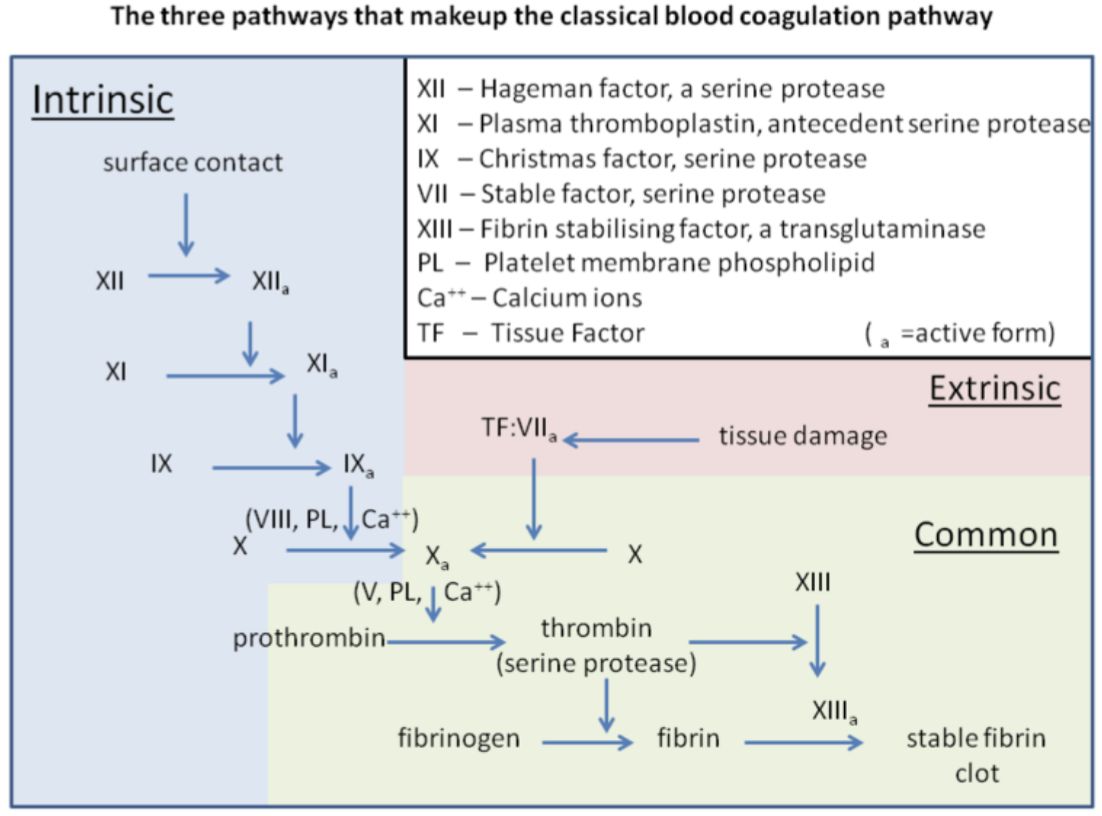
Image Source: mage Source: Wikimedia Commons (2012). Classical blood coagulation, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Classical_blood_coagulation_pathway.png (Accessed 29 August 2024)
Heparin induced thrombocytopaenia
Heparin-induced thrombocytopenia (HIT) is classified into two types: HIT type 1 and HIT type 2. HIT type 1 is a non-immune condition where heparin directly causes platelet aggregation and is less severe than HIT type 2.
HIT type 1 occurs in about 10% of patients within 72 hours of starting heparin treatment. It involves a modest drop in platelet count, rarely below 100 (normal 150-400 *109/L) and is not linked to an increased risk of thrombosis. Symptoms improve once heparin is discontinued.
HIT type 2 is an immune-mediated reaction occurring within 10 days of starting heparin. Platelet factor 4 (PF4) forms immune complexes with heparin, accumulating on platelets and activating them. This triggers the release of more PF4, creating a positive feedback loop. Procoagulant microparticles are then released, leading to excessive thrombin formation, consumptive thrombocytopenia, and a high risk of thrombosis. These characteristics make HIT type 2 a significant clinical concern.
Opioids
Opioids, including natural opiates like morphine and synthetic analogues such as oxycodone, act on opioid receptors in the central nervous system to provide rapid relief for acute severe pain or chronic pain in palliative care. They can cause respiratory depression, nausea, vomiting, pinpoint pupils, constipation, and itching. Prolonged use can lead to physical dependence, necessitating careful management to avoid withdrawal symptoms like sweating, tremors, anxiety, and cravings. Oxycodone is contraindicated in patients with acute hepatic failure.
Immunosuppressants
Immunosuppressant medications are essential for treating chronic inflammatory diseases, autoimmune disorders, and preventing organ rejection post-transplantation. Examples include azathioprine and mercaptopurine, ciclosporin, methotrexate, mycophenolate and tacrolimus. However, their use increases susceptibility to infections by suppressing the innate, cellular and humoral immune response.
Azathioprine
Azathioprine is converted to its active form, 6-mercaptopurine, which disrupts nucleic acid production as a purine analogue. Adverse effects include bone marrow suppression, nausea, vomiting, and pancreatitis. Testing for thiopurine methyltransferase (TPMT) activity before treatment is recommended, as individuals with low enzyme activity are at greater risk of developing myelosuppression from thiopurine therapy.
Ciclosporin
Ciclosporin, an immunosuppressive drug, works by inhibiting T-cell activation. A key step in this process is the influx of calcium into T-cells, which activates the enzyme calcineurin. Calcineurin then dephosphorylates transcription factors like NF-AT, which triggers the production of interleukin-2 (IL-2) and other cytokines that regulate T-helper cells and inflammation. Ciclosporin binds to cyclophilin, forming a complex that blocks calcineurin activity. This inhibition reduces IL-2 synthesis, thereby suppressing the immune response.
Ciclosporin use is associated with numerous side effects, including gingival hyperplasia, hirsutism, convulsions, hypertension, immunosuppression, gastrointestinal disturbances, liver and kidney problems, hyperkalaemia and peripheral neuropathy. Of particular concern is the increased risk of skin cancers due to its immunosuppressive effects.
Methotrexate
Methotrexate, classified as an antimetabolite, acts distinctly in neoplastic and inflammatory conditions. In neoplasms, it functions as a potent inhibitor of dihydrofolate reductase, crucial for converting dihydrofolate to tetrahydrofolate—a cofactor essential for nucleotide synthesis. This inhibition halts DNA and RNA synthesis, effectively suppressing the proliferation of cancer cells.
In inflammatory disorders, it inhibits DNA and RNA synthesis, suppresses immunoglobulins crucial for immune responses, reduces B lymphocytes, and dampens cytokine production. These mechanisms collectively modulate inflammation.
Methotrexate therapy carries a range of potential adverse effects, such as macrocytic anaemia from folate deficiency, immunosuppression, mucositis, leukopenia, gastrointestinal disturbances, and possible impacts on renal and hepatic function. Additionally, it is teratogenic, increasing the risk of birth defects and additional neoplasms. Pulmonary fibrosis is also a significant concern associated with its use.
Mycophenolate
Mycophenolic acid, also known as mycophenolate, is a compound of fungal origin that exerts its pharmacological effects as a prodrug. Central to its mechanism of action is the inhibition of inosine monophosphate dehydrogenase (IMPDH), an enzyme critical to the de novo synthesis of purines. Given that purines can be acquired through two distinct pathways – de novo synthesis and the salvage pathway – and that leukocytes predominantly rely on de novo synthesis for their purine requisites, the inhibition of IMPDH by mycophenolic acid effectively impairs purine biosynthesis, resulting in the downregulation of inflammatory cells, particularly T and B lymphocytes, through the inhibition of DNA synthesis.
Despite its therapeutic benefits, the use of mycophenolic acid requires careful monitoring due to potential adverse effects. Common side effects include gastrointestinal disturbances, nausea, anaemia, agranulocytosis, metabolic acidosis and immunosuppression, which has led to the association with progressive multifocal leukoencephalopathy.
Tacrolimus
Tacrolimus is a potent immunosuppressant that targets T-cells by interacting with the protein FKBP12 to form a complex that blocks calcineurin activity. This blockade prevents T-cell activation and interleukin-2 (IL-2) Tacrolimus is a crucial immunosuppressant in post-transplant care. It presents with a spectrum of potential adverse effects across various physiological systems. Cardiovascular effects, notably hypertension and arrhythmias, are critical concerns post-transplant. Central nervous system impacts such as headaches and tremors can significantly affect daily functioning. Dermatologically, tacrolimus may induce acne and pruritus. Endocrine and metabolic effects include the development of new-onset diabetes mellitus after transplantation (NODAT) and electrolyte imbalances like hyperkalaemia and hypomagnesemia, necessitating meticulous management. Gastrointestinal side effects such as nausea and diarrhoea can lead to dehydration and exacerbate electrolyte disturbances if not properly controlled. Tacrolimus also heightens susceptibility to infections, including urinary tract infections and opportunistic infections, requiring vigilant monitoring. Renal function is particularly vulnerable to tacrolimus-associated nephrotoxicity, necessitating continuous assessment and careful dosage adjustment.
Corticosteroids
Corticosteroids exert their therapeutic effects by activating cytoplasmic receptors, which then translocate to the nucleus to modify transcription. This process leads to the downregulation of pro-inflammatory molecules and the upregulation of anti-inflammatory proteins. One notable complication is oral candidiasis, resulting from immunosuppression that predisposes the oral mucosa to fungal colonisation. Prolonged corticosteroid use can also suppress the Hypothalamic-Pituitary-Adrenal (HPA) axis, reducing endogenous cortisol production and requiring careful tapering to avoid adrenal crisis.
Long-term use may also compromise skeletal integrity, increasing the risk of osteoporosis and avascular necrosis. The pathogenesis involves decreased bone formation and enhanced resorption, with avascular necrosis particularly affecting the femoral head. Metabolic derangements, such as glucose intolerance, heighten the risk of iatrogenic diabetes mellitus. Psychiatric manifestations, ranging from mood alterations to psychosis, necessitate thorough psychiatric assessment in predisposed individuals. Gastrointestinal complications, notably peptic ulceration, are exacerbated by concurrent NSAID use. Additionally, the immunosuppressive effects increase susceptibility to fungal, mycobacterial, and viral infections.
Statins
Statins play a pivotal role in atherosclerosis management by inhibiting the 3-hydroxy-3-methyl-glutaryl coenzyme A (HMG CoA) reductase enzyme, crucial in cholesterol biosynthesis. This inhibition leads to reduced hepatic cholesterol production and increased clearance of low-density lipoprotein (LDL) cholesterol from the blood. While effective in lowering cardiovascular risk, statins are associated with adverse effects such as myopathy and the more severe rhabdomyolysis, characterised by significant muscle damage and potential renal impairment. Other common side effects include headaches and gastrointestinal disturbances, including dyspepsia and diarrhoea. Despite these potential drawbacks, the benefits of statins in cardiovascular disease prevention are significant, necessitating careful monitoring and management of these adverse effects to ensure continued patient compliance and therapeutic efficacy.
References
- British National Formulary. Heparin (unfractionated). In: BNF [Internet]. London: BMJ Group and Pharmaceutical Press; [cited 2024 May 15]. Available from: https://bnf.nice.org.uk/drugs/heparin-unfractionated/#side-effects
- British National Formulary. Warfarin sodium. In: BNF [Internet]. London: BMJ Group and Pharmaceutical Press; [cited 2024 May 15]. Available from: https://bnf.nice.org.uk/drugs/warfarin-sodium/#side-effects
- British National Formulary. Rivaroxaban. In: BNF [Internet]. London: BMJ Group and Pharmaceutical Press; [cited 2024 May 15]. Available from: https://bnf.nice.org.uk/drugs/rivaroxaban/#side-effects
- British National Formulary. Argatroban monohydrate. In: BNF [Internet]. London: BMJ Group and Pharmaceutical Press; [cited 2024 May 15]. Available from: https://bnf.nice.org.uk/drugs/argatroban-monohydrate/#side-effects
- Thomson AW, Bonham CA, Zeevi A. Mode of action of tacrolimus (FK506): molecular and cellular mechanisms. Ther Drug Monit. 1995 Dec;17(6):584-91. doi: 10.1097/00007691-199512000-00007. PMID: 8588225
- Sharma H, Wadhwa R. Mercaptopurine. [Updated 2023 May 22]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2024 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK557620
- Allison AC. Mechanisms of action of mycophenolate mofetil. Lupus. 2005;14 Suppl 1:s2-8. doi: 10.1191/0961203305lu2109oa. PMID: 15803924
- Cronstein, B.N., Aune, T.M. Methotrexate and its mechanisms of action in inflammatory arthritis. Nat Rev Rheumatol 16, 145–154 (2020). https://doi.org/10.1038/s41584-020-0373-9
- Hitchings A, Lonsdale D, Burrage D, Baker E. The top 100 drugs. Clinical pharmacology and practical prescribing. Churchill Livingstone Elsevier 2015
Cytochrome P450
Cytochrome p450 enzymes are found in the hepatocytes and they play an important role in drug metabolism. These enzymes are particularly involved in phase I reactions such as oxidation, reduction, and hydrolysis of ingested medications. Certain drugs are known as cytochrome p450 ‘inducers’ and inhibitors. Inducers increase the amount of the enzyme and speed up the oxidation or clearance of a drug. Inhibitors reduce the activity of the enzyme thereby increasing the plasma concentration of the drug being metabolised. This may lead to adverse effects.
| Inhibitors | Inducers |
|---|---|
| SSRIs: fluoxetine, sertraline
Anti-fungals: ketoconazole, fluconazole Isoniazid Cimetidine Omeprazole Sodium valproate Acute alcohol intake Antibiotics: ciprofloxacin, erythromycin |
St John’s Wort
Chronic alcohol intake Phenytoin Carbamazepine Rifampicin Smoking Grapefruit juice |
| Enzyme | Prevalence | Substrates | Inducers | Inhibitors | Role |
|---|---|---|---|---|---|
| CYP3A4 | Most abundant in liver and intestines | Statins, calcium channel blockers, benzodiazepines, immunosuppressants | Rifampicin, St. John’s wort, phenytoin | Grapefruit juice, diltiazem, macrolides, ketoconazole, ritonavir | Drug metabolism and detoxification |
| CYP2C9 | Significant portion in liver | Warfarin, phenytoin, NSAIDs | Rifampicin, barbiturates | Amiodarone, fluoxetine, fluconazole | Metabolism of therapeutic agents and endogenous compounds |
| CYP2D6 | Smaller percentage of hepatic CYPs, metabolises ~25% of all meds | Antidepressants, antipsychotics, beta-blockers, opioids | – | Quinidine, paroxetine | Personalised medicine, genetic variability |
| CYP1A2 | Predominantly in liver | Caffeine, theophylline, some antipsychotics | Polycyclic aromatic hydrocarbons, cruciferous vegetables | – | Metabolism of xenobiotics and endogenous substrates |
| CYP2E1 | Liver and other tissues | Ethanol, acetaminophen (toxic metabolite), some anaesthetics | Ethanol, isoniazid | Disulfiram | Metabolism of drugs and environmental toxins, oxidative stress, liver injury |
Reference
Gilani B, Cassagnol M. Biochemistry, Cytochrome P450. [Updated 2023 Apr 24]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2024 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK557698/
Acetylator status
Acetylation is a type of phase II reaction of drug metabolism, and it involves adding an acetyl group to a drug. This is known as conjugation, and it helps to inactivate and excrete the products. The transfer of acetyl groups is catalysed by an enzyme N-acetyltransferase which the patient may be deficient in. Acetylator status affects the following medications:
- Sulfasalazine
- Procainamide
- Dapsone
- Isoniazid
- Hydralazine
This means that if a patient is a ‘slow acetylator’, they are at a higher risk of developing toxicity when given any of the above drugs.
Reference
- Pande JN, Pande A, Singh SP. Acetylator status, drug metabolism and disease. Natl Med J India. 2003 Jan-Feb;16(1):24-6. PMID: 12715953
QTc prolongation
The QT interval is a measurement on an electrocardiogram that represents the time it takes for the heart’s ventricles to depolarise and then repolarise. A corrected QT interval (QTc) is often used to account for variations in heart rate. QTc is calculated using formulas like Bazett’s formula to provide a standardised measurement.
Prolongation of the QT interval on the ECG reflects delayed ventricular repolarisation. Normal QTc reference ranges are < 440ms for men and <460 for women. A potentially dangerous condition called Torsades de Pointes, which can lead to sudden cardiac arrest. Many factors can cause QTc prolongation, as summarised in the table below.
| Category | Causes |
|---|---|
| Medications | Antiarrhythmics (e.g., sotalol), antibiotics (e.g., erythromycin), antipsychotics (e.g., haloperidol), antidepressants (e.g., citalopram) |
| Electrolyte Imbalances | Hypokalaemia, hypomagnesemia, hypocalcaemia |
| Medical Conditions | Heart failure, bradycardia, myocardial infarction |
| Genetic Factors | Congenital long QT syndrome (LQTS) |
| Others | Starvation, severe diarrhoea, certain toxins |
References
- Acquired long QT syndrome: Definitions, pathophysiology, and causes. UpToDate. Available from: https://www.uptodate.com/contents/acquired-long-qt-syndrome-definitions-pathophysiology-and-causes. Accessed 26 Jun 2024
Glucose 6 Phosphate Dehydrogenase (G6PD) deficiency
G6PD is an X-linked recessive disorder that clinically encompasses a spectrum of haemolytic syndromes. Patients can have a normal life span and be asymptomatic however they may have episodic anaemia or haemolytic crises. Fava beans, infections and medications can precipitate a crisis.
Drugs which may cause haemolysis include sulphonamides, sulfasalazine, sulfonylureas, ciprofloxacin and primaquine.
Reference
- Glader B. Genetics and pathophysiology of glucose-6-phosphate dehydrogenase (G6PD) deficiency. Means R, Raby B, editors. 2024
Hypersensitivity
Hypersensitivity reactions are inadequate or exaggerated immune mediated responses to an allergen or antigen. These can be divided to five types:
- Type I reactions occur when an antigen reacts with immunoglobulin E (IgE) bound to mast cells, as seen in anaphylactic reactions. Conditions such as asthma, eczema, and urticaria are also classified as Type I reactions.
- Type II reactions involve immunoglobulin G (IgG) or immunoglobulin M (IgM) binding to antigens. Diseases such as pernicious anaemia and Goodpasture’s syndrome fall under this category.
- Type III reactions are immune complex mediated. These reactions can cause systemic lupus erythematosus and allergic alveolitis.
- Type IV reactions are delayed hypersensitivity reactions mediated by T cells. Examples include Guillain-Barré syndrome, multiple sclerosis, and graft-versus-host disease.
- Type V has been a recently recognised reaction in which auto antibodies bind to the cell surface receptors in e.g. myasthenia gravis.
Reference
Descotes J, Choquet-Kastylevsky G. Gell and Coombs’s classification: is it still valid? Toxicology. 2001 Feb 2;158(1-2):43-9. doi: 10.1016/s0300-483x(00)00400-5. PMID: 11164991
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

