


 Close
 5th April 2024
Electrolyte Imbalance
Disorders of Sodium
Sodium ions are the major cation in extracellular fluid and contribute a large part to its osmotic pressure. Normal serum sodium concentration is between 135-145 mmol/L. Loss of water from the extracellular space results in increased sodium concentration, a cause of hypernatraemia, defined by serum sodium exceeding 145 mmol/L. Hyponatraemia is defined by serum sodium concentration less than 135 mmol/L.
Hyponatraemia
Causes of hyponatraemia can be divided based on fluid status:
- Hypovolaemic hyponatraemia due to renal and extra renal losses
- Euvolaemic hyponatraemia includes SIADH; hypothyroidism, glucocorticoid deficiency, primary polydipsia and drugs including antipsychotics and thiazide like diuretics.
- Hypervolaemic hypernatraemia occurs with congestive cardiac failure; cirrhosis, nephrotic syndrome, acute and chronic kidney disease.
Psuedohyponatraemia may occur in hypertriglyceridaemia or hyperproteinemia, giving a falsely low sodium when the actual serum sodium concentration is normal.
Clinical manifestations
Signs and symptoms of sodium imbalance will depend on the severity and speed of onset. Mild hyponatremia can be asymptomatic but nausea, confusion and headaches may manifest with moderate sodium increases. Severe hyponatremia causes vomiting, seizures, sleep abnormalities and coma.
Investigations
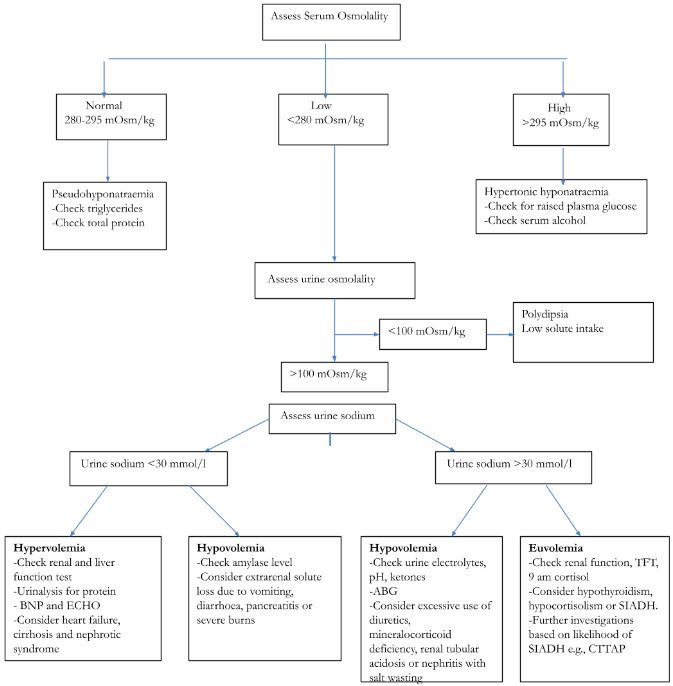
Initial investigations include renal function tests; serum and urine osmolality, urine sodium and thyroid function tests (TFT). The investigation algorithm and different causes of hyponatraemia are shown in the image below.
Syndrome of inappropriate antidiuretic hormone
Syndrome of inappropriate antidiuretic hormone (SIADH) secretion causes hyponatraemia, characterised by low plasma osmolality with inappropriate urinary response. Diagnosis requires elevated urine sodium, euvolemic fluid status and for other causes of euvolemic hyponatremia to be excluded. Causes of SIADH can be divided into:
- Neurological: stroke, trauma, epilepsy and haemorrhage
- Respiratory: COPD, sarcoidosis, asthma and acute respiratory failure
- Medications: carbamazepine, phenytoin, risperidone, quetiapine, duloxetine, gabapentin
- Malignancy: lung cancer, genitourinary and gastrointestinal cancers
Algorithm for investigations in hyponatraemia
Management
Management depends on the cause, and where hyponatremia is due to congestive cardiac failure with a hypervolemic fluid status, fluid restriction and diuretics are used.
Hyponatraemia secondary to gastrointestinal losses will require fluid replacement with 0.9% sodium chloride.
In SIADH related hyponatremia, treating the cause; fluid restriction and medications such as tolvaptan and demeclocycline are used.
In severe symptomatic hyponatremia, emergency correction using 150 ml of 1.8% or 3% sodium chloride over 20 minutes is used, with frequent sodium monitoring. The aim is to increase sodium concentration by 4-6 mmol in 24 hours and once stable, correction is slowed, aiming to increase sodium by 10 mmol in 24 hours.
Osmotic demyelination syndrome
Correcting hyponatremia too quickly can cause rapid changes in osmolality and disrupt the blood brain barrier. This is toxic to and causes damage to the myelin sheath. Presentation includes progressive neurological deficits and weakness; behavioural changes, encephalopathy, quadriplegia and locked in syndrome.
Hypernatraemia
High plasma sodium > 145 mmol/L is usually the result of water depletion but can be caused by excess salt intake, diabetes insipidus and administration of hypertonic sodium. Low serum protein may result in falsely raised sodium levels. The cause can be determined by the timeline of events with accompanying serum and urine sodium testing. Hypernatraemia can be classified according to the patient’s fluid status:
- Hypovolemic hypernatraemia from excessive sweating and dehydration; vomiting, diarrhoea, diuretic use and kidney disease.
- Euvolemic hypernatraemia due to fever, diabetes insipidus and drugs including lithium.
- Hypervoleamic hypernatraemia causes include hyperaldosteronism, excess administration of hypertonic saline or sodium bicarbonate and rarely, from excess salt intake
- Low serum protein may result in falsely raised sodium
Clinical manifestations
Early symptoms include polydipsia, anorexia, nausea and weakness. Severe symptoms include confusion, myoclonic jerks and seizures.
Management
Acute hypernatraemia with onset over hours can be corrected rapidly using dextrose 5% and normal saline. The usual rate is 3-6ml/kg/hour with regular monitoring of serum sodium concentrations. Once serum sodium is below 145 mmol/L the infusion rate should be reduced to 1ml/kg/hour to restore sodium concentrations around 140 mmol/L.
In chronic hypernatraemia, present longer than 48 hours, 5% dextrose fluids are used with the aim to lower sodium concentrations by 10 mmol/L over a 24-hour period.
Diabetes insipidus
Diabetes insipidus (DI) is characterised by hypernatraemia, polydipsia, polyuria and inappropriately dilute urine. Cranial DI is due to a lack of production of arginine vasopressin (AVP), also known as antidiuretic hormone (ADH). Nephrogenic DI occurs from a lack of response to AVP. The hormone is secreted from the posterior pituitary and acts at the distal convoluted tubule and collecting ducts of the nephron to increase water reabsorption.
Causes of cranial DI include:
- Pituitary surgery
- Craniopharyngioma
- Traumatic brain injury
- Subarachnoid haemorrhage
- Wolfram syndrome
Risk factors for nephrogenic DI include:
- Lithium therapy
- Chronic kidney disease
- Chronic hypercalcaemia or hypokalemia
Initial investigations include serum and urine sodium testing, water deprivation test and MRI brain where cranial DI is suspected.
Water deprivation test
This is also called the desmopressin stimulation test (see table below) and can distinguish between psychogenic polydipsia, cranial and nephrogenic DI. Patients are advised to avoid fluids up to eight hours before the test, following which urine osmolality is measured.
In primary polydipsia, water deprivation alone causes urine osmolality to be high and desmopressin need not be given as the high urine osmolality rules out diabetes insipidus. Administration of desmopressin in primary polydipsia has little effect on urine osmolality.
Where the urine osmolality is low, synthetic desmopressin (DDAVP) is administered either 20 mcg intranasally or 2 ug intramuscularly and urine osmolality remeasured.
In cranial DI, where the patient lacks AVP, administration of desmopressin causes water reabsorption by the kidneys and an increase in urine osmolality. In nephrogenic DI, the urine osmolality will remain low before and after desmopressin administration as the kidneys are unable to respond to desmopressin.
| Post dehydration osmolality (mOsm/kg) | Post DDAVP osmolality (mOsm/kg) | ||
| Diagnosis | Serum | Urine | Urine |
| Cranial DI | >300 | < 300 | >400-600 |
| Nephrogenic DI | >300 | < 300 | <300 |
| Primary polydipsia | <295 | > 600 | > 600 |
The water deprivation test
Management for cranial DI includes administration of desmopressin. Nephrogenic DI is treated with dietary salt restriction, diuretics and adequate fluid intake.
References
Water deprivation test https://mft.nhs.uk/app/uploads/2023/03/Water-deprivation-test-Adults.pdf
Disorders of Potassium
Potassium is a predominantly (98%) intracellular cation in the body where the concentration is relatively higher (100-120 mmol/L) than blood concentration of 3.5-5.2 mmol/L. The serum potassium concentration relates to both the internal balance between intra and extracellular fluids and that determining total body potassium. This is maintained by the kidney under the control of aldosterone secreted by the zona glomerulosa of the adrenal glands.
The Na/K ATPase enzyme helps to regulate intracellular potassium using adenosine triphosphate (ATP) as energy. For every molecule of ATP the pump uses, three sodium ions are exported and two potassium ions are imported into the cell.
The majority of potassium (90%) is excreted in urine via the kidneys, while less than 10% is excreted through sweat and faeces.
Hypokalaemia
This is defined as serum potassium levels of less than 3.5 mmol/L and can be divided into:
- Mild 3.1 – 3.5 mmol/L
- Moderate 2.5 – 3.0 mmol/L
- Severe < 2.5 mmol/L
The various mechanisms causing hypokalemia include:
- Spurious hyperkalemia, where potassium is taken up by cells outside the body, e.g., white blood cells in leukaemia. This is likely to occur if there are delays in analysing the sample.
- Transcellular redistribution due to metabolic/respiratory alkalosis and in the presence of excess insulin levels
- Potassium depletion due to diuretic use, diarrhoea, laxative use/abuse and profuse sweating
- Medications including beta adrenoreceptor agonists such as salbutamol and in theophylline overdose.
- Hypomagnesaemia results in hypokalemia as reduced intracellular magnesium increases potassium secretion.
- Mineralocorticoid excess in primary hyperaldosteronism (Conn’s syndrome) and secondary hyperaldosteronism (renal artery stenosis).
- Bartter syndrome, where abnormal chloride ion transport in the loop of Henle results in sodium wasting, metabolic alkalosis and potassium depletion
- Gitelman’s syndrome is the most common cause of congenital hypokalemia characterised by a defect in the distal tubule Na+/Cl– co-transporter gene. The result is hypokalemia, hypomagnesemia, metabolic alkalosis and hypocalciuria. Both Bartter and Gitelman’s syndrome activate the renin-angiotensin aldosterone system.
- Vomiting causes loss of chloride ions, leading to high levels of aldosterone, which inhibits potassium reabsorption from the kidney tubules.
Clinical manifestations
Mild hypokalemia is usually asymptomatic, but where potassium levels reach below 3.0 mmol/L, symptoms include generalised weakness, fatigue, myalgia and constipation. Potassium levels <2.5 mmol/L result in more serious problems including:
- Muscle weakness and paralysis ascending from the lower limbs
- Respiratory failure where respiratory muscles are involved
- Ileus due to involvement of the gastrointestinal muscles
- Paraesthesia
- Tetany
- Polyuria and polydipsia
Investigations
Blood tests, including urea and electrolytes, serum bicarbonate, glucose and magnesium, provide useful information in hypokalemia investigations. If the patient is on digoxin, then levels should be taken at the appropriate time and a review of medications for other causative agents, such as loop/thiazide diuretics. Concurrent hyponatremia with hypokalemia is suggestive of thiazide diuretic use or marked volume depletion. Low magnesium should be corrected to allow recovery of serum potassium.
Patients with moderate to severe hypokalemia should have an ECG performed to determine whether cardiac function is affected and to detect digoxin toxicity. Ventricular arrhythmias, including torsades de pointes, ventricular tachycardia and ventricular fibrillation, can occur. ECG findings with potassium levels < 3.0mmol/L include:
- Flat T waves
- ST segment depression
- Presence of U waves
- Pseudo prolongation of QT interval due to flattened T waves merging into the u waves.
Other investigations include urine potassium, sodium and urine osmolality, which is necessary to interpret urinary potassium levels. Low urine potassium is suggestive of poor intake, gastrointestinal loss or a shift into the intracellular space. High urinary sodium indicates renal loss.
A low urinary sodium in combination with high urinary potassium indicates secondary hypoaldosteronism.
Additional tests may be indicated and directed toward finding the underlying cause of hypokalemia:
- Bone profile (calcium and phosphate)
- Arterial blood gas (to establish metabolic acidosis/alkalosis)
- Urinary calcium (in suspected Bartter’s syndrome)
- Serum renin, aldosterone and cortisol
- Low dose dexamethasone suppression test in suspected Cushing’s syndrome
- Pituitary MRI to further evaluate Cushing’s syndrome
- CT imaging of the adrenal glands
- Renal angiogram id renal artery stenosis is suspected
- Sweat chloride test in suspected cystic fibrosis
Management
This is almost always done by potassium replacement and the mode of administration and amount of supplementation depends on the severity of hypokalaemia. Any result should be compared with previous results and repeated urgently if inconsistent.
Oral replacement is appropriate for mild hypokalemia and consists of potassium replacement between 20-40 mmol 2-4 times a day for three days. Potassium rich foods include bananas, tomatoes, avocados, potatoes and apricots. One medium banana contains 12 mmol potassium, the equivalent of one effervescent tablet of sando-K®).
Where oral replacement is not possible, intravenous potassium is used and can be given via a peripheral cannula not exceeding a rate of 10 mmol/hour to avoid phlebitis and discomfort. Monitoring of serum potassium is essential and once ECG abnormalities have resolved the rate of replacement can be further slowed or switched to oral formulations.
In emergencies, higher replacement rates can be used but must be administered through a central line with continuous cardiac monitoring. The maximum replacement rate should be 0.5 mmol/kg/hour with the weight capped at 80 kg. For example, in an 80 kg adult, the maximum rate of replacement in an emergency via a central line would be 40 mmol/hour. Potassium chloride should never be bolused as it can result in fatal arrhythmias.
Hyperkalaemia
This is defined as serum potassium levels of greater than or equal to 5.5 mmol/L and can be divided into:
- Mild 5.5 – 5.9 mmol/L
- Moderate 6 – 6.4 mmol/L
- Severe > 6.5 mmol/L
There are various mechanisms leading to hyperkalemia, including haemolysis and release of intracellular potassium from red blood cells during difficult venepuncture, delay between venepuncture and long transit time to the laboratory and taking a blood sample from the limb receiving intravenous fluids with added potassium. Other causes of hyperkalemia include:
- Transcellular redistribution which occurs in acidosis, low insulin states, hypertonicity, rhabdomyolysis and in extreme, prolonged exercise.
- Potassium retention can occur with acute kidney injury or in advanced chronic kidney injury
- Medications including potassium sparing diuretics (spironolactone), ACE inhibitors, beta blockers, trimethoprim, heparin and digoxin at toxic levels
- Diabetic ketoacidosis: potassium shifts from the intracellular to the extracellular space due to a lack of insulin
- Addison’s disease results in decreased aldosterone levels. Normally, aldosterone promotes the excretion of potassium via the kidneys. Decreased aldosterone levels results in reduced renal excretion of potassium thus hyperkalaemia.
Clinical manifestations
Symptoms of hyperkalemia may be non-specific, including fatigue and weakness, but occasionally, a patient may complain of shortness of breath, palpitations, chest pain or present with muscular paralysis. Reflexes may be depressed or absent on physical examination.
Investigations
Any spurious results should be repeated, particularly if there has been a delay between venepuncture and transport to the laboratory. 24-hour urine volume and electrolytes can be a reliable check of kidney function. Capillary blood and plasma glucose can reveal hyperglycaemia.
If patients are on digoxin, blood digoxin levels should be taken alongside an arterial blood gas, looking for metabolic acidosis. Patients’ medications should be reviewed and those contributing to hyperkalaemia temporarily held.
The ECG in hyperkalaemia may show:
- Peaked T waves
- Prolongation of PR interval
- Widening of QRS
- Reduced amplitude or loss of P wave
- AV dissociation
- Sine wave pattern
- Asystole
In patients with heart disease who have an abnormal baseline ECG, bradycardia may be the only new abnormality on ECG.
Management
Initial management of a patient with hyperkalaemia requires an ABCDE approach. A 12 lead ECG should be performed looking for changes of hyperkalaemia and where serum potassium is > 6.0 mmol/L continuous monitoring of cardiac rhythm is required.
Empirical treatment is advised where hyperkalaemia is suspected. This includes intravenous calcium to reduce the risk of arrhythmias and to stabilise cardiac myocytes. Initially, 30ml of 10% calcium gluconate may be given or 10 ml of 10% calcium chloride given over 10 minutes.
Insulin with dextrose is administered to shift potassium into the intracellular space. Typically, 10 units of soluble insulin in 50ml of 50% dextrose is used. Alternatively, 125ml of 20% dextrose can be administered over 15 minutes. Nebulised salbutamol, a beta 2 receptor agonist, is also administered to shift potassium into the intracellular space.
To facilitate renal excretion of potassium, any reversible renal disease should be treated, for example, stopping nephrotoxic drugs that cause intrinsic renal failure. This includes aminoglycoside antibiotics and amphotericin B, drugs which cause dose-related acute tubular necrosis. Fludrocortisone may be effective for managing chronic hyperkalaemia due to hypoaldosteronism.
Gastrointestinal excretion is achieved by using potassium binders including calcium resonium, patiromer or sodium zirconium cyclosilicate.
Refractory hyperkalaemia requires extracorporeal removal either by dialysis or hemofiltration.
Once hyperkalemia is treated, prevention of recurrence is achieved by:
- Dietary potassium restriction
- Medication review of causative agents, i.e., changing spironolactone for a loop diuretic furosemide.
- Correcting acidosis with sodium bicarbonate supplements
- Potassium binding resins
- Dialysis
References
- Potassium management. BMJ Learning. Available at: https://new-learning.bmj.com/course/10047565
- Hypokalaemia. Patient information professional article. Available at: https://patient.info/doctor/hypokalaemia
Disorders of Magnesium
Magnesium is the second most abundant intracellular and fourth most extracellular cation in the human body, with normal plasma concentrations between 0.70 – 0.85 mmol/L. It is required for the following physiological functions:
- Enzyme processes involving ATP – to be biologically active, ATP must be bound to a magnesium ion
- Protein synthesis (including DNA and RNA) where magnesium is a cofactor
- Cardiac excitability – magnesium regulates ion transporters, including potassium and calcium channels
- Glucose metabolism – insulin secretion requires magnesium. Deficiency results in impaired insulin secretion
- Regulation of parathyroid hormone secretion
Magnesium is also involved in cellular proliferation and apoptosis; mitochondrial function, neuromuscular excitability, vasomotor tone and blood pressure regulation.
There is evidence for the efficacy of magnesium in pre-eclampsia, eclampsia, asthma and arrhythmia. Given its role in a wide range of physiological activity, changes in concentration can have a sweeping impact on many bodily functions.
The majority of magnesium (65%) is sequestered in bone with the remaining in soft tissue cells and about 1% in extracellular fluid. Sources of magnesium include whole grains, spinach, nuts, potatoes and legumes. The plasma concentration is a reflection of dietary magnesium intake and the ability of the gastrointestinal tract and kidneys to retain it.
Hypermagnesemia
This is defined as serum magnesium levels of greater than 1 mmol/L and is less common than hypomagnesaemia. In health, excess magnesium intake is excreted by the kidneys. Hypomagnesaemia is encountered in:
- End stage renal failure due to impaired excretion
- When taking medications containing magnesium (antacids, laxatives and enemas)
- Parenteral nutrition
- In pregnancy, if treated with intravenous magnesium for eclampsia or preeclampsia.
Causes of mild hypermagnesemia include hypercalcaemia, hypothyroidism, Addison’s disease, dialysis and lithium therapy.
Clinical manifestations
Features of hypermagnesaemia depend on approximate serum concentrations:
- 2.0 -3.5 mmol/L – nausea and vomiting, flushing and ECG changes
- 4.0 – 5.0 mmol/L – hypotension, absent deep tendon reflexes, drowsiness and slurred speech
- > 6.0 mmol/L – respiratory depression, coma and paralytic ileus
- > 8.0 mmol/L – cardiac arrest and complete heart block
Investigations
In addition to checking serum magnesium levels, calcium levels should be taken as often there is hypocalcaemia present.
Where hypermagnesemia is recurrent or unexplained thyroid function tests and early morning cortisol tests should be performed to investigate Addison’s disease.
ECG changes in hypermagnesemia include an increased PR interval, broad QRS complexes and Qt prolongation.
Management
The extent of hypermagnesaemia and presence of comorbidities such as renal failure determines whether treatment is required. A person with normal renal function and good urine output who has received intravenous magnesium for eclampsia will be able to correct the resultant hypermagnesaemia without further treatment. In contrast, a patient with significant renal impairment impacting renal excretion of magnesium, who received a magnesium containing enema, will be at risk of problematic hypermagnesaemia and require treatment.
For mild hypermagneseamia (2.0 – 4.0 mmol/L) or in asymptomatic patients the source of magnesium should be identified and removed; good urine output maintained and serum concentrations checked after 24 hours.
Treatment is indicated with senior support and intensive care team involvement where serum magnesium concentrations are > 4.0 mmol/L or if there are significant features of hypermagnesaemia:
- Calcium salts, such as 10 ml of 10% calcium gluconate, administered as a slow intravenous injection over five minutes, are used to antagonise the neuromuscular and cardiovascular side effects of magnesium. Administration may be repeated in arrhythmias.
- Continuous cardiac monitoring
- Regular monitoring of serum magnesium levels
Hypomagnesemia
This is defined as serum magnesium concentrations < 0.7 mmol/L and may be caused by malabsorption syndromes, including Coeliac and inflammatory bowel disease, chronic diarrhoea, short bowel syndrome and prolonged nasogastric suctioning. Other causes include:
- Protein calorie malnutrition – anorexia nervosa
- Parathyroid gland disorders – low magnesium suppresses PTH release and blunts the end organ response to PTH. The resulting hypocalcaemia is refractory to replacement until magnesium is replete.
- Chronic alcohol excess
- Diabetes where poor glycaemic control results in glucose-induced diuresis
- Medications – proton pump inhibitors, diuretics, digoxin, calcineurin inhibitors, theophylline, cisplatin and some aminoglycosides
- Renal disorders resulting in reduced resorption – renal tubular acidosis, post obstructive diuresis, acute tubular necrosis
- Refeeding syndrome
- Severe burns
- Acute pancreatitis
Clinical manifestations
Hypomagnesaemia is usually asymptomatic until levels reach < 0.5 mmol/L, and it is commonly associated with other metabolic abnormalities such as hypokalaemia, hypocalcaemia and metabolic acidosis. Cardiovascular manifestations of hypomagnesaemia include both ventricular and supraventricular dysrhythmias such as atrial fibrillation, premature atrial and ventricular complexes and ventricular tachycardia.
Neuromuscular features of low magnesium include:
- Tremor
- Weakness
- Paraesthesia
- Tetany
- Muscle fasciculations
- Seizures, confusion and coma
Investigations
As a small amount of total body magnesium is extracellular, serum magnesium may be normal in early mild deficiency and a more accurate picture can be obtained with ionised magnesium levels. The majority of extracellular magnesium is protein bound; therefore protein levels are important as protein loss can affect the reading.
Calcium, phosphate and potassium levels should be checked as hypomagnesaemia is associated with hypokalemia, hypocalcemia and hypophosphatemia. Due to the association with diabetes, glucose levels should be checked.
The ECG in hypomagnesaemia may include broad QRS complexes, Qt interval and PR prolongation.
To determine the cause of low magnesium, 24-hour urinary magnesium excretion is sometimes used, with high urinary levels indicating renal wasting. Fractional excretion of magnesium provides a ratio which is useful to determine if the cause is renal or extra-renal.
Management
The cause of low magnesium should be identified and any contributing medications stopped where possible. Oral replacement can be used for biochemical hypomagnesaemia in asymptomatic patients but severe deficiency requires intravenous replacement with magnesium sulphate. Local guidelines should be followed and the maximum infusion rate should not exceed 2 g/hour. Serum magnesium or 24-hour urinary magnesium excretion may be monitored to measure response to treatment.
References
- Magnesium metabolism and its disorders. PubMed. Available at: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC1855626/
- Magnesium disorders. Patient information professional article. Available at: https://patient.info/doctor/magnesium-disorders
Disorders of Phosphate
The normal serum phosphate level in adults is 0.8 – 1.5 mmol/L. As it is present in all living organisms, a normal diet contains plenty of phosphate. Serum phosphate exhibits a circadian rhythm with a peak around 03:00 and a nadir around 11:00.
It is absorbed in the intestinal tract and reabsorbed by renal tubular cells with its uptake increased by vitamin D.
Phosphate and calcium homeostasis in terms of bone content and renal excretion is regulated by parathyroid hormone, vitamin D, calcitonin and fibroblast growth factor 23.
Hypophosphatemia
The three main ways significant hypophosphatemia (< 0.4 mmol/L) may result include inadequate intake; renal losses or through redistribution into cells.
- Inadequate intake:
- Secondary to poor diet, eating disorders such as anorexia nervosa and alcohol dependency
- Malabsorption or recurrent vomiting
- Vitamin D deficiency
- Use of phosphate binders such as aluminium hydroxide
- Renal losses:
- Hyperparathyroidism – PTH reduces reabsorption at the proximal renal tubules
- Renal tubular disorders – Fanconi’s syndrome and Dent’s disease
- Vitamin D deficiency – including hypophosphatemic rickets
- Drugs – aminoglycoside, cisplatin and tenofovir cause renal phosphate leak
- Post renal transplantation – low phosphate is common, especially after a prolonged period of dialysis
- Paraproteinemias and heavy metal poisoning that impair renal tubule function
- Oncogenic osteomalacia
- Redistribution:
- Treating diabetic ketoacidosis – insulin drives phosphate into cells
- Refeeding syndrome
- Acute respiratory alkalosis
- Hungry bone syndrome post parathyroidectomy
- Lymphomas or leukaemia
Clinical manifestations
Many patients with mild (0.6 – 0.8 mmol/L) hypophosphatemia will report no specific symptoms. Common presentations include diaphragmatic, skeletal and cardiac muscle weakness, bone pain, altered mental status and rhabdomyolysis. Low phosphate states increase predisposition to haemolysis and thrombocytopenia.
Severe and acute hypophosphatemia ( < 0.3 mmol/L) may present with focal neurological deficits, myalgia, congestive cardiac failure, seizures and altered mental status.
If hypophosphatemia started from childhood, there may be short stature and bowed legs from rickets.
In an adult, marked hypophosphatemia with bone pain and excess urinary phosphate loss is suggestive of oncogenic osteomalacia.
Investigations
In addition to serum phosphate levels, calcium, magnesium and plasma protein should be taken. In the presence of low phosphate:
- Hypercalcaemia indicates hyperparathyroidism
- Hypocalcaemia suggest malabsorption, vitamin D deficiency or hungry bone syndrome
- Hypomagnesemia suggests dietary deficiency
- Paraproteinaemia should be suspected in severe hypophosphatemia with high globulins and suspicious features such as bone pain; hypercalcaemia, reduced renal function and anaemia.
Other investigations include:
- Renal function – renal tubular disease or extra renal causes can cause electrolyte abnormalities
- Liver function may show raised alkaline phosphatase due to osteomalacia in chronic hypophosphatemia
- PTH and vitamin D levels
- Arterial blood gas to check for respiratory alkalosis
- Plasma bicarbonate and urate, urine glucose and amino acids if considering Fanconi’s syndrome
- X Rays of affected joints – Looser zones suggest osteomalacia
- Bone scintigraphy can show increased uptake in multiple areas in severe osteomalacia
- Ultrasound neck or technetium 99mTc scan to identify enlarged parathyroid or ectopic glands
- Dual energy xray absorptiometry (DEXA) bone density scan as chronic hypophosphatemia will result in loss of bone density
Management
Treatment depends on the cause, severity and duration of low phosphate. Mild hypophosphatemia can be treated with oral phosphate replacement. Parenteral phosphate is usually indicated when levels reach < 0.3 mmol/L with close monitoring of phosphate, calcium and renal function as there is a risk of hypocalcaemia, over treatment resulting in hyperphosphatemia and hyperkalemia. Those with poor renal function are at increased risk from intravenous replacement.
Where low phosphate is secondary to Coeliac disease or Crohn’s, the underlying condition should be treated. Similarly, problems with alcohol dependency or eating disorders need appropriate input from specialist teams and in hyperparathyroidism, the causative tumour should be identified and removed. In oncogenic osteomalacia, phosphate supplements are useful until the tumour has been found and removed.
In vitamin D deficiency, oral vitamin D is usually sufficient but in severe renal disease where the kidneys are unable to convert hepatic hydroxyvitamin D3 to 1, 25 dihydroxy vitamin D3, active vitamin D should be given.
Hyperphosphatemia
The most common cause of hyperphosphatemia is renal failure as filtration of inorganic phosphate is significantly reduced when the glomerular filtration rate falls < 30 mL/min, increasing the serum phosphate concentration. Other causes include:
- Rhabdomyolysis
- Tumour lysis syndrome
- Excessive use of phosphate containing laxatives/enemas
- Vitamin D intoxication increasing intestinal phosphate absorption
- Hypoparathyroidism, acromegaly and thyrotoxicosis enhance renal phosphate reabsorption
- Tumoral calcinosis, which can be genetic or secondary, seen in patients undergoing renal dialysis
- Pseudohypoparathyroidism – characterised by resistance to PTH at its receptor and resultant hyperphosphatemia, hypocalcaemia and raised PTH levels.
Pseudohyperphosphatemia is a laboratory artefact due to interference in phosphate assay and is sometimes seen in patients with hyperglobulinemia, hyperlipidaemia and hyperbilirubinemia.
Clinical manifestations
The majority of patients with hyperphosphatemia are asymptomatic with the underlying pathology contributing to presenting symptoms.
Long term bone demineralization can result in bone fractures and raised phosphate levels may induce symptomatic hypocalcaemia resulting in:
- Tetany
- Muscle spasms
- Seizures
- Chvostek’s sign
- Trousseau’s phenomenon
Calcium-phosphate complexes deposited throughout the body lead to ectopic vascular calcification and atherosclerosis. This results in hypertension and eventually, left ventricular hypertrophy.
Investigations
Diagnosis is made by measuring serum phosphate concentrations. Renal function, serum calcium, PTH levels, thyroid function tests and vitamin D levels provide useful information. As haemodialysis removes phosphate, if the patient is on renal replacement therapy, the timing between the last dialysis sessions and sampling is important.
High calcium and phosphate levels with increased vitamin D levels indicates vitamin D intoxication.
Marked hyperphosphatemia with hyperkalemia; hyperuricemia and hypocalcaemia suggests tumour lysis syndrome.
In rhabdomyolysis, serum uric acid and creatinine kinase levels are elevated while in tumour lysis syndrome, there is markedly raised serum uric acid but normal or slightly elevated creatinine kinase.
Management
In normal renal function, intravenous saline can facilitate renal elimination of excess phosphate. Dietary phosphate restriction and phosphate binders are used to avoid high phosphate levels in chronic hyperphosphatemia. Examples of phosphate binders include Sevelamer, Lanthanum carbonate, calcium carbonate and calcium acetate.
Calcium based phosphate binders are most commonly prescribed as they also address hypocalcaemia which often accompanies hyperphosphataemia. However, the main concern is hypercalcaemia and accelerated vascular calcification, particularly when combined with vitamin D therapy. Non calcium based binders include Sevelamer and Lanthanum carbonate. A common side effect of phosphate binders is constipation.
Haemodialysis may be indicated in severe cases of hyperphosphatemia with symptomatic hypocalcemia and impaired renal function.
References
- Phosphate replacement. UpToDate. Available at: https://www.uptodate.com/contents/search?search=phosphate
- Hypophosphatemia. Patient information professional article. Available at: https://patient.info/doctor/hypokalaemia
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

