


 Close
 10th July 2023
Hair and Nail Disorders
Hair Disorders
Hypertrichosis and Hirsutism
Excessive hair growth can be androgen-independent (hypertrichosis) or androgen-dependent (hirsutism – excess hair growth in a male pattern that occurs in women).
| Causes of Hypertrichosis | Causes of Hirsutism |
|---|---|
| Hereditary: Congenital hypertrichosis lanuginosa Epidermolysis bullosa Hurler syndromeAcquired: Acquired hypertrichosis lanuginosa Thyroid disease Medication: diazoxide, minoxidil, ciclosporin, streptomycin Malnutrition Anorexia nervosaHereditary/Acquired: Porphyria, e.g. PCT |
Polycystic ovary syndrome
Ovarian tumours |
Table 7: Causes of hypertrichosis and hirsutism
Treatment options can include physical hair removal or medication such as the combined oral contraceptive pill (that contains anti-androgenic cyproterone acetate), spironolactone, finasteride and topical eflornithine.
Scarring alopecia
Scarring alopecia is hair loss with destruction of hair follicles. Causes include ichthyosis, tuberculosis, syphilis, burns, radiotherapy, kerion, lichen planus, discoid lupus, morphoea, sarcoidosis and cicatricial pemphigoid.
Non scarring alopecia
Non scarring alopecia is hair loss with preservation of hair follicles. Alopecia areata often presents as the classic ‘exclamation mark’ hair. It is often associated with nail dystrophy, cataracts, and other autoimmune diseases such as vitiligo, autoimmune thyroid disease, pernicious anaemia, and Addison’s disease. 50% of patients have hair growth within 1 year. First line treatment includes topical corticosteroids.
Other causes of non-scarring alopecia include male pattern (androgenic) alopecia, hypopituitary state, thyroid disease, hypoparathyroidism, pregnancy, iron deficiency anaemia, telogen effluvium, trichotillomania, and chronic illness. Medications that can lead to non-scarring alopecia include retinoids, anticoagulants, anti-mitotic agents, oral contraceptive pill, carbimazole, thiouracil and lithium.
Trichotillomania
Also known as a hair pulling disorder leading to alopecia. It affects 4% of the general population and is more commonly seen in females. It is associated with obsessive-compulsive disorder and is triggered by stress and anxiety. There have been studies that have identified a genetic linkage.
Nail Disorders
Nail changes associated with skin disorders
- Psoriasis: nail changes include onycholysis, nail pitting, subungual hyperkeratosis, pustule, and occasional loss of the nail.
- Fungal: fungal infection signs include thickening of the nail, onycholysis and discolouration. Treatment: oral terbinafine.
- Bacterial: usually secondary to staphylococcal infections. Pseudomonas infections give the nail a green/black discolouration and are often treated with oral ciprofloxacin.
- Lichen planus: nail changes occur in up to 10% of patients. Changes include thinning of the nail plate and longitudinal linear depressions/ ridging. Occasionally patients present with pterygium.
- Alopecia areata: pitting, thickening, and ridging of the nail – known as sandpaper nail
- Dermatitis: coarse pits, cross ridging and onycholysis may be seen
Nail changes associated with systemic disease
- Koilonychia: thin, brittle spoon shaped/concave nails. Associated with iron deficiency anaemia.
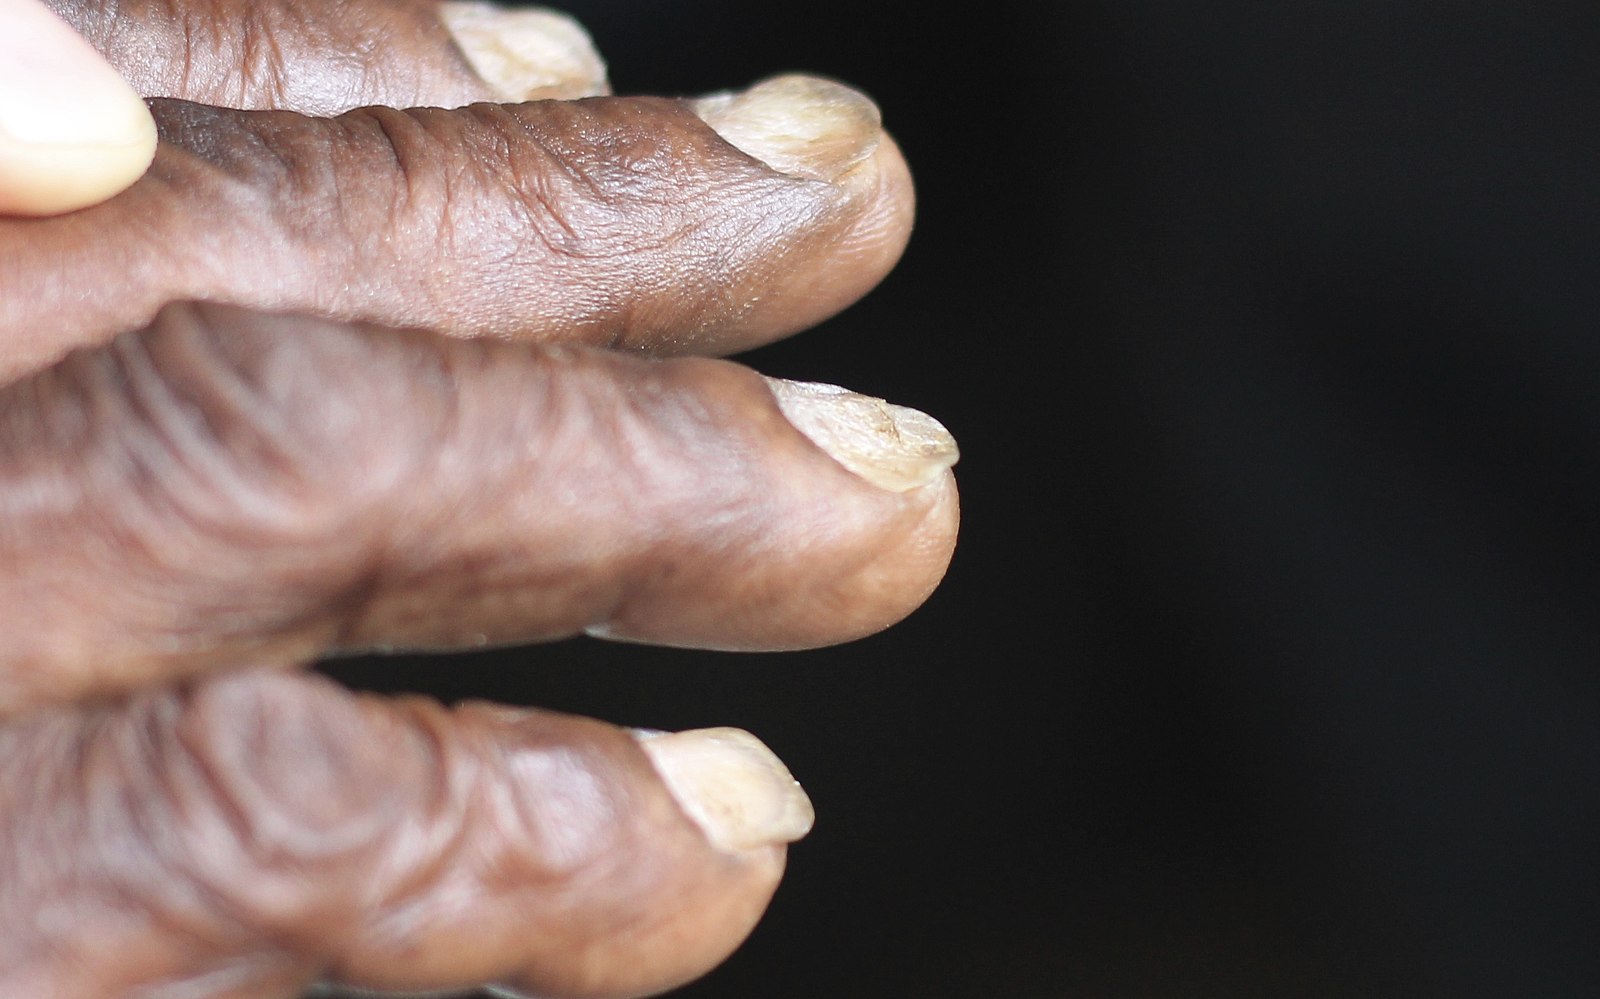
Koilonychia
Image Source: Wikimedia Commons (2018). Koilonychia iron deficiency anemia, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Koilonychia_iron_deficiency_anemia.jpg (Accessed on: 16 July 2022).

- Yellow nail syndrome: excessively curved, yellow nails. Often associated with recurrent pleural effusions, chronic bronchitis, bronchiectasis, congenital lymphedema, nephrotic syndrome, and hypothyroidism.
- Nail-patella syndrome: loss of the ulnar half of the nail, usually affecting the thumbnail. Associated with small patellae, bony spines over the posterior iliac crests, renal abnormalities, over extension of the joints and laxity of the skin.
- Beau’s lines: transverse depressions in the nail due to temporary arrest in growth. They usually occur after illness or infection.

Beau’s Lines
Image Source: Wikimedia Commons (2014). Beau’s line on left, middle fingernail, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Beau%27s_line_on_left,_middle_fingernail.jpg (Accessed on: 16 July 2022).

Onycholysis
Onycholysis is when the nail plate separates/lifts away from the underlying nail bed. Causes include dermatological (psoriasis, dermatitis), infective (fungal), vascular (Raynaud’s), metabolic (hypo/euthyroid), and traumatic (such as through regular manicures).
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

