


 Close
 17th February 2024
Nervous System
Central nervous system
Cerebrum
Clinical anatomy
The cerebral cortex consists of 2 hemispheres along with the diencephalon and basal ganglia centrally. The longitudinal cerebral fissure divides the cerebral hemisphere. The diencephalon and basal ganglia are located deep within the cerebral cortex. The diencephalon consists of the thalamus and hypothalamus. These structures sit superior to the tentorium cerebelli.
Each cerebral hemisphere can be divided into four separate lobes: Frontal, Parietal, Temporal and Occipital. The anterior-most portion of the cerebral hemisphere is the frontal lobe and is divided from the parietal lobe posteriorly by the central sulcus. The lateral sulcus divides the temporal lobe inferiorly and the parietal lobe superiorly. The occipital lobe is found posteriorly, with the parieto-occipital sulcus separating the two lobes.
The function of the lobes is as follows:
- Frontal lobe – Personality, higher executive functions, primitive reflexes, motor function (precentral gyrus), olfactory sensation.
- Parietal lobe – Language; sensation (Post-central gyrus); visuospatial awareness, visual pathway; ability for calculation, writing and learned movements.
- Temporal lobe – Visual pathways, auditory processing, memory formation.
- Occipital lobe – Visual processing
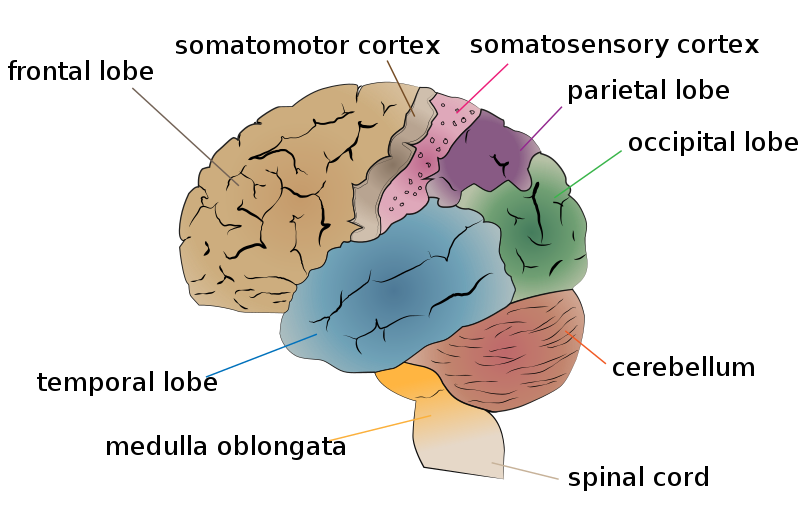
Image Source: Wikimedia Commons (2016). Cerebrum lobes, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Cerebrum_lobes.svg (Accessed: 9 January 2024).
Each lobe of the cerebral hemisphere will control the contralateral side of the body.
The basal ganglia is a subcortical structure that consists of several nuclei, including the caudate nucleus, lentiform nucleus, subthalamic nucleus and substantia nigra. While its function is complex, it is primarily a feedback circuit to help modulate and refine motor functions.

Image Source: Wikimedia Commons (2018). The structures of the basal ganglia, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:The_structures_of_the_basal_ganglia.png (Accessed: 9 January 2024).
The thalamus and hypothalamus have separate functions. The thalamus serves as a sensory processing centre as it receives input from the sensory organs and relays this information to relevant areas of the cerebral cortex. The hypothalamus controls many essential bodily functions, including hormonal release, thermoregulation, sleep regulation, appetite control and memory formation.
The pituitary gland is situated underneath the cerebrum and is suspended by the pituitary stalk. It sits within the sella turcica and is superiorly covered by the diaphragma sellae. The optic chiasm also runs superior to the pituitary gland. It is divided into two parts, the anterior pituitary and posterior pituitary, but both regions’ primary function is hormonal secretion.
Vasculature
The arterial supply to the brain mainly stems from the internal carotid artery and vertebral artery. The internal carotid has no extracranial branches and enters the skull via the carotid canal in the petrous part of the temporal bone. The carotid canals also contain the venous plexus and carotid sympathetic plexus. The internal carotid courses through the cavernous sinus in close proximity to CN III, IV, and VI within the carotid groove on the sphenoid body. It terminates as the anterior and middle cerebral arteries and forms the anterior circulation of the brain.
The posterior circulation of the brain originates from the vertebral artery, the first branch of the first part of the subclavian artery. Each vertebral artery will ascend through the transverse foramina of the cervical vertebrae and enter the cranium through the foramen magnum. The intracranial vertebral arteries unite to form the basilar artery. The basilar artery terminates at the Circle of Willis as it divides into the posterior cerebral artery.
Communicating arteries exist to allow anastomosis within the cerebral circulation. The anterior communicating artery connects the anterior cerebral arteries, while the posterior communicating artery connects the internal carotid artery to the posterior cerebral artery. The anterior, posterior and middle cerebral arteries, along with the anterior and posterior communicating arteries, complete the Circle of Willis.

Image Source: Wikimedia Commons (2013). 2123 Arteries of the Brain, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:2123_Arteries_of_the_Brain.jpg (Accessed: 9 June 2022).
The venous drainage of the brain begins through the cerebral veins, which carry deoxygenated blood into the dural venous sinuses. The draining cerebral veins pierce through the arachnoid and dura mater as bridging veins to empty their contents into the dural sinus. Arachnoid granulations/villi are outpouchings of the arachnoid mater that enter the dural sinus to allow drainage of CSF into the venous system.
There are 11 dural sinuses, with the main sinuses being the superior sagittal sinus, inferior sagittal sinus, straight sinus, transverse sinus, sigmoid sinus and cavernous sinus. The confluence of sinuses is the location where the transverse, superior sagittal, straight and occipital sinuses meet. Blood is drained from the confluence of sinuses through the transverse sinus and sigmoid sinus into the internal jugular vein.
The cavernous sinus contains several venous plexus within the body of the sphenoid. It is important as many intracranial structures pass through it, including the internal carotid artery, CNIII, CNIV, and CNVI, along with the ophthalmic and maxillary division of CNV.
 Image Source: Wikimedia Commons (2016). 1315 Brain Sinuses, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:1315_Brain_Sinuses.jpg (Accessed: 9 January 2024).
Meninges
The cranial meninges are the protective lining surrounding the brain and spinal cord. This also serves as the lining to the subarachnoid space and acts as a supportive structure for the cranial vasculature. There are three distinct layers to the cranial meninges: dura mater, arachnoid mater and pia mater.
The periosteal dura mater adheres to the calvarium’s internal surface and cranial sutures. In contrast, the meningeal dura mater lines the brain and forms a continuous layer along the foramen magnum into the spinal cord. Apart from the areas where the dural sinuses exist, both layers of the dura mater are fused. The meningeal dura mater also creates infolding that forms partitions within the brain, including:
- Falx cerebri – Lies in the longitudinal cerebral fissure
- Tentorium cerebelli – Lies between the occipital lobe and cerebellum
- Falx cerebelli – Lies inferior to the tentorium cerebelli and partially separated the cerebellar hemispheres
- Diaphragm sella – Suspended between the clinoid process and forms a roof over the hypophysial fossa.
The arachnoid mater and pia mater both form the lining of the leptomeninx. The space between the arachnoid mater and the pia mater is the subarachnoid space. The pia mater is a highly vascular structure adherent to the brain’s surface.
Ventricular system and cerebrospinal fluid (CSF) production
The ventricular system in the brain consists of 4 main ventricles: 2 lateral ventricles, the third ventricle and the fourth ventricle. The two lateral ventricles connect to the third ventricle via the interventricular foramen, while the cerebral aqueduct within the midbrain connects the third and fourth ventricles. Two lateral apertures and a median aperture allow CSF to drain from the fourth ventricle into the subarachnoid space around the brain and spinal cord.
CSF production begins in the choroid plexus within the ventricular system. It will circulate through the various ventricles and is excreted around the subarachnoid space. Reabsorption of the CSF occurs at the dural sinuses, where arachnoid granulations project into the superior sagittal sinus. The CSF’s primary function is to cushion the brain and blood vessels from the cranial vault.

Image Source: Wikimedia Commons (2013). Blausen 0896 Ventricles Brain, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Blausen_0896_Ventricles_Brain.png (Accessed: 9 January 2024).
The cerebellum and the brainstem
Cerebellum
The cerebellum is located within the posterior fossa and is inferior to the occipital lobe. It consists of 2 cerebellar hemispheres connected by the cerebellar vermis. The cerebellum communicates with the remainder of the cerebral cortex and brainstem via three main peduncles: superior cerebellar peduncle, middle cerebellar peduncle, and inferior cerebellar peduncle. Each cerebellar hemisphere controls the ipsilateral half of the body. The cerebellum’s primary function is to allow the control and coordination of complex movement within the extremities, along with the maintenance of normal muscle tone and ocular movements. Proprioceptive information is also processed within the cerebellum to allow control of balance.
The vascular supply to the cerebellum is via the basilar and vertebral arteries. The basilar artery supplies the superior and anterior aspects of the cerebellum via the superior cerebellar artery and anterior inferior cerebellar artery, respectively. The superior cerebellar peduncle is supplied by the superior cerebellar artery, while the superior and anterior inferior cerebellar artery supply the middle cerebellar peduncle. The vertebral artery supplies the posterior aspect of the cerebellum and inferior cerebellar peduncle via the posterior inferior cerebellar artery.
The cerebellar veins will drain via the transverse and superior petrosal sinuses.

Image Source: Wikimedia Commons (2015). Cerebellum arteries en, Licensed under a creative commons licence. Available for free at: https://upload.wikimedia.org/wikipedia/commons/d/d9/Cerebellum_arteries_en.svg (Accessed: 9 January 2024).
Brainstem
The brainstem consists of 3 separate structures: the midbrain, pons and medulla. The brainstem holds the nuclei of several cranial nerves, sensory and motor tracts, and reflex centres.
The midbrain, or mesencephalon, is between the cerebral cortex, pons and cerebellum. The midbrain houses the oculomotor (CNIII) and the trochlear nerve (CNIV) nuclei. The Edinger-Westphal nucleus is also located within the midbrain between the oculomotor nucleus and the Sylvius aqueduct and acts as the parasympathetic innervation to the iris and ciliary muscle. Other structures within the midbrain include the red nucleus, ventral tegmental area, periaqueductal grey area and the substantia nigra. There are also complex reticular networks that exist within the midbrain that are responsible for visceral functions, movement control and maintenance of consciousness/wakefulness. The reticular formation forms three columns, including the raphe nucleus (serotonergic nucleus), gigantocellular reticular nuclei (movement control) and parvocellular reticular nuclei (expiration control). Lastly, the midbrain also has ascending and descending pathways, including the spinothalamic, corticospinal, and rubrospinal tract.
The midbrain receives an extensive blood supply, with the basilar artery branches supplying the anterior aspects of the midbrain, the posterior cerebral artery supplying the lateral aspects, and the superior cerebellar artery supplying the posterior aspects.
 Image Source: Wikimedia Commons (2009). Midbrainsection, Licensed under a creative commons licence. Available for free at: https://upload.wikimedia.org/wikipedia/commons/c/cb/Midbrainsection.svg (Accessed: 9 January 2024).
The pons are inferior to the midbrain and medulla oblongata. The pons serve as the site of origin for several cranial nerve nuclei, including the trigeminal nerve (CN V), abducens nerve (CN VI), facial nerve (CN VII) and the vestibulocochlear nerve (CN VIII). Many ascending and descending tracts also pass through the pons, including the corticospinal, corticobulbar, spinothalamic and medial lemniscus tracts. The vasculature to the pons predominantly arises from the pontine artery of the basilar artery. Small contributions arise from the anterior inferior cerebellar and superior cerebellar arteries.

Image Source: Wikimedia Commons (2016). Pons section at facial colliculus, Licensed under a creative commons licence. Available for free at: https://upload.wikimedia.org/wikipedia/commons/1/13/Pons_section_at_facial_colliculus.png (Accessed: 9 January 2024).
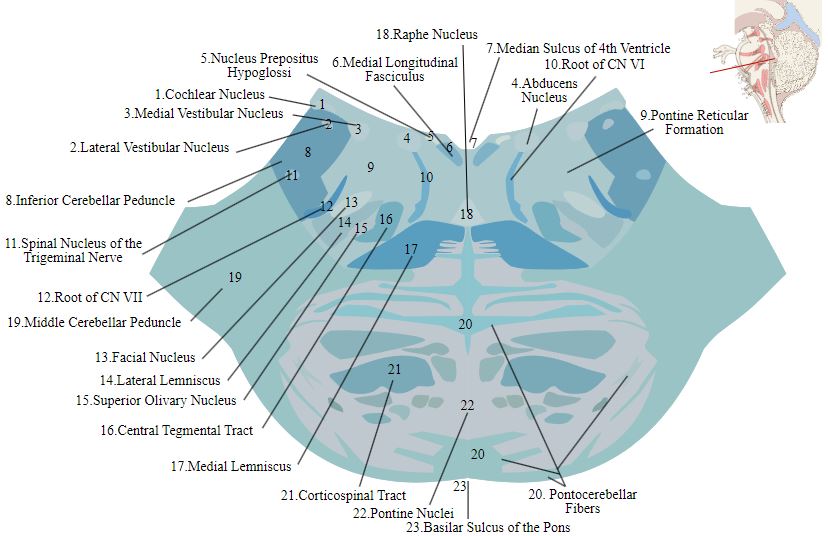 Image Source: Wikimedia Commons (2011). Lower pons horizontal KB, Licensed under a creative commons licence. Available for free at: https://upload.wikimedia.org/wikipedia/commons/d/dc/Lower_pons_horizontal_KB.svg (Accessed: 9 January 2024).
The medulla oblongata is the inferior-most portion of the brainstem. The ventral portions of the medulla house the pyramids and olives. The pyramids house the descending motor tracts of the brain, and the decussation of the motor fibres at this level forms the anterior and lateral lemniscus tracts of the spinal cord. The olivary nuclei allow cerebellar motor function and sound perception. It also houses the nuclei for the glossopharyngeal nerve (CN IX), vagus nerve (CN X), accessory nucleus nerve (CN XI) and the hypoglossal nerve (CN XII). Lastly, the medulla also houses the cardiovascular and respiratory regulatory centres within the ventral medulla. The vascular supply to the medulla is complex, with blood supplies originating from the anterior spinal artery, vertebral artery, posterior spinal artery and the posterior inferior cerebellar artery.
 Image Source: Wikimedia Commons (2013). Sobo 1909 665, Licensed under a creative commons licence. Available for free at: https://upload.wikimedia.org/wikipedia/commons/7/79/Sobo_1909_665.png (Accessed: 9 January 2024).
Ocular system
The visual pathway begins within the retinal layer of the eye. The fibres of the retina unite at the optic disc to form the optic nerve. The optic nerve is surrounded by the dura mater as a direct extension of the intracranial dura mater. It exits via the orbital foramen and enters the cranium via the optic canal into the middle cranial fossa. The optic nerves will unite above and behind the pituitary stalk to form the optic chiasm. At the optic chiasm, the nasal fibres from the right eye will unite with the temporal fibres of the left eye to form the left optic tract. Each optic tract continues posteriorly through the lateral geniculate body to the genico-calcarine tracts within the parietal and temporal lobes. It terminates within the primary visual cortex in the occipital lobe. A small proportion of fibres will pass through the superior colliculus and Edinger-Westphal nucleus to provide parasympathetic innervation to the eye.
The visual and parasympathetic system drives the pupillary reflex. The optic nerve controls the afferent limb, and its impulses are directed towards the pretectal nucleus and, subsequently, the Edinger-Westphal nucleus bilaterally. The oculomotor nerve controls the efferent limb as parasympathetic fibres leave the Edinger-Westphal nucleus into the ciliary ganglion and the oculomotor nerve before terminating at the pupillary sphincter muscle.
Spinal cord
Clinical anatomy
The spinal cord is a continuation of the medulla oblongata after it exits the foramen magnum. It is housed within the vertebral canal of the spinal cord and continues down to the level of L2. The spinal cord contains a cervical and lumbar enlargement to accommodate the formation of the brachial plexus and the lumbosacral plexus, respectively. At the level of L1, the spinal cord tapers off into a conical structure known as the conus medullaris before dividing into the final spinal nerves as the cauda equina at L2. After the cord divides into the cauda equina, the extension of the pia and dura mater travels inferiorly to form the filum terminale, providing longitudinal anchoring for the spinal cord. The spinal cord is covered with a similar lining to the cerebral cortex: the dura, subarachnoid, and pia mater. CSF flows within the subarachnoid space between the subarachnoid and pia mater.
Transverse sections of the spinal cord reveal the internal morphology of the spinal cord. The grey matter of the spinal cord is located centrally as an H-shaped structure and can be divided into several laminae based on its function. The anterior (ventral) horn contains the motor nerve cells, while the posterior (dorsal) horn contains the sensory nerve cells. Within levels T1-L2, the spinal cord also contains a pair of lateral horns within the spinal cord grey matter, which contains neurons responsible for sympathetic innervation and reflex pathways. The white matter of the spinal cord surrounds the grey matter, which houses the main ascending and descending tracts of the nervous system. The white matter tracts are divided into three sections: anterior (ventral) funiculus, lateral funiculus and posterior (dorsal) funiculus.
The posterior column contains the primary sensory tract, the dorsal column-medial lemniscus system. This column receives proprioception, fine touch and two-point discrimination sensation and transmits this to the sensory cortex.
The spinothalamic tract is the other major sensory tract within the spinal cord. The ventral spinothalamic tract transmits crude touch and pressure sensation, while the lateral spinothalamic tract transmits pain and temperature sensation. It is important to note that sensory fibres of both spinothalamic tracts will cross the midline at each level of the spinal accord before ascending the spinal cord.
The ventral column holds the corticospinal tract. This column carries motor fibres from the brain’s motor cortex down to the muscles of the body, allowing voluntary muscle movement. Extrapyramidal tracts that are responsible for the maintenance of posture, tone and reflexes are also found within the ventral column. This includes the rubrospinal tract, vestibulospinal tract, reticulospinal tract and tectospinal tract.
Sensory nerve fibres enter the spinal cord via the dorsal root ganglion into the posterior spinal cord. The motor fibres exit the spinal cord via the ventral root through the anterior spinal cord. The motor and sensory roots meet at the intervertebral foramen to form the spinal nerve, and there are 31 pairs of spinal nerves for each corresponding spinal level. Each spinal root then divides into the ventral and dorsal rami. The spinal nerve’s dorsal rami typically innervates the back’s skin and muscles. The ventral rami of the spinal nerves will form the bulk of the peripheral nervous system.
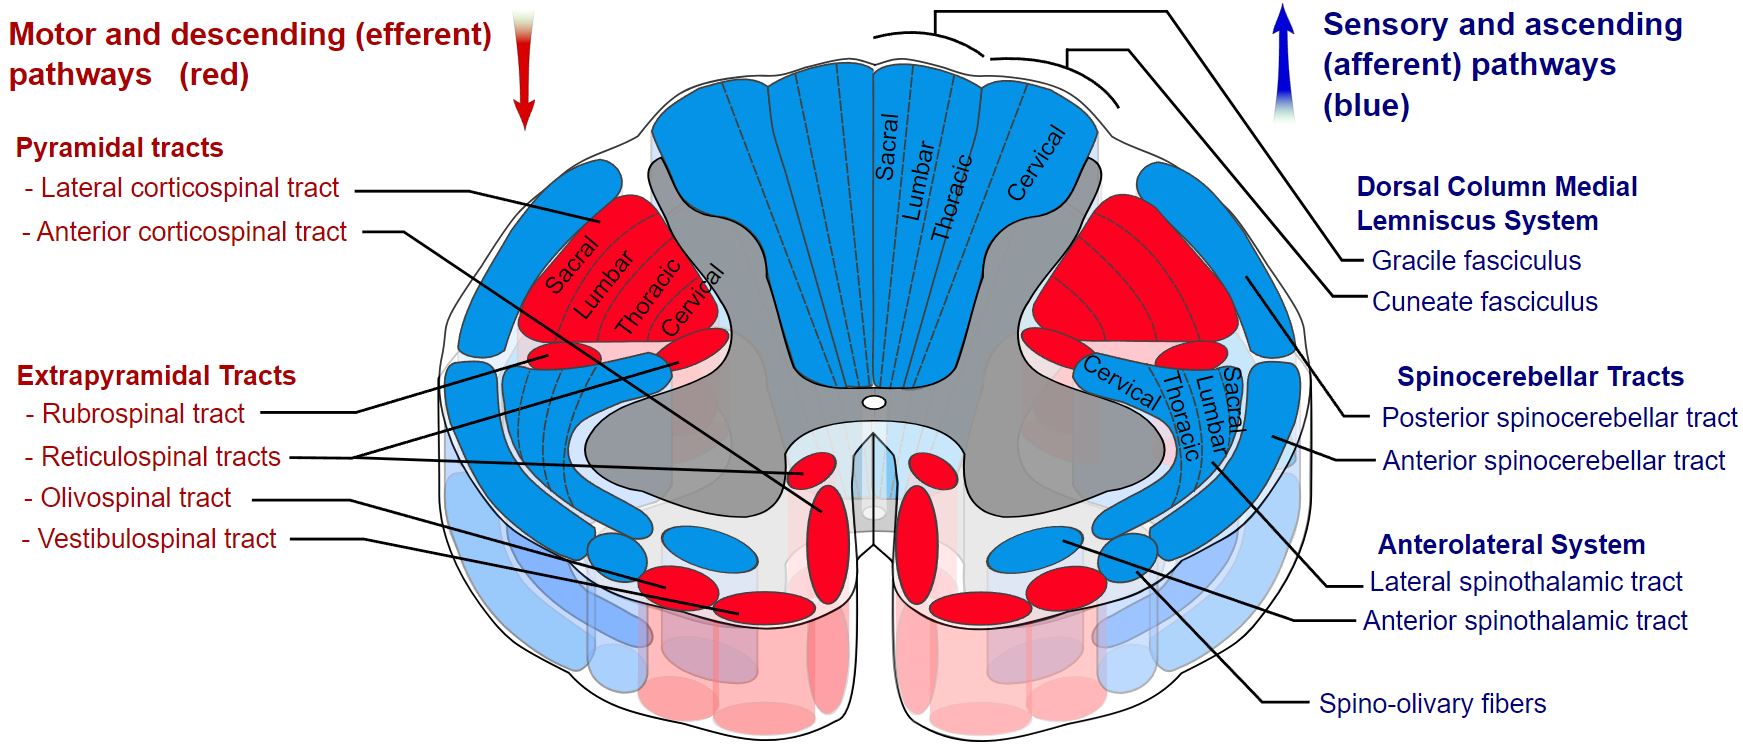 Image Source: Wikimedia Commons (2019). Spinal cord tracts – English, Licensed under a creative commons licence. Available for free at: https://upload.wikimedia.org/wikipedia/commons/b/b2/Spinal_cord_tracts_-_English.svg (Accessed: 9 January 2024).
Vasculature
The main blood supply of the spinal cord originates from the anterior and posterior spinal arteries. The anterior spinal artery originates from the anastomosis of the two vertebral arteries and supplies the anterior 2/3rd of the spinal cord. The posterior spinal artery arises from the posterior inferior cerebellar and vertebral arteries.
References
- Moore, K. L., Dalley, A. F., & Agur, A. M. R. (2014). Head In Moore’s Clinically Orientated Anatomy (7th ed.). China: Lippincott.
- Moore, K. L., Dalley, A. F., & Agur, A. M. R. (2014). Cranial Nerves. In Moore’s Clinically Orientated Anatomy (7th ed.). China: Lippincott.
- Moore, K. L., Dalley, A. F., & Agur, A. M. R. (2014). Back. In Moore’s Clinically Orientated Anatomy (7th ed.). China: Lippincott.
- Hall, J. E. (2011). The Nervous System: A. General Principles and Sensory Physiology. In Guyton and Hall Textbook of Medical Physiology (12th ed.). USA: Saunders Elsevier.
- Hall, J. E. (2011). The Nervous System: B. The Special Senses. In Guyton and Hall Textbook of Medical Physiology (12th ed.). USA: Saunders Elsevier.
- Hall, J. E. (2011). The Nervous System: C. Motor and Integrative Neurophysiology. In Guyton and Hall Textbook of Medical Physiology (12th ed.). USA: Saunders Elsevier.
- Jarman, P. (2012). Neurological Diseases. In P. Kumar & M. Clark (Eds.), Kumar & Clark’s Clinical Medicine (12 ed.). Spain: Elsevier.
- Jimsheleishvili S, Dididze M. Neuroanatomy, Cerebellum. [Updated 2021 Jul 31]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2022 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK538167/
- Basinger H, Hogg JP. Neuroanatomy, Brainstem. [Updated 2021 May 8]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2022 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK544297/
- Ganapathy MK, Reddy V, Tadi P. Neuroanatomy, Spinal Cord Morphology. [Updated 2021 Oct 30]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2022 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK545206/
- Bui T, M Das J. Neuroanatomy, Cerebral Hemisphere. [Updated 2021 Jul 31]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2022 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK549789/
- Torrico TJ, Munakomi S. Neuroanatomy, Thalamus. [Updated 2021 Jul 31]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2022 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK542184/
- Young CB, Reddy V, Sonne J. Neuroanatomy, Basal Ganglia. [Updated 2021 Jul 31]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2022 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK537141/
- Ngnitewe Massa R, Minutello K, Mesfin FB. Neuroanatomy, Cavernous Sinus. [Updated 2021 Jul 26]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2022 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK459244/
Peripheral nervous system
Brachial plexus
Root, trunk, division and cord
The brachial plexus provides the motor, sensory and autonomic innervation to the upper limb, including the scapular region. The C5-T1 spinal nerves will contribute towards the brachial plexus. The anterior (ventral) rami of these spinal nerves will form the roots of the brachial plexus. These spinal nerves will pass along the border of the anterior and medial scalene muscles to enter the base of the neck.
Once at the base of the neck, the roots will combine to form the brachial plexus trunks. Three trunks exist:
- Superior trunk – C5-C6 roots
- Middle trunk – C7 root
- Inferior trunk – C8-T1 roots
The brachial plexus trunks will then divide into the brachial plexus divisions at the neck’s posterior triangle. Each trunk will divide into an anterior and posterior division, resulting in 6 nerve fibres passing into the axillae
Each division of the brachial plexus will combine within the axillae to form 3 cords, and the nomenclature of the cord depends on the nerve fibre’s relation to the axillary artery. The three cords consist of the following:
- Lateral cord – Anterior division of the superior and middle trunk
- Posterior cord – Posterior divisions of the superior, middle and medial trunk
- Medial cord – Anterior division of the inferior trunk
The cords will then continue down the upper limb and give rise to the major nerves of the upper limb.
Major branches
The first nerve to exit the brachial plexus arises from the root of the brachial plexus. The dorsal scapular nerve arises directly from the C5 spinal nerve and innervates the levator scapulae, rhomboid major and rhomboid minor muscles. The long thoracic nerve will arise from the C5, C6 and C7 spinal nerves and innervates the serratus anterior muscle.
The superior trunk of the brachial plexus gives rise to the suprascapular nerve and nerve to subclavius. The suprascapular nerve innervates the supraspinatus and infraspinatus muscles. There are no branches from the middle and inferior trunks. There are also no branches arising from the division of the brachial plexus.
The branches of the cords of the brachial plexus are as follows:
- Lateral cord
- Lateral pectoral nerve (C5-C7 roots) – Innervates the pectoralis major
- Middle cord
- Medial pectoral nerve (C8-T1 roots) – Innervates the pectoralis major and pectoralis minor
- Medial brachial cutaneous nerve (C8-T1 roots) – Innervate medial side of the arm
- Medial antebrachial cutaneous nerve (C8-T1 roots) – Innervates the medial side of the forearm.
- Posterior cord
- Upper subscapular nerve (C5-6 roots) – Innervates the subscapularis muscle
- Middle subscapular nerve (C6-8 roots) – Innervates the latissimus dorsi muscle
- Lower subscapular nerve (C5-6 roots) – Innervates the subscapularis and teres major muscles.
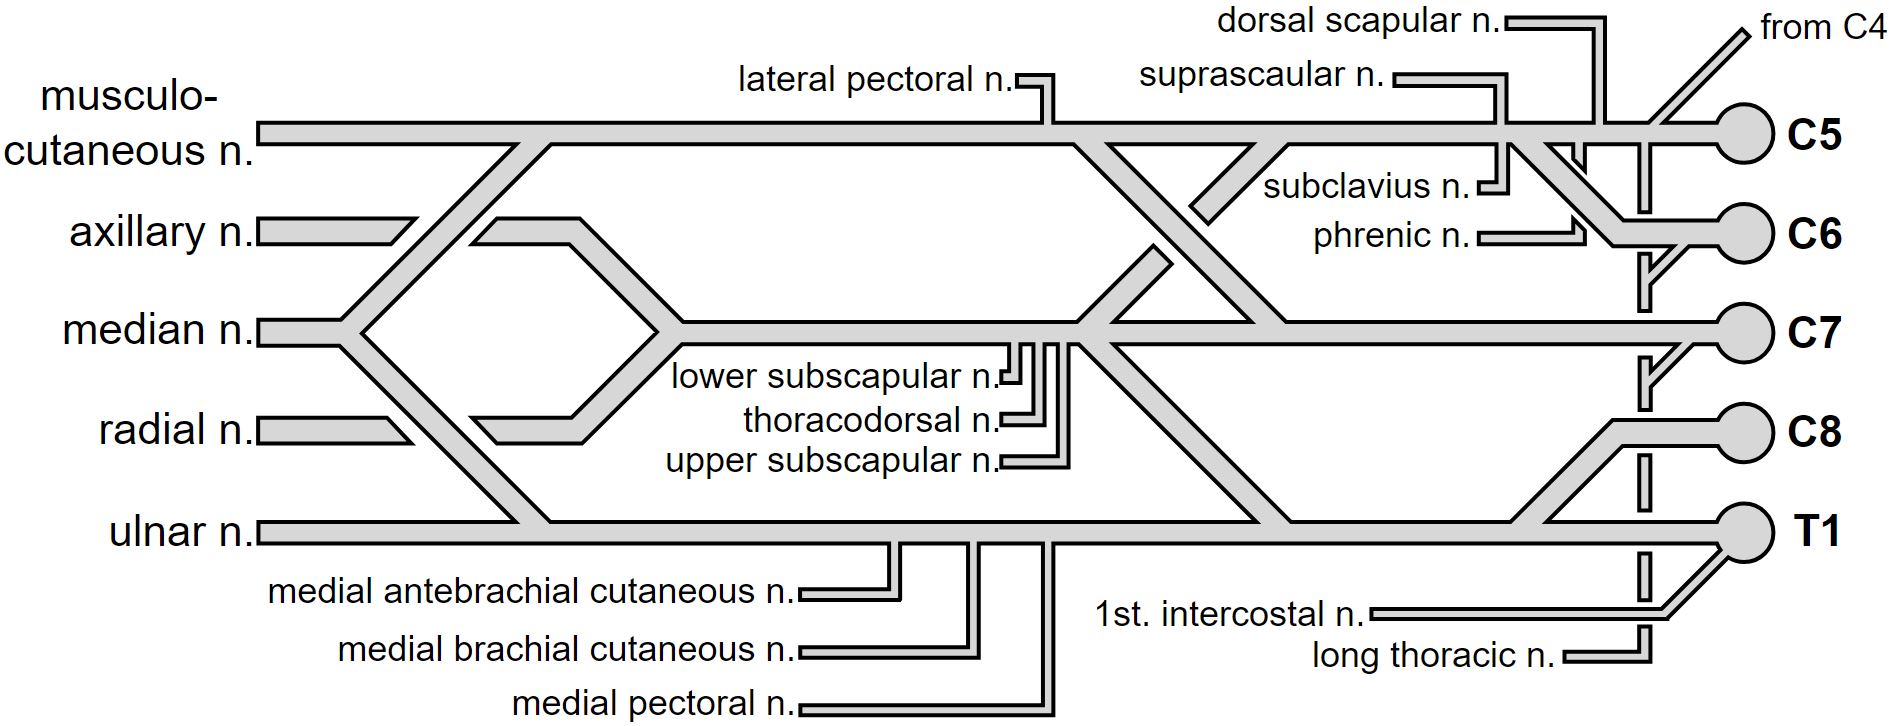 Image Source: Wikimedia Commons (2007). Brachial plexus, Licensed under a creative commons licence. Available for free at: https://upload.wikimedia.org/wikipedia/commons/7/73/Brachial_plexus.svg (Accessed: 9 January 2024).
The cords of the brachial plexus will terminate as the five major nerves within the upper extremities. These are the musculocutaneous, axillary, ulnar, radial and median nerves.
Musculocutaneous nerve
The musculocutaneous nerve is the terminal branch of the lateral cord and consists of the C5, C6 and C7 nerve roots. It provides motor innervation to the coracobrachialis, brachialis and biceps brachialis. As the nerve emerges lateral to the biceps within the forearm, it provides sensory innervation to the lateral forearm as the lateral cutaneous nerve. Injuries to this nerve are relatively uncommon due to its protected location in the axillae but can still be damaged iatrogenically or via stabbing injuries to the axillae.
Axillary nerve
The axillary nerve is a continuation of the posterior cord and comprises the C5 and C6 roots. The nerve passes posterior to the axillary artery, exits along the inferior border of the subscapularis, and passes medial to the surgical neck of the humerus. It will divide into its 3 terminal branches past this point:
- Posterior terminal branch: Motor innervation to the posterior deltoid and teres major + sensory innervation of the skin over the inferior deltoid (as supplied by the upper lateral cutaneous nerve of the arm).
- Anterior terminal branch – Motor innervation to the anterior deltoid muscle.
- Articular branch – Supplies the glenohumeral joint.
Injury to the axillary nerve commonly occurs with proximal humeral or shoulder injuries, including shoulder surgery, shoulder dislocations and proximal humeral fractures.
Ulnar nerve
The ulnar nerve is the continuation of the middle cord and contains the C8 and T1 root fibres. The ulnar nerve does not branch within the arm. As it courses through the forearm, it gives off three branches:
- Muscular branch – Innervates the flexor carpi ulnaris and the medial half of flexor digitorum profundus.
- Palmar cutaneous branch – Supplies the medial 1/3rd of the palm
- Dorsal cutaneous branch – Supplies the medial 1/3rd of the dorsum of the hand and medial 1/3rd of digits.
The ulnar nerve traverses superficial to the flexor retinaculum and enters via the Guyon’s canal. It terminates as the ulnar nerve divides into a superficial and deep branch of the ulnar nerve. The superficial branch of the ulnar nerve innervates the palmaris brevis along with sensory innervation to the palmar surface of the medial half of the fourth digit and the fifth digit. The deep branch of the ulnar nerve innervates the muscles within the hypothenar eminence and the interosseous muscles. Ulnar nerve injuries can occur with injuries to the elbow at the level of the medial epicondyle, along with compression along the cubital tunnel. It can also be damaged at the level of the wrist.
Median nerve
The median nerve is derived from the anterior divisions of the medial and lateral cords and contains the roots from the C6-T1 spinal nerve. No branches arise within the arm. Within the forearm, the anterior interosseous and palmar cutaneous nerves arise from the median nerve. The anterior interosseous nerve provides motor innervation to the deep flexors of the anterior compartment of the forearm. The palmar cutaneous branch innervates the lateral aspect of the palm. The median nerve will provide direct innervation to the superficial and middle flexors of the forearm.
The median nerve continues into the palm via the carpal tunnel and divides into its terminal branches. The recurrent branch of the median nerve will innervate the thenar muscles. The palmar digital branch will provide sensory innervation of the palmar surface and fingertips of the lateral three-and-a-half digits. Damage to the median nerve can occur via injury to the nerve at the carpal tunnel level or the level of humeral condyles.
Radial nerve
The radial nerve is the continuation of the posterior cord of the brachial plexus, which contains C5-T1 spinal roots. As it passes down the arm, it courses along the radial groove and supplies the triceps muscle. Three sensory branches of the radial nerve arise in the arm:
- The lower lateral cutaneous nerve of the arm – Innervates the lateral aspect of the arm inferior to the deltoid insertion
- Posterior cutaneous nerve of the arm – Innervates the posterior surface of the arm
- Posterior cutaneous nerve of the forearm – Innervates the skin along the middle of the forearm.
It terminates as it divides into two branches, the deep and superficial branches. The deep branch of the radial nerve provides motor innervation to the posterior compartment of the forearm. It collectively allows extension of the forearm and fingers along with the supination of the forearm. The superficial branch of the radial nerve provides sensory innervation to the dorsal surface of the lateral three-and-a-half digits of the hand. Injuries to the radial nerve can occur within the axillae, radial groove during a humeral fracture, within the forearm or during injuries to the radial head.
Reference
Moore, K. L., Dalley, A. F., & Agur, A. M. R. (2014). Upper Limb. In Moore’s Clinically Orientated Anatomy (7th ed.). China: Lippincott.
Okwumabua E, Thompson JH. Anatomy, Shoulder and Upper Limb, Nerves. [Updated 2021 Jul 28]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2022 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK526056/
Polcaro L, Charlick M, Daly DT. Anatomy, Head and Neck, Brachial Plexus. [Updated 2021 Aug 25]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2022 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK531473/
Lumbosacral plexus
Lumbar plexus
The lumbar plexus originates from the anterior rami of the L1-L4 spinal nerves, and they will combine to contribute towards six major nerves. The six nerves that arise from the lumbar plexus include:
- Iliohypogastric nerve
- Contains the T12 and L1 spinal roots. It provides sensory innervation to the lateral gluteal region.
- Motor innervation is provided to the internal oblique and transverse abdominis muscle.
- Ilioinguinal nerve
- Contains nerve roots from the L1 spinal nerve.
- It provides motor innervation to the transverse abdominis and internal obliques.
- Sensory innervation is provided to the skin of the anteromedial thigh. Sensation is also supplied to the root of the penis and anterior scrotum in males, while it supplies the mons pubis and labia majora in females.
- Genitofemoral nerve
- Contains the L1 and L2 nerve roots.
- Provides motor function to the cremasteric muscle.
- The genital branch provides sensory innervation to the anterior scrotum in males and the mons pubis and labia majora in females. Its femoral branch provides sensory innervation to the anterior thigh.
- Lateral cutaneous nerve of the thigh
- Contains the L2 and L3 spinal roots.
- Provides sensation to the anterior and lateral thigh down to the knee.
- Obturator nerve
- Contains the L2, L3 and L4 spinal roots.
- Motor innervation to the medial thigh (obturator externus, adductor longus, adductor brevis, adductor magnus, gracilis)
- Sensory innervation to the medial thigh
- Femoral nerve
- Contains the L2, L3 and L4 spinal roots
- Motor innervation to the anterior thigh (iliacus, pectineus, sartorius and quadriceps femoris)
- Sensory innervation to the anterior thigh and medial leg.
Sacral plexus
The sacral plexus is the network of nerves that supplies the lower limbs, predominantly arising from the S1-S4 spinal nerves. It also receives contributions from the L4 and L5 spinal nerves. Five major nerves arise from the sacral plexus and leave the pelvic wall via the greater sciatic foramen. The following major nerves are derived from the sacral plexus:
- Superior gluteal nerve
- Contains the L4, L5 and S1 spinal roots.
- Motor innervation to the gluteus minimus, gluteus medius and the tensor fascia lata
- Inferior gluteal nerve
- Contains the L5, S1 and S2 spinal roots
- Motor innervation to the gluteus maximus.
- Posterior femoral cutaneous nerve of the thigh
- Contains the S1, S2 and S3 spinal roots
- Provides sensory innervation to the posterior surface of the thigh, leg and the perineum.
- Pudendal nerve
- Contains the S2, S3 and S4 spinal roots
- Motor innervation to the perineal muscles, urethral sphincter, anal sphincter and levator ani.
- Sensory innervation is provided to the penis, clitoris and most of the perineal skin.
- Sciatic nerve
- Contains the L4, L5, S1, S2 and S3 spinal roots
- Motor innervation to the posterior compartment of this thigh (biceps femoris, semimembranosus, semitendinosus and the ischial portion of the adductor magnus)
- It divides further into two major branches after passing the popliteal fossa
- Tibial nerve
- Motor innervation to the posterior compartment of the leg and some intrinsic muscles of the foot
- Sensory innervation to the posterolateral leg, lateral foot and sole of the foot.
- Common peroneal/fibular nerve
- Motor innervation to the anterior and lateral compartments of the leg and intrinsic muscles of the foot
- Sensory innervation to the lateral aspect of the leg and the dorsum of the foot.
- Tibial nerve

Image Source: Wikimedia Commons (2010). Lumbar plexus, Licensed under a creative commons licence. Available for free at: https://upload.wikimedia.org/wikipedia/commons/7/73/Lumbar_plexus.svg (Accessed: 9 January 2024).
Reference
Moore, K. L., Dalley, A. F., & Agur, A. M. R. (2014). Lower Limb. In Moore’s Clinically Orientated Anatomy (7th ed.). China: Lippincott.
Spence KT, Forro SD. Anatomy, Bony Pelvis and Lower Limb, Nerves. [Updated 2021 Jul 31]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2022 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK532304/
Singh O, Al Khalili Y. Anatomy, Back, Lumbar Plexus. [Updated 2021 Aug 11]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2022 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK545137/
Autonomic nervous system
Sympathetic nervous system
Main structure
The preganglionic neurons of the sympathetic nervous system arise within the thoracolumbar section of the spinal cord. These can be found within the lateral horns of the spinal cord within spinal levels T1-L2. The sympathetic fibres will exit the spinal cord with the spinal nerves. However, they will quickly diverge from the spinal nerve as the white rami communicans and synapses onto the sympathetic chain.
The sympathetic chain consists of 3 separate structures: 2 paravertebral ganglion chains that run alongside the spinal cord and a central prevertebral ganglion located anterior to the aorta. The paravertebral chains extend along the entire length of the spinal cord. The prevertebral ganglion is closely associated with the origin of the major blood vessels within the abdominal aorta.
The preganglionic sympathetic neurons will follow one of the following paths once it has entered the sympathetic chain:
- Ascend and synapse with a ganglion at a higher vertebral level
- It is usual for sympathetic fibres to leave the T1-T5 levels as they supply the cervical ganglion
- Three main cervical ganglion exist – Superior, middle and inferior
- Inferior ganglion can be merged with the first thoracic ganglion to form the stellate ganglion.
- Descend and synapse with a ganglion at a lower vertebral level
- Usual for fibres from T5-L2 as it supplies the lumbosacral ganglions
- Synapse within the same vertebral level
- Fibres will leave the chain as a grey ramus communicans and merge with the spinal nerve’s anterior rami to arrive at its target organ.
- Travel without synapsing towards its target organ
- This usually occurs with the T5 -L2 preganglionic fibres as they travel towards the prevertebral ganglion to contribute towards the splanchnic nerves.
Once the sympathetic fibre synapses within the sympathetic chain, the postganglionic nerve fibres will leave and join the course of the peripheral nerves to reach their end-organ targets. These include the sweat glands, smooth muscle walls, erector pili muscles, respiratory lining, cardiac tissues, GI tract, urinary tracts, ciliary muscles within the eye and the adrenal glands.
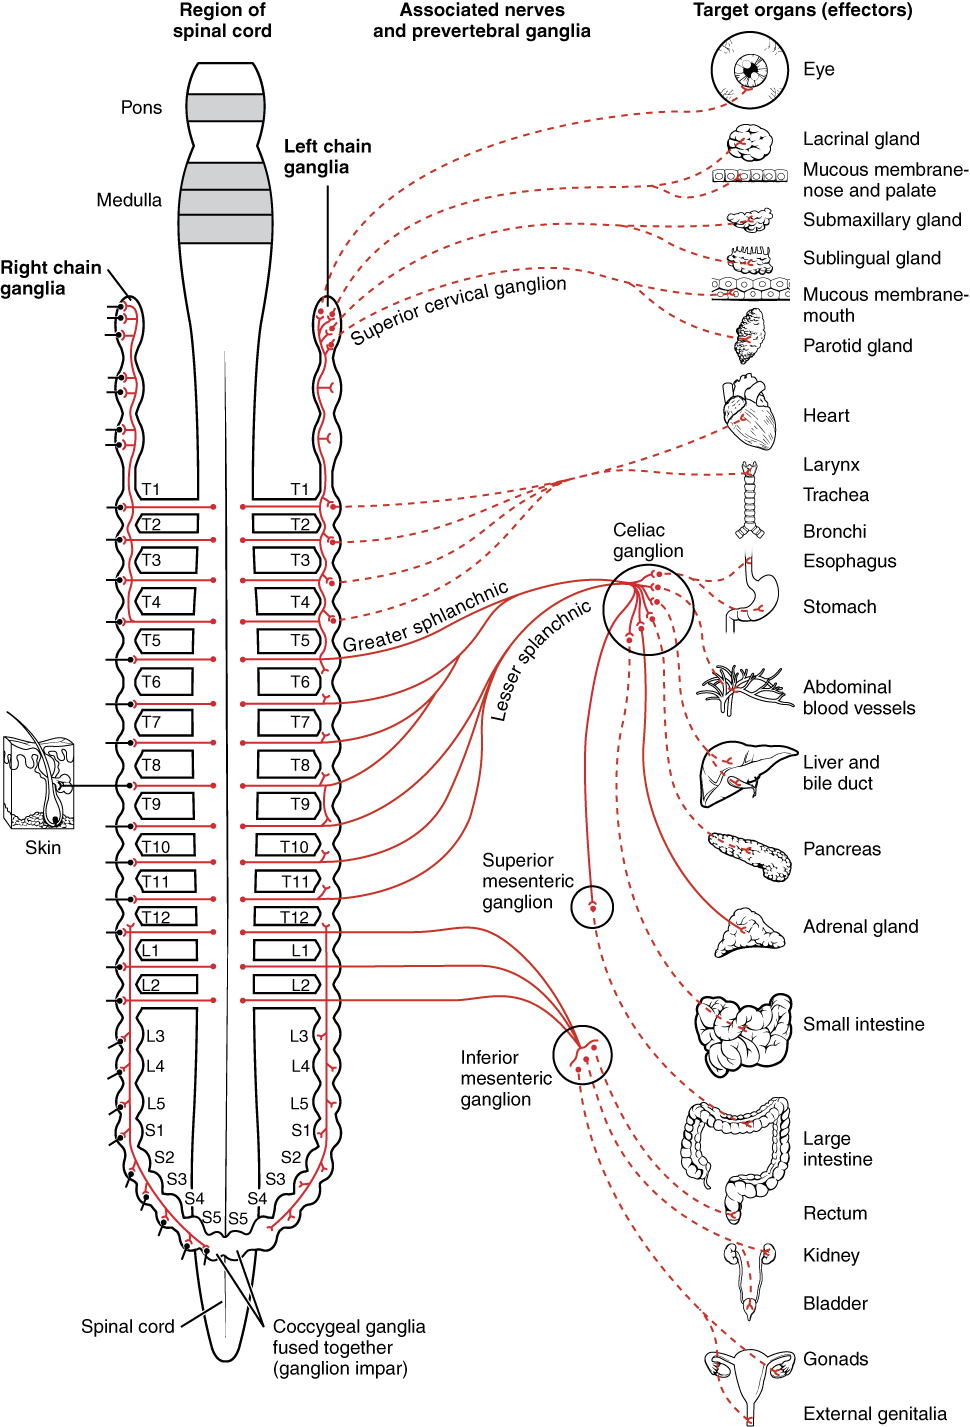 Image Source: Wikimedia Commons (2013). 1501 Connections of the Sympathetic Nervous System, Licensed under a creative commons licence. Available for free at: https://upload.wikimedia.org/wikipedia/commons/f/fd/1501_Connections_of_the_Sympathetic_Nervous_System.jpg (Accessed: 9 January 2024).
Parasympathetic nervous system
Main structure
The preganglionic neurons of the parasympathetic nervous system are concentrated within several cranial nerve nuclei within the medulla oblongata and the sacral spinal cord. In contrast to the sympathetic nervous system, the preganglionic neurons have long courses and will travel close to their effector organ before they synapse with their postganglionic neuron.
The cranial parasympathetic nervous system originates from CN III, VII, IX, and X. CN III supplies the parasympathetic fibres destined for the ciliary ganglion. Fibres from the Edinger-Westphal nucleus will travel towards the ciliary ganglion before it synapses and supplies the ciliary muscle and pupils with parasympathetic fibres via the short ciliary nerves.
CN VII carries parasympathetic fibres from the superior salivary nucleus and synapses with the pterygopalatine and submandibular ganglion. It will then supply the lacrimal gland and nasal mucosa via the greater petrosal nerve, while the submandibular nerve will supply the submandibular gland.
CN IX carries fibres from the inferior salivary nucleus with its synapse within the otic ganglion. The auricular nerve will then carry the parasympathetic fibres towards the parotid gland.
CN X supplies most of the parasympathetic innervation within the body, with the abdominal and thoracic cavities receiving its parasympathetic innervation from the vagus nerve. The origin of the fibres is from the nucleus ambiguous within the medulla. The presynaptic fibres travel down into the thorax and abdomen to supply the lungs, heart and abdominal organs via various parasympathetic ganglions close to the aforementioned organs. The abdominal organs are supplied up to the level of the splenic flexure of the large intestine.
The sacral portion of the parasympathetic nervous system arises from the S2-S4 levels. These provide the parasympathetic innervation to the descending colon, sigmoid colon, rectum and pelvic organs.
 Image Source: Wikimedia Commons (2014). Blausen 0703 Parasympathetic Innervation, Licensed under a creative commons licence. Available for free at: https://upload.wikimedia.org/wikipedia/commons/f/f0/Blausen_0703_Parasympathetic_Innervation.png (Accessed: 9 January 2024).
References
Moore, K. L., Dalley, A. F., & Agur, A. M. R. (2014). Introduction to Clinically Orientated Anatomy. In Moore’s Clinically Orientated Anatomy (7th ed.). China: Lippincott.
Hall, J. E. (2011). The Nervous System: C. Motor and Integrative Neurophysiology. In Guyton and Hall Textbook of Medical Physiology (12th ed.). USA: Saunders Elsevier.
Waxenbaum JA, Reddy V, Varacallo M. Anatomy, Autonomic Nervous System. [Updated 2021 Jul 29]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2022 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK539845/
Tindle J, Tadi P. Neuroanatomy, Parasympathetic Nervous System. [Updated 2021 Nov 5]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2022 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK553141/
Patel, T. R. (2015). Chapter 36 – Anatomy of the Sympathetic Nervous System. In R. S. Tubbs, E. Rizk, M. M. Shoja, M. Loukas, N. Barbaro, & R. J. Spinner (Eds.), Nerves and Nerve Injuries (pp. 495–506). San Diego: Academic Press.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

