


 Close
 7th June 2023
Ischaemic Stroke
It is helpful with ischaemic strokes to consider the arterial blood supply to the brain as this determines how ischaemic strokes are subdivided in the Bamford classification, according to which part of the cerebral blood supply is affected.
Circle of Willis
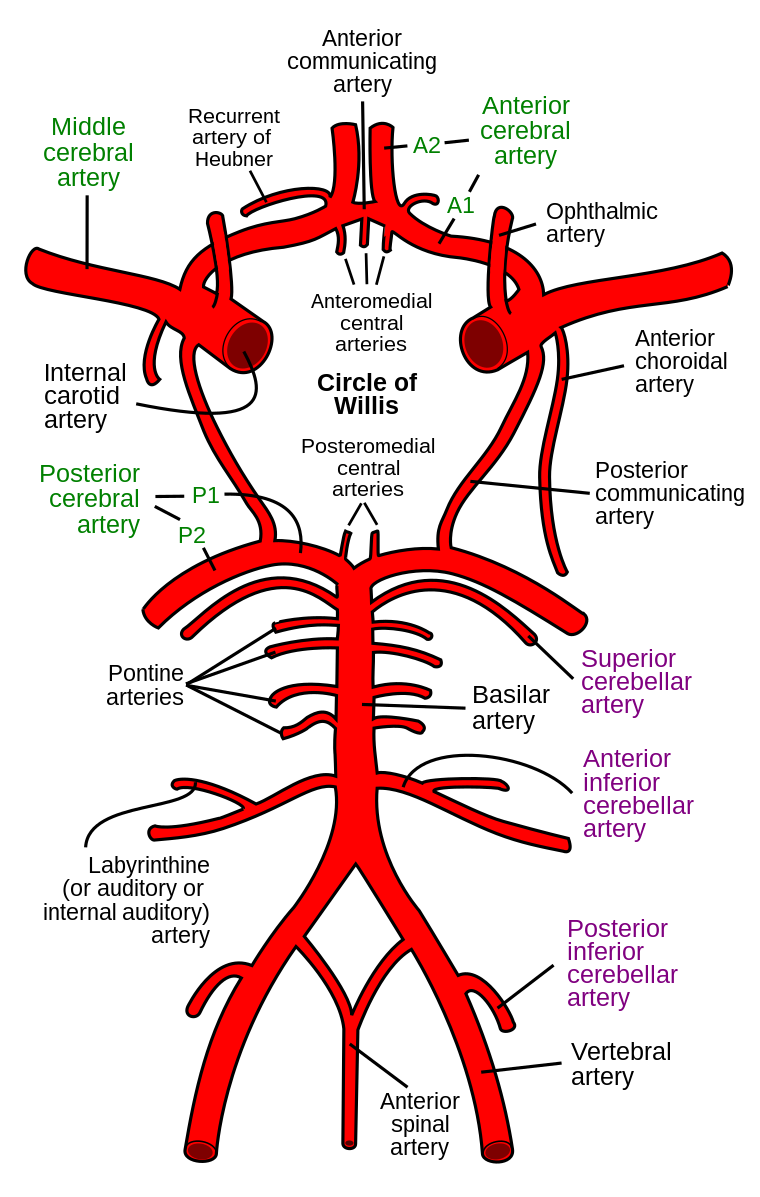
Diagram of the Circle of Willis.
Image Source: Wikimedia Commons (2007). Circle of Willis en, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Circle_of_Willis_en.svg (Accessed on: 11 January 2023).

Branches of the anterior and posterior circulations of the brain form a ring-like structure known as the circle of Willis. This connects the anterior and posterior circulation and, in the event of an ischaemic lesion, will provide collateral blood flow to maintain cerebral perfusion.
The anterior circulation is formed by the internal carotid artery dividing into the anterior and middle cerebral arteries. The anterior communicating artery connects the anterior cerebral arteries. The posterior circulation is formed by the vertebral artery forming the basilar artery, giving rise to the pontine and posterior cerebral arteries. These then connect to the anterior part of the circulation via the posterior communicating arteries.
Bamford Classification
This divides strokes into four subtypes by their clinical presentation and depending on which part of the circulation is affected.
| Type of Stroke | Diagnosis | |
|---|---|---|
| TACS (Total anterior circulation stroke) |
Large cortical stroke Anterior/middle cerebral arteries |
All three of:
|
| PACS (Partial anterior circulation stroke) |
Large cortical stroke Anterior/middle cerebral arteries |
Any two of:
|
| POCS (Posterior circulation syndrome) |
Posterior circulation syndrome | Any one of:
|
| LACS (Lacunar stroke) |
Subcortical stroke Caused by small vessel disease No higher cerebral dysfunction |
5 syndromes:
|
Investigation
Investigations for stroke can be divided into those to confirm the diagnosis of stroke and those to identify the cause of the stroke, which will affect secondary prevention measures.
Initial investigation in the emergency setting is most commonly with a non-contrast CT brain, which aims to rule out a bleed and look for stroke mimics, such as tumours, etc. There may be early signs of stroke, such as a hyperdense vessel, loss of insular ribbon and loss of grey-white differentiation, but the absence of these signs does not rule out a stroke. The changes on CT associated with stroke can take hours or days to become apparent, and it is common for a person presenting with an acute stroke to initially have a completely normal CT scan. MRI with diffusion-weighted imaging (DWI) is very sensitive at picking up acute ischaemia. Changes are apparent within approximately forty minutes but start to fade after ten days. It is important to note, however, that about ten percent of strokes are negative on MRI with DWI; therefore, stroke remains a clinical diagnosis.
Investigations to look for a cause include a 48-hour tape or Holter monitor for atrial fibrillation as a cause of cardioembolic stroke, cholesterol and glucose levels to look for risk factors or hypercholesterolaemia and diabetes and an echocardiogram to look for a cardiac thrombus. Carotid dopplers are indicated for anterior circulation strokes, and if symptomatic carotid artery stenosis >50% on the affected side is found, the patient should be referred for carotid endarterectomy.
In cases of young stroke or where a cause cannot be identified (cryptogenic stroke), one can consider screening for thrombophilia (e.g. antiphospholipid syndrome, factor V Leiden) as well as rarer causes such as a patent foramen ovale with a bubble echocardiogram.
Management
The acute management of ischaemic strokes consists of intravenous thrombolysis with alteplase (tissue plasminogen activator) and/or clot retrieval (mechanical thrombectomy) in suitable patients. Thrombolysis is indicated within four and a half hours of symptom onset. There is a risk of causing bleeding, including intracerebral haemorrhage, which can be life-threatening. The risk increases with increasing age and with time from symptom onset. Contraindications include being on a therapeutic anticoagulant and recent bleeding, although the relative risks and benefits are considered on an individual basis.
Mechanical thrombectomy is indicated within six hours of symptom onset and is considered for patients with a significant level of impairment from their stroke and good premorbid function.
High-dose antiplatelets (usually aspirin) are given if a patient is not suitable for either thrombolysis or thrombectomy and continued for two weeks before switching to a maintenance dose. Longer term, the mainstays of treatment are antiplatelet therapy, statins, blood pressure lowering drugs, and management of other risk factors. Patients should be anticoagulated if atrial fibrillation is present and referred for carotid endarterectomy if significant carotid artery stenosis is found.
Transient Ischaemic Attack
Transient ischaemic attack (TIA) is ‘an acute loss of focal cerebral or ocular function with symptoms lasting less than 24 hours and which is thought to be due to inadequate cerebral or ocular blood supply as a result of low blood flow, thrombosis or embolism associated with diseases of the blood vessels, heart, or blood’. Patients are at higher risk for having further vascular events, especially in the first few weeks and therefore require urgent assessment by a stroke specialist. Treatment is with antiplatelet therapy and treatment of vascular risk factors such as hypertension, hypercholesterolaemia, for example.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

