


 Close
 9th June 2023
Types of muco-cutaneous paraneoplastic syndromes
Acanthosis Nigricans
Acanthosis nigricans (AN) is a dermatological condition characterised by papillomatous hyperpigmented plaques, often symmetrical and found in flexural creases such as the axillae.
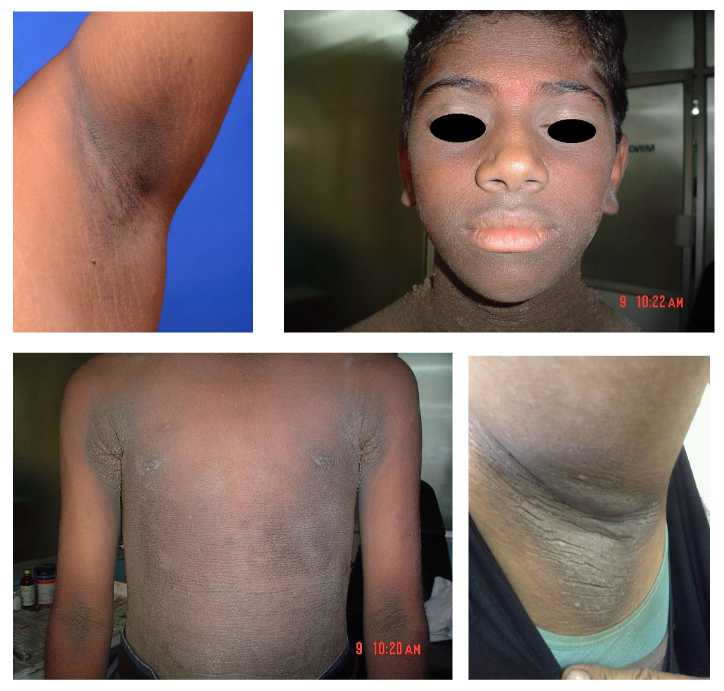
Acanthosis nigricans (underarm)
Acanthosis nigricans (face)
Acanthosis nigricans (body)
Acanthosis nigricans (neck)
Image Sources:
- Wikimedia Commons (2019). Acanthosis nigricans, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Acanthosis_nigricans.jpg (Accessed on: 9 February 2023).
- Wikimedia Commons (2010). Familial acanthosis nigricans, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Familial_acanthosis_nigricans.jpg (Accessed on: 9 February 2023).
- Wikimedia Commons (2010). Familial acanthosis nigricans5, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Familial_acanthosis_nigricans5.jpg (Accessed on: 9 February 2023).
- Wikimedia Commons (2017). Acanthious nigricans new photo for diagnosis, pigmentation appears in neck ,arm,elbow,it be related often to insulin it related to obesity and some times called pseudonigricans, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Acanthious_nigricans_new_photo_for_diagnosis,_pigmentation_appears_in_neck_,arm,elbow,it_be_related_often_to_insulin_it_related_to_obesity_and_some_times_called_pseudonigricans.jpg (Accessed on: 9 February 2023).
Its aetiology is of increased levels of insulin or insulin-like growth factor (IGF1), and therefore usually found in obese patients with insulin resistance. In the absence of these factors, a malignant cause needs to be explored. Paraneoplastic AN is most commonly associated with gastric adenocarcinomas, comprising ~60% of all malignant causes of AN, due to the ectopic secretion of IGF1. Other malignancies of the upper GI tract are the next most implicated, although the syndrome has been associated with several different solid tumours and Haematological malignancies. The paraneoplastic syndrome is indistinguishable from the benign condition, although in paraneoplastic AN there is an increased incidence of non-pigmented oro-mucosal lesions (15-25%). The management is directed at the treatment of the underlying malignancy.
Dermatomyositis
Dermatomyositis (or dermatopolymyositis), as the name suggests, is a condition of immunological aetiology characterised by myositis along with distinctive skin lesions. Like polymyositis, the exact pathophysiology is unclear, but thought to be via T cell infiltration and subsequent immune-mediated damage of the muscle and cutaneous tissues.

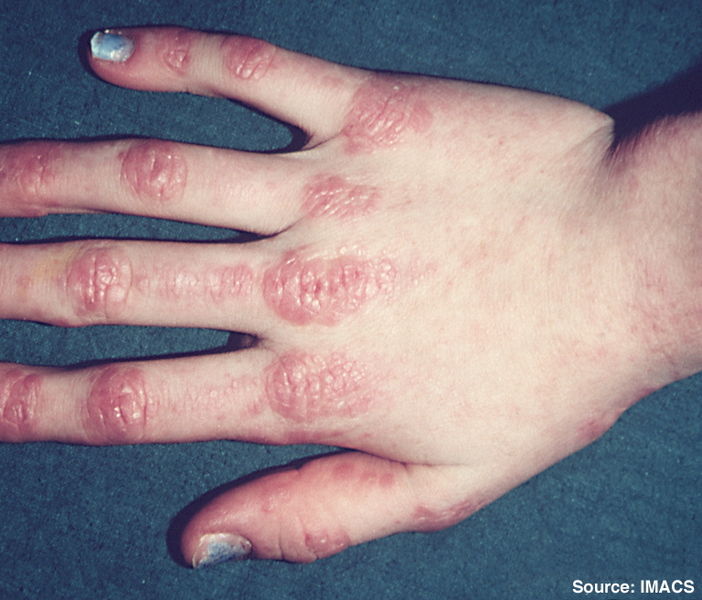
Dermatomyositis (hands)
Wikimedia Commons (2010). Dermatomyositis, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Dermatomyositis.jpg (Accessed on: 9 February 2023).
Dermatomyositis (face)
Wikimedia Commons (2010). Dermatomyositis14, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Dermatomyositis14.jpg (Accessed on: 9 February 2023).
In dermatomyositis, the skin lesions often present first, with a dusky heliotrope rash around the eyes, across the upper back, shoulders, and upper neck in a “shawl” distribution, and on the extensor surfaces of the knees and elbows, as well as the presence of Gottron’s papules (dusky erythematous or violet lesions across the backs of the carpal joints). The myositis can present later or be absent, characterised by symmetrical muscle weakness and pain particularly affecting the girdle muscles. A diagnosis of dermatomyositis is supported by raised creatine kinase and myoglobinuria, and confirmed by muscle and/or skin biopsy.
Dermatomyositis is frequently associated with underlying malignancy and is most associated with ovarian, lung, pancreatic, gastric, colorectal, and non-Hodgkin lymphoma. As with other immune mediated paraneoplastic syndromes, treatment is directed at the underlying malignancy, although steroids and immunosuppression can be used in severe cases, often whereby the morbidity of the syndrome is precluding treatment of the cancer.
Clubbing
Clubbing is the common descriptive term for swelling of the soft tissue of the distal phalanx along with loss of the angle between the nail and nail bed, resulting in characteristic deformity of the ends of the digits, as pictured. This can be further assessed using the Schamroth test: holding two opposing fingers back-to-back against each other. In unaffected fingers, there is usually a small diamond shaped gap at the nail beds, which is lost when clubbing is present.
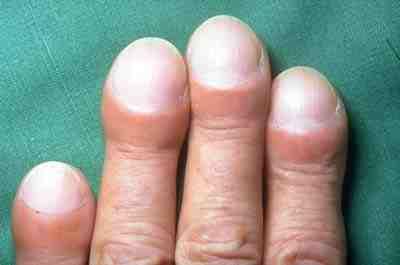
Finger clubbing.
Wikimedia Commons (2013). Clubbing of fingers in IPF, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Clubbing_of_fingers_in_IPF.jpg (Accessed on: 9 February 2023).

Schamroth test for finger clubbing.
Wikimedia Commons (2021). Schamroths, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Schamroths.jpg (Accessed on: 9 February 2023).
The pathophysiology of clubbing is not fully understood but is thought to be related to an increase in platelet-derived growth factor (PDGF) and associated factors involved in tissue proliferation. As clubbing is generally asymptomatic and non-morbid, it usually heralds the diagnosis of an underlying condition rather than requiring treatment itself.
Clubbing is typically associated with chronic or inflammatory disease, predominantly cardiac, respiratory, or gastrointestinal in origin, however, there is also an association with underlying malignancy, which needs to be investigated if other common causes have been excluded. Cancers particularly associated with clubbing are primary or metastatic lung tumours, mesothelioma, and Hodgkin lymphoma, although the co-existence of chronic lung or cardiac disease alongside malignancy makes paraneoplastic causality of the clubbing difficult to assess in many cases.
Erythema Gyratum Repens
Erythema Gyratum Repens is a cutaneous condition with a strong association with malignancy, with underlying cancer in ~80% of cases, and as such is considered paraneoplastic until otherwise proven. As with a number of other cutaneous paraneoplastic syndromes, the underlying mechanism is immunological, with similarities between tumour and cutaneous antigens causing cross-reactivity between tumour-directed and cutaneous-directed antibodies.
It is characterised by a classic concentric erythematous plaque-like rash resulting in a “wood grain” effect, typically affecting the trunk and is often itchy. The diagnosis is made on this classic morphology and the diagnosis of an underlying malignancy, as skin biopsy findings can share histological features with other conditions. Lung cancers are the predominant underlying malignancy, or less commonly oesophageal, breast or gastric cancer. Treatment is of the underlying malignancy, although a loss of skin integrity can cause significant morbidity, requiring treatment of rash with steroids or immunosuppression prior to any cancer-directed treatment.
Migratory thrombophlebitis
Thrombophlebitis is a common condition with many different (and usually benign) aetiologies, characterised by a superficial venous thrombus with an associated inflammatory reaction causing pain and erythema around the site. Migratory thrombophlebitis (also known as Trousseau sign of malignancy) is a condition whereby areas of thrombophlebitis resolve and re-present in different sites, often affecting the lower limbs, including moving from one leg to the other. Its pathophysiology, whilst not fully understood, lies in the hypercoagulable states associated with malignancy, though why this condition should affect the superficial veins and predominate in certain malignancies is not known. It is strongly associated with malignancy, particularly adenocarcinoma of the lung, the upper GI tract (including pancreas) and the urogenital tract, and can pre-date a cancer diagnosis by months or even years. A diagnosis of malignancy should be presumed until otherwise proven. The condition is not life-threatening, nor particularly morbid, and so treatment is directed at the underlying malignancy, with topical anti-inflammatories and compression stockings for symptom relief, and thromboprophylaxis if considered clinically appropriate.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

