


 Close
 22nd June 2023
Tubular Function
Reabsorption and secretion
Compared to glomerular filtration, which is relatively non-selective, tubular reabsorption is highly selective, allowing for precise control of the body plasma composition. During reabsorption, solutes and water move from the renal tubule into the renal interstitium and then into the peritubular capillaries to rejoin the circulation.
Reabsorption can be passive (i.e. diffusion of solutes down a concentration gradient) or active (i.e. transport of solutes against a concentration gradient). Reabsorption can occur paracellularly (solutes are transported between cells) or transcellularly (solutes are transported through cells).
Secretion is the active movement of substances from the peritubular capillaries into the renal tubular fluid.

Reabsorption of water and solutes from tubular lumen, through the renal interstitium and to the blood.
Proximal Convoluted Tubule
The main role of the proximal convoluted tubule (PCT) is reabsorption. It is lined by cuboidal epithelial cells covered in microvilli forming a ‘brush border’, increasing surface area for reabsorption. The epithelial cells are packed with mitochondria, providing an energy supply for the active transport of solutes.
Approximately 65% of sodium and water in the glomerular filtrate is reabsorbed in the PCT.
Na⁺-K⁺-ATPase transporters on the basolateral membrane form a primary active transport mechanism in which 3 Na⁺ ions are pumped out of the cell in exchange for 2 K⁺ ions pumped into the cell. This forms an electrochemical gradient which allows diffusion of sodium from the lumen of the renal tubule into the cell.
Sodium can be co-transported with other solutes via symporters, whereby sodium moves down its concentration gradient whilst actively co-transporting other solutes, such as glucose and amino acids, against their concentration gradients. In normal physiological states, all organic solutes, such as glucose and amino acids, are reabsorbed in the PCT via these symporters.
Sodium can also be transported out of the lumen via an antiporter, which enables reabsorption of sodium with the concurrent secretion of other ions, in particular hydrogen ions, which have a role in maintaining acid/base homeostasis. H⁺ ions secreted via the Na⁺/H⁺ antiporter combine with bicarbonate ions, forming carbonic anhydrase (H₂CO₃), which subsequently splits to form CO₂ and H₂O. These are absorbed by the PCT epithelial cells, where the previous reaction reverses, releasing bicarbonate (which is absorbed into the blood) and hydrogen ions (which are recycled for further reactions). Approximately 90% of bicarbonate is reabsorbed in the PCT.

Ion absorption and secretion in the PCT.
Image Source: Wikimedia Commons (2007). Renal Diuretics, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Renal_Diuretics.gif (Accessed on: 13 February 2023).
As the concentration of solutes within PCT decreases due to reabsorption, the solute concentration in the renal interstitium increases, and water can move out of the lumen into the interstitium by osmosis.
The PCT is also a site of secretion of organic acids and bases (e.g. bile salts, oxalate and catecholamines), and certain drug metabolites, from the peritubular capillaries into the renal tubule for rapid removal from the body.
Loop of Henle
The loop of Henle consists of the thin descending limb, the thin ascending limb, and the thick ascending limb. Despite the description, the diameter of the tubule is in fact consistent throughout the loop of Henle; the ‘thin’ limbs refer to the thin squamous epithelial cells in these segments, which lack a brush border and have low metabolic activity, whereas the thick ascending limb has cuboidal epithelium with higher metabolic activity.
The thin descending limb has a high permeability to water due to the presence of aquaporin-1 channels and lower permeability to most solutes, including sodium ions and urea.
The thin ascending limb does not contain aquaporin channels and is, therefore, impermeable to water. Passive diffusion of sodium and chloride ions can continue to occur here due to the concentration gradient between the tubular fluid and interstitium.
The thick ascending limb (TAL) is also impermeable to water. Sodium, potassium, and chloride ions are actively reabsorbed in the TAL; Na⁺-K⁺-ATPase transporters on the basolateral membrane (as also seen in the PCT) pump three sodium ions out of the cell into the interstitium, in exchange for two potassium ions. This creates a low intracellular sodium concentration and an electrochemical gradient between the lumen and the epithelial cells, allowing the movement of sodium ions out of the lumen and into the epithelial cells via Na⁺/K⁺/2Cl⁻ co-transporters (NKCC2) and Na⁺/H⁺ antiporters on the luminal membrane. The NKCC2 to-transporter is the target site of loop diuretics such as furosemide.
There is also paracellular reabsorption of magnesium, calcium, sodium, and potassium ions in the TAL down an electrical gradient due to the slight positive charge in the lumen compared to the interstitium.

Ion transport in the thick ascending limb.
Image Source: Wikimedia Commons (2007). Renal Diuretics, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Renal_Diuretics.gif (Accessed on: 13 February 2023).
Counter-current multiplication
As the TAL is impermeable to water, but reabsorbs solutes, the interstitium surrounding the loop of Henle has a high osmolarity. This high concentration of ions outside of the lumen drives the movement of water from the thin descending limb lumen into the interstitium by osmosis. This is known as counter-current multiplication.
Distal Convoluted Tubule
The thick ascending limb of the loop of Henle flows into the distal convoluted tubule (DCT), which is subdivided into the early DCT and late DCT.
Early distal tubule
The early distal tubule forms the macula densa, a group of sensing epithelial cells which are part of the juxtaglomerular apparatus, a structure providing control of glomerular filtration rate and blood flow in the nephron.
Na⁺-K⁺-ATPase transporters on the basolateral membrane (as also seen in the PCT and TAL) generate an electrochemical gradient for the movement of sodium ions into the epithelial cells through Na⁺/Cl⁻ symporters (NCC). Chloride ion channels on the basolateral membrane then allow the diffusion of chloride into the extracellular fluid. Thiazide diuretics inhibit the NCC symporter.

Ion transport in the early distal tubule.
Late distal tubule
The late distal tubule is made up of principal cells and intercalated cells.
The principal cells again use Na⁺-K⁺-ATPase transporters on the basolateral membrane to generate an electrochemical gradient for the passage of sodium from the lumen to epithelial cells through epithelial Na⁺ channels (ENaC) and secretion of potassium ions into the lumen through K⁺ uniporter channels. Principal cells are the target of potassium-sparing diuretics (e.g. spironolactone, eplerenone, amiloride). The rate of sodium ion reabsorption and potassium ion secretion in the late DCT and cortical collecting duct is controlled largely by aldosterone (see RAAS below).
Intercalated cells secrete hydrogen ions and reabsorb bicarbonate and potassium. The hydrogen ions secreted are generated as a result of a reverse reaction to that seen in the PCT, i.e. CO₂ and H₂O absorbed into the cell combine to form carbonic acid, which subsequently splits into HCO₃- and H⁺ ions. Each hydrogen ion is secreted back into the lumen via hydrogen-ATPase and H⁺/K⁺-ATPase transporters to then combine with a bicarbonate ion to be reabsorbed, as per the reaction described in the PCT. Contrary to the PCT, the intercalated cells have the capability of secreting hydrogen ions against a large concentration gradient, allowing for H⁺ ion secretion in response to acidosis, and thus play an important role in acid-base balance.
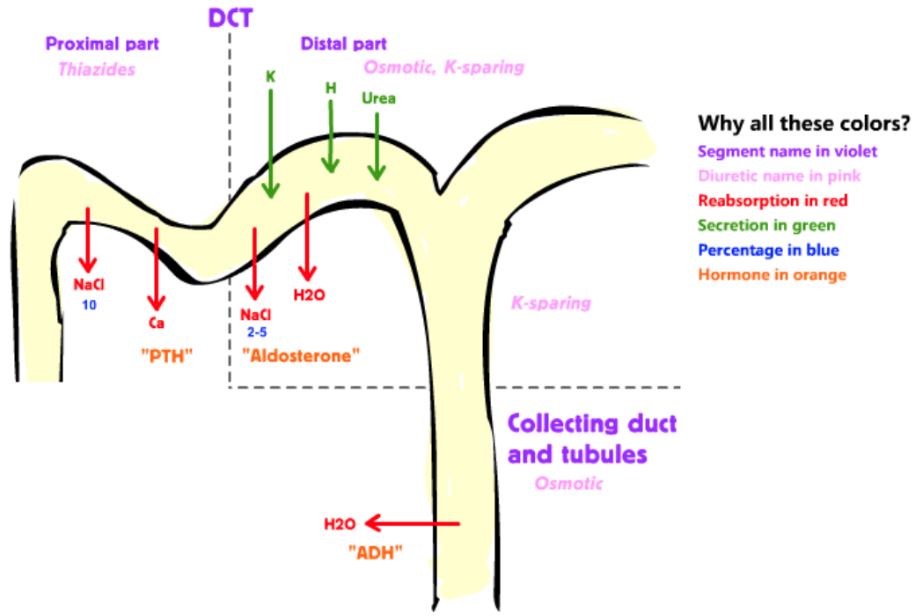
Sodium reabsorption and potassium secretion in the late distal tubule.
Image Source: Wikimedia Commons (2007). Renal Diuretics, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Renal_Diuretics.gif (Accessed on: 13 February 2023).
Collecting Duct
The permeability of the late distal tubule, cortical and medullary collecting ducts to water is controlled by antidiuretic hormone (ADH), produced by the hypothalamus, and stored in the posterior pituitary gland. In the presence of high levels of ADH (e.g. secondary to dehydration), the number of aquaporin-2 channels in the distal convoluted tubule and collecting duct increases, increasing water reabsorption, and thereby reducing the volume and increasing the osmolality of urine. Thus, ADH has an important role in controlling the degree of concentration of the urine.
ADH is clinically relevant in conditions such as: SIADH (syndrome of inappropriate ADH secretion), resulting in excessive blood dilution leading to hyponatraemia; Diabetes insipidus (DI), an insufficient release of ADH from the posterior pituitary (central DI) or reduced response of the collecting ducts to ADH (nephrogenic DI), resulting in polyuria and subsequent polydipsia.
The late DCT and cortical collecting duct are almost completely impermeable to urea, therefore, urea in these segments is excreted in the urine. Conversely to the cortical collecting duct, the medullary collecting duct is permeable to urea. In the interstitium, urea is an effective osmole (i.e. unable to cross from extracellular fluid to intracellular fluid, raising its osmolality) which allows increased reabsorption of water from the renal tubule.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

