


 Close
 18th January 2024
Presentation
Articular manifestations
RA typically presents with symmetrically swollen, painful and stiff small joints of the hand and feet. Morning stiffness is a sign of inflammatory arthritis and typically lasts over an hour. Classically, metacarpophalangeal (MCP), proximal interphalangeal joints (PIP), and metatarsophalangeal (MTP) joints are involved (The distal interphalangeal (DIP) joints and thoracic and lumbosacral spine are spared in RA). Other synovial joints which may be involved include wrists, knees, elbows, ankles, hips, shoulders and cervical spine (C1-C2).
RA onset can vary, and initial presentation may occur in the following ways:
- Insidious onset of symmetric polyarthropathy of small joints of the wrists, hands and feet is the commonest
- Insidious onset of monoarticular or oligoarticular arthritis similar to a seronegative spondyloarthropathy. Additional small joint and symmetric involvement can occur over time.
- Sudden onset polyarticular arthritis is less common
- Palindromic RA is characterised by brief, self-limited and recurrent episodes of mono/polyarthritis of various joints
- Systemic illness with extra-articular symptoms
Signs
There is inflammation early in the disease process, but usually no joint damage. With progressive inflammation and disease progression, damage to the joints and surrounding tendons can result in the classic deformities associated with RA (now rarely seen with earlier diagnosis and initiation of disease-modifying anti-rheumatic drug (DMARD) therapy.
The following signs are some of the characteristic findings associated with RA:
- ‘Zigzag’ deformity- ulnar deviation and palmar subluxation of the MCP joints and radial deviation of the wrist
- Swan neck deformities- PIP hyperextension and DIP flexion
- Boutonniere deformities- PIP flexion and DIP hyperextension
- Trigger finger- thickening of the tendon sheaths, causing the finger to lock in flexion
- Rupture of hand extensor tendons
- Carpal tunnel syndrome- tenosynovitis in the flexor tendon sheaths can cause median nerve impingement
- Claw toe deformities of the PIP joints due to plantar subluxation of the metatarsal heads
- Valgus and pes planus deformities.

Image Source: Wikimedia Commons (2014). Swan neck deformity in a 65 year old Rheumatoid Arthritis patient- 2014-05-27 01-49, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Swan_neck_deformity_in_a_65_year_old_Rheumatoid_Arthritis_patient-_2014-05-27_01-49.jpg (Accessed: 24 November 2021).

Image Source: Wikimedia Commons (2021). RA hand deformity. Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:RA_hand_deformity.JPG (Accessed: 24 November 2021).
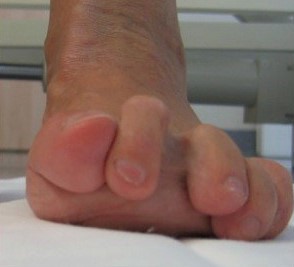
Image Source: Wikimedia Commons (2021). Luxierte Zehen bei Rheumatoidarthritis (praop), Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Luxierte_Zehen_bei_Rheumatoidarthritis_(pr%C3%A4op.)..jpg (Accessed: 24 November 2021).
Extra-articular features and complications of RA
Persistent, long-standing inflammation can lead to earlier development of cardiovascular and lung diseases and malignancy. Therefore, RA is associated with increased morbidity and premature death. Patients with high titres of Rheumatoid Factor (RF) are most likely to have extra-articular manifestations of RA.
- Skin Manifestations
- Rheumatoid nodules are the most commonly occurring skin manifestation and are associated with RF positivity. They tend to be seen on extensor surfaces which are exposed to external pressure.
- Splinter haemorrhages
- Periungual infarcts
- Leg ulcers
- Digital gangrene
- Pyoderma gangrenosum- rare
- Ocular Manifestations
- Keratoconjunctivitis sicca is the most frequent ocular manifestation and is often seen together with xerostomia in patients with secondary Sjogren’s syndrome.
- Episcleritis- inflammation of the layer superficial to the sclera, generally self-limiting and not as painful as scleritis
- Scleritis – inflammation of the sclera itself- intensely painful
- Ulcerative keratitis
- Pulmonary manifestations
- Pleural effusions- these are usually exudative in nature
- Interstitial lung disease
- Nodules can also be seen in the lung and are a feature of Caplan syndrome (Rheumatoid pneumoconiosis)- combination of seropositive RA and a characteristic pattern of fibrosis.
- Airways disease due to chronic inflammation
- Cardiac manifestations
- Increased risk of atherosclerosis with subsequent complications associated with atherosclerotic disease
- Pericarditis
- Myocarditis
- Myocardial fibrosis can lead to conduction abnormalities
- Endocarditis with formation of rheumatoid nodules in aortic or mitral valves
- Haematological manifestations
- Anaemia- multiple causes, including drug-induced, nutritional, Gastrointestinal (GI) bleed, bone marrow suppression and ineffective erythropoiesis
- Anaemia of chronic disease (normochromic and normocytic) is correlated with disease activity, especially the degree of articular inflammation
- Eosinophilia- related to disease activity or hypersensitivity to drugs
- Thrombocytosis- related to the number of active inflamed joints
- Increased risk of non-Hodgkin’s lymphoma- this risk may be further increased by immunosuppressive agents
- Felty’s syndrome- the triad of RA, splenomegaly (clinically evident or on US) and neutropenia (<1.8*10/L) on two different occasions where other causes are deemed unlikely.
- Secondary AA Amyloidosis- as with many other chronic inflammatory diseases. RA can increase the risk of developing secondary amyloidosis. The disease process is increased production of serum amyloid (AA) protein, fibrils of which get deposited in the extracellular tissues of various organs. Amyloidosis can manifest as macroglossia, cardiac failure, chronic kidney disease (usually due to nephrotic syndrome), GI bleeding or malabsorption or as hepatomegaly/ deranged liver function tests. Diagnosis is confirmed via biopsy (usually fat pad or rectal biopsy), which shows the characteristic findings of red-green birefringence when stained with Congo red. Management is through achieving control.
- GI and renal manifestations are usually iatrogenic and rare
- Neurologically- peripheral neuropathy presenting as diffuse sensorimotor neuropathy or mononeuritis multiplex.
References
- Ebel A, O’Dell J. Clinical Features, Diagnosis, and Treatment of Rheumatoid Arthritis. Physician Assistant Clinics. 2021;6(1):41-60.
- Manole Cojocaru R. Extra-articular Manifestations in Rheumatoid Arthritis [Internet]. PubMed Central (PMC). 2021 [cited 10 November 2021]. Available from: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3152850/
- Gaillard F. Caplan syndrome | Radiology Reference Article | Radiopaedia.org [Internet]. Radiopaedia.org. 2021 [cited 10 November 2021]. Available from: https://radiopaedia.org/articles/caplan-syndrome?lang=gb
- Young A, Koduri G. Extra-articular manifestations and complications of rheumatoid arthritis. Best Practice & Research Clinical Rheumatology. 2007;21(5):907-927.
- Figus F, Piga M, Azzolin I, McConnell R, Iagnocco A. Rheumatoid arthritis: Extra-articular manifestations and comorbidities. Autoimmunity Reviews. 2021;20(4):102776.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

