


 Close
 27th June 2023
Genital Ulcers
Genital ulceration can be caused by a number of STIs, including herpes, chancroid, syphilis, lymphogranuloma venereum, and donovanosis. However, it is also important to consider other non-sexually transmitted aetiologies of genital ulceration, such as malignancy, inflammatory bowel disease, herpes zoster virus, Behçet’s disease, and drug reactions.
Herpes, chancroid and syphilis have all been covered earlier and therefore will not be included in detail here. A summary of some of the differentiating features of genital ulcers can be seen in Table 1.
| Number of lesions | Pain | Lymphadenopathy | |
|---|---|---|---|
| Herpes
(Herpes simplex virus) |
Multiple | Painful | Tender
Bilateral |
| Chancroid
(Haemophilus ducreyi) |
Multiple | Painful | Tender
Can suppurate to form buboes |
| Syphilis
(Treponema pallidum) |
Solitary (usually) | Painless | Non-tender
Unilateral |
| Lymphogranuloma venereum
(Chlamydia trachomatis L1,2,3) |
Variable | Painless (though can be variable) | Tender
Unilateral ‘Groove sign’ |
| Granuloma inguinale/Donovanosis
(Klebsiella granulomatis) |
Variable | Painless (usually) | Uncommon
Pseudobuboes may occur |
Table 1: Comparison of genital ulcer aetiologies
Lymphogranuloma venereum
Lymphogranuloma venereum (LGV) is an STI caused by serovars L1, L2, and L3 of Chlamydia trachomatis, L2 being the most common strain involved. Transmission is via sexual contact, including orogenital and anal contact.
Clinical presentation is divided into three stages:
- Primary LGV
- This usually presents with a small, painless, papule/pustule or shallow ulcer in the genital region. Extra-genital sites include lips, tonsils or perianal.
- LGV proctocolitis and pharyngitis can occur, particularly in MSM.
- Secondary LGV
- Dissemination within the inguinal region leads to tender inguinal or femoral lymphadenopathy, which is often unilateral. This can cause the ‘groove sign’ in some cases in which there are enlarged inguinal lymph nodes above the inguinal ligament and enlarged lymph nodes below, with the inguinal ligament forming a groove between the two lines of swellings (See image below).
- This stage occurs 1-6 weeks after the primary lesion.
- There may be systemic features such as fever, malaise, and arthritis.
- Tertiary LGV
- Persisting infection in the anogenital tissues causes a chronic inflammation and oedema, which can result in enlargement and destructive ulceration of the genitals, leading to fistulae, scarring and fibrosis of the tissues.
- This is the commonest presentation of LGV in women and can cause esthiomene (genital lymphoedema) secondary to lymph node destruction from LGV.
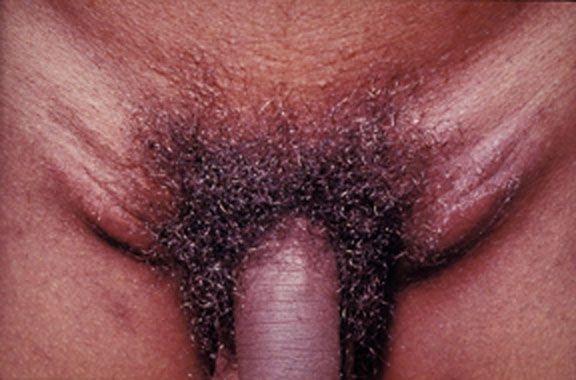
The ‘groove’ sign bilaterally in LGV
Image Source: Wikimedia Commons (2008). Lymphogranuloma venerum – lymph nodes, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Lymphogranuloma_venerum_-_lymph_nodes.jpg (Accessed on: 13 February 2023).
Diagnosis can be made with NAATs for LGV-specific DNA using swabs of the ulcer, rectum, pharynx or urethra. Culture is not readily available and has a much lower sensitivity than PCR. Lymph node aspiration or biopsy may occasionally be required to rule out other causes of lymphadenopathy. It is also important to complete a full STI screen to identify any co-infection.
Treatment is with antibiotics; in the UK, doxycycline for 21 days is the first-line choice, with erythromycin for 21 days being the second-line choice if tetracycline allergy, pregnancy, or breastfeeding. If buboes have formed, these should be aspirated. Sexual contacts within four weeks prior to the onset of LGV symptoms, or three months in asymptomatic LGV, should be tested and treated.
Donovanosis
Donovanosis, also known as granuloma inguinale, is a rare STI associated with genital ulceration, caused by Klebsiella granulomatis. It is endemic to tropical and sub-tropical countries such as Papua New Guinea, India, and Vietnam. It presents with a firm papule or nodule at the primary site of inoculation (usually the genitals but can be found orally), which later ulcerates, forming a characteristic painless ‘beefy-red’ ulcer. The lesions may heal spontaneously, however, without treatment, there is a risk of necrosis and local tissue destruction.
Lymphadenitis is uncommon, but pseudobuboes may occur (subcutaneous granulomatous nodules which may mimic buboes.)
Diagnosis is more reliably made through direct microscopy of material from a swab of the ulcer. This is stained with Giemsa and characteristically will show large mononuclear cells with intracytoplasmic cysts filled with deeply stained Gram-negative Donovan bodies.
Treatment is usually with azithromycin (first-line), doxycycline or erythromycin for three weeks minimum and until all lesions have healed.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

