


 Close
 13th February 2024
Interpretation of different statistical outcomes
Different studies will present different statistical outcomes. We will now define and discuss common statistical terminology that appears in Part 1 questions, with accompanying sample questions.
Prevalence and incidence
These two concepts are often quoted in literature but can be easily confused. Simply put, the prevalence represents the existing cases within a defined population at a particular time point, which can reflect the population’s disease burden. Incidence, on the other hand, represents the number of new cases within a defined period.
Relative risks, odds ratios and number needed to treat
Being asked to calculate any of the above from a given scenario is not uncommon in Part 1. We can measure the strength of an observed association between a risk factor and an outcome in relative terms (using risk ratios, incidence rate ratios or odds ratios) or in absolute terms (using risk differences and incidence rate differences).
Remember that the null value for risk/incidence/odds ratios is 1. This is 0 for absolute measurements (i.e., risk and incidence rate differences). The result is statistically insignificant if the confidence interval crosses the null value.
It is easy to get caught out by a question asking to calculate an odds ratio from a case-control study. This is calculated by dividing the odds of one group by the odds of another group. For example, in this 2×2 table, to calculate the odds ratio of developing mesothelioma in those exposed to asbestos compared to those without asbestos exposure:
| Healthy | Has mesothelioma | |
| With exposure to asbestos | 50 | 10 |
| Without exposure to asbestos | 50 | 2 |
Odds of mesothelioma in individuals exposed to asbestos: 10/50 = 0.20
Odds of mesothelioma in individuals unexposed to asbestos: 2/50 = 0.04
Odds ratio = 0.20/0.04 = 5 (i.e., the odds of developing mesothelioma is five times higher in those exposed to asbestos compared to those without)
Number needed to treat (NNT) and number needed to harm (NNH)
Rather than a relative risk or risk reduction or an odds ratio, an NNT can be a helpful way to summarise the results of a clinical therapeutic trial. An NNT is the number of people who undergo a specific treatment or take a medication in order to prevent an additional adverse outcome. For example, suppose a newly developed antiplatelet has an NNT of 15. In that case, one has to treat 15 people with the antiplatelet to prevent an additional adverse outcome such as a myocardial infarction.
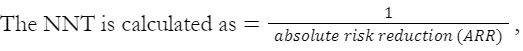
where the ARR =control event rate CER-experimental event rate (EER).
Conversely, the NNH represents the number of people needed to be exposed to a risk factor to result in additional harm.
Evaluation of diagnostic tests
Another study you could be assessed on involves determining the adequacy and appropriateness of a diagnostic or screening test. These can be assessed by examining the sensitivity, specificity, positive and negative predictive values and likelihood ratios.
The simplest way to understand how to determine these ratios is by using the following 2×2 table:
| Test result | Disease present | Disease not present |
| Positive | True positive | False positive |
| Negative | False-negative | True negative |
Adapted from: Shreffler J, Huecker MR (2021). Diagnostic Testing Accuracy: Sensitivity, Specificity, Predictive Values and Likelihood Ratios. In: StatPearls. United States: StatPearls Publishing. Available from: https://www.ncbi.nlm.nih.gov/books/NBK557491/
Sensitivity and specificity
Sensitivity defines the proportion of true positives in the population, i.e., it is the test’s ability to yield a positive result for someone who has the disease.
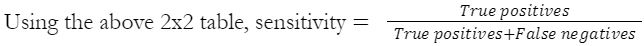
On the other hand, specificity defines the proportion of true negatives in the population, i.e., it is the test’s ability to yield a negative result for someone without the disease.
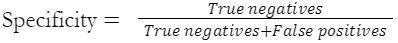
Both sensitivity and specificity are used together to determine the validity of a diagnostic test. They are inversely related such that as the sensitivity of a test increases, its specificity tends to decrease. A test with higher sensitivity is more beneficial to exclude a disease if a person tests negative. A highly specific test, however, is helpful to “rule in” a diagnosis when the person tests positive.
Positive and negative predictive values
In a clinical setting with the test result in front of you, the positive predictive value (PPV) and negative predictive value (NPV) help the clinician understand how to interpret a result and explain it to the patient in front of them.
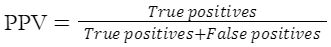

Generally, the greater the value of the PPV and NPV, the closer the test becomes a “gold standard”. Notably, the prevalence of a disease also affects the PPV and NPV. The higher the disease prevalence, the greater the PPV; conversely, the NPV would decrease.
Positive and negative likelihood ratios
The literature increasingly quotes likelihood ratios as they can be clinically more relevant than sensitivity and specificity. They are also unaffected by disease prevalence, unlike predictive values, but they can comment on how much the utilisation of a test can alter its probability. Therefore, it can be used to calculate an individual’s disease probability. They are calculated as follows:

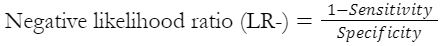
An LR+ is the probability of a person with the disease having a positive test result divided by the probability of a person without the disease having a positive test result. If the LR+ is >1, a positive result is more likely to occur in individuals with the disease than in those without. If the LR+ is between 0 and 1, then the converse is true: a positive result is less likely to occur in individuals with the disease than in those without.
An LR- is the probability of a person with the disease having a negative result divided by the probability of a person without the disease having a negative result. Therefore, an LR- >1 means a negative result is more likely to occur in those with the disease than in those without, and an LR- between 0 and 1 indicates a negative result is less likely to occur in those with the disease than those without.
References
Noordzij M, Dekker FW, Zoccali C, Jager KJ (2010). Measures of Disease Frequency: Prevalence and Incidence. Nephron Clin Pract, 115, c17-c20. doi: 10.1159/000286345
Tripepi G, Jager KJ, Dekker FW, Zoccali C (2010). Measures of Effect in Epidemiological Research. Nephron Clin Pract, 115, c91-c93. doi: 10.1159/000312870
Centre for Evidence-Based Medicine (2022). Number Needed to Treat (NNT). Accessed on 2022 Apr 1. Available from: https://www.cebm.ox.ac.uk/resources/ebm-tools/number-needed-to-treat-nnt
Shreffler J, Huecker MR (2021). Diagnostic Testing Accuracy: Sensitivity, Specificity, Predictive Values and Likelihood Ratios. In: StatPearls. United States: StatPearls Publishing. Available from: https://www.ncbi.nlm.nih.gov/books/NBK557491/
Akobeng, A.K. (2007). Understanding diagnostic tests 1: sensitivity, specificity and predictive values. Acta Pædiatrica, 96, 338-341. https://doi.org/10.1111/j.1651-2227.2006.00180.x
Akobeng, A.K. (2007). Understanding diagnostic tests 2: likelihood ratios, pre- and post-test probabilities and their use in clinical practice. Acta Pædiatrica, 96, 487-491. https://doi.org/10.1111/j.1651-2227.2006.00179.x
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

