


 Close
 7th May 2025
Left-to-Right Shunt
Atrial Septal Defect
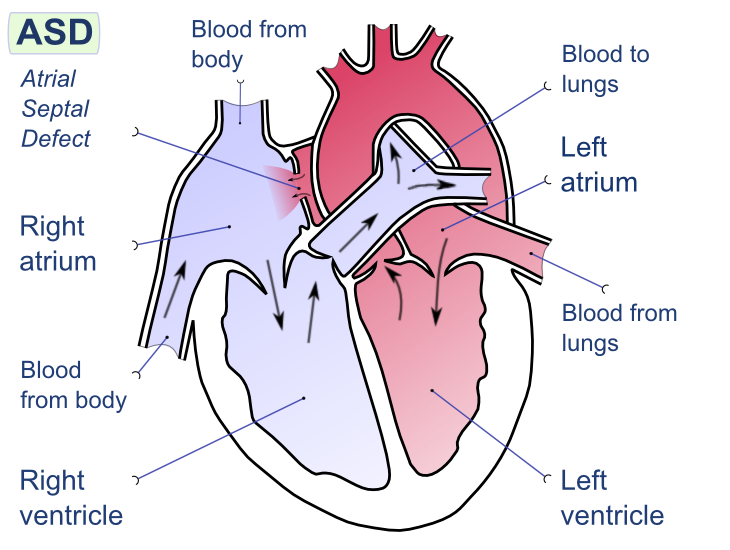
Image Source: Wikimedia Commons (2008). Atrial Septal Defect, Licensed under a creative commons licence. Available for free at:
https://upload.wikimedia.org/wikipedia/commons/9/92/Atrial_septal_defect-en.png?20080221094223 (Accessed 2 May 2025).
Atrial septal defects (ASD) refer to an intra-arterial connection that often results from the incomplete separation of the right and left atrium during foetal development. The result is a shunt between the two atria. The key features can be seen in Table Two. There are five types of ASD, from most common to least, they are patent foramen ovale, ostium secundum defect, ostium primum defect, sinus venous defect and coronary sinus defect.
| Feature | Summary |
|---|---|
| Epidemiology | 1 to 2 per 1000 live births
Most common CHD in adults |
| Aetiology | Most occur sporadically, with no prior family history
Associated with some genetic syndromes, e.g. Noonan, trisomy 21 More likely in females than males. |
| Classification |
|
| Clinical History | Adults can be asymptomatic
Often symptomatic after 4th decade: palpitations, dizziness (an atrial arrhythmia), shortness of breath, dyspnoea, fatigue, reduced exercise tolerance |
| Clinical Examination | Dependent on the size of the ASD
Most common:
Uncommon:
|
| Diagnostic Investigations | Echocardiogram: allows direct visualisation of the ASD
ECG: typically normal in small ASD but tall P waves and large R waves in V1 (moderate to severe) Chest X-ray: normal if small ASD, possible cardiomegaly (moderate to severe) |
| Management | Dependent on the calculation of the ratio of pulmonary vascular to systemic blood flow (Qp:Qs)
Qp:Qs <1.5 – observation, may resolve spontaneously Qp:Qs ≥ 1.5 or enlargement of the right atrium – corrective surgical or transcatheter closure Pulmonary Vascular Resistance >5
|
| Follow Up | For small ASD, observation should include signs of arrhythmias.
If there is no evidence of pulmonary vascular obstructive disease, there is an excellent prognosis. The older the age of the patient at the point of repair, the increased risk of adverse events. |
Table 2: The above table details the key areas regarding atrial septal defects. Sourced and adapted from Haller, Intra-atrial Communications (Atrial Septal Defects): BMJ Best Practice; 2023.
Eisenmenger Syndrome
This rare syndrome results from a congenital heart defect and a large shunt, which impacts both the heart and lungs. Initially, there is an acyanotic left-to-right shunt, which leads to increased vascular resistance and severe pulmonary arterial hypertension. Over time, the increased pulmonary resistance eventually reverses the blood flow, resulting in a cyanotic right-to-left shunt. A summary of the key features is detailed in Table Three.
| Feature | Summary |
|---|---|
| Epidemiology | A rare condition typically presents in areas with poor access to healthcare resulting in late presentation. |
| Aetiology | It can develop from any CHD where pulmonary arterial hypertension results. For example, ASD, ventricular septal defects, patent ductus arteriosus, and unrepaired tetralogy of Fallot. |
| Clinical History | A patient with known CHD presenting with worsening exertional dyspnoea
Other symptoms can include palpitations, haemoptysis, syncope, progressive cyanosis and swelling. Also, due to chronic hypoxaemia, the patient can develop symptoms related to polycythaemia. These include headache, dizziness, stroke and visual changes. |
| Clinical Examination | Signs of pulmonary hypertension
Signs related to the underlying CHD
Signs of right-to-left shunt and chronic hypoxaemia
|
| Diagnostic Investigations | Echocardiogram
ECG Chest X-ray Bloods, including full blood count and iron studies |
| Management | The ideal management is preventative, i.e. correcting the potentially causative CHD prior to the development of Eisenmenger syndrome.
Once Eisenmenger syndrome has developed, reversal of the high pulmonary arterial pressure is not possible, and a cardiopulmonary transplant is needed. This is not always possible and is associated with high mortality. Supportive treatment options can include:
|
| Follow Up | Patients with Eisenmenger have a reduced life expectancy and high mortality in the 3rd/4th decade of life.
The most common cause of death is stroke, haemoptysis, ventricular failure and pregnancy complications. Management is required from a multidisciplinary team, including cardiologists. |
Table 3: This table describes the key areas of Eisenmenger Syndrome. Sourced and adapted from Basit et al, Eisenmenger Syndrome: StatPearls Publishing; 2023 and Watchman, Eisenmenger Syndrome: Zero to Finals; 2019.
Ventricular Septal Defects
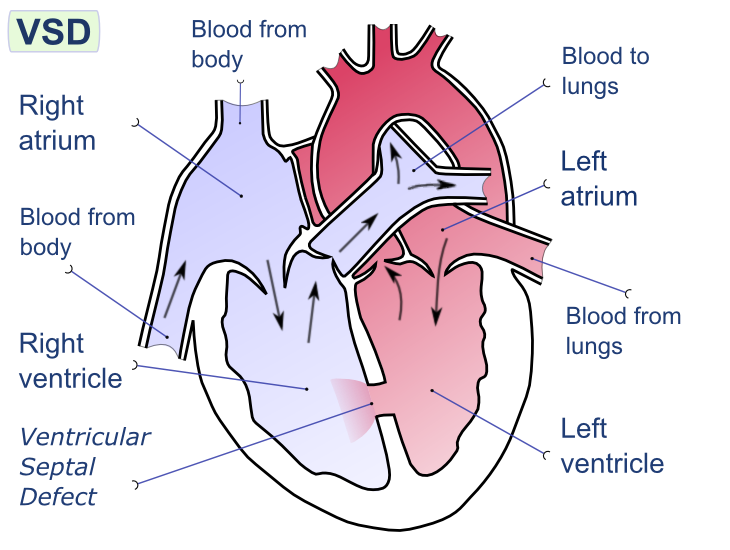
Image Source: Wikimedia Commons (2008). Ventricular Septal Defect, Licensed under a creative commons licence. Available for free at:
https://upload.wikimedia.org/wikipedia/commons/e/e1/Ventricular_septal_defect-en.png?20080222192725 (Accessed 2 May 2025).
Ventricular Septal Defects (VSD) are often congenital abnormalities in the development of the interventricular septum. These anomalies result in an abnormal conduit between the left and right ventricles, which results in an often acyanotic left-to-right shunt. It is important to note that an untreated VSD can result in Eisenmenger syndrome, which results in a cyanotic right-to-left shunt. The key details of VSD are detailed in Table Four.
| Feature | Summary |
|---|---|
| Epidemiology | The most common CHD in infants and children
Isolated VSD occurs in 3.5 per 1000 live births but often close spontaneously. VSD can accompany other congenital defects, not just in isolation Acquired VSD secondary to trauma or myocardial infarction is rare Unusual for VSD to present in adults. |
| Aetiology | Multiple classification systems exist, but the easiest is to think of them as congenital vs acquired.
Congenital
Acquired
|
| Clinical History | Failure to thrive in infancy
Shortness of breath on exertion Risk factors: Maternal alcohol use in pregnancy, Down’s syndrome, family history of CHD Repeated pulmonary infections: in shunt reversal associated with large defects |
| Clinical Examination | Holosystolic Systolic Murmur
Loud pulmonary component of the second heart sound
|
| Diagnostic Investigations | Echocardiogram – to visualise the VSD and confirmation of the left-to-right shunt.
Chest x-ray – may be normal or show cardiomegaly. ECG – dependent on the size of the VSD, not diagnostic but supportive. In medium VSD can show signs of left ventricular hypertrophy. |
| Management | Once a diagnosis has been made utilising an echocardiogram, the pulmonary-systemic blood flow ratio (Qp:Qs) is calculated.
Prophylactic antibiotics should be considered in all VSDs to prevent endocarditis. Congenital Small VSD (Qp:Qs <1) – monitoring and observation, they may spontaneously close. Medium/Large VSD (Qp:Qs ≥1.5)
Acquired Surgical repair |
| Follow Up | Annual follow-up of asymptomatic patients to monitor for development of complications.
Patients who have corrective closure require monitoring for the development of heart block or arrhythmia. Potential complications include aortic regurgitation, heart block, arrhythmia and infective endocarditis. The prognosis is dependent on the size of the VSD.
|
Table 4: This table describes the key features of ventricular septal defects. Sourced and adapted from Aggarwal, Ventricular septal defects: BMJ Best Practice; 2022.
Patent Ductus Arteriosus
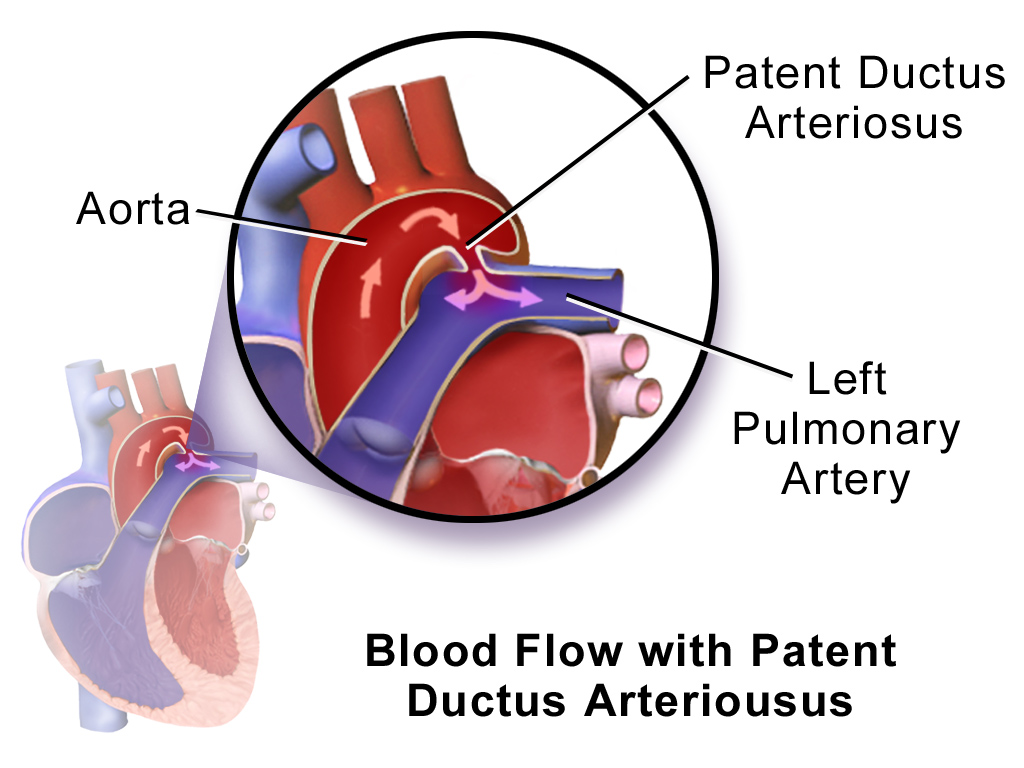
Image Source: Wikimedia Commons (2014). Blausen 0707 Patent Ductus Arteriousus, Licensed under a creative commons licence. Available for free at:
https://upload.wikimedia.org/wikipedia/commons/a/a0/Blausen_0707_PatentDuctusArteriosus.png?20140528155004 (Accessed 2 May 2025).
Patent Ductus Arteriosus (PDA) refers to the persistence of the ductus arteriosus after the first 48 hours of life. The ductus arteriosus is a foetal vascular structure that allows blood passage from the pulmonary artery to the aorta in utero, thus bypassing the foetal lungs. Therefore, PDA describes the CHD where the ductus arteriosus fails to close postnatally, allowing blood to flow from the aorta to the pulmonary artery. This is down a pressure gradient. The details of PDA are summarised in Table Five.
| Feature | Summary |
|---|---|
| Epidemiology | Incidence of 3-8 per 10,000 live births
2:1 female-to-male ratio May be present with other congenital heart defects It can present in some genetic syndromes, e.g. Noonan, Downs, DiGeorge |
| Aetiology | In utero, patency is maintained by hypoxaemia and circulating prostaglandins (PGE2 and PG12).
In the post-natal period, increased oxygen saturations and reduced circulating prostaglandin secondary to placental loss result in the closure of the ductus. The pathology of PDA is due to the left-to-right shunting of blood from the aorta to the pulmonary artery. |
| Clinical History | This varies depending on the age of the initial presentation and the size of the PDA.
An older child or adult can present with shortness of breath and exercise intolerance. |
| Clinical Examination | Small PDA
Moderate PDA
Large PDA
|
| Diagnostic Investigations | Echocardiogram – visualisation of the defect and shunt.
Chest X-ray – normal if PDA is small, slight cardiomegaly if moderate, left heart enlargement if large. Ecg – normal if PDA is small, biventricular hypertrophy and left atrial anomaly if large. |
| Management | In adults, closure is often warranted if there is sizeable left-to-right shunting and/or pulmonary arterial hypertension. Often percutaneous closure is utilised with prophylactic antibiotics for six months. However, closure is contraindicated if the pulmonary vascular resistance is too high. In some cases, surgical ligation is used in larger PDAs. |
| Follow Up | Patient monitoring is required until the definitive closure of the PDA is attained. There are several complications which include congestive cardiac failure, pulmonary hypertension, and endarteritis. |
Table 5: This table details the main features of patent ductus arteriosus. Sourced and adapted from Johnson et al. Patent Ductus Arteriosus: BMJ Best Practice 2022 and Doyle et al. Clinical manifestations and diagnosis of patent ductus arteriosus (PDA) in term infants, children, and adults.: UpToDate; 2022.
Patent Foramen Ovale
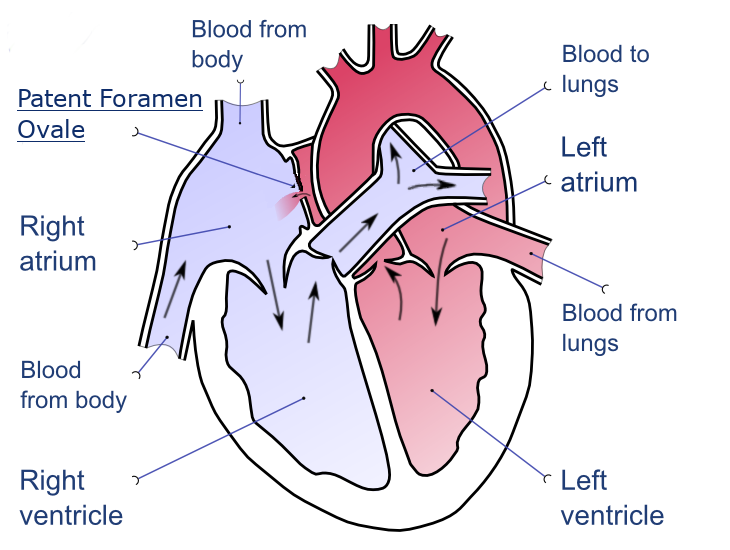
Image Source: Wikimedia Commons (2020). Patent Foramen Ovale, Licensed under a creative commons licence. Available for free at: https://upload.wikimedia.org/wikipedia/commons/0/0a/Patent-foramen-ovale-en.png?20201209214228 (Accessed 2 May 2025).
Patent Foramen Ovale (PFO) is a CHD in which the foramen ovale, located within the atrial septum, remains open into adulthood. Typically, in those without PFO, the foramen ovale closes due to raised left atrial pressure during the first breath after birth. PFO is often asymptomatic but can cause a cerebrovascular accident due to paradoxical embolism, i.e., venous to arterial transit of emboli. The key summary of PFO can be reviewed in Table Six.
| Feature | Summary |
|---|---|
| Epidemiology | Present in around 10% of patients having contrast echo. The incidence of PFO declines with age, suggesting that spontaneous closure can result in adulthood. |
| Aetiology | Idiopathic |
| Clinical History/Examination | Most patients are asymptomatic. However, one should exclude PFO in those under sixty and presenting with a cryptogenic stroke, sudden onset pain and coldness in any limb, transient ischaemic attack and where no obvious embolic source is identified.
Risk factors include atrial septal aneurysms and congenital heart defects. |
| Clinical Examination | In some instances, second heart sound splitting and a systolic murmur are noted on auscultation. |
| Diagnostic Investigations | A transthoracic echo with contrast and colour Doppler is used to visualise the passage of microbubbles from the right atrium into the left atrium. This is often when there is low clinical suspicion of PFO.
A trans-oesophageal echo with contrast and colour Doppler is used when a definitive diagnosis is required. |
| Management | If the individual is asymptomatic, then observation is often the main treatment. However, is it best to think of patients categories as per below:
Asymptomatic
Cryptogenic stroke or transient ischaemic attack Patient selection based on a MDT approach involving neurology and cardiology
High-risk professions, e.g. astronauts, pilots and deep-sea divers
|
| Follow Up | In small PFOs which are asymptomatic, then no long-term follow-up is required. In those with TIA or CVA, routine follow-up is required. A 6-month echo is required in patients who have undergone a percutaneous closure to confirm sufficient closure and rationalisation of antiplatelet treatment.
Prognosis is variable, dependent on the category of patient. In most, however, PFO is not correlated with a higher risk of death or stroke if medically treated. In those with CVA and/or TIA, the risk of a reoccurrence of CVA and/or TIA is 3x higher in PFO, and this increases to 6x higher in those with a concurrent atrial septal aneurysm. |
Table 6: This table provides an overview of patent foramen ovale. Sourced and adapted from Aggarwal, Patent Foramen Ovale: BMJ Best Practice 2022 and Hara, Patent Foramen Ovale: UpToDate; 2022.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

