


 Close
 7th May 2025
Obstructive Valvular and Non-Valvular Lesions
Coarctation of the Aorta
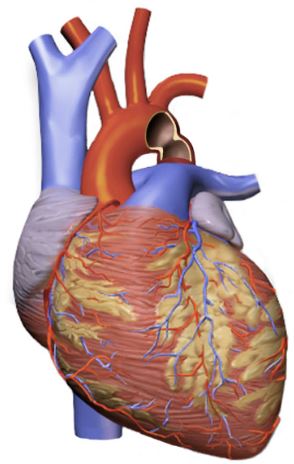
Image Source: Wikimedia Commons (2016). Coarctation Of Aorta, Licensed under a creative commons licence. Available for free at:
https://upload.wikimedia.org/wikipedia/commons/3/30/Coarctation_Of_Aorta.png?20160926151738 (Accessed 2 May 2025).
Coarctation of the aorta (CoA), or aortic coarctation, describes a vasculature abnormality with a narrowing of the descending aorta. Most often, this lesion is located distal to the left subclavian artery, i.e., the insertion site for the ductus arteriosus. A consequence of CoA is increased left ventricular pressure due to increased left ventricular outflow resistance. This syndrome is described in Table Eight.
| Feature | Summary |
|---|---|
| Epidemiology | Mostly sporadic
Prevalence of 4 in 10,000 live births and is more common in males Often associated with VSD and bicuspid aortic valve |
| Aetiology | Congenital manifestation is still not fully understood. However, two theories exist.
Genetics, e.g. Turner syndrome, DiGeorge Acquired presentation is rare but can be related to Takayasu arteritis |
| Classification | Several strategies exist, but they are commonly based on location
|
| Clinical History | In mild or moderate cases, patients are often asymptomatic. In severe cases, these present in the neonate when the ductus arteriosus closes and presents with shock, hypotension and cyanosis.
Potential features within a clinical history include:
|
| Clinical Examination | Reduced palpable pulses in the lower limbs
Difference in the upper and lower limb blood pressure Ejection systolic murmur – heard loudest in the left upper sternal border or back Male |
| Investigations | ECG – often normal, or may show left or right ventricular hypertrophy
CXR – features depend on the severity and age. It can be normal, have posterior rib notching (collateral vessel enlargement) or cardiomegaly (pulmonary venous congestion) Echocardiogram – definitive and will show a discrete thoracic aortic narrowing with a pressure gradient. |
| Diagnostic Criteria | This criterion allows for the deduction of the clinical severity of the CoA.
|
| Management | The main goal is a complete repair of the coarctation with no residual pressure gradient. The choice depends on the clinical presentation and severity.
Severe coarctation in the neonate requires prostaglandin E1 to maintain ductus arteriosus patency and then emergency surgical repair. Non-critical coarctation repair is dependent on the age of the patient. If less than one year, then surgical repair is often used. If older than one year, then surgical or percutaneous repair is utilised. If there is recurrent coarctation, then stent or balloon angioplasty is utilised. |
| Follow Up | Patients will require indefinite follow-ups with a suitable cardiologist.
Complications include treatment resistant hypertension resulting in coronary artery disease, cerebral aneurysm, aortic dissection, aortic pseudoaneurysm or coarctation recurrence. Prognosis is often excellent in those with isolated CoA but often will require life-long antihypertensive treatment and cardiology follow-up. In the context of other abnormalities, there is a higher risk of long-term complications. |
Table 8: The above table details the main findings regarding coarctation of the aorta, sourced and adapted from Gossett, Coarctation of the Aorta: BMJ Best Practice; 2023 and Hijazi, Clinical manifestations and diagnosis of coarctation of the aorta: UpToDate; 2023.
Pulmonary Stenosis
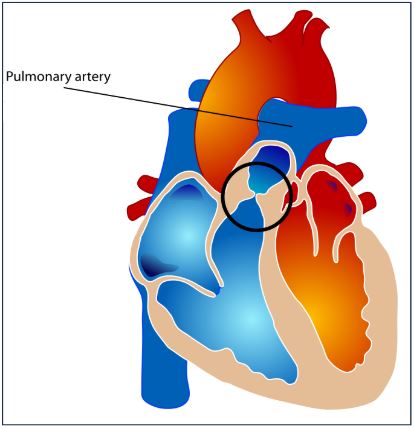
Image Source: Wikimedia Commons (2016). Pulmonary Valve Stenosis, Licensed under a creative commons licence. Available for free at:
https://upload.wikimedia.org/wikipedia/commons/thumb/7/7f/Pulmonary_valve_stenosis.svg/1232px-Pulmonary_valve_stenosis.svg.png?20070716043327 (Accessed 2 May 2025).
Pulmonary stenosis (PS) is an obstruction of blood flow from the right ventricle into the pulmonary vasculature. The obstruction results in a pressure gradient across the pulmonary valve of over 10mmHg during systole. Around 80% of cases are due to the pulmonary valve, but other variants can arise distally and proximal, and it is most commonly present in the context of other CHDs. The clinical picture is variable, ranging from asymptomatic to extreme cyanosis and even death. The main features associated with PS can be reviewed in Table Nine.
| Feature | Summary |
|---|---|
| Epidemiology | Present in 7% of all children with CHD
Occurs in more females |
| Aetiology | Most are congenital in nature
The key consequence of PS is increased right ventricular strain and pressure. In mild-to-moderate cases, patients are often acyanotic and without cardiac signs. However, in severe cases, right ventricular failure can result. |
| Classification | Often this is via the location of the obstruction
|
| Clinical History | Even without intervention, survival into adulthood is typical, but this can result in calcification and fibrotic changes of the pulmonary valve.
Mild-to-moderate cases are often asymptomatic. However, severe PS may report syncope on exertion, chest pain, exertional dyspnoea and fatigue. |
| Clinical Examination | Common examination findings include:
Dysmorphic features, e.g. Noonan, Williams |
| Investigations | ECG – normal (mild), right ventricular conduction delay and right axis deviation (moderate), right atrial enlargement and extreme right axis deviation (severe)
Chest X-ray – normal (mild or moderate), cardiomegaly/right ventricular or atrial enlargement (severe) Echocardiogram with Doppler – visualisation of valvular pathology and systolic pressure gradient |
| Management | Treatment of PS depends on the severity of the disease
|
| Follow Up | Outpatient monitoring for signs of progression (mild PS), but more frequent follow-up is needed in patients who have undergone a procedure.
Potential complications include pulmonary valve insufficiency after valvuloplasty, right-sided heart failure, and risk associated with valvuloplasty procedure. The prognosis is related to PS severity. In mild PS, even if untreated, survival is similar to that of the general population. In critical PS, if there is no intervention, then it is a terminal presentation in the neonate. In PS requiring surgical intervention, the outcome is impacted by younger age at the point of intervention, a higher initial pressure gradient and a high residual gradient. |
Table 9: The above table outlines the main features relating to pulmonary stenosis, sourced and adapted from Asnes and Keesham, Pulmonary Stenosis: BMJ Best Practice 2022 and Stout, Clinical manifestations and diagnosis of pulmonic stenosis in adults: UpToDate; 2021.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

