


 Close
 5th June 2025
Diagnosis
LcSSc and dcSSc both show the same signs and symptoms, but the skin distribution and course of the disease is different. Two thirds of patients with scleroderma have dcSSc, which has widespread skin involvement including proximal limbs. This is often rapidly progressive, has significant internal organ involvement and has a worse prognosis. One third of patients with scleroderma have lcSSc, where the sclerosis is limited to the digits, face and distal limbs (does not spread further than elbows or knees). It has a slower progression and less organ involvement, but carries a risk of pulmonary artery hypertension. Up to 20% of patients have an overlap syndrome with another connective tissue disease.
Systemic features
- Gastrointestinal: dysmotility, gastroesophageal reflux (GORD), dysphagia, bloating, nausea and vomiting, alternating diarrhoea/constipation
- Cardiopulmonary: interstitial lung disease (ILD), pulmonary artery hypertension, cardiomyopathy
- Renal dysfunction: patients may present with abrupt onset of moderate/marked hypertension, which is a sign of scleroderma renal crisis
- Musculoskeletal: friction rubs over joints and tendons, synovitis, weakness and limited movement causing contractures
- Ophthalmological: tight eyelids, reduced tear secretion, retinopathy
- Fatigue, arthralgia, myalgia
- Sicca symptoms and Sjogren syndrome
Cutaneous features
- Skin sclerosis, commonly sclerodactyly (hardening of the skin causing the fingers to curl inward) or microstomia
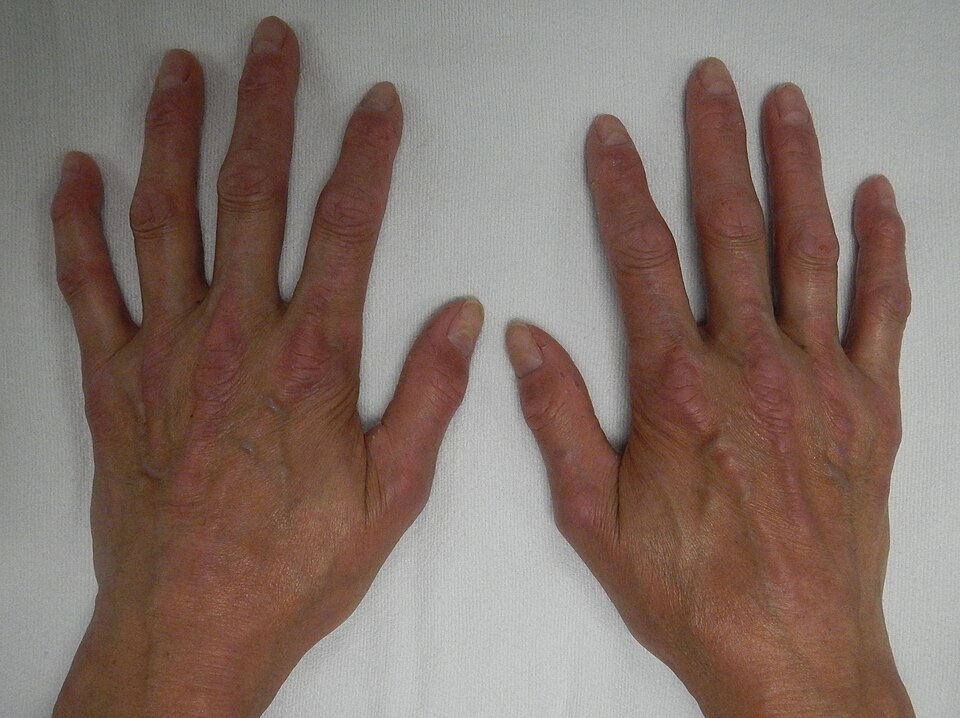 Image Source: Wikimedia Commons (2015). Crest 1, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:CREST1.JPG (Accessed 19 May 2025).
- Puffy hands, often one of the first symptoms
- Raynaud’s phenomenon
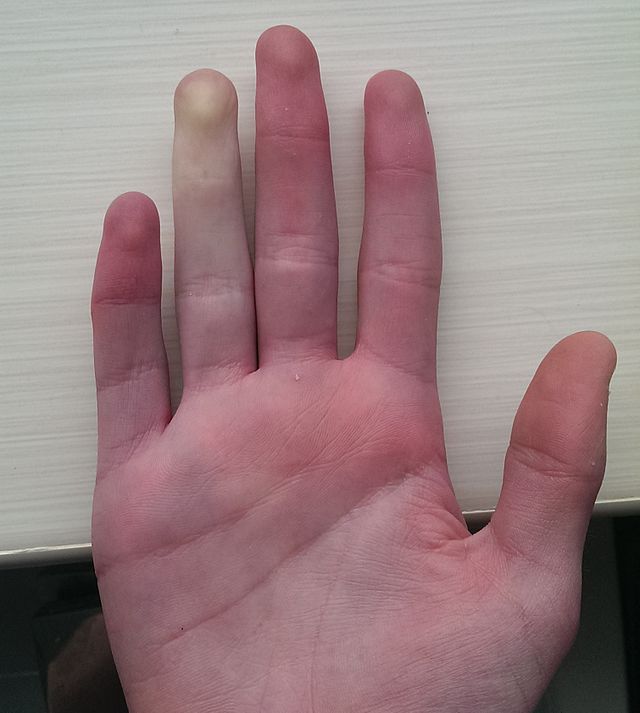 Image Source: Wikimedia Commons (2014). Raynaud Phenomenon, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/w/index.php?search=Raynaud%E2%80%99s+phenomenon&title=Special:MediaSearch&go=Go&type=image (Accessed 19 May 2025).
- Digital pits and/or ulceration
- Abnormal nail fold capillaries
- Telangiectases – often located on the face, hands and mucous membranes
- Subcutaneous calcinosis – small, hard masses on pressure points (eg. Fingers, forearms)
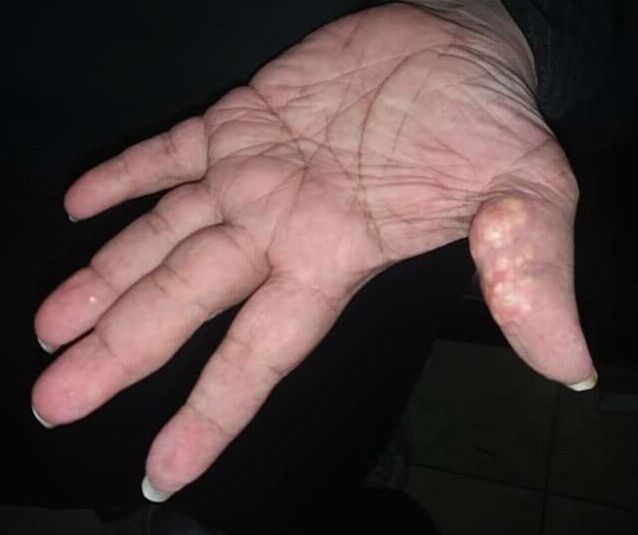 Image Source: Wikimedia Commons (2018). Calcinosis Cutis, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Calcinosis_cutis_new_image.jpg (Accessed 19 May 2025).
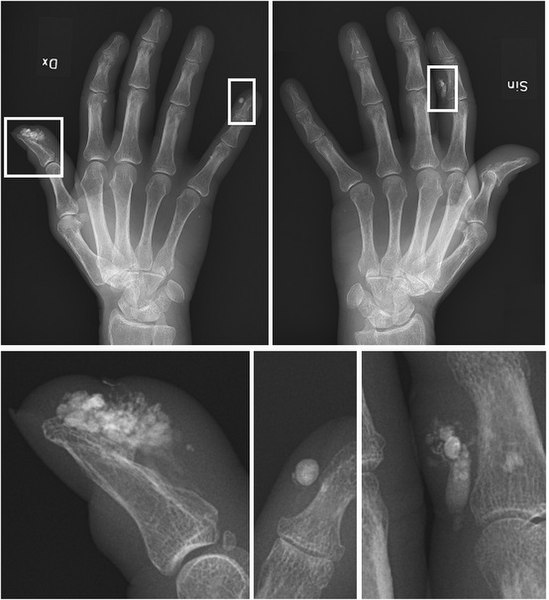
Image Source: Wikimedia Commons (2018). Calcinosis of Crest Syndrome, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Calcinosis_of_CREST_syndrome.jpg (Accessed 19 May 2025).
- Salt and pepper dyspigmentation – hyperpigmentation with vitiligo-like depigmentation
Though the previous name, CREST syndrome, of lcSSc is no longer used, it remains a useful mnemonic to remember the key features:
- Calcinosis
- Raynaud’s phenomenon
- (O)esophageal dysmotility
- Sclerodactyly
- Telangiectasia
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

