


 Close
 30th July 2026
Erythema Multiforme
Background
Erythema Multiforme (EM) is an immune-mediated hypersensitivity reaction affecting cutaneous and mucosal membranes. The condition is characterised by typical targetoid lesions with concentric rings that develop in a symmetrical acral distribution with mucosal involvement in a small number of patients. The majority of cases are triggered by herpes simplex virus (HSV), but other triggers exist including drugs and vaccinations. It is self-limiting but has a tendency to recur in 30% of affected patients. Although historically believed to be part of the same disease process that causes Steven-Johnsons Syndrome(SJS)/Toxic Epidermal Necrolysis (TEN) , emerging research has provided evidence to suggest EM is its own disease entity.
Epidemiology
The condition is relatively rare with an estimated annual incidence of 1%. EM has a male predominance of 3:2 and most commonly presents in the second and third decade of life. No association with race has been found. Specific HLA allotypes such as HLA-DQB1*0301 are thought to also increase risk of developing EM, particularly triggered by HSV.
Aetiology
The exact pathogenesis of EM remains unclear but the underlying mechanism is proposed to be a type IV hypersensitivity reaction caused by cytotoxic T cells. A number of different causes exist, summarised in the table below.
| Infectious | Medication-related | Other |
| HSV type 2 | Antibiotics | Inflammatory Bowel Disease |
| SARS-CoV-2 | Anti-epileptics | Hepatitis C |
| Orf | NSAIDS | Leukaemia |
| Vulvoginal candidiasis | Vaccinations | Lymphoma |
| Influenza virus | Malignancy | |
| Epstein-Barr Virus | ||
| Cytomegalovirus | ||
Table 1: Causes of erythema multiforme
Diagnosis
Classification
| EM Minor | EM Major |
|---|---|
| Affects < 10% of Total Body Surface Area | Affects > 10% of Total Body Surface Area |
| Acral distribution | Acral distribution |
| Target lesions | Target lesions |
| No mucocutaneous involvement | Involvement of 1 or more mucocutaneous sites |
Table 2: Classification of Erythema Multiforme
Clinical features
Target lesions eruption over 72 hours over the distal, extensor surfaces. Prodromal symptoms are rare.
Mucosal involvement includes oral blistering and genital ulceration. Symptoms usually heal within 2-3 weeks with minimal scarring although hyperpigmentation has been reported.
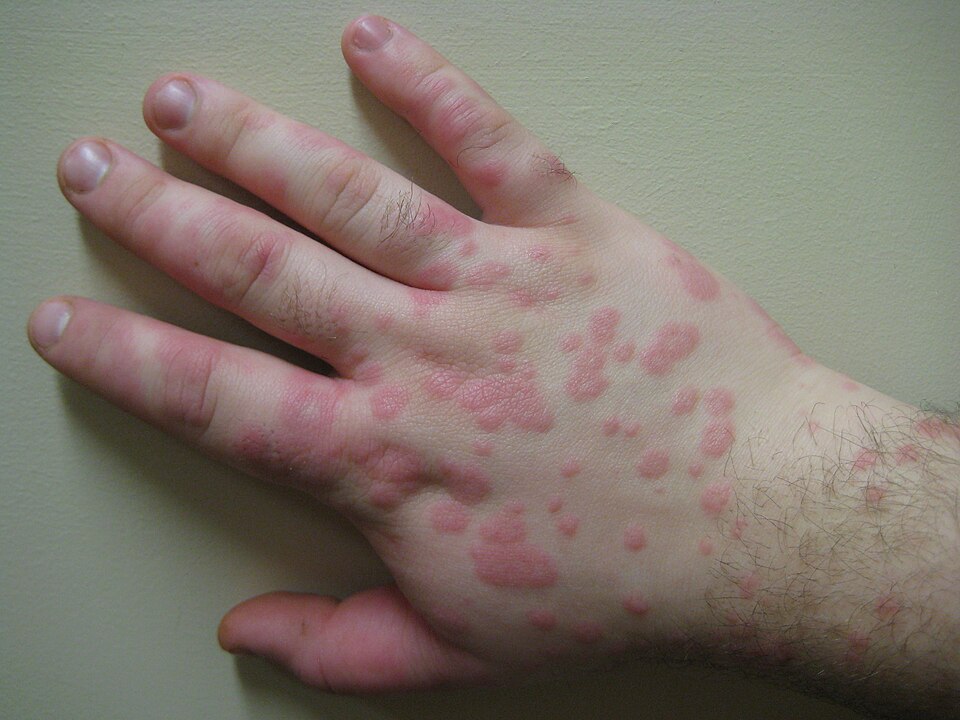
Target lesion on the dorsum of the hand.
Image Source: Wikimedia Commons (2009). Erythema Multiforme Minor of the Hand, Licensed under a creative commons licence. Available for free at https://commons.wikimedia.org/wiki/File:Erythema_multiforme_minor_of_the_hand.jpg (Accessed 19 May 2025)
Differential Diagnosis
- Rowell’s syndrome (targetoid lesions in Systemic Lupus Erythematosus)
- Pemphigus Vulgaris
- Urticaria
- Polymorphous light eruption
- Steven Johnson’s syndrome/Toxic Epidermal Necrolysis
- Paraneoplastic pemphigus
Investigations
- Full blood count
- Urea & electrolytes
- Liver function tests
- HSV serology and other infectious disease serology
- Chest X-ray: to look for evidence of mycoplasma pneumoniae as a cause of EM
- Skin biopsy: upper dermal oedema and epidermal keratinocyte necrosis.
- Biopsy is not usually required however may be considered to differentiate from other serious skin reactions.
Medical management
- Omit offending agent or treat the underlying cause
- Emollient
- Prednisolone/methylprednisolone
- Analgesia
- Ocular involvement requires ophthalmology review
- Recurrent disease: 6 months of anti-fungal treatment (vanciclovir/aciclovir) whether or not a clear trigger has been identified.
Complications
- Microstomia secondary to lip scarring
- Secondary bacterial infection
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

