


 Close
 14th July 2026
Background
Basal cell carcinoma (BCC) is the most common carcinoma worldwide. Typical presentation is a pearly white/pink papulo-nodule or plaque. Usually locally aggressive, with metastasis being rare. Management is usually with surgical excision, with low recurrence rates.
Epidemiology
The most common malignancy of the skin with increasing incidence. Incidence in the United Kingdom is thought to be around 110 per 100,000 people.
Aetiology
Frequent and repetitive exposure to the sun is a well-known risk factor, as UV radiation leads to DNA damage of keratinocytes. Other risk factors include exposure to arsenic. BCC arises from pluripotent cells in the epidermis and follicular epithelium. A background of xeroderma pigmentosum, Gorlin-Goltz syndrome (nevoid basal cell carcinoma due to mutations in the PTCH1 tumour suppressor gene) or solid organ transplantation also increases risk for BCC. BCCs arise from pluripotent cells in the epidermis and follicular epithelium. It is thought that both p53 gene mutations and aberrant activation of the Sonic Hedgehog signalling cascade contribute to the development of BCCs.
Diagnosis
A biopsy is needed in order to differentiate subtype, which will impact treatment.
Classification:
- Nodular: most common form of BCC, a pearly white nodule with telangiectasia on surface
- Superficial: poorly defined margins. Dermoscopy reveals short fine telangiectasia, maple leaf areas, without grey/blue ovoid nests
- Micronodular: typically appears as multiple small nests in the dermis, with an increased risk of recurrence
- Metatypical: squamous differentiation
- Morpheaform/infiltrating/sclerosing: similar to plaques of morphea (scleroderma), poorly defined margins, perineural invasion common
- Infundibulocystic: stimulates trichoepithelioma, composed of mitotically active hyperchromatic blue cells
- Mixed: mixture of two or more of the above types of BCC
- Periocular: slow growing, painless and non-resolving, presents as a small white nodule on the eyelid
Typically presents as pearly papules +/- plaques, non-healing scars, nodules/plaques with rolled borders and papules with telangiectasias.
Investigations
Dermoscopy findings include arborising telangiectasia, focal ulceration, shiny white/red structureless areas, short white streaks/lines under polarised light, blue-grey ovoid nests, and leaf-like areas (Figure 3).
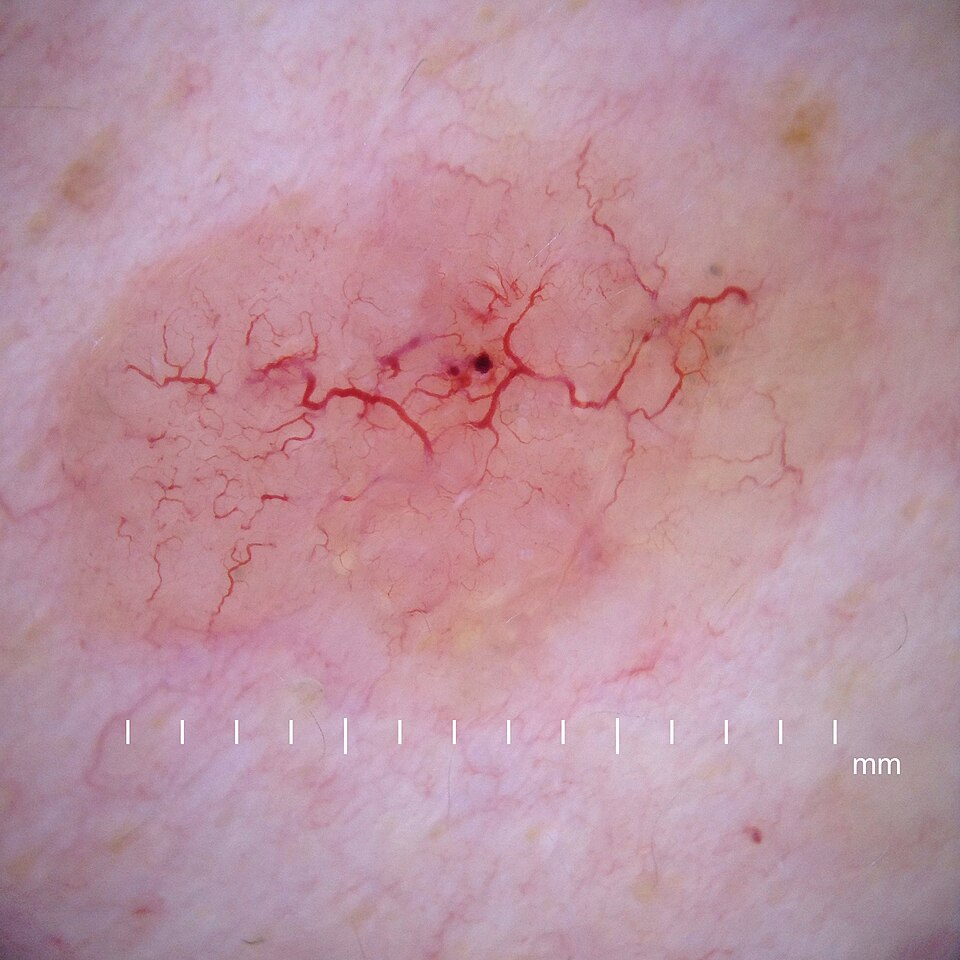
Dermoscopy of BCC
Image Source: Wikimedia Commons (2020), ECG AVNRT, Licenced under a creative commons licence. Available for free at: https://en.wikipedia.org/wiki/Basal-cell_carcinoma#/media/File:Dermoscopy_nodular_basal_cell_carcinoma.jpg (Accessed: 20 May 2026).
Either a shave or punch biopsy should be performed to confirm diagnosis. Punch biopsy is typically used in non-challenging cosmetical areas, as closure with stitches is usually required.
Histopathology shows proliferation of basal cells, well-defined linear and branching serpentine vessels, basophilic (blue) hyperchromatic ovoid nests, blue-grey globules and spoke wheel areas (Figure 4).
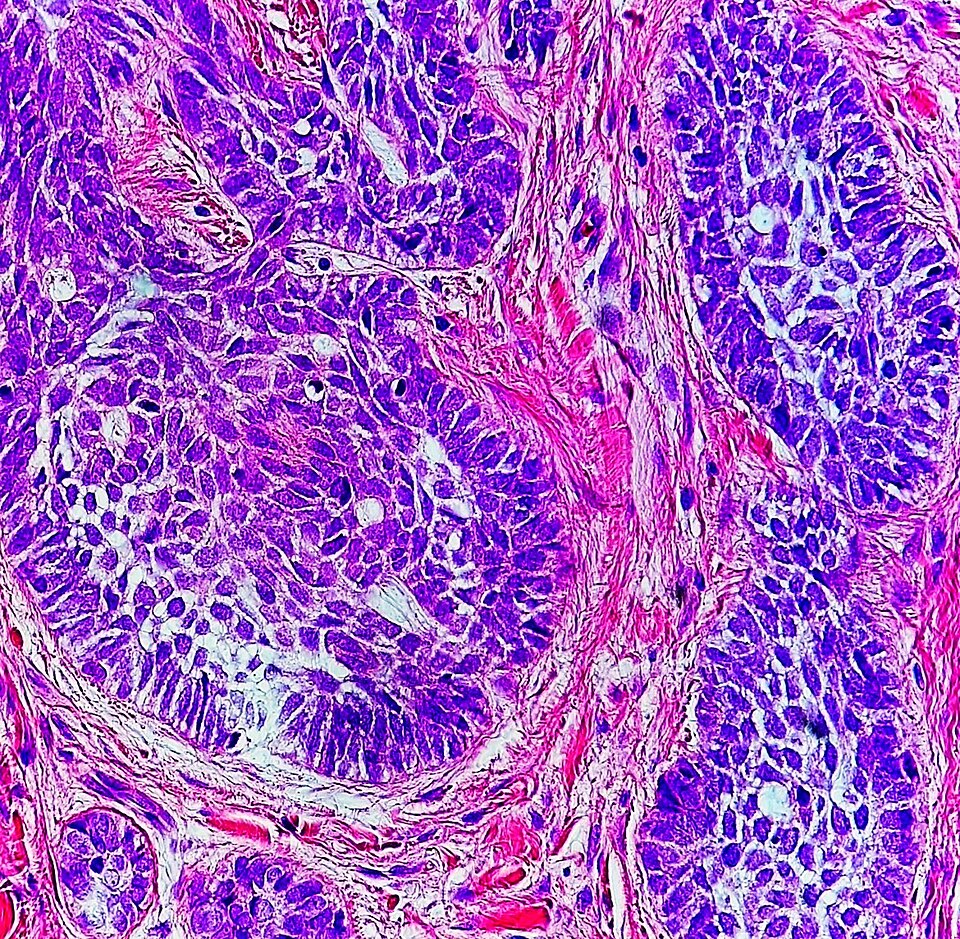
Histology of BCC
Image Source: Wikimedia Commons (2020), ECG AVNRT, Licenced under a creative commons licence. Available for free at: https://en.wikipedia.org/wiki/Basal-cell_carcinoma#/media/File:High-magnification_micrograph_of_basal-cell_carcinoma.jpg (Accessed: 20 May 2026).
Medical management
Low risk:
- Cryosurgery: effective for superficial variants
- Topical 5% imiquimod, a toll-like receptor-7 agonist chemotherapy agent, can be used in patients with superficial basal cell carcinoma. This is thought to result in an inflammatory response to BCC via induction of interferon alpha. The treatment course is five times a week for six weeks.
Sites not amenable to surgery: radiotherapy
Metastatic disease:
- Hedgehog pathway inhibitors: vismodegib and sonidegib
Surgical management
Surgery is the mainstay of treatment to ensure complete removal and prevent recurrence.
Low risk:
- Non-cosmetically challenging: excision or curettage +/- electrodesiccation and biopsy
- Cosmetically challenging (e.g., head and neck): Mohs surgery
High risk:
- Mohs surgery
Complications
Low likelihood: lymph node spread, distant metastasis
Medium likelihood: local spread of BCC
References
- https://bestpractice.bmj.com/topics/en-gb/269/pdf/269/Basal%20cell%20carcinoma.pdf
- https://www.ncbi.nlm.nih.gov/books/NBK1133/
- https://www.ncbi.nlm.nih.gov/books/NBK430921/
- https://www.uptodate.com/contents/treatment-and-prognosis-of-basal-cell-carcinoma-at-low-risk-of-recurrence
- https://patient.info/doctor/basal-cell-carcinoma
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

