


 Close
 3rd June 2026
Diseases of the arteries
Atherosclerosis
Atherosclerosis is a chronic inflammatory process caused by an accumulation of plaque materials made up of lipids and connective tissue matrix proteins. These lipoproteins are deposited and retained in the subintimal space of blood vessels, secondary to loss of endothelial structure. As these retained plaques harden over time, they cause narrowing of the opening of the arteries and restricted blood flow. As the plaques rupture, there can be formation of thrombosis, leading to possible complications such as myocardial infarction (MI), unstable angina or cardiac death.
Atherosclerosis is the underpinning mechanism of coronary artery disease (CAD), peripheral arterial disease (PAD) and cerebrovascular disease, depending on which arteries are affected.
Cardiovascular disease is the leading cause of death in the UK, with atherosclerosis as the main underlying cause, specifically accounting for roughly 50% of all cardiovascular events that occur. Atherosclerotic cardiovascular disease (ASCVD) had a prevalence of 6.58% in England in 2022 and 8.26% in Northern Ireland.
Epidemiology
Modifiable factors include:
- Hypertension
- Hyperlipidaemia (specifically high LDL, low HLD)
- Smoking
- Diabetes
- Obesity
- Excess alcohol
- Chronic Kidney Disease (CKD)
- Presence of implantable cardiac devices
- Chronic haemodialysis
Non-modifiable factors include:
- Male sex
- Age
- Genetics (e.g familial hypercholesterolaemia)
- Inflammatory conditions
- Autoimmune conditions
Aetiology and Pathophysiology
The underlying mechanism of atherosclerosis is one of endothelial dysfunction. Damage is undertaken on the intima, which may be caused by stress at vessel bifurcations. This endothelial damage leads to a decrease in the bioavailability of nitric oxide and an increase in the amount of reactive oxygen species that are produced. This is made worse by factors such as dyslipidaemia and hypertension.
LDL cholesterol moves into the arterial wall at the site of the damage, leading to formation of a fatty streak as macrophages cross the endothelium to enter the subintimal space. Smooth muscle cells follow and collagen proliferates, leading to a plaque/ fibrous cap developing. A necrotic core develops within the plaque, containing oxidised cholesterol, secondary to the foam cell accumulation.
The plaque growth not only narrows the arterial lumen, leading to restricted blood flow and ischaemia, but also risks rupture, in turn leading to blood clot formation. These clots can then lead to life-threatening conditions such as MIs, Transient ischemic attacks (TIAs) and ischaemic strokes.
Table 1. The 3 stages of atherosclerosis summarised
| Stage of plaque formation | |
|---|---|
| 1. Lipid-streak formation | Lipids are retained in the arterial wall. Macrophages will move into the intimal wall and bring in excess amounts of lipids. This leads to foam cell formation. |
| 2. Fibrous plaque formation | Smooth muscle cells move into the intimal arterial wall and lead to the fibrous cap being built. Further accumulation of foam cells initiate necrosis inside the plaque. |
| 3. Thrombosis and further lesions | As the core of necrosis grows, the cap will disappear. The substances making up the core will interact with coagulation cells and can lead to thrombosis. |
Key features of an atherosclerotic plaque are:
- Proliferation of macrophages, fibroblasts and smooth muscle cells
- Deposition of lipids
- High levels of collagen
- Necrosis
Once a certain vascular territory is damaged by atherosclerosis, the total risk for any CV event is much higher, as well as in the organ that is damaged by the compromised blood flow.
Diagnosis
The diagnosis of atherosclerosis can be made based on a thorough medical history, including risk factors (family history and lifestyle, etc.), physical examination, blood tests, and imaging.
History
- Any previous atherosclerotic conditions, e.g., cerebral vascular disease?
- Any risk factors for atherosclerotic disease, e.g., hypertension, smoking
- Family history of any coronary events, especially at a young age.
Clinical examination
- Xanthomata – Yellow raised deposits on the skin, usually around the tendons, knuckles, elbows, and ankles. These are an indication of familial hypercholesterolaemia.
- Xanthelasma – Yellow raised deposits that appear around the eyelids
- Corneal arcus – Grey ring that forms around the cornea edge. Associated with ageing, however, if present in younger patients may be a sign of familial hypercholesteremia.
- Buerger’s test – Tests for arterial insufficiency, which may be present secondary to atherosclerosis. It involves raising the feet of the patient and supporting them at 45-degrees for 2 to 3 minutes. Look for developing pallor to indicate draining of the blood from the peripheries. Then sit the patient up with their legs over the side of the bed, watching for reactive hyperaemia (positive test). The feet will have a delay in return of colour and will be a dusky red.
- Diminished pulses over the posterior tibial pulse and dorsalis pedis pulse — may indicate PAD.
- Bruits on auscultation of pulses (peripherally, carotids, renal arteries) – may indicate stenosis of arteries
- Colour changes to peripheries.
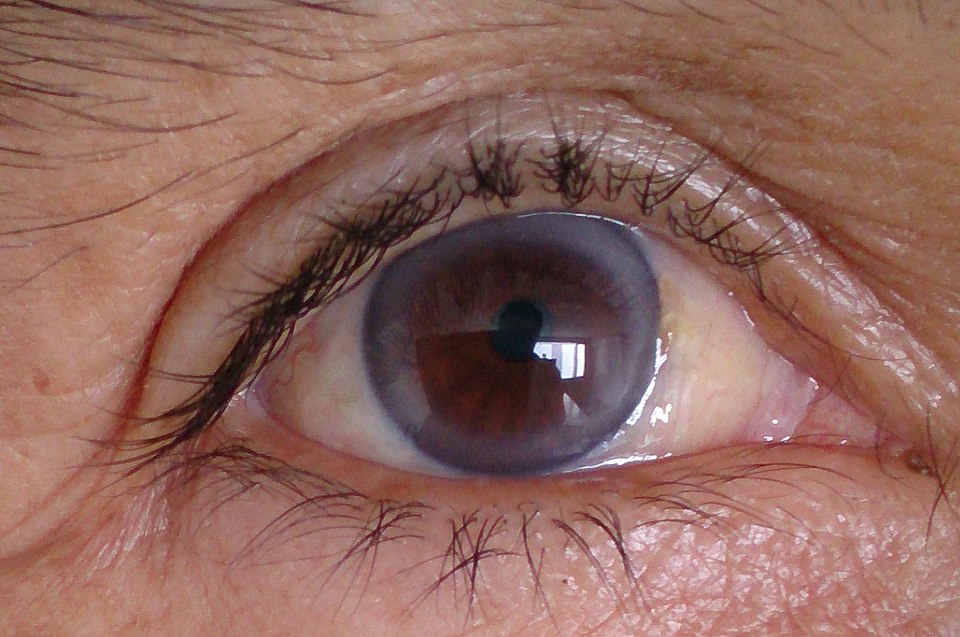
Corneal arcus
Image source: Wikimedia Commons (2020), ECG AVNRT, Licenced under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Arcus_Senilis_(cropped).jpg (Accessed: 27 April 2026)
Clinical Manifestations
Atherosclerosis can manifest in different clinical conditions/signs depending on which vessels the deposits are situated in, and how much blood flow is restricted.
- Carotid artery disease – Altered mental status, bruits over carotid arteries, may be asymptomatic until a stroke or TIA occurs.
- Stroke/ TIA – Sudden onset of neurological symptoms, e.g., hemiparesis or hemisensory symptoms, ataxia, vertigo, altered mental status, vomiting, dysarthria, dysphagia. TIA symptoms completely resolve in 24 hours.
- Coronary heart disease – chest pain at rest or activity, neck/shoulder/arms/ jaw radiation, dyspnoea, syncope, palpitations
- Peripheral arterial disease – pain on movement in legs and buttocks (usually bilateral but can be unilateral), parasetheisa in legs, hair loss on legs and feet, non-healing ulcers, blue discolouration of feet
- Mesenteric artery ischaemia – abdominal pain that is acute and severe, usually starting about 30 minutes after eating, nausea, vomiting, diarrhoea.
- Erectile Dysfunction
- Renal artery stenosis – Hypertension that can be difficult to treat, worsening kidney function, and flash pulmonary oedema.
Investigations
Risk Assessment:
- Assessment of CVD risk is undertaken depending on previous risk factors. This is followed by a full formal risk assessment if the patient’s estimated 10-year risk of CVD is 10% or more.
- The QRISK3 tool is used to calculate the estimated CVD risk for people aged between 25 and 84 without existing CVD over the following 10 years.
- You cannot use QRISK scores for patients with T1DM, CKD (eGFR <60) or familial hypercholesteremia.
Blood tests:
- Lipid profile (Total cholesterol, HDL- C, LDL-C, triglycerides) – a non-fasting sample is required
- Non-HDL cholesterol – This can give a more accurate estimate of cardiovascular risk with non-fasting samples
- LFTS – To assess liver function before statin initiation
- Glucose and HbA1c
- Renal function (eGFR, creatinine, us&es) – to assess for reduced renal function secondary to atherosclerosis, for dosing of statins and risk stratification
- TSH – To exclude hypothyroidism as a secondary cause of hyperlipidaemia
- Genetic testing of Lipoprotein (a) – may be undertaken if there is a history of familial hypercholesteremia
Imaging:
- Coronary Artery Disease
- Coronary angiography (Gold standard) – especially if intervention (PCI/CABG) is likely
- CT Coronary Angiography – Has the benefit of being non-invasive, and is the first-line investigation in outpatient cardiology or chest pain clinics.
- CT calcium scoring – A non-invasive test that provides a calcium score regarding the exact location and degree of plaque that is calcified on the coronary arteries.
- Stress testing – myocardial perfusion scan, stress echocardiograms
- ECG – To look for evidence of a prior MI
- Cerebrovascular Disease
- Carotid duplex ultrasound – to assess for stenosis in stroke/TIA patients
- Transcranial Doppler (TCD) — non-invasive and portable, uses a Doppler transducer to evaluate blood flow within major cranial arteries
- CT angiography of carotids for pre-operative planning
- Non-contrast CT
- MRI
- Peripheral Arterial Disease
- Ankle-Brachial Pressure Index (ABPI)
- Normal: 1-1.4; PAD <0.9 : Critical limb ischaemia: <0.5
- Duplex ultrasound – first line when assessing stenosis
- CT angiogram or conventional angiography – when considering revascularisation
- Ankle-Brachial Pressure Index (ABPI)
Medical management
Lifestyle interventions
Lifestyle change support, such as weight management and smoking cessation should be offered before commencement of medication in primary prevention.
If managing secondary prevention, lifestyle measures should be discussed alongside initiation of treatment.
Risk factor control
Blood pressure: Target BP <140/90mmHg in low risk. Target BP should be 130/80mmHg in high-risk patients (established atherosclerosis, CKD, diabetes).
Glycaemic control: Aiming for a fasting glucose <6mmol/L and HbA1c of less than 6.5%
Antiplatelet therapy: If patients have known peripheral or coronary disease caused by atherosclerosis, then aspirin 75mg OD should be considered, with clopidogrel as a second-line choice. Aspirin should not be considered in primary prevention, as the risk of GI bleeding outweighs the benefits.
Pharmacological Management
Lipid-lowering agents such as Atorvastatin 20mg are used for primary prevention if QRISK3 > or equal to 10%. The latest guidance from NICE advises to ‘not rule out’ those with a QRISK score of less than 10% for treatment. Atorvastatin 80mg is used for secondary prevention regardless of cholesterol level.
Repeat lipid levels and LFTS must be checked in 3 months of starting a lipid-lowering agent, then annually. Non-HDL cholesterol targeted with greater than or equal to 40% reduction for primary prevention. Non-HDL target is ≤ 2.6mmol/L or LDL target is ≤ 2.0 mmol/L for secondary prevention.
Clinicians should increase the dose of the statin if these are not met, and the patient agrees. If the target level is still not achieved post an increase in dose, Ezetimibe 10mg OD can be added in.
If target is still not achieved, newer lipid-lowering agents (PCSK9 inhibitors or inclisiran) may be added in, however, these may need to be discussed with specialist care.
Please see (Williams et al., 2024) for a summary of the NICE guidelines regarding primary and secondary prevention.
Surgical/ Interventional management
Coronary Artery Disease
- Percutaneous Coronary Intervention (PCI) – Utilised in acute coronary syndrome (ACS) or for angina not controlled by medical therapy
- Coronary Artery Bypass Grafting (CABG) – Utilised when plaques block coronary arteries, usually in complex blockages, unstable or uncontrolled angina. It involves bypassing the blood flow with arterial or venous conduits. The most commonly used vessel for a conduit is the left internal thoracic artery (ITA) due to its patency over long time periods. The radial artery and saphenous vein are also used frequently, however may be less patent in the long term.
Carotid disease
- Carotid Endarterectomy (CEA) – This involves the removal of cholesterol deposits and clots in the artery wall. Utilised for symptomatic carotid stenosis above 70%, however may be beneficial for patients with 50-69% stenosis. When performed in asymptomatic stenosis, the risk of any stroke is reduced by 30% over the next 3 years.
- Carotid Stenting – Utilised if there is severe stenosis plus co-morbidities, high surgical risk or contraindications to endarterectomy.
Peripheral Arterial Disease
- Treatment depends on severity.
- Angioplasty or bypass surgery – if there are persistent symptoms or critical limb ischaemia
- Amputation – In non-reconstructable ischaemia or severe infection
Complications
As discussed above, complications of atherosclerosis are dependent on which vessels the plaques are found in.
- Neurological – Ischaemic stroke, TIA, vascular dementia
- Cardiac – Myocardial infarction, heart failure, arrhythmias, angina
- Peripheral – Ulcers, claudication, critical limb ischaemia, gangrene, limb loss
- Renal – CKD, Renovascular hypertension
- Abdominal – Abdominal aortic aneurysms, mesenteric ischaemia
Aortic dissection
An aortic dissection is classified as an acute aortic syndrome (AAS) that occurs when there is a tear in the intimal layer of the wall of the aorta, leading to blood flowing into the space between the Tunica media and the Tunica intima, separating these layers. This creates a false lumen, which then reduces blood flow to organs, often leading to ischaemia of organs, branch occlusion, aortic regurgitation, cardiac tamponade or rupture of the aorta. The dissection may spread proximally or in a retrograde direction.
Although it is not a common condition, it has a high mortality rate of 10-35%, with the highest period of mortality in the first 10 days. The reported annual incidence of acute aortic dissection (AAD) is 3-4 cases per 100,00 in the UK.
Aortic dissection can be classified in several ways, with the Stanford classification (Type A and B) most commonly used to determine the management plan. Depending on the staging, treatment may be medical or surgical, and will always require prompt recognition and imaging to initiate treatment either way.
Epidemiology
Risk factors (For non-traumatic dissection)
- Hypertension (present in 70% of all cases) – causes weakening of the tunica media
- Atherosclerosis
- Aortic aneurysm
- Substance use (leading to a sudden increase in blood pressure) – e.g: cocaine use, ecstasy use, energy drinks
- Pain or emotional stress (leading to a sudden increase in blood pressure)
- Giant cell arteritis (GCA)
- Genetic conditions including: Marfan syndrome (estimated to be in 50% of cases where patients are under 40), Ehlers- Danlos syndrome, Turner syndrome, Bicuspid aortic valve, and coarctation of the aorta
- Atherosclerotic aneurysmal disease
- Family history of aortic disease
- Pregnancy and delivery of the baby
- Aortic surgery – e.g: CABG, valve replacements (mitral or aortic), stent or catheter insertion
- Male sex
- Age of 50-70 years old
Aetiology
For an aortic dissection to occur, there must be medial degeneration alongside mechanical wall stress.
Medial wall degeneration: Likely due to loss of elastic and interconnecting elastic fibres, associated with damage to the vasa vasorum. This damage leads to an entry site for the false lumen. Precipitants to medial wall degeneration include hypertension, connective tissue disorders and aortic aneurysms.
Chronic hypertension changes the composition of the arterial wall by causing a thickening of the intimal layer via fibrosis and calcification. This thickening will lead to compromised nutrient and oxygen supply to the wall of the artery, alongside fibrosis obstructing vessels that supply the wall and the vasa vasorum. This will lead to necrosis of the elastic structures and smooth muscle cells in the wall, leading to a rigid wall unable to tolerate pulsatile forces, and therefore creating an easy area for aneurysms and dissections to occur.
Mechanical aortic wall stress > Caused by sheer stress from blood flow, alongside hypertension.
The 3 ways that blood may enter the media space are: through an atherosclerotic ulcer, which leads to a tear, via an intramural haematoma from damage to the vasa vasorum and via a new (de novo) intimal tear. Most tears occur in the ascending aorta because it is nearer to the outflow from the left ventricle, leading to high pressure on the aortic wall.
Often, the true lumen of the blood vessel will decrease in size due to compression from the blood flow through the false lumen. Dissection can also occur without an initial tear.
Investigations
Bloods
- FBC
- Us&Es
- LFTs
- Coagulation profile
- Troponin – If there has been a MI secondary to the dissection this may be raised
- Lactate – A raised lactate can indicate tissue ischaemia
- Group and save
- Crossmatch
- D-dimer – This will be elevated in most cases. Whilst a negative result significantly lowers the likelihood, it does not exclude a dissection.
- ABG
- Smooth muscle myosin heavy chain
Imaging
- ECG – Common to see ischaemic changes on an ECG and may mimic an MI in up to 40%. Roughly 30% of ECGs can be normal in an acute dissection.
- CXR – About 60% show a widened mediastinum (>8cm). It may also show an abnormal aortic contour, a globular heart (haemopericardium) or pleural effusion (L>R), which represents a haemothorax. A CXR may be normal in confirmed aortic dissection.
- CT angiography (whole aorta) – Gold standard and first-line in an acute setting. Sensitivity is 95-100%, and it is quicker than an MRI. However unable to assess for AR or LVF. Two lumens are identified with a visible intimal flap for diagnosis. An initial tear may be visualised and evidence of aortic dilatation or acute rupture. Any poor perfusion of end organs will also be seen.
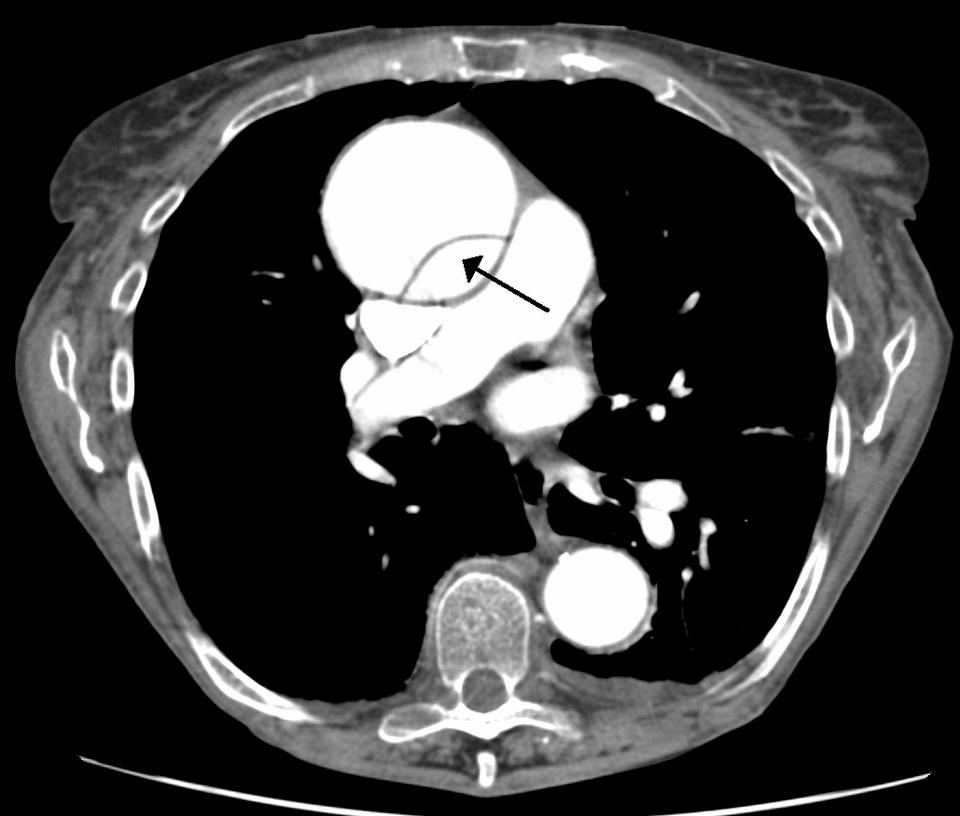
CT scan showing a dissection of the ascending aorta with an arrow pointing to the false lumen
Image Source: Wikimedia Commons (2020), ECG AVNRT, Licenced under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:DissectionCT.png (Accessed: 27 April 2026)
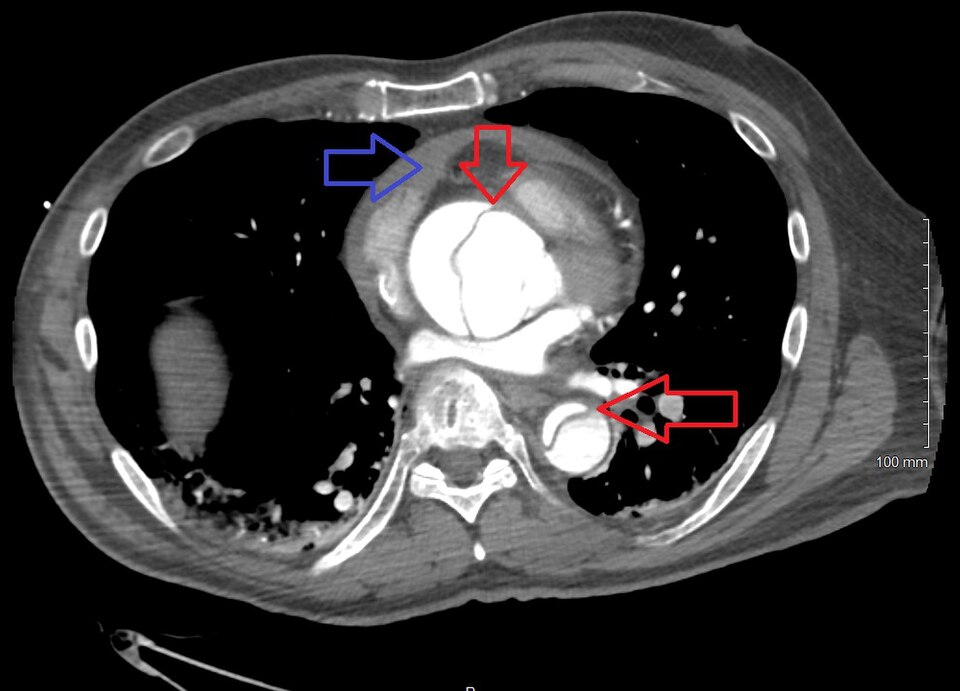
CT showing a Type A dissection with a pericardial effusion as a result. Red arrows show the ascending and descending thoracic aorta. The blue arrow highlights the pericardial effusion.
Image Source: Wikimedia Commons (2020), ECG AVNRT, Licenced under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Dissection2018WithPericardial.jpg (Accessed: 27 April 2026)
- Transthoracic echocardiogram (TTE) – Useful for identifying complications such as cardiac tamponade or aortic regurgitation. Poor sensitivity for type B dissections. Useful as an adjunct to CT.
- Transoesophageal echocardiogram (TOE) – Can be undertaken at the bedside. TOE has a sensitivity of roughly 98% and can easily view the extent of dissection.
- Magnetic resonance angiography (MRA) – High sensitivity, however, limited by its availability and difficulties in continuous monitoring whilst undergoing the MRA.
The Aortic Dissection Detection Risk Score (ADD-RS)
The ADD-RS is a risk stratification tool to assist with the low-to-moderate risk patient where a diagnosis of acute aortic dissection is suspected.
Low risk – score of 0, intermediate risk if the score is 1, and high risk if the score is >1.
A higher risk score indicates a higher likelihood of aortic dissection
Table 2: ADD-RS Scoring Criteria
| Clinical history | Points | |
|---|---|---|
| Anyone with these high-risk conditions | Family history of aortic disease, Marfan syndrome, known thoracic aortic aneurysm, Recent aortic manipulation, known aortic valve disease | +1 |
| Anyone with these high-risk pain features | Chest, abdominal or back pain that is described as: 1. Abrupt onset or 2. Severe intensity or 3. Tearing/ripping in nature | +1 |
| Anyone with these high-risk examination features | New murmur of aortic insufficiency (with any pain associated), hypotension or shock, Evidence of perfusion deficit | +1 |
Diagnosis
History
Typically, an aortic dissection presents with sudden onset of ‘tearing’ abdominal, back or chest pain. However, we must be aware of atypical symptoms as these can often lead to a missed diagnosis, and if no treatment is provided within 48 hours of initial symptom onset, then mortality rates reach up to 50%.
Key diagnostic features
- Sudden onset severe chest pain/ retrosternal (anterior dissection) / interscapular (descending aorta) or lower back pain – described as ‘sharp’ or ‘tearing’ and is a maximal pain level at onset.
- Sudden onset abdominal pain – can occur with dissection; however, more likely to be a ruptured AAA
- Radiation of the pain to the jaw, neck or throat
- Pain that migrates (highly specific for AAD) – starts where the initial tear is present and is associated with where the tear continues to e.g: starting in the back and moving to the legs, may be due to common iliac or external iliac involvement.
- Pain that stops quickly – If the process halts or if a re-entry tear is created into the true lumen.
- Some patients (5-15%) present with no pain! (see points below)
- Syncope – If a patient presents with syncope, they may not feel the initial pain associated with the tear
- Seizures
- Stroke – As the primary tear occurs, there is instantaneous neurological deficit, so no pain is felt. It is important to consider if a patient becomes dysphasic, they won’t be able to highlight pain.
- Dyspnoea
- Haemoptysis
- Altered mental status
- Paraplegia/ limb paraesthesia – typically painless due to occlusion of the origin of spinal arteries
- Limb pain or weakness
- Flank pain
*Consider an acute aortic dissection if symptoms include chest/back pain AND new or evolving neurological deficit.
Key examination features
An A-E examination must be undertaken, including a full cardiovascular and abdominal examination.
Measuring blood pressure in both upper limbs should be performed if AAD is suspected.
- Hypertension
- Asymmetrical pulses and readings of blood pressure – A difference of >20mmHg between each limb
- Aortic regurgitation
- Shock – hypovolaemia, tamponade
- Acute abdomen symptoms (if mesenteric/coeliac artery affected)
- Acute heart failure symptoms – caused by sudden aortic annular dilatation with acute aortic regurgitation (severe) or dissection of the coronary artery with vessel occlusion leading to shock (Cardiogenic).
- Neurological deficits – reduced power/weakness in limbs, paraesthesia, Horner’s syndrome
- Haemothorax
Constellations of symptoms may suggest the following:
- Haemopericardium: Absent or faint heart sounds, pulsus paradoxus, distended neck veins and the presence of shock.
- Branch vessel occlusion: Weak central or peripheral pulse unilaterally, >20mmHg difference in BP in each arm, bruit or palpable thrill over any pulse or the abdominal aorta, neurological deficit or stroke features
Aortic dilatation: Diastolic murmur heard over aortic valve area, a wide pulse pressure –
Classifications
Stanford
- Stanford Type A – A tear that involves the ascending aorta, even if it starts elsewhere. It is proximal to the brachiocephalic artery.
- Stanford Type B – A tear that involves the descending aorta only. Its origin is distal to the left subclavian artery.
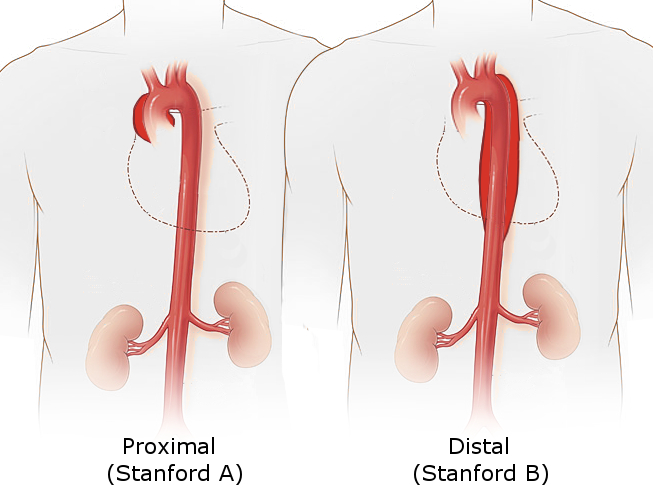
Figure 4: Stanford classifications of dissection
Image Source: Wikimedia Commons (2020), ECG AVNRT, Licenced under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Aortic_dissection_types.jpg (Accessed: 27 April 2026)
DeBakey
- DeBakey Type 1 – A dissection that involves the whole aorta – originating either in the ascending, arch or descending areas.
- DeBakey Type 2 – A dissection that originates in and involves only the ascending aorta/arch.
- DeBakey Type 3 – A dissection that originates in the descending aorta.
- 3a – Extends to above the diaphragm, and either proximal or distal to the left subclavian artery.
- 3b – Extends to below the diaphragm, and distal to the left subclavian artery.
Svensson
This classification has been developed more recently to include aortic ulcers, intramural haematomas and iatrogenic causes.
- Class 1 – A flap is created between the false lumen and true lumen – A ‘classic’ dissection.
- Class 2 – Caused by an intramural haematoma.
- Class 3 – A limited dissection with a bulge at tear site, and no haematoma.
- Class 4 – A atherosclerotic penetrating ulcer with a haematoma surrounding it.
- Class 5 – Traumatic or iatrogenic dissection.
Classification by timeframe
- Hyperacute – An aortic dissection <24 hours since initial symptoms
- Acute – 1-14 days
- Subacute — 15-90 days
- Chronic >90 days
Medical management
During your A-E examination, you need to think about controlling the BP, controlling any bleeding and very cautious fluid resuscitation.
- High-flow oxygen
- 2x wide bore cannulas for IV access
- Invasive monitoring – arterial line, central venous catheter and a urinary catheter
- Analgesia! – IV opiates
- Cautious fluid replacement if required – discuss with senior team
- Blood bank warned – Likely to require 6 units of cross-matched blood + additional products
- Control and active monitoring of HR and BP – Aiming for systolic BP of 100-120 and HR 60-80bpm
- Senior support from anaesthetics/critical care, vascular/ cardiothoracic surgeons and IR (interventional radiology)
- If an aortic dissection has already been confirmed on imaging – urgent discussion is required with the on-call cardiothoracic/vascular team with urgent transfer organised.
How to manage the BP
It is essential to manage blood pressure in dissection patients due to the increased risk of further tearing with hypertension, and the risk of organ compromise with hypotension. This is why we aim for a BP of 100-120mmHg systolic and HR 60-80bpm.
- Monitor BP in both arms and target therapy at the higher reading.
- An arterial line must be placed to ensure you are getting an accurate BP measurement.
- Opiate analgesia will reduce the sympathetic stimulus of pain.
- First line = IV beta-block infusion (e.g, labetalol). However, labetalol has a half-life of 3-5 hours, which could cause complications if there is sudden bleeding or haemodynamic instability. Esmolol is being used more recently due to its short 9-minute half-life.
- Second line = IV non-dihydropyridine calcium channel blockers (diltiazem or verapamil). These are rarely used, only where β-blockers are contraindicated.
- If BP is still not controlled (refractory hypertension) and HR is around 60bpm, then IV nitrate-based vasodilators (i.e. GTN infusion) should be considered.
Surgical management
Indications for surgery: Type A (Stanford) dissection, persistent pain, Branch occlusion, Leak, Continued extension of the dissection despite medical management.
- Type A dissection – Requires urgent open surgery to prevent rupture of the aorta and the pericardial sac. It will involve replacement of the ascending aorta with a synthetic graft.
- Type B dissections – Requires medical management if uncomplicated, however they may require stenting (endovascular) if there are complications such as poor perfusion of end organs, continuous pain, an aortic diameter that is rapidly expanding or aortic rupture/impending rupture.
The endovascular management is sometimes known as TEVAR (thoracic endovascular aortic repair), which aims to completely occlude the initial entry tear via stenting. Balloon fenestration can also be used. If aortic rupture or organ malperfusion occurs, then the stenting must occur urgently (<24 hours), however other complications may be surgically managed within 14 days. If a dissection is managed with endovascular repair, it is advised to have a surveillance CT scan done at 4 weeks, before annual surveillance.
Medical management of uncomplicated type B dissections includes tight control of blood pressure and analgesia, with continuous CTA imaging to monitor further complications is advised at 2-3 days post-event, 1 week and then 1 month. Annual surveillance may then be indicated.
Complications
It is essential that all patients are followed up long term to monitor for complications, including formation of aneurysms, aortic rupture, branch occlusions, malperfusion, re-dissection and other cardiovascular events.
If there is an aortic rupture – depending on the site of the aorta that the rupture occurs in, there can be various pathophysiological consequences.
- Ascending aorta > Rupture into the right haemothorax (sudden death) or haemopericardium (syncope and/or sudden death)
- Arch of the aorta > Rupture into the mediastinum (mediastinal haematoma), interatrial septal haematoma, compression of pulmonary artery/trunk
- Descending aorta > Rupture into the left haemothorax (sudden death), rupture into the oesophagus (rare), leading to haematemesis
- Abdominal aorta > Rupture into the retroperitoneal area (back pain with shock), rupture into intraperitoneal area (shock and acute abdomen symptoms)
If there is a branch occlusion or branch vessel involvement, there may be further complications:
- Coronary vessels > Myocardial infarction (ST elevation)
- Common carotids > Stroke (ischaemic or haemorrhagic)
- Subclavian vessels > Ischaemic upper limb
- Coeliac/mesenteric vessels > Ischaemic bowel
- Renal vessels > Frank haematuria
- Spinal arteries > Painless paraplegia of sudden onset
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

