


 Close
 6th June 2025
Hair and Nail Disorders
Alopecia
- Alopecia Areata
- Thought to be an autoimmune condition that causes hair to fall out
- Androgenetic Alopecia
- Male pattern hair loss and female pattern hair loss. Hair falls out in a well-defined pattern in men, whereas in women, the hair usually becomes thinner all over the head rather than receding from the temples.
- Central Centrifugal Cicatricial Alopecia
- A form of scarring alopecia that starts in the centre of the scalp.
- Chemotherapy-Induced Alopecia (CIA)
- When the hair falls out following chemotherapy.
- Frontal Fibrosing Alopecia (FFA)
- A type of Scarring Alopecia, where the hair follicle is destroyed and replaced with scar tissue.
- Traction Alopecia
- when hair falls out because it has been pulled in the same way for a long time.
- Trichotillomania
- A psychological condition, where you cannot stop pulling out hair, which leads to hair loss.
Alopecia Areata
Alopecia is the medical term for bald and areata means patchy. This patchy baldness can develop anywhere on the body, including the scalp, beard area, eyebrows, eyelashes, armpits, inside the nose, or ears. Alopecia areata happens when the immune system attacks hair follicles and causes hair loss. Researchers do not fully understand what causes the immune attack on hair follicles, but they believe that both genetic and environmental factors play a role. Anyone can have alopecia areata. Men and women get it equally, and it affects all racial and ethnic groups. If it occurs when you are younger typically it is more extensive. People with certain autoimmune diseases, such as psoriasis, thyroid disease, or vitiligo, are more likely to get alopecia areata, as are those with allergic conditions such as hay fever. Types of alopecia areata include patchy alopecia areata, alopecia totalis, alopecia universalis, alopecia barbae, diffuse alopecia areata and alopecia ophiasis.
Treatment of alopecia areata
- Finasteride: treatment for male pattern baldness
- Minoxidil: treatment for male and female pattern baldness
- Tattooing: Tattoo used to look like short hair and eyebrows
- Topical immunotherapy: applied to bald patches
- Scalp reduction surgery: sections of scalp with hair are stretched and stitched together
- Artificial hair transplant
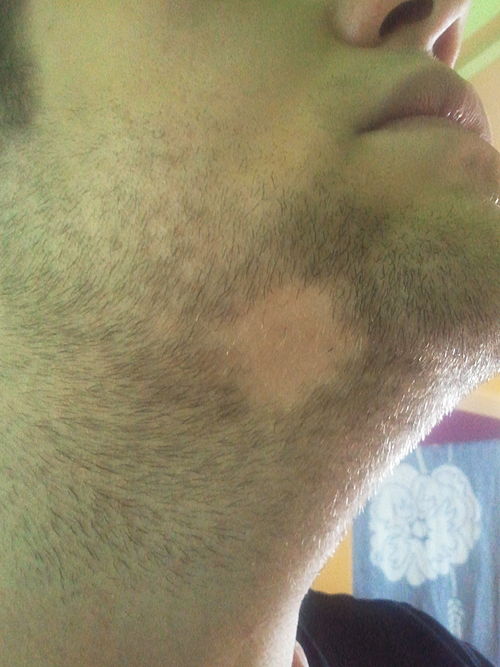
Image Source: Wikimedia Commons (2012). Alopecia Areata under the chin, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Alopecia_areata_unter_dem_Kinn.jpg (Accessed 22 May 2025).
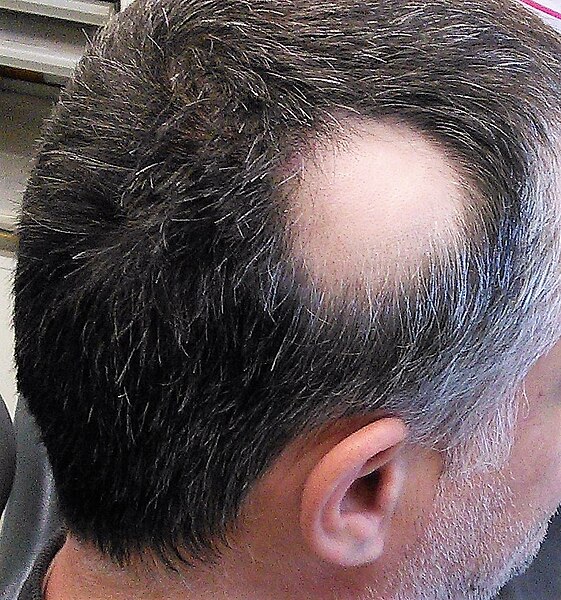
Image Source: Wikimedia Commons (2017). Alopecia Areata, Licensed under creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Alopecia_areata_1.jpg (Accessed 22 May 2025).
Hirsutism
Hirsutism is where women have thick, dark hair on their face, neck, chest, abdomen, lower back, buttocks, or thighs. Hirsutism occurs if the level of androgens in the body increases or if sensitivity to them increases. The two most common causes of hirsutism are polycystic ovary syndrome (PCOS) and idiopathic hirsutism. It affects around 5-10% of women. Hirsutism is usually the result of an underlying endocrine imbalance, which may be adrenal, ovarian, or central. The amount and location of the hair is measured by a Ferriman-Gallwey score. It is different from hypertrichosis, which is excessive hair growth anywhere on the body. The examiner scores the subjects on a scale of 0–4 for terminal hair growth on eleven different body areas according to the Ferriman-Gallwey scoring system (see figure 5). A Ferriman-Gallwey score of 8 or more was considered diagnostic of hirsutism.
Treatments for hirsutism include contraceptive pills, antiandrogen tablets or insulin sensitisers. Other forms of treatment include epilation, waxing, laser hair removal and electrolysis.
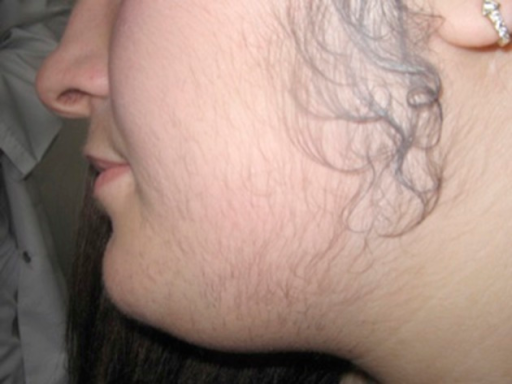
Image Source: Wikimedia Commons (2014). PMC410300, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:PMC4103002_ircmj-16-9410-g001.png (Accessed 22 May 2025).
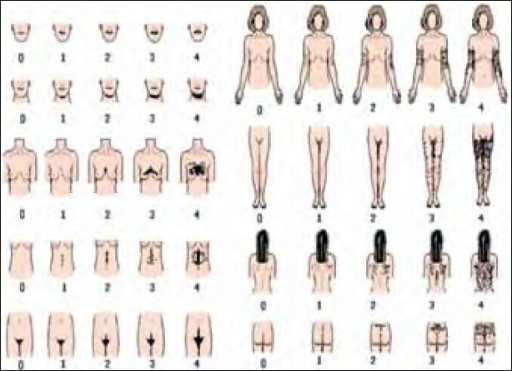
Image Source: Wikimedia Commons (2010). Ferriman-Gallwey Score, Licensed under a creative commons licence. Available for free at: https://upload.wikimedia.org/wikipedia/commons/8/88/Modified_Ferriman-Gallwey-score.png (Accessed 22 May 2025).
Hypertrichosis
Hypertrichosis is defined as excessive hair growth anywhere on the body in either males or females. It is important to distinguish hypertrichosis from hirsutism, which is a term reserved for females who grow an excessive number of terminal hairs in androgen-dependent sites. Hypertrichosis can be either congenital (present at birth) or acquired later in life.
Two methods of classification are used for hypertrichosis. One divides them into either generalised versus localised hypertrichosis, while the other divides them into congenital versus acquired.
Definitions of Hypertrichosis
Congenital: Congenital forms of hypertrichosis are caused by genetic mutations, and are extremely rare, unlike acquired forms. Congenital hypertrichosis is always present at birth.
Acquired: Acquired hypertrichosis appears after birth. The multiple causes include the side effects of drugs, associations with cancer, and possible links with eating disorders. Acquired forms can usually be reduced with various treatments. Drugs associated with acquired generalised hypertrichosis include; Antibiotics such as streptomycin, Anti-inflammatory drugs such as benoxaprofen and corticosteroids, Vasodilators (diazoxide, minoxidil, prostaglandin E1), Diuretics (acetazolamide), Anticonvulsants (phenytoin), Immunosuppressives (cyclosporine, mycophenolate mofetil), Psoralens (methoxypsoralen, trimethylpsoralen), Antiseptic agents (hexachlorobenzene), Chelators (penicillamine), Interferon-alpha, Fenoterol and EGFR inhibitors (cetuximab, panitumumab, erlotinib, gefitinib).
There is no treatment for the underlying cause of hypertrichosis, but the symptoms may be managed with hair removal methods, such as shaving, waxing, epilation, or electrolysis – the chosen method is guided by the patient’s preference.
Nail Disorders
Nail Changes Associated with Skin Disorders
Psoriasis
Psoriasis can affect both fingernails and toenails, with half of those with psoriasis having some form of nail involvement. The incidence increases in those with psoriatic arthritis, and it is reported that this could be as high as 4 out of 5 people seeing changes to their nails. Fingernails are more often involved than toenails. For many people, nail psoriasis is often mild and causes few problems.
The changes of the nails with psoriasis include:
- Pitting of the nails – the surface of the nail develops small pits, looking rather like the surface of a thimble. The number of pits can vary from one to dozens.
- Onycholysis – the nail becomes detached from the underlying nail bed and a gap develops under the nail. When it starts there is a white or yellowish patch at the tip of the nail, and this then extends down to the cuticle. The gap between the nail and the nail bed can become colonised by particular bacteria, such as pseudomonas, which can then produce a dark green pigment. The nail can become infected and discoloured and can easily be mistaken for melanoma under the nail.
- Subungual hyperkeratosis – a chalky substance accumulates under the nail. The nail becomes raised and can become tender, especially when the surface of the nail is pressed. Subungual hyperkeratosis of the toenails can be particularly uncomfortable because when wearing shoes the nail may be put under constant pressure.
- Discolouration – this may be seen as unusual nail colouration, such as yellow/brown.
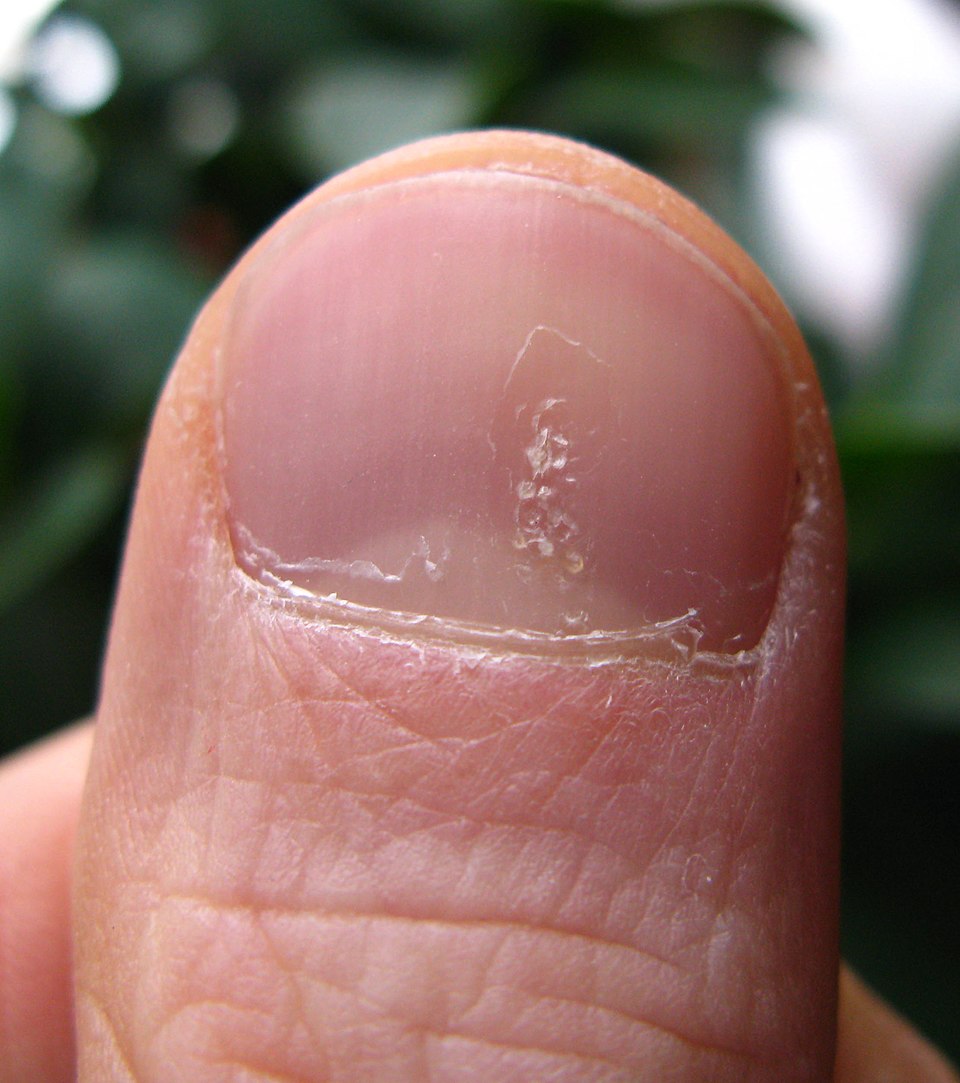
Image Source: Wikimedia Commons (2011). Luszczyca Paznokcia, Licensed under a a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Luszczyca_paznokcia.jpg (Accessed 22 May 2025).
Eczema
Eczema is another skin condition associated with nail changes. It is not as common as psoriasis nail changes. Pompholyx eczema can affect the nail folds and skin around the nails (cuticles), resulting in swelling. Nail eczema can cause pitting in the nails and requires treatment to avoid worsening of the condition. A 2019 study looked at the nails of 235 patients aged 2 to 19 with eczema. Of the group, 10% of people had nail abnormalities. The most common nail changes found were grooved nails (25%), nail pitting (16.7%), and koilonychia (16.7%).
Nail Changes Associated with Systemic Disease
Koilonychia
Spoon nails (koilonychia) are soft nails that look scooped out. It is a nail change that can be a sign of hypochromic anaemia, especially iron deficiency. Even though Koilonychia has been associated with iron deficiency in case reports, it is more likely seen as an occupational change in nails and may be idiopathic; ruling out iron deficiency anaemia in these patients is the only work-up necessary in this condition.
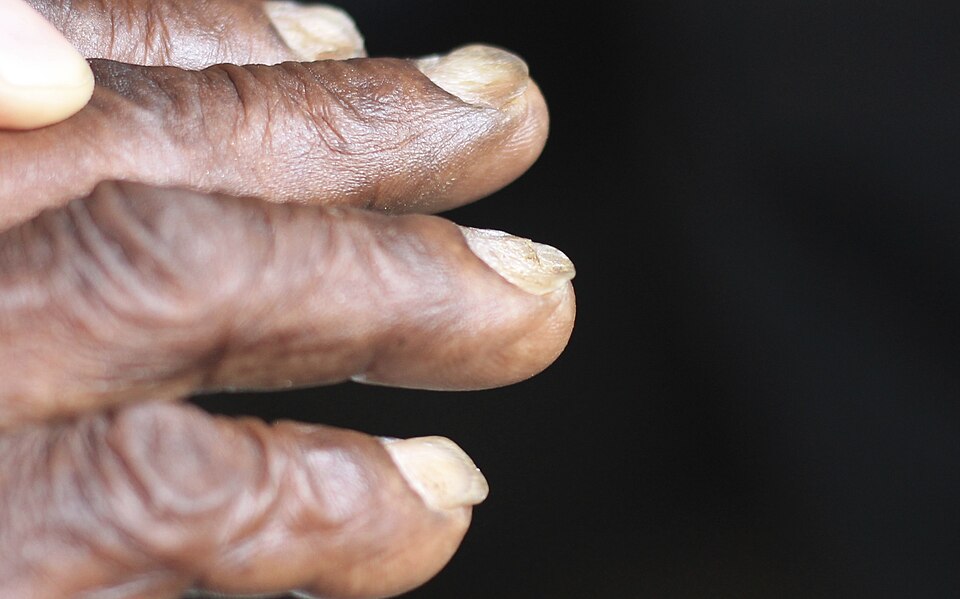
Image Source: Wikimedia Commons (2014). Koilo Nychia Iron Deficiency Anaemia, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Koilonychia_iron_deficiency_anemia.jpg (Accessed 22 May 2025).
Leukonychia
Leukonychia, or white nails, is usually not an alarming sign, but it can sometimes unmask severe systemic disorders or congenital conditions. Examples of systemic disorders include; anaemia, hepatitis C, Wilson’s disease and ischemic cardiomyopathy and congenital conditions include; Bart–Pumphrey syndrome, keratoderma-hypotrichosis-leukonychia totalis syndrome and Carvajal/Naxos syndrome. The white colour can be due to nail plate or nail bed abnormalities.
Leukonychia consists of whitening of the nail and the morphology classifies the nail according to the distribution of the white lines: total, partial, transversal, and longitudinal leukonychia. Mees’ and Muehrcke’s lines are examples of transversal leukonychia, while Terry’s and Lindsay’s nails are examples of total and partial leukonychia. The anatomical classifies according to the structure responsible for the white colour: the nail plate in true leukonychia, the nail bed in apparent leukonychia, and the surface only in pseudo-leukonychia.
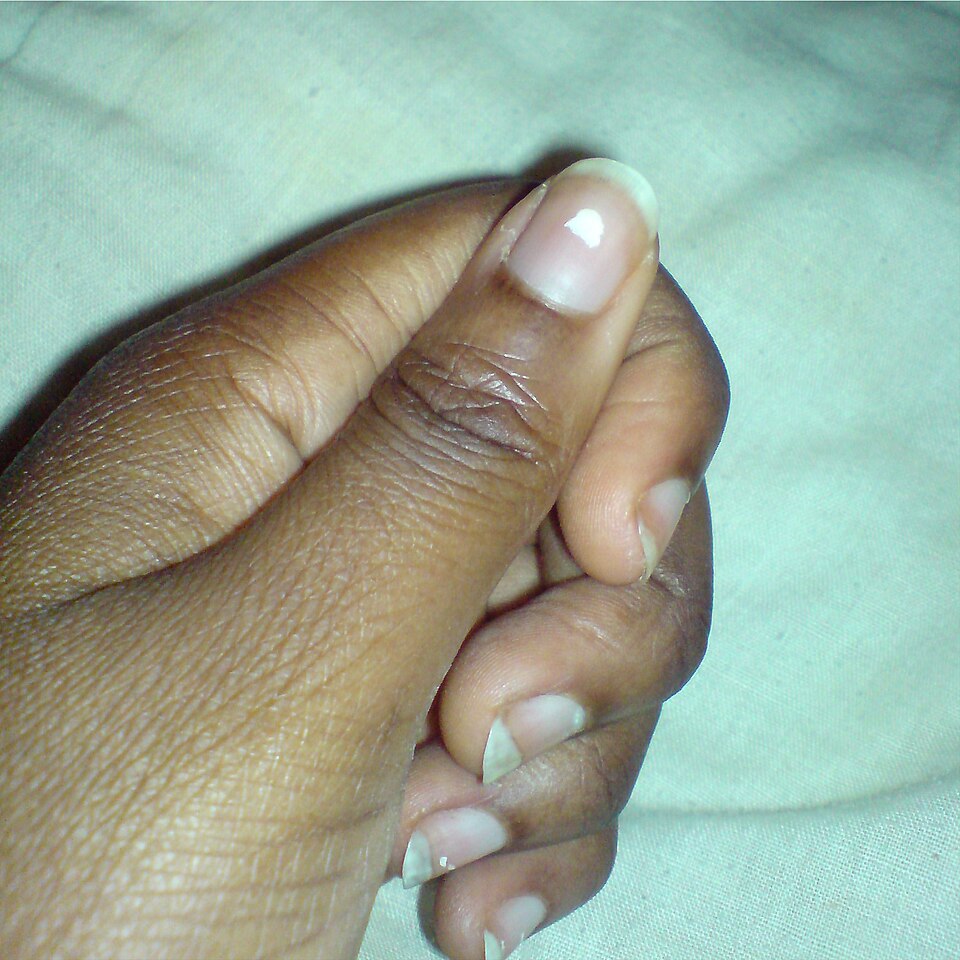
Image Source: Wikimedia Commons (2010). Leukonychia2, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Leukonychia2.jpg (Accessed 22 May 2025).
Yellow Nail Syndrome
This is a rare condition defined by a presence of two of the following: (1) slow-growing, hard, yellow, and dystrophic nails, (2) lymphedema, and (3) respiratory tract disease. Yellow nail syndrome most often starts in middle age, although a similar condition has been described in younger children. The cause of yellow nail syndrome is unknown; however, it is seen in multiple conditions: rheumatoid arthritis, internal malignancies, pleural effusions and bronchiectasis.
Image Source: Wikimedia Commons (2007). YNS, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Yns.jpg (Accessed 22 May 2025).
Nail Changes Associated with Infections
A change in colour, size, shape or texture of finger- and toenails can be an indicator of underlying systemic infection. An appreciation of these nail signs, and an ability to interpret them when found, can help guide diagnosis and management of a general medical patient.
Examples can include:
- Bacterial Endocarditis: Splinter haemorrhages are small, linear subungual structures, normally red, purple or brown in colour, most frequently located in the distal third of the nail plate.
- Untreated HIV or AIDs can present with nail infections; bacterial, viral and fungal. Proximal white onychomycosis is a pattern of fungal nail infection that is rarely seen without a diagnosis of immunosuppression, where HIV is an example; trichophyton rubrum is commonly the underlying pathogen.
Leprosy and Malaria infections can be associated with Mees Lines. Mees’ lines are white lines or bands that appear on the fingernails or toenails.
Onycholysis
Onycholysis is when your nail separates from its nail bed. It often appears after an injury to your nail, but it may have other causes, including fungal infection. Onycholysis can affect both sexes, all ages and races. It is most frequently seen in adult women. Onycholysis can be associated with: Psoriasis, infection, hyperthyroidism, sarcoidosis, trauma, amyloidosis and connective tissue disorders. The distal part of the nail is most commonly affected by lifting the free edge; sometimes the nail may detach laterally or proximally. Diagnosis is made clinically but investigations can be carried out to find out the cause if not clear including nail clippings and blood tests.
Treatment is based on the fact that the detached portion of the nail will not reattach. The aim of treatment is for the new nail growth to remain attached to the underlying nail bed. Onycholysis can be managed by; clipping the affected portion, wearing gloves, minimising activity which traumatises the nails and taping the nail down.

Image Source: Wikimedia Commons (2014). Hand Taxotere 1, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Handstaxotere_1.jpg (Accessed 22 May 2025).
References
- https://dermnetnz.org/topics/hypertrichosis
- https://anndermatol.org/DOIx.php?id=10.5021/ad.2019.31.2.121
- https://cks.nice.org.uk/topics/anaemia-iron-deficiency/
- https://www.ncbi.nlm.nih.gov/books/NBK559311/
- https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8809498/#:~:text=Introduction-,Leukonychia%2C%20or%20white%20nails%2C%20is%20usually%20not%20an%20alarming%20sign,classification%20and%20interpretation%20of%20leukonychia.
- https://www.ncbi.nlm.nih.gov/books/NBK557760/#:~:text=Yellow%20nail%20syndrome%20(YNS)%20is,reported%20by%20Heller%20in%201927.
- https://dermnetnz.org/topics/yellow-nail-syndrome
- https://dermnetnz.org/topics/onycholysis
- https://www.ncbi.nlm.nih.gov/books/NBK534854/
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

