


 Close
 8th August 2024
Neurodegenerative Disorders
Dementia and other cognitive disorders
Alzheimer’s disease
Overview of Alzheimer’s disease
Alzheimer’s disease is the most common dementia in adults of all ages. There is an initial deficit in episodic memory that progresses to include executive functioning, attention, language and visuospatial skills as the disease advances. Neuropsychiatric symptoms can be prominent, including mood disturbance, anxiety, hallucinations, agitation and restlessness. End-stage disease resulting additionally in reduced mobility, incontinence and inability to communicate can require high levels of care.
The histopathological hallmark of Alzheimer’s disease is cerebral cortical accumulation of beta amyloid (Aβ) plaques and neurofibrillary tangles.
Diagnosis of Alzheimer’s disease
Diagnosis is clinical and made from history, examination, investigations to exclude reversible causes and cognitive testing such as mini-mental state examination (MMSE) or Montreal Cognitive Assessment (MoCA) demonstrating deficits in short-term memory with reduction of category fluence (naming as many items of a category beginning a specific letter) and deficit in visuospatial tasks (copying 3D drawings/clocks) in more advanced disease.
Cognitive testing is complemented by structural correlates on MRI brain, with hallmark symmetrical medial temporal lobe and hippocampal atrophy in early disease and later inclusion of the parietal lobes.
CSF examination has a typical pattern of elevated tau protein and reduced Aβ1-42, but this is not routinely required.
Histological diagnosis is rarely acquired outside of post-mortem. Silver staining and specific tau protein immunohistochemistry demonstrate neurofibrillary tangles within neurons.
Management of Alzheimer’s disease
The mainstay of management is supportive and multidisciplinary. In early stages of disease, management should be proactive in providing education to patients and family, support for advanced care and financial planning whilst capacity is retained and facilitating everyday activities with assistance. Coordination across services such as a community dementia team, day centres, care agencies and GPs is key. With further disease progression and in advanced dementia, care may be better provided in a residential or nursing home setting with consideration of carer respite.
Pharmacological management aims to slow disease progression and prolong time before requiring 24-hour care. The main classes of drugs are anticholinesterases and NMDA receptor antagonists.
Donepezil, galantamine and rivastigmine are acetylcholinesterase inhibitors (AChEi) that are licensed for treatment of mild-to-moderate Alzheimer’s disease. Treatment should be initiated by a clinician with relevant specialist expertise in diagnosis and management of Alzheimer’s. A small but consistent benefit to cognitive function with AChEis compared to placebo has been demonstrated in meta-analyses with some evidence to suggest that withdrawal of treatment may be associated with worsening cognition. Common side effects of AChEis include gastrointestinal manifestations – diarrhoea, vomiting, nausea, reduced appetite, dyspepsia – as well as dizziness, muscle cramps and insomnia. Significant caution should be exercised in patients with bradycardia, heart block or recurrent syncope.
Memantine, an NMDA receptor antagonist, can be considered as an additional agent in individuals already on AChEis with disease progression or as a single agent in individuals with severe Alzheimer’s or those with moderate Alzheimer’s for whom AChEis is contraindicated.
The management of behavioural and psychological symptoms such as aggression or depression is less well evidenced. Conservative approaches addressing surroundings and care should be attempted before consideration of antidepressants and antipsychotics, under specialist guidance, particularly as atypical antipsychotics are associated with increased risk of stroke and mortality in this cohort.
Vascular dementia
Overview of vascular dementia
Vascular dementia is the second most common cause of dementia in older people. It is a dementia syndrome recognised as the decompensation of cognitive function resulting from the accumulation of vascular insults and can be considered on a spectrum of cognitive impairment of vascular aetiology.
The presentation is varied, and the affected domains and severity of cognitive deficits relate to the location and burden of cerebrovascular disease. Mechanisms of vascular insult include large vessel ischaemia resulting in discrete infarcts, small vessel disease of subcortical structures (basal ganglia, thalamus, brainstem), deep white matter disease (leukoaraiosis) and haemorrhage (cortical haemorrhage associated with cerebral amyloid angiopathy).
In contrast to Alzheimer’s disease, typically, executive and attention function is more affected than memory with earlier involvement of mobility and mood. Classically, a history of a stepwise progression is seen with repeated clinically significant vascular events, although sequential silent events will present with insidious cognitive decline. A mixed dementia syndrome with Alzheimer’s is common.
Diagnosis of vascular dementia
Diagnosis requires cognitive testing showing impairment in two or more domains and brain imaging demonstrating cerebrovascular disease with either history of cognitive symptoms related to vascular event(s) or cognitive impairment explained by the degree/pattern of disease seen on imaging.
Small vessel disease on MRI is seen as periventricular and subcortical white matter lesions, subcortical infarcts, and cerebral microbleeds (hypointense foci on T2-weighted sequences).
Management of vascular dementia
Antiplatelets and anticoagulation, respectively, are used as secondary prevention for arteriosclerotic and cardioembolic causes. Prevention is through modification of risk factors, which are hypertension, smoking, hypercholesterolaemia, diabetes and obesity; however, increasing age is the greatest risk factor.
Rare causes of vascular dementia
CADASIL
Cerebral autosomal dominant arteriopathy with subcortical infarcts and leukoencephalopathy (CADASIL) is caused by autosomal dominant inheritance of a mutation in the notch3 gene. There is typically a history of adult-onset migraine-like headaches and episodes of focal neurological symptoms, with an accumulation of subcortical infarcts resulting in dementia by the late forties.
Primary cerebral vasculitis
Primary cerebral vasculitis, isolated inflammation of cerebral vasculature, can cause a progressive dementia. It may present as cerebral amyloid-associated inflammation in some patients with cerebral amyloid angiopathy (CAA), presenting with headaches, seizures and progression of cognitive deficit. Neuroimaging can show microhaemorrhages, white matter changes and vasogenic oedema. Treatment is with immunosuppression.
Frontotemporal dementia
Overview of frontotemporal dementia
Frontotemporal dementia (FTD) is a syndrome that has a wide presentation that can be categorised into variants predominantly affecting behaviour or language. The peak incidence is between the ages of 45-65, and it affects both sexes equally. 40% of patients with FTD have a relevant family history.
In behavioural variants, there is a progressive history (usually verified by collateral) of deterioration in behaviour and cognition resulting in disinhibition, apathy, loss of empathy, hyperorality, perseveration and loss of executive functioning, with relative sparing of memory.
There are three language variants, termed collectively as primary progressive aphasias:
- Progressive non-fluent aphasia: impaired production of expressive speech with difficulties in repeating complex words or phrases, poor speech flow and fluency and incorrect grammatical formation of phrases with phonological substitutions for words. In early disease, recognition of objects and understanding of language is preserved.
- Semantic dementia: loss of semantic memory, i.e. naming of objects and understanding the meaning of words, but with production of language that is grammatically correct and fluent. Names of items are substituted with a generic reference such as ‘that thing’. Repetition of phrases is preserved, although comprehension can be impaired. In contrast with Alzheimer’s disease and in early stages, short-term memory for daily activities remains intact.
- Logopaenic aphasia: paucity of speech, particularly groping for words and inability to repeat phrases resulting from a deficit in working memory capacity.
Diagnosis of frontotemporal dementia
Imaging, either MRI or PET, shows frontal and/or anterior temporal atrophy or hypoperfusion, respectively. CSF examination excludes causes such as infection and inflammation, and Alzheimer’s disease.
Lewy body dementia
Overview of Lewy body dementia
Lewy body dementia (LBD) is conventionally understood to be on the same spectrum as Parkinson’s disease dementia (PDD), but nomenclature is dependent on whether cognitive impairment precedes motor symptoms of Parkinsonism (defined as LBD) or vice versa, i.e. PDD. It often co-exists with Alzheimer’s and vascular dementia.
The microscopic histopathological hallmark of LBD is intracellular neural Lewy bodies (formed of α-synuclein) distributed in three typical sites (cortex, brainstem and limbic areas). These stain with haematoxylin-eosin and α-synuclein histochemistry. Macroscopically, there is pallor of the substantia nigra and locus coeruleus and diffuse cerebral atrophy.
The cognitive presentation is similar to Alzheimer’s, however there is predominance of problems affecting executive, visuospatial and attentional functions with relatively less involvement of memory.
The key distinguishing features are:
- Fluctuations in cognition (attention and alertness)
- Visual hallucinations in up to 60% of patients – typically formed people or animals and usually not distressing (compared to psychiatric hallucinations); alternatively a sense of a ‘presence’
- Parkinsonism – eventually seen in most cases, depending on LBD/PDD, may predate or follow cognitive symptoms. Bradykinesia, rigidity, gait impairment and autonomic dysfunction
Other common features include:
- Rapid eye movement (REM) sleep behavioural disturbance
- Daytime somnolence
- Autonomic dysfunction (falls, syncope, postural hypotension, constipation, urinary urge, frequency and incontinence)
- Mood disturbance, including anxiety and depression
Diagnosis of Lewy body dementia
Although brain imaging is recommended at least once in dementia work up, there are no specific structural imaging features of LBD. Single-photon emission CT (SPECT) or PET can help differentiate between LBD and Alzheimer’s and will show reduced uptake of dopamine transporter uptake in the basal ganglia.
CSF examination is usually carried out in atypical presentations to exclude infection.
Referral to a sleep specialist and for polysomnography is advised as REM sleep without atonia is a suggestive feature of LBD.
Management of Lewy body dementia
Management is targeted at symptoms and supportive measures. Given the underlying deficits are of choline and dopamine neurotransmission, priority review of medications is important to avoid anticholinergics and dopamine agonists to reduce exacerbation of autonomic, motor and psychiatric symptoms. First-generation antipsychotics (haloperidol) should be avoided and patients tend to be very sensitive to atypical antipsychotics.
First-line treatments are anticholinesterase treatments such as donepezil and rivastigmine, which act to improve cognition and behavioural symptoms without significant worsening of motor symptoms, however side effects may include nausea and vomiting, runny nose, muscle cramps, hypersalivation, vivid dreams and postural hypotension.
Clonazepam in low doses is effective for REM sleep behaviour disturbance.
SSRIs are choice antidepressants, avoiding tricyclics that have anticholinergic effects.
Levodopa can be considered in specialist use if motor symptoms are significantly problematic.
Human prion disease – Creutzfeldt-Jakob disease
Creutzfeldt-Jakob disease (CJD) is a rare and inevitably fatal cause of progressive dementia with neurological symptoms. Intracellular human prion proteins are misfolded from an alpha-helical structure into a beta-pleated form, which in turn causes adjacent proteins to undergo this transformation. These ‘infectious proteins’ drive the pathophysiology of neuronal injury and eventual cell death as a result of accumulation of abnormal prion proteins in the CNS.
There are three main types of CJD:
- Sporadic (sCJD) – accounts for the majority of cases, up to 90% of CJD
- Acquired – include iatrogenic CJD (iCJD) (transmission of prion protein from contaminated surgical equipment or cadaveric tissue grafts) and variant CJD (vCJD) (ingestion of CJD-contaminated beef or blood transfusion)
- Familial – mutations in the gene coding for PRNP (endogenous prion protein) on chromosome 20; usually autosomal dominant with 100% penetrance, however, clinical presentation can be variable and less aggressive than sCJD and vCJD
| sCJD | Familial | vCJD | iCJD | |
|---|---|---|---|---|
| Onset | 60s | Younger onset than sCJD | Young adults – teenagers, 20s | Variable incubation period – also related to timing of inoculation event |
| Features
(in order of presentation) |
Cognitive symptoms – memory loss, aphasia and impaired executive functioning with progressive dementia
Ataxia Rigidity Limb myoclonus Familial can have a variable rate of progression, although it can present almost identically to sCJD |
Psychiatric symptoms – often severe depression
Dementia (initially mild cognitive impairment) Ataxia Painful sensory symptoms Involuntary movements – dystonia, chorea, myoclonus |
For neurosurgical inoculation – similar presentation to sCJD | |
Diagnosis of CJD
CSF examination – can be bland with mildly raised protein. Elevated 14-3-3 protein has high sensitivity and specificity for sCJD but is not useful for vCJD; real-time quaking-induced conversion for abnormal prions has high sensitivity and specificity.
EEG – periodic triphasic spikes
Imaging – MRI brain with FLAIR (fluid attenuated inversion recovery) and diffusion-weighted imaging (DWI) best demonstrates affected areas:
- sCJD – hyperintensities in the basal ganglia (caudate and putamen) and ‘cortical ribboning’ on DWI
- vCJD – bilateral periventricular thalamic hyperintensities, ‘hockey stick sign’
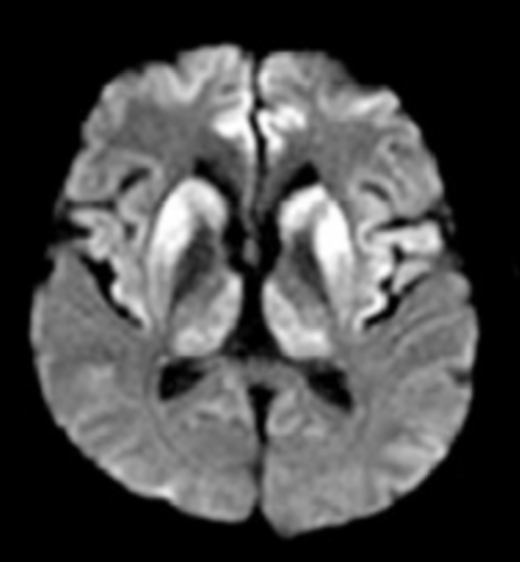
Image Source: ncbi.nlm.nih.gov 2025, PMC5619326, Licensed under a creative commons licence. Available for free at: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5619326/pdf/dn-09-04-0424.pdf (Accessed: 17 July 2024)

Image Source: ncbi.nlm.nih.gov 2025, PMC5619326, Licensed under a creative commons licence. Available for free at: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5619326/pdf/dn-09-04-0424.pdf (Accessed: 17 July 2024)
Normal pressure hydrocephalus
Normal pressure hydrocephalus (NPH) was historically described as the triad of gait disturbance, urinary incontinence and cognitive slowing as a result of hydrocephalus without raised cerebrospinal fluid pressure. The aide-memoire “wobbly, wet and wacky” may have come up in medical school! Clinical features typically develop gradually over years.
The reported incidence of NPH is variable as there are different diagnostic criteria. The pathophysiology is not well understood, but the underlying processes are thought to drive formation of a communicating hydrocephalus with resultant ischaemic insult to subcortical and periventricular structures including the basal ganglia.
Risk factors are predominantly age >65 and vascular, thought to be related to effects on compliance of cerebral blood vessels that, in turn, regulate the flow of CSF.
Diagnosis and management of NPH
Gait disturbance is the key and usually first symptom noticed and is typically small stepped, slow, hesitant, wide based and magnetic (‘stuck to the floor’), with difficulties in making 180 degree turns in 3 or fewer steps.
Lumbar puncture has both a diagnostic and therapeutic role – specifically, pressure measured by manometry should be normal. Large volume CSF removal (40-50 ml) can be done with cognitive testing and gait assessment pre- and post-therapeutic lumbar puncture; cases that respond to this may represent candidates for further lumbar drainage, although identifying this group of individuals can be challenging.
A trial of levodopa should not yield gait improvement (excluding Parkinson’s disease) and brain imaging can demonstrate ventriculomegaly which is disproportionate to sulcal atrophy, distinguishing it from global cerebral atrophy. There may also be evidence of periventricular white matter change, although imaging can also be normal. A space-occupying lesion with obstruction would exclude the diagnosis of NPH.
Movement disorders and dementia
Parkinson’s plus syndromes (including progressive supranuclear palsy and corticobasal degeneration) and Huntington’s disease that cause dementia as part of advanced disease are covered more thoroughly in the movements disorder section. These dementias typically present as frontotemporal or subcortical types.
Mimics of dementia
Depression (pseudodementia)
Cognitive deficits are common in psychiatric disorders, as is the coexistence of depression with dementia. It can be difficult to explicitly distinguish the degree of contribution of each factor, and occasionally, a trial of an antidepressant and/or referral for further psychiatric testing is considered. Typically, individuals present with distractibility, poor concentration and short term memory in the context of low mood (although not always experienced) and may also include biological symptoms of depression such as poor sleep and loss of libido and appetite. Cognitive screening tests often show reduced engagement with testing and inconsistent results with impaired attention and variably poor performance in memory and behavioural domains.
Delirium
Delirium is an acute state of rapidly fluctuating consciousness impacting orientation and attention, that is usually reversible (to a degree), precipitated by a homeostatic or metabolic disturbance. The diagnosis of dementia must exclude cognitive impairment that is exclusively in the context of a delirium. Management is driven by identification and treatment of the precipitant with supportive care to allow for delirium to resolve.
Hypothyroidism
Severe hypothyroidism can cause symptoms of apathy, slowing of cognition and speech, overlapping with the symptoms of dementia and depression.
Mild cognitive impairment
Mild cognitive impairment (MCI) is an acquired cognitive decline beyond that expected for age or level of education, however, which does not cause significant functional impairment. It is a differential to consider if dementia is suspected but the criteria are not met, or if it is of low severity. Mild cognitive impairment can be divided into amnestic (affecting memory) or non-amnestic (affecting cognitive domains such as language, executive function or visuospatial skills, but not memory). There is an increased incidence of progression of amnestic MCI to Alzheimer’s disease compared to the general population.
Encephalitis and infectious causes of dementia
HIV
Progressive cognitive impairment in HIV-infected individuals requires evaluation to exclude systemic illness or opportunistic infections of the central nervous system (and their long-term sequelae). Key factors to consider are an individual’s CD4 count and duration of/concordance with antiretrovirals. HIV-associated neurocognitive disorder (HAND) represents a broad spectrum of cognitive impairment from asymptomatic/mild cognitive impairment to HIV-associated dementia that meets criteria of affecting at least two cognitive domains with significant effect on activities of daily living.
Opportunistic cerebral infections in HIV are prevalent when the CD4 count is <100 cells/microlitre. Toxoplasma, herpes simplex and varicella zoster encephalitis, cryptococcal or tuberculous meningitis, progressive multifocal leukoencephalopathy secondary to JC (John Cunningham) virus infection and EBV infection with primary CNS lymphoma.
There can also be cognitive and neuropsychiatric side effects to certain antiretrovirals (commonly efavirenz in early treatment), however immune reconstitution inflammatory syndrome (IRIS) as a cause of progressive cognitive impairment in the context of recent initiation on antiretrovirals should be considered.
HIV-associated dementia (HAD) presents with logopaenic speech, slow and poor thought processes, with flat or labile affect in the absence of sadness. There can often be a degree of overlap with psychiatric morbidity. There are no specific neuroimaging changes seen in HAD and neurological examination can show gait disturbance, frontal release and pyramidal signs.
Neurosyphilis
Infection with syphilis that has spread to the meninges and cranial nerves causes the neurological signs of absent reflexes, Argyll-Robertson pupils, ataxia, peripheral motor/sensory deficits and associated cognitive impairment.
Nutritional causes of dementia
Wernicke’s encephalopathy
Typically presents as the triad of a complex ophthalmoplegia, delirium and ataxia due to severe B1 deficiency, most commonly seen in alcoholics. Needs urgent treatment with Vitamin B complex replacement to prevent permanent cognitive impairment.
B12 deficiency
Other features, in addition to cognitive impairment, include macrocytic anaemia, neurological signs (subacute combined degeneration of the cord) such as ataxia, and reduced proprioceptive and vibration sense in the lower limbs.
B3 deficiency – pellagra
Pellagra is a systemic disease best remembered using the 3 Ds: dermatitis, diarrhoea and dementia. It is caused by deficiency in niacin, most commonly due to diet in developing countries. It usually presents initially with characteristic skin changes and non-specific abdominal symptoms. Neuropsychiatric involvement with cognitive impairment is a late sign in untreated disease.
References
- National Institute for Health and Care Excellence (NICE). Donepezil, galantamine, rivastigmine and memantine for the treatment of Alzheimer’s disease. 2018 [cited 17 April 2023]. Available from: https://www.nice.org.uk/guidance/ta217/resources/donepezil-galantamine-rivastigmine-and-memantine-for-the-treatment-of-alzheimers-disease-pdf-82600254699973
- Firth, John, Christopher Conlon, and Timothy Cox (eds), Oxford Textbook of Medicine, 6 edn (Oxford, 2020; online edn, Oxford Academic, 1 Jan. 2020) Schott, J. Chapter 24.4.2, 24.11.5. [cited 16 March 2023]. Available from: https://doi.org/10.1093/med/9780198746690.001.0001
- Neugroschl J, Matthews B, Bhutto A, Gammack J. Alzheimer’s disease. BMJ Best Practice. Feb 2023. [cited 29 March 2023]. Available from: https://bestpractice.bmj.com/topics/en-gb/317
- Passmore P, Wilson D, Bateman G, Srikanth V. Vascular dementia. BMJ Best Practice. Nov 2022. [cited 29 March 2023]. Available from: https://bestpractice.bmj.com/topics/en-gb/319
- Lerner A, Elkasaby M, Appleby B, Gore E, Shrestha R, Wuerz T, Schneider J, Fahmy V, Banerjee S. Dementia with Lewy bodies. BMJ Best Practice. Jun 2023. [cited 29 March 2023] Available from: https://bestpractice.bmj.com/topics/en-gb/320
- Radhakrishnan R, Jauhari S, Whalley L, Onyike C. Frontotemporal dementia. BMJ Best Practice. Nov 2022. [cited 29 March 2023]. Available from: https://bestpractice.bmj.com/topics/en-gb/968
- Sim V, Geschwind M, Kuo A, Finley R. Prion disease. BMJ Best Practice. Feb 2020. [cited 29 March 2023]. Available from: https://bestpractice.bmj.com/topics/en-gb/484
- Grünewald R, Rowe J. Normal pressure hydrocephalus. BMJ Best Practice. Oct 2022. [cited 29 March 2023]. Available from: https://bestpractice.bmj.com/topics/en-gb/712
- Brouillette M-J, Hull M, Harris M, Repetto M. Assessment of HIV-related mental status changes. BMJ Best Practice. 11 Jul 2023. [cited 29 March 2023]. Available from: https://bestpractice.bmj.com/topics/en-gb/900
- Mead S, Rudge P. CJD mimics and chameleons. Pract Neurol 2017;17:113–121. [cited 13 April 2023]. Available from: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5520355
- V Ngan, Pellagra. DermnetNZ website. [cited 14 Jan 2024] Available from: https://dermnetnz.org/topics/pellagra
Parkinson’s and other movement disorders
Overview of movement disorders
This section will explain what a movement disorder is, and the forms that it can take. Movement disorders affect the nervous system, classically the basal ganglia or cerebellum, resulting in abnormal voluntary movements or causing involuntary movements. It is important to note that not all disorders causing abnormalities of movement are part of a movement disorder syndrome; examples include hemiplegia in stroke, tonic-clonic seizures in epilepsy and neuromuscular disorders. There are a few treatable movement disorders – Parkinson’s disease, Wilson’s disease and dopa-responsive dystonia – and there should be a high index of suspicion for these.
Movement disorders have historically been, and still are, broadly divided into two categories: hypokinetic (reduced movement) or hyperkinetic (excess movement). Even though a degree of overlap is now recognised, with many disease processes not falling neatly into one category, they are still widely used today. This original classification was based on clinical syndromes with suspected underlying basal ganglia dysfunction. However with longer life spans allowing diseases to progress, the development of modern imaging techniques and new investigations we now have a much greater understanding of these conditions and the widespread effects they have on the CNS, outside of the classical movement disorder presentation from which they were originally described and categorised.

Tremor
Tremor is the rhythmic shaking of a part of the body due to involuntary muscle contractions. It can be divided into two main forms, resting or action, the latter occurring during voluntary movement. Action tremors can be divided into sub-categories including intention, postural, and isometric amongst others. Everyone has a physiological tremor, most commonly a fine shaking of the hands which is often not visible to the naked eye due to its low amplitude and frequency. In some individuals it is more prominent, including in those with hyperthyroidism, hypoglycaemia and alcohol withdrawal in which the normal physiological tremor is enhanced.
Essential tremor
This is the most common type of tremor and most common movement disorder worldwide. It can be a mix of a number of different tremor types, including kinetic, postural and sometimes rest. The tremor is mostly symmetrical and progresses over time. It commonly involves the hands and forearms and can also involve the voice, head and jaw. Incidence increases with age, although in those with a family history it can appear in adolescence. Stress and caffeine can make essential tremors more prominent while alcohol can lessen them. It is a clinical diagnosis although sometimes investigations are used to rule out other pathologies such as hyperthyroidism or Wilson’s disease.
For most the tremor does not cause any problems and no treatment is needed. As it progresses it may start to interfere with daily activities and cause social distress for which propranolol or primidone can be used. Second-line agents include gabapentin and topiramate. In very severe cases deep brain stimulation (DBS) or thalamotomy, either using MRI-guided focused ultrasound or gamma knife radiation, are possible.
Myoclonus
Sudden, brief, involuntary jerking or twitching movements, most commonly non-rhythmic. It can be described as positive or negative with the former being a sudden muscle contraction and the latter being a sudden loss of muscle tone. Myoclonic jerks occur physiologically including as hiccups or as limb twitches when a person drifts off to sleep. However, myoclonus can also be pathological and can occur in many different forms in isolation and as part of other neurological disorders, e.g. post-anoxic brain injury, genetic and neurodegenerative disease. Of note it can sometimes be the only manifestation of epilepsy and thus can indicate underlying seizure activity. Asterixis is a form of negative myoclonus which can occur due to metabolic disturbance such as hypercapnia (carbon dioxide retention flap), uraemia and liver failure (liver flap).
Parkinsonism
Parkinsonism is the triad of:
- Akinesia and bradykinesia
- Tremor: a resting tremor; described as ‘pill rolling’ when limited to the fingers
- Rigidity: lead-pipe (constant resistance to motion) and cogwheel (intermittent resistance to passive movement)
Although not part of the triad, the festinant, stooped, slow-turning gait of parkinsonism is also a cardinal sign.
Parkinsonism is due to impaired functioning of the basal ganglia. It most commonly presents due to idiopathic Parkinson’s disease (PD), but can be caused by a number of other conditions, including vascular disease (vascular parkinsonism), Parkinson’s plus syndromes, Wilson’s disease, post encephalitis, drug induced (antipsychotics most commonly) or toxins (carbon monoxide, MPTP [1-methyl-4-phenyl-1,2,3,6-tetrahydropyridine]).
Idiopathic Parkinson’s disease
Overview of idiopathic Parkinson’s disease
Idiopathic Parkinson’s disease (PD) is characterised by the presence of Lewy bodies in the dopaminergic cells of the substantia nigra resulting in the death of those cells over time. It is more commonly seen in men, with an average age of onset of age of 65 years and a prevalence of 1% in the over 60s.
Symptoms frequently start unilaterally, and all three components of the triad may not be present. Over time, postural instability and gait disturbance develop along with speech and swallowing difficulties, hypomimia and micrographia, and non-motor symptoms such as depression, autonomic dysfunction, sleep disturbance and dementia. The rate at which the symptoms progress varies greatly, with most patients having a near-normal life expectancy. The biggest cause of death in the PD population is pneumonia, with dysphagia greatly contributing to this.
Idiopathic PD is normally a clinical diagnosis, but where there is uncertainty a dopamine transporter (DaT) scan can be performed. This has a good negative predictive value, with a negative result almost ruling out idiopathic PD or a Parkinson’s plus syndrome (unless too early in the disease course). However, a positive DaT scan does not necessarily indicate PD. In young patients, other movement disorders should be considered and investigated, including Wilson’s and Huntington’s diseases.
The next two sections will cover pharmacological management of the symptoms of idiopathic PD. It is important to note that non-pharmacological management is also incredibly important, including speech and language therapy, counselling, psychological support, physiotherapy and occupational therapy.
Pharmacological management of motor symptoms
Treatment is to manage symptoms; at present we do not have a way to slow disease progression. The aim is to minimise the frequency and severity of ‘off’ periods, when patients feel their movements slowing and becoming increasingly difficult to initiate.
Diagnosis and treatment initiation should only be done by those with expertise in movement disorders. The first-line therapy depends on whether motor symptoms are affecting the patient’s quality of life. NICE suggests the following:
| If motor symptoms are affecting quality of life | Trial levodopa (+ decarboxylase inhibitor) |
| If motor symptoms are NOT affecting quality of life | Trial levodopa (+ decarboxylase inhibitor)
or dopamine agonist or monoamine oxidase (MAO) B inhibitor |
| With dyskinesia (can be secondary to levodopa) or motor fluctuations, including medicines ‘wearing off’, despite optimal levodopa therapy | Offer an adjunct to levodopa (+ decarboxylase inhibitor):
either dopamine agonist or MAO B inhibitor or catechol O methyl transferase (COMT) inhibitor |
Some further information about the above medications is as follows:
- Levodopa is nearly always combined with a decarboxylase inhibitor, either carbidopa or benserazide (as co-careldopa and co-beneldopa respectively), to prevent its conversion to dopamine in the peripheral circulation. This increases the amount of levodopa that reaches the CNS and reduces side effects.
- Dopamine agonists include ropinirole, rotigotine and pramipexole. Apomorphine is a liquid dopamine agonist preparation, which is fast acting and can help with the management of off periods.
- MAO B inhibitors reduce the breakdown of dopamine within the CNS and include selegiline, rasagiline and safinamide.
- COMT is an enzyme that breaks down levodopa, and its inhibitors prolong the activity of the levodopa. Examples include entacapone and tolcapone. They can only be used as an adjunct to levodopa.
Other treatment options include:
- Amantadine: considered if medication-induced dyskinesia is not managed by alternative agents. Side effects include ataxia, slurred speech, confusion, dizziness and livedo reticularis.
- Deep brain stimulation: can be considered when medical therapy alone is ineffective or insufficient.
A summary of the potential harms and benefits of the main drugs used in idiopathic PD is as follows:
| Levodopa | Dopamine agonists | MAO B inhibitors | COMT inhibitors | Amantadine | |
|---|---|---|---|---|---|
| Motor symptoms | More improvement | Improvement | Improvement | Improvement | No improvement |
| Activities of daily living | More Improvement | Improvement | Improvement | Improvement | No improvement |
| Motor complications | More | Fewer | Fewer | Fewer** | Fewer** |
| Adverse events | Fewer specified adverse events* | More specified adverse events*; overall intermediate risk of adverse events | Fewer adverse events | More adverse events | Not known |
| Hallucinations | Lower risk** | Higher risk | Lower risk | Lower risk | Not known |
| Off time | More off time reduction** | More off time reduction | Off time reduction | Off time reduction | Not known |
* Excessive sleepiness, hallucinations and impulse control disorders
** Not included in NICE guideline tables but added here for completeness
The side effect profiles are similar across the four main treatments (levodopa, dopamine agonists, MAO B and COMT inhibitors) but vary in severity. Hallucinations, impulse control disorders, psychosis and dyskinesias are related to increased dopamine activity and are most severe with dopamine agonists. Side effects common to all drug classes mentioned in Table 2 and sometimes due to the Parkinson’s disease itself, include dry mouth, nausea and low blood pressure (most commonly orthostatic),
- MAO B inhibitors are mostly well tolerated, although they have been known to cause serotonin syndrome, especially if taken alongside SSRIs or other drugs that increase serotonin, and these should therefore be avoided.
- COMT inhibitors can cause gastrointestinal upset; tolcapone therapy requires careful monitoring due to the risk of hepatotoxicity.
- Psychotic symptoms (hallucinations or delusions) can occur with all treatments and can also occur later on due to the disease itself. Hallucinations are most commonly visual, like in Lewy body dementia. They do not always need treatment if well tolerated. If needed, the offending medication can be reduced, and if there is no cognitive impairment, quetiapine can be considered. Clozapine is an alternative if standard treatment is ineffective. NICE recommends that olanzapine should NOT be offered due to its possible worsening of motor symptoms.
- Impulse control disorders may manifest as gambling, hypersexuality, binge eating or obsessive shopping, and can develop at any time in the disease course. Risk factors include high alcohol consumption, smoking and history of impulsive behaviours. If these develop, the NICE recommendation is to reduce the dose of the dopamine agonist or, if this is not sufficient, the medication may need to be discontinued.
- Excessive sleepiness can be related to the disease itself or dopamine agonists. If this develops the patient must not drive and needs to inform DVLA. It is also important to consider any hazards at work. If reducing the medication is not possible then modafinil can be considered.
The pharmacological response threshold increases as the disease progresses and thus patients require increasing doses of levodopa and additional agents for symptom control. This reduces the therapeutic window between a sufficient motor response and dyskinesia, resulting in increasing difficulty managing ‘off’ periods and dyskinesias later in the disease course. Gait freezing can also develop, even when other motor symptoms are well controlled.
Another important side effect is neuroleptic malignant syndrome. This can occur on abrupt withdrawal of medication or in patients initiated on antipsychotic treatment. This is important to consider when patients develop poor absorption, for example secondary to diarrhoea or vomiting, or if they become unable to take their medication orally due to confusion or an unsafe swallow. Levodopa is a medication that is particularly at risk of poor absorption. In such cases either an NG tube can be considered or the oral medication can be converted into the equivalent dose as a dopamine agonist patch. If anti-emetics are required, domperidone is the medication of choice in idiopathic PD, as it does not cross the blood-brain barrier and therefore does not cause extrapyramidal side effects.
Management of other symptoms
Along with the traditional motor symptoms managed with the dopamine treatments above, there are other motor and non-motor symptoms of PD which require different treatment.
Other motor symptoms include:
- REM sleep disorders: loss of the normal paralysis during this sleep phase, which may result in violent, powerful movements, which may cause harm to the patient or those with whom they share a bed. It can be due to the disease process itself or secondary to medication. If it is due to the latter, the offending medication should ideally be discontinued; if this is not an option or does not work, clonazepam or melatonin can be trialled. Note that REM sleep disorders are not the same disease process as sleepwalking or night terrors common in childhood, which occur in the non-REM sleep phase.
- Restless leg syndrome.
- Nocturnal akinesia: reduced or absent movement overnight, hindering re-positioning and ultimately causing pain and sleep impairment. Thus, it is important to use long-acting forms of dopamine overnight.
- Dysphagia: impaired swallowing in PD is multifactorial. It causes two major complications: an inability to meet nutritional requirements and a risk of aspiration. Patients may eventually need a gastrostomy, although this does not eliminate the risk of salivary aspiration and some patients may decide to risk feed for pleasure alongside the gastrostomy.
- Sialorrhea (drooling): thought to be due to increased saliva secretion, an inability to maintain saliva in the mouth due to head drooping and hypomimia, and impaired saliva clearance. Treatment involves behaviour modification (such as frequent conscious swallowing), dopamine treatment, glycopyrronium bromide and botox injections.
Psychiatric symptoms include:
- Depression: the aetiology of depression in PD is not well understood but it occurs in around 35% of patients and is likely often multifactorial. NICE recommends psychosocial interventions first, such as a physical activity programme, a peer support group, a guided self-help programme or CBT (cognitive behavioural therapy). If these do not help then antidepressant medication such as an SSRI can be trialled.
- Dementia: there are two dementias associated with lewy body deposition – PD dementia and Lewy body dementia. In PD dementia, cognitive impairment is a late sign usually occurring many years after the motor symptoms have developed. In Lewy body dementia, cognitive impairment is an early symptom with motor symptoms developing after or at the same time, and progressing together. Management of these conditions is similar to other dementias such as Alzheimer’s and involves cognitive therapies along with medications.
Autonomic symptoms:
- Constipation: often occurs early and is likely multifactorial, partly due to autonomic dysfunction.
- Gastroparesis: affects >70% of individuals with PD. Although often asymptomatic, it is of particular importance in regards to levodopa treatment as delayed absorption causes delayed onset of action.
- Bladder dysfunction: can present as either an overactive bladder/urge incontinence, nocturia or less commonly urinary retention. Retention increases the risk of a urinary tract infection, which is an important cause of acute neurological deterioration. Overactive bladder can be treated with anticholinergic agents.
- Orthostatic hypotension: more commonly seen in later stages of the disease. Unfortunately, PD medication can precipitate or worsen hypotension. The advice is to stop possible contributing medications such as antihypertensives and diuretics, avoid dehydration and optimise cardiac function. If lifestyle measures are not sufficient then midodrine is first line and fludrocortisone is second line.
- Sexual dysfunction: erectile dysfunction or ejaculation difficulties in men and loss of lubrication and involuntary urination in women. Sexual counselling is important. Sildenafil and apomorphine can be used in erectile dysfunction. Other important factors that contribute to sexual dysfunction include hypersexuality from dopaminergic treatment and the effect low mood has on sexual drive and arousal.
A key miscellaneous symptom is that of:
- Olfactory dysfunction: impaired smell often precedes motor symptoms.
Parkinson’s plus syndromes
Multiple system atrophy (MSA), progressive supranuclear palsy (PSP) and corticobasal degeneration (CBD) often present in a similar way to idiopathic PD but have a different pathogenesis. Unfortunately, they are usually unresponsive to dopamine therapy, or at best respond transiently. A trial of levodopa can therefore help to distinguish them from PD.
Multiple system atrophy
MSA is classified according to the predominant motor symptoms: parkinsonian MSA (MSA-P) or cerebellar MSA (MSA-C). The cerebellar subtype may present with cerebellar ataxia rather than parkinsonism. MSA is characterised by prominent early onset autonomic involvement resulting in bladder problems (most commonly retention, also urgency and incontinence), erectile dysfunction, constipation and significant orthostatic hypotension. MRI showing pontine and cerebellar atrophy can support the diagnosis but is not diagnostic.
Progressive supranuclear palsy
Loss of truncal control and vertical gaze are key features of PSP and result in frequent falls and impaired sight. As the disease progresses the patient can also lose eye movements in the horizontal plane. There are a few different subtypes of PSP, which unfortunately progress more rapidly than idiopathic Parkinson’s disease. Midbrain atrophy can support the clinical diagnosis but is not diagnostic.
Corticobasal degeneration
CBD is a type of frontotemporal dementia. The cortex and basal ganglia are affected resulting in personality changes, memory impairment and difficulties with language or maths along with parkinsonian symptoms. It is a clinical diagnosis with apraxia being a common finding. ‘Alien limb’ is a diagnostic feature of CBD and describes the feeling of disassociation the patient has from the involuntary movements in the affected limb.
Other causes of parkinsonism
Drug-induced parkinsonism
Drug-induced parkinsonism is the second most common cause of parkinsonism after idiopathic Parkinson’s disease. There are a range of different medications that have been identified as triggers including calcium channel blockers, tetrabenazine and metoclopramide, but most commonly it is due to antipsychotic medications resulting in iatrogenic inhibition of dopamine. It is normally more rapid in onset and symmetrical given the drug will affect both sides of the brain equally, with tremor a less prominent feature compared to idiopathic Parkinson’s disease. DaT imaging can help differentiate drug-induced parkinsonism from idiopathic PD or Parkinson’s plus syndromes, as it will normally be negative in drug-induced parkinsonism. Treatment involves stopping the offending drug if possible and/or using antimuscarinics such as procyclidine, benztropine or trihexyphenidyl (benzhexol).
Vascular parkinsonism
Vascular parkinsonism is a clinical syndrome secondary to vascular insults to the basal ganglia. The predominant feature is gait disturbance known as lower body parkinsonism, along with dementia, pyramidal signs and incontinence. Symptoms are normally symmetrical and progress in a stepwise manner. MRI imaging in these patients will typically show significant small vessel disease or basal ganglia lacunar infarcts. This group of patients have minimal response to dopamine therapy if at all. Treatment involves managing vascular risk factors to reduce the risk of disease progression.
Huntington’s disease
Huntington’s is a neurodegenerative condition resulting in a choreiform movement disorder, impaired cognition and emotional/behavioural disturbance. It has autosomal dominant inheritance due to an abnormally long triplet ‘CAG’ repeat in the huntingtin gene on chromosome 4. Disease usually occurs in middle age, age 40-60 years, but onset can be much earlier or later than this. With successive generations there is a risk of elongation of the CAG repeat length, resulting in earlier symptom onset (anticipation). This is much more common when the gene is transmitted through the paternal line.
Clinical onset is insidious, and subtle cognitive and behavioural changes often predate the onset of motor symptoms by a decade or more, but may not be recognised. The defining movement abnormality is chorea, Latin for ‘dance’, characterised by sudden, uncontrollable and involuntary jerking movements of the limbs or face, which may make the patient appear to be dancing or fidgeting. The more severe form is ballism, in which the movements are quite violent and can be distressing for the patient, sometimes resulting in injuries to the patient or others in the vicinity.
Huntingdon’s is a clinical diagnosis although genetic testing can be useful if there is uncertainty such as in de novo cases with no family history. Brain atrophy is prominent and occurs earliest in the caudate nucleus and putamen, with cortical involvement as the condition advances.
Unfortunately, there is currently no way to prevent disease progression, so treatment aims to manage symptoms. Anti-dopaminergic drugs such as tetrabenazine or antipsychotics can be used for movement disorders including chorea. A variety of standard psychiatric drugs are used to treat the behavioural impairments including antidepressants, in particular SSRIs and other mood-stabilising drugs such as valproate or carbamazepine for the irritability. There are no pharmacological options for the cognitive impairment. As the disease progresses, physiotherapy, occupational therapy and speech therapy input are very helpful, and affected individuals may eventually need a wheelchair or be bed bound and need full-time care due to the combination of motor and cognitive impairment.
Wilson’s disease
Wilson’s disease is characterised by liver failure, neuropsychiatric symptoms and movement disorders. It is an autosomal recessive disorder that results in abnormal copper metabolism leading to excessive copper deposition in tissues, most notably the liver, eyes and brain. The defective gene responsible is ATP7B located on chromosome 13. It usually presents between 10-25 years of age. If it presents earlier in life it is normally through liver failure, while those with later presentation predominantly display neurological signs.
The copper in the liver results in hepatitis, which leads over time to cirrhosis. In the brain, copper accumulation, particularly in the basal ganglia, can result in chorea, parkinsonism, dementia, speech disturbance, behavioural and psychiatric symptoms. Corneal deposition leads to green-brown rings around the edge of the iris known as Kayser-Fleischer rings, which can be seen on slit-lamp testing. These deposits do not affect vision and are more commonly seen in those who have neurological involvement compared to those with isolated liver disease. The excess copper can also result in renal tubular acidosis (Fanconi syndrome), haemolysis and blue nails.
Test results include reduced serum caeruloplasmin, reduced total serum copper (due to 95% copper being carried by caeruloplasmin), increased free serum copper and increased 24-hour urinary copper. MRI brain is non specific but may show basal ganglia abnormalities. There is a clinical criteria, ‘a Leipzig score,’ that helps to guide clinicians as to the likelihood of Wilson’s disease.
Treatment is with penicillamine, which chelates copper, enabling its excretion in the urine. Trientine hydrochloride is an alternative chelating treatment. The prognosis is very good with patients leading normal lives with normal life expectancy if the disease is detected early and there is good treatment adherence.
Restless legs syndrome
Restless legs syndrome is a condition that results in a strong and often overwhelming urge to move one’s legs, often accompanied by an unpleasant sensation if the legs are kept still. Its mechanism is unknown. Although similar to akathisia (generalised restlessness), restless legs syndrome is considered a distinct clinical syndrome. It usually occurs during inactivity or at rest in the late afternoon, evening and prior to sleep.
It is more commonly seen in those with PD and often predates the onset of parkinsonism. It can also be related to iron deficiency, and thus all patients should have iron studies performed (in particular ferritin – although remember this is an acute phase reactant so may be raised in infection and inflammation). If ferritin is low, then iron supplements should be prescribed as this may reduce or eliminate the condition. The cause of the iron deficiency, if unknown, may also require investigation using quantitative faecal immunochemical testing (FIT) in line with the two-week-wait colorectal cancer NICE guidelines. Less commonly, restless leg syndrome can be related to renal disease, neuropathy, pregnancy and other sleep disorders.
Management involves walking or stretching exercises and avoiding alcohol, nicotine and caffeine. Medications can also be used, the first line being dopamine agonists and alternatives/additional treatments including gabapentin and benzodiazepines.
Stiff person syndrome
This is a rare condition that is more common in females. It presents mostly between the ages of 30-50 with stiffness and muscle spasms, most commonly of the truncal muscles, which can be painful and over time impair gait, resulting in frequent falls. The spasms can be triggered by emotional stress or environmental stimuli such as an unexpected loud noise, physical touch or cold temperatures.
It is associated with anti-GAD (glutamic acid decarboxylase) antibodies, like in type 1 diabetes but in much higher concentrations, and thus can be associated with T1DM and other related autoimmune conditions, including pernicious anaemia, thyroid disease and vitiligo. The anti-GAD antibodies can be found in either the serum or CSF.
The mainstay of treatment is symptom control with botox, benzodiazepines and neuropathic agents such as gabapentin. There are some immune therapies now to help to slow disease progression including plasma exchange, IVIg and immunosuppressants.
Acute drug reactions to medications affecting dopaminergic transmission
Acute dystonia
Dystonia describes an involuntary muscle contraction, which can be primary or secondary. Cervical dystonia, also known as torticollis, is the most common focal dystonia.
Acute dystonia is rare and usually secondary to anti-dopaminergic agents, including metoclopramide. It is often painful and can be life threatening due to occlusion of the airway depending on the muscle groups affected. Examples include oculogyric crisis causing intermittent deviation of the eyes, often upwards, or laryngeal dystonia, which causes intermittent contractions of the muscles in the larynx and therefore difficulty speaking or changes/hoarseness to the voice.
If the patient has been exposed to an anti-dopaminergic treatment then benztropine or diphenhydramine should be given intravenously and the offending agent should be discontinued or weaned. It is important to assess for concurrent pathology such as neuroleptic malignant syndrome or metabolic, infectious or toxin causes.
Of note, dopa-responsive dystonia, which presents in childhood, is a rare disorder but one which is treatable, responding to L-dopa or dopamine agonists and is therefore important not to miss.
Tardive dyskinesia
Hyperkinetic movement disorders (including tardive dystonia, myoclonus and tremor) that develop due to prolonged anti-dopaminergic treatment, usually antipsychotic medication but also metoclopramide. Tardive, derived from the Latin for ‘slow’, describes the slow, writhing (choreiform or athetoid) movements often seen in the face, commonly lip smacking, lip puckering and intermittent blinking. The diagnosis is clinical and requires the movements to have been present for at least 4 weeks.
The offending drug should be withdrawn, however that may involve a weaning regime while an alternative medication is uptitrated. Symptoms can last up to 6 months after the offending medication is discontinued, and in unfortunate cases may be irreversible. First-line treatment is tetrabenazine (also used in the management of chorea in Huntington’s disease).
Neuroleptic malignant syndrome
Neuroleptic malignant syndrome, also known as parkinsonism hyperpyrexia syndrome, is a drug reaction that presents similarly to severe parkinsonism with rigidity along with a high fever, confusion or altered behaviour and autonomic dysfunction resulting in labile blood pressures, dilated pupils, tachycardia and sweating. In severe cases the airway may be compromised due to loss of consciousness, or severe rigidity may prevent adequate ventilation. It most commonly occurs in patients recently started on antipsychotic treatment, but can also develop in those whose dopaminergic treatment is abruptly withdrawn. Clinically it can look quite similar to serotonin syndrome and thus it is important to take a thorough drug history.
Treatment involves addressing the precipitant, i.e. stopping the offending antipsychotic medication or restarting the necessary dopamine agonist, alongside managing the fever and any kidney injury or rhabdomyolysis. In severe cases dantrolene, a muscle relaxant, and bromocriptine, a dopamine agonist, can be used.
Ataxia
Ataxia is the loss of coordination, which can cause gait, speech, swallow and balance problems. It is not a specific diagnosis, but a neurological sign which can develop due to damage to a number of different areas within both the peripheral and the central nervous systems. Ataxia due to dysfunction of the cerebellum or its tracts is considered a movement disorder, whereas sensory (peripheral or dorsal column lesions) and vestibular ataxias result in disorders of movement but would not be cared for by a movement disorders specialist.
Sensory ataxia
Sensory ataxia will only briefly be covered here as it is not a movement disorder. It develops due to damage to the somatosensory nerves, inhibiting sensory feedback and therefore proprioception.
Sensory ataxia can be due to peripheral sensory neuropathies or spinal lesions. Peripheral neuropathies are commonly due to diabetes or alcohol excess, but can also be due to nutritional deficiencies, or metabolic, genetic, toxin, vascular and autoimmune causes. Spinal causes are due to damage to the dorsal column of the spinal cord, including tabes dorsalis secondary to syphilis, subacute combined degeneration of the spinal cord due to B12 deficiency (or functional B12 deficiency, as in nitric oxide poisoning), and vascular causes. Gluten ataxia describes ataxia in the presence of the antibodies of gluten sensitivity or coeliac disease, and may occur without gastrointestinal symptoms. Coeliac testing is therefore recommended in those who have unexplained peripheral neuropathies or ataxia.
Cerebellar disease
Cerebellar disease gives a specific set of findings remembered by the acronym ‘DANISH’: dysdiadochokinesia, ataxia, nystagmus, intention tremor, slurred speech and hypotonia. The ataxia can manifest as a wide-based gait, difficulty with the heel-to-shin test, past-pointing and slow hyper and hypometric saccades.
The causes of cerebellar disease can be split into genetic and non-genetic. Non genetic causes include:
- Vascular: stroke
- Autoimmune: MS, immune-mediated (Miller Fisher syndrome), paraneoplastic
- Metabolic: thiamine deficiency, hepatic encephalopathy
- Toxin: alcohol, gluten in coeliac disease
- Infectious: syphilis
- Degenerative: MSA-C
We will focus on a few genetic conditions in more detail.
Spinocerebellar ataxia
Spinocerebellar ataxias (SCA) are a large, complex group of over 20 inherited degenerative conditions presenting with progressive cerebellar ataxia, and named numerically in order of discovery (SCA1, SCA2 etc.). Alongside cerebellar syndromes, the various SCAs can also present with movement disorders, peripheral neuropathies, cognitive impairment, oculomotor/retinal/bulbar symptoms and pyramidal signs. Like Huntington’s disease they are mostly caused by triplet repeats with autosomal dominant inheritance. Most SCAs present in adulthood, however some can present in childhood. Treatment aims to reduce symptoms and maximise function as there are no cures.
Friedreich’s ataxia
Friedreich’s ataxia is an autosomal recessive progressive ataxia due to mutations in the frataxin gene. It is the most common hereditary ataxia and has a mean age of onset of 14 years. It is due to abnormal iron metabolism in the mitochondria leading to increasing cell death over time. It particularly affects the heart, pancreas, and nervous system (specifically the cerebellum, spinal cord and peripheral nerves), and leads to hypertrophic obstructive cardiomyopathy (90%), diabetes and ataxia/loss of proprioception/weakness. The cardiac complications are the leading cause of death.
The first and classical feature is ataxia with gait disturbance. Other symptoms include ataxia of the trunk and limbs, which may be described by the patient as ‘general clumsiness’, cerebellar dysarthria, loss of tendon reflexes with upgoing plantars, and a sensory neuropathy with distal loss of proprioception and vibration sensation, but typically preservation of pain and temperature sensation. Later features include motor weakness, more prominently of the lower limbs, and optic and vestibular atrophy. Other findings include scoliosis. There is generally no cognitive impairment.
There is currently no cure or effective treatment for the disease, so focus is on managing complications, in particular cardiac involvement given the high associated mortality, and helping individuals maintain a normal level of function for as long as possible.
Ataxia telangiectasia
Ataxia telangiectasia is another autosomal recessive ataxia, similar to Fredrich’s ataxia. It is one of the inherited combined immunodeficiency disorders that begins early in childhood. As the name suggests, it causes a progressive cerebellar ataxia resulting in most affected individuals requiring a wheelchair by adolescence, and telangiectasias, spider-like clusters of dilated capillaries most commonly seen around the eyes and cheeks. In addition, it results in recurrent infections (IgA deficiency) and an increased risk of cancer (10-30% lifetime risk), in particular lymphoma and leukaemia.
Functional neurology
Functional neurology can present in many different ways, including with movement disorders. Functional neurological disorder should ideally be a positive diagnosis based on clinical findings rather than a diagnosis of exclusion, although initial tests may be necessary to rule out some disorders with similar presentations. A full discussion is beyond the scope of this chapter.
References
- National Institute of Neurological Disorders and Stroke. Tremor [Internet]. Available from: https://www.ninds.nih.gov/health-information/disorders/tremor [Accessed 22 January 2024]
- Guy’s and St Thomas’ NHS Foundation Trust. Your child’s stereotypies [Pamphlet]. London (UK): Guy’s and St Thomas’ NHS Foundation Trust. 2023. Available from: https://www.evelinalondon.nhs.uk/resources/patient-information/your-childs-stereotypies.pdf. [cited 31 January 2024]
- BMJ Best Practice. Essential tremor [Internet]. British Medical Journal. 2023. Available from: https://bestpractice.bmj.com/topics/en-gb/1089 [Accessed 31 january 2024]
- Korczyn AD. Vascular parkinsonism—characteristics, pathogenesis and treatment. Nature Reviews Neurology. 2015 Apr 28;11(6):319–26
- Okunoye O, Horsfall L, Marston L, Walters K, Schrag A. Mortality of People with Parkinson’s Disease in a Large UK‐Based Cohort Study: Time Trends and Relationship to Disease Duration. Movement Disorders. 2021; 36(12): 2811-2820
- National Institute for Health and Care Excellence. Parkinson’s disease in adults [Internet]. NICE. Available from: https://www.nice.org.uk/guidance/ng71 [Accessed 23 January 2024]
- Aarsland D, Påhlhagen S, Ballard CG, Ehrt U, Svenningsson P. Depression in Parkinson disease—epidemiology, mechanisms and management. Nature Reviews Neurology [Internet]. 2012;8(1):35–47. Available from: https://www.nature.com/articles/nrneurol.2011.189
- National Institute for Health and Care Excellence. Depression in adults with a chronic physical health problem [Internet]. NICE; 2009. Available from: https://www.nice.org.uk/guidance/cg91. [Accessed 23 January 2024]
- Chen Z, Li G, Liu J. Autonomic dysfunction in Parkinson’s disease: Implications for pathophysiology, diagnosis, and treatment. Neurobiology of Disease. 2020;134:104700. Available from: https://www.sciencedirect.com/science/article/pii/S0969996119303754
- International Parkinson and Movement Disorder Society. Orthostatic Hypotension in Parkinson’s Disease: Essential Facts for Patients [Internet]. Available from: https://www.movementdisorders.org/MDS/Resources/Patient-Education/Orthostatic-Hypotension-in-Parkinsons-Disease.htm. [Accessed 23 January 2024]
- BMJ Best Practice. Parkinson’s disease [Internet]. British medical journal. 2023. Available from: https://bestpractice.bmj.com/topics/en-gb/147. [Accessed 23 January 2024]
- BMJ Best Practice. Huntington’s disease [Internet]. British Medical Journal. 2022. Available from: https://bestpractice.bmj.com/topics/en-gb/513 [Accessed 28 January 2024]
- BMJ Best Practice. Wilson’s disease [Internet]. British medical journal. 2023. Available from: https://bestpractice.bmj.com/topics/en-gb/427 [Accessed 28 January 2024]
- National Institute for Health and Care Excellence. Restless legs syndrome [Internet]; 2022. Available from https://cks.nice.org.uk/topics/restless-legs-syndrome/ [Accessed 22 January 2024]
- Stiff-Person Syndrome | National Institute of Neurological Disorders and Stroke [Internet]. www.ninds.nih.gov. [cited 22 January 2024]. Available from: https://www.ninds.nih.gov/health-information/disorders/stiff-person-syndrome
- BMJ Best Practice. Dystonias. [Internet]. British medical journal. [cited 27 January 2024]. Available from: https://bestpractice.bmj.com/topics/en-gb/1096
- Tardive dyskinesia. BMJ Best Practice [Internet]. British medical journal. [cited 27 January 2024]. Available from: https://bestpractice.bmj.com/topics/en-gb/3000325
- BMJ Best Practice. Neuroleptic malignant syndrome. [Internet]. British medical journal. [cited 27 January 2024]. Available from: https://bestpractice.bmj.com/topics/en-gb/3000227
- BMJ Best Practice. Evaluation of ataxia. [Internet]. British medical journal. 2024. [cited 28 January 2024]. Available from: https://bestpractice.bmj.com/topics/en-gb/1097
- NHS Choices. Types – Ataxia [Internet]. NHS. 2019. [cited 28 January 2024]. Available from: https://www.nhs.uk/conditions/ataxia/symptoms/
- Autosomal dominant spinocerebellar ataxias. UpToDate [Internet]. [cited 2 May 2024] Available from: https://www.uptodate.com/contents/autosomal-dominant-spinocerebellar-ataxias#H332089703
- National Institute of Neurological Disorders and Stroke. Friedreich Ataxia. [Internet]. www.ninds.nih.gov. 2023. [cited 28 January 2024] Available from: https://www.ninds.nih.gov/health-information/disorders/friedreich-ataxia
- Friedreich ataxia — Knowledge Hub [Internet]. GeNotes. [cited 28 January 2024]. Available from: https://www.genomicseducation.hee.nhs.uk/genotes/knowledge-hub/friedreich-ataxia
- Ataxia telangiectasia — Knowledge Hub [Internet]. GeNotes. [cited 28 January 2024]. Available from: https://www.genomicseducation.hee.nhs.uk/genotes/knowledge-hub/ataxia-telangiectasia
Multiple sclerosis and neuroinflammatory disorders
Overview of multiple sclerosis
Multiple sclerosis (MS) is an immune-mediated demyelinating condition of the central nervous system, clinically defined as two or more episodes of neurological dysfunction affecting the brain, spinal cord or optic nerves separated in time and space. The hallmark of MS is symptomatic episodes of demyelination occurring months to years apart and affecting different anatomical locations.
The cause of MS is unknown, but it likely involves a combination of genetic factors, making some individuals more susceptible to the disease. Non-genetic triggers such as a preceding viral infection or low vitamin D levels can also cause an autoimmune response against myelinated axons in the CNS. A characteristic feature of MS is the periventricular infiltration of lymphocytes and macrophages.
There is a marked geographic variation in the incidence of MS with the incidence being lower in equatorial regions, which supports the probability of an environmental trigger. MS classically presents in white women between the ages of 20 and 40.
Clinical features and diagnosis of multiple sclerosis
Symptoms of MS
The symptoms of MS vary and depend on the location of the demyelinating lesion. Common presentations of MS include optic neuritis, usually unilateral, and transverse myelitis. Individuals can also present with brainstem syndromes including internuclear ophthalmoplegia, cerebellar syndromes characterised by ataxia, and sensory syndromes. In addition, MS can present with symptoms of cognitive decline, depression or psychosis. As neural inflammation resolves and remyelination occurs there can be some recovery of function.
MS seems to be less active during pregnancy, especially in the last trimester, however many patients with MS have a relapse of symptoms within 3 months of delivery. MS does not affect fertility or increase the risk of miscarriage.
Uhthoff’s phenomenon is a transient worsening of symptoms when the body is overheated, such as in hot weather, during vigorous exercise or in a hot shower, and is often observed with MS.
Internuclear ophthalmoplegia (INO) is a gaze disorder where the affected eye shows impairment of adduction on conjugate lateral gaze. This is due to demyelination of the medial longitudinal fasciculus, a heavily myelinated tract connecting the oculomotor nucleus on the side of the lesion with the contralateral abducens nucleus. The commonest causes of INO are MS and brainstem infarcts.
Optic neuritis and MS
Optic neuritis is the first demyelinating event in 20% of patients who are diagnosed with MS. Approximately 40% of patients with MS experience optic neuritis at some point during their disease course.
Symptoms of optic neuritis include:
- Pain which is worsened by eye movement
- Temporary reduction in vision, the extent of which varies, and which can be permanent
- Visual field loss
- Loss of colour vision and colour perception
- Flashing lights, especially with eye movements
- Rapid afferent pupillary defect (RAPD), occurs due to asymmetrical disease of the optic nerve. The affected pupil will dilate to the light stimulus instead of constricting
A key differential for a RAPD is the Holmes-Adie pupil, which is often idiopathic but can be caused by a lesion in the efferent parasympathetic pathway. It is characterised by slow and incomplete constriction of the pupil to light, and, after the pupil has constricted, it remains so for a long time (tonic pupil). The full syndrome also includes an absence of deep tendon reflexes (although an abnormal pupil may be seen in isolation).
Diagnosis of MS
Diagnosis is based on clinical findings and further confirmatory tests, such as:
- MRI brain and spine: imaging modality of choice for both confirming and monitoring disease progression
- Evoked potentials: results not specific for MS but can be useful for the identification of subclinical lesions. Visual evoked potential testing can reveal slowing of conduction in the optic nerve due to demyelination
- Lumbar puncture: CSF evaluated for oligoclonal bands (OCB) and intrathecal IgG production. CSF protein levels can also be elevated. CSF OCB detection is not specific for MS and 5-10% patients diagnosed with MS do not show CSF abnormalities
Diagnosis of MS is made as per the McDonald diagnostic criteria, comprising clinical, radiographic, and laboratory factors. MS can be diagnosed when a patient has experienced at least two clinical attacks, or has evidence of MS plaques in at least two distinct brain areas on an MRI. This is described as having plaques separated in time and space.

Image Source: doi.org (2022), s00062-022-01144-3, Licensed under a creative commons licence. Available for free at: https://doi.org/10.1007/s00062-022-01144-3 (Accessed: 17 July 2024)
Classification of MS
- Relapsing remitting MS (RRMS): approximately 85% of cases. Characterised by unpredictable relapses followed by periods of remission, which can last for months to years. Deficits caused by relapses may resolve or be permanent. If they resolve completely between attacks it is classified as benign MS.
- Primary progressive MS (PPMS): approximately 10% of cases. Patients do not recover from their first relapse, and symptoms decline continuously without clear attacks or episodes of remission. This subtype is common in patients with older disease onset.
- Secondary progressive MS (SPMS): seen in approximately 80% of patients who initially present with RRMS. Characterised by progressive neurological decline between acute attacks without definite periods of remission. SPMS causes the highest amount of disability.
- Progressive relapsing MS (PRMS): characterised by progressive worsening of neurological symptoms with superimposed flares from the onset of MS.
- Clinically isolated syndrome (CIS): a single episode of neurological symptoms lasting over 24 hours. Individuals who develop CIS may or may not go on to develop MS. Further investigation with an MRI is recommended. The detection of oligoclonal bands in CSF is the most sensitive predictor of conversion from CIS to MS.
Management of multiple sclerosis
Treatment of MS has two main aspects: treatment of acute flares and treatment of the underlying condition with disease-modifying agents. Disease-modifying treatments are not routinely administered during an acute flare.
Treatment of acute relapse
- Methylprednisolone: accelerates recovery from an acute attack of MS; it does not alter the disease course. Systematic reviews have shown the efficacy of corticosteroids in reducing symptoms of an acute relapse however the optimal dose, route of administration and duration of treatment remain unclear.
- Plasma exchange: used short term during acute attacks if steroids are ineffective or are contraindicated.
Disease-modifying treatment
- Interferons (IFN), e.g. IFN beta, peginterferon
- Monoclonal antibodies, e.g. natalizumab, alemtuzumab, ocrelizumab
- Sphingosine-1-phosphate (S1P)-receptor modulators, e.g. Fingolimod, Siponimod
- Cyclophosphamide can be used for the treatment of aggressive MS
Note that natalizumab has been associated with progressive multifocal leukoencephalopathy (PML), a rare and often fatal condition caused by the JC virus.
The Expanded Disability Status Scale (EDSS) is a scale used for quantifying disability in patients with multiple sclerosis and monitoring the changes in the level of their disability over time. It takes into account how ambulant patients are, and the severity of pyramidal, brainstem and cerebellar symptoms. In addition to this, bowel, bladder and visual symptoms are ranked. It has been widely used in clinical trials and in assessing people with MS.
Neuroinflammatory disorders
Neuromyelitis optica spectrum disorder
Previously known as Devic disease, neuromyelitis optica (spectrum disorder) (NMO)(SD) presents with recurrent episodes of unilateral or bilateral optic neuritis associated with myelopathy.
It is caused by an immune-mediated attack on aquaporin 4 (AQP4), which is a neural channel protein. NMO-IgG antibody selectively binds AQP4 causing demyelination and axonal death.
Symptoms caused by optic neuritis include:
- Loss or blurring of vision; NMOSD often affects both eyes, unlike MS
- Eye pain with movement
- Loss of colour vision
Symptoms caused by transverse myelitis include:
- Loss of bowel or bladder control or urinary retention
- Spasticity (increased muscle tone or stiffness in the arms or legs)
- Weakness, numbness, or loss of sensation
Blood testing for the AQP4 antibody is highly specific (>99%) and its sensitivity ranges from 48-87%.
Treatments consist of IV corticosteroids and plasma exchange. Immunosuppressive drugs such as mycophenolate mofetil, rituximab, and azathioprine have also been found to be beneficial in treatment. MS treatment is often ineffective in NMO.
Transverse myelitis
This describes inflammation of both sides of a section of the spinal cord due to damage to the myelin sheath.
Symptoms include:
- Pain
- Sensory loss in upper and lower limbs
- Motor weakness in upper and lower limbs
- Bladder and bowel dysfunction
Various conditions can cause transverse myelitis:
- Immune disorders such as MS, NMO, and post-infectious or post-vaccine autoimmune phenomena.
Myelin oligodendrocyte glycoprotein (MOG) antibody associated disease (MOGAD) causing autoimmune demyelination of the CNS, in particular the optic nerves, brain and spinal cord, can also cause transverse myelitis. Anti-MOG antibodies are present in cases of MOGAD - Viral infections, including herpes simplex, varicella zoster, cytomegalovirus, Epstein-Barr virus, hepatitis B, mumps, measles, and rubella
- Bacterial infections such as syphilis, TB, actinomyces, pertussis, tetanus, diphtheria, and Lyme disease
- Fungal infections including aspergillus
- Parasites, including toxoplasmosis, cysticercosis, and schistosomiasis
- Inflammatory disorders, such as sarcoidosis, systemic lupus erythematosus, Sjögren’s syndrome, mixed connective tissue disease, scleroderma, and Beçhet’s syndrome

Image Source: Wikimedia Commons (2010). Transverse_myelitis_MRI, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/File:Transverse_myelitis_MRI.jpg (Accessed: 17 July 2024)
Transverse myelitis is diagnosed by MRI of the spinal cord, which confirms the presence of a lesion. An MRI brain may provide clues to underlying causes, especially MS.
Blood tests may be performed to rule out differentials and identify the cause of transverse myelitis, including the presence of autoantibodies (anti-AQP4, anti-myelin oligodendrocyte) and paraneoplastic antibodies. CSF analysis often shows elevated protein and leukocytes.
Management depends on the cause.
Autoimmune encephalitis
Autoimmune encephalitis comprises a group of non-infectious immune-mediated inflammatory disorders of the brain involving the cortical deep grey matter, with or without involvement of white matter, meninges, or spinal cord.
- Common causes of autoimmune encephalitis include acute disseminated encephalomyelitis (ADEM) and anti-NMDA (N-methyl-D-aspartate) receptor encephalitis.
- Paraneoplastic encephalitis is seen most with small cell lung, breast, ovarian and testicular cancer, and Hodgkin’s lymphoma. Antineoplastic antibodies (Anti-Hu, Yo, Ri and Ma) are often positive.
- MRI may often be normal in autoimmune encephalitis therefore, diagnosis is made by CSF analysis including analysis for CSF antibodies.
References
- Polman CH, Reingold SC, Edan G, et al. Diagnostic criteria for multiple sclerosis: 2005 revisions to the “McDonald Criteria”. Ann Neurol. 2005 Dec;58(6):840-6
- Brooks BR, Miller RG, Swash M, et al; World Federation of Neurology Research Group on Motor Neuron Diseases. El Escorial revisited: revised criteria for the diagnosis of amyotrophic lateral sclerosis. Amyotroph Lateral Scler Other Motor Neuron Disord. 2000;1:293-299
- Lublin FD, Reingold SC, Cohen JA, et al. Defining the clinical course of multiple sclerosis: the 2013 revisions. Neurology. 2014 Jul 15;83(3):278-86
- Wingerchuk DM, Lucchinetti CF. Comparative immunopathogenesis of acute disseminated encephalomyelitis, neuromyelitis optica, and multiple sclerosis. Curr Opin Neurol. 2007 Jun;20(3):343-50
- Compston A, Coles A. Multiple sclerosis. Lancet. 2008 Oct 25;372(9648):1502-17
- West TW, Hess C, Cree BA. Acute transverse myelitis: demyelinating, inflammatory, and infectious myelopathies. Semin Neurol. 2012 Apr;32(2):97-113
- Graus F , Titulaer MJ , Balu R , et al . A clinical approach to diagnosis of autoimmune encephalitis. Lancet Neurol2016;15:391–404
Motor neuron disease
Overview of motor neuron disease
Motor neuron disease (MND) is a heterogeneous group of incurable neurodegenerative disorders affecting the motor neurons. The disease is characterised by progressive degeneration of both upper (UMN) and lower motor neurons (LMN). Sensory examination in patients with MND is often unremarkable as there is no sensory neuron involvement.
MND is often classified as affecting primarily the upper or lower motor neurons, or involving both, and symptoms can vary depending on which neurons are affected.
Types of MND
Amyotrophic lateral sclerosis (ALS)
ALS is the most common MND of adult onset with incidence peaking at the age of 75 years. It is a fatal disorder characterised by progressive skeletal muscle weakness, fasciculation, spasticity and atrophy due to UMN and LMN degeneration. Therefore ALS presents with a combination of both UMN and LMN signs.
ALS has sporadic and familial forms; 5-10% of cases are due to a superoxide dismutase-1 (SOD1) gene mutation.
It often presents with asymmetric lower limb motor neuropathy. However, regardless of which muscles are first affected, the symptoms spread to affect all four limbs and bulbar muscles. Death in ALS occurs due to progressive respiratory muscle paralysis.
Riluzone, a glutamate release inhibitor, is licensed for slowing down ALS progression, but there is no cure.
Primary lateral sclerosis (PLS)
PLS is a rare idiopathic disorder involving mostly UMNs. It is characterised by progressive spinobulbar weakness, and usually presents with lower limb spasticity with hyperactive reflexes and clonus. LMNs are generally spared.
Hereditary spastic paraparesis
This group of genetic disorders is characterised by a slowly progressive spastic, UMN pattern of weakness. Early presentations are with gait disturbance; upper limb involvement is usually mild.
Genetically they are classified by mode of inheritance, with the autosomal dominant form most common, however autosomal recessive and X-linked forms also occur. There can be significant clinical overlap with PLS.
Progressive bulbar palsy
This presents with LMN weakness of the glossopharyngeal, vagus, accessory and hypoglossal nerves (CN IX-XII) due to degeneration of their motor nuclei in the medulla. Symptoms include tongue weakness and fasciculations, dysarthria and dysphagia. Patients may present with a history of regurgitation of food and fluids, tongue wasting and fasciculations. Spinal cord involvement often occurs late in the disease course. Infantile forms also exist.
Spinal muscular atrophy
This is a genetic disorder characterised by degeneration of LMNs with no sensory or UMN involvement. The commonest inheritance pattern is autosomal recessive, however autosomal dominant and X-linked forms do exist. It is often first diagnosed in childhood and presents with weakness and progressive muscle atrophy
X-linked spinobulbar muscular atrophy (Kennedy disease)
This is an adult-onset X-linked recessive trinucleotide expansion disorder, with CAG repeats in the androgen receptor gene. It is characterised by progressive bulbar and limb muscle weakness, but also presents with endocrine disturbances such as androgen insensitivity. As an X-linked disorder it exclusively affects males but is transmitted by female carriers.
Post-polio syndrome
This presents after an acute attack of paralytic poliomyelitis and is characterised by late-onset skeletal and bulbar muscle weakness. Is a diagnosis of exclusion.
Diagnosis of MND
Electromyography (EMG) and nerve conduction studies (NCS) are the most useful investigations in the diagnosis of motor neuron disease. Findings include:
- Evidence of widespread denervation
- Preservation of motor conduction velocity
The exception is primary lateral sclerosis, as this typically only involves the upper motor neurons.
Differentials to consider
Key differentials for motor neuron disease include:
- Cervical radiculopathy – may present with sensory symptoms as well; MRI will show disc compression
- Syringomyelia – loss of sensitivity to pain or temperature, primarily in the upper limbs; MRI will show a fluid-filled syrinx
- Motor neuropathies, e.g. multifocal motor neuropathy (MMN) – both MMN and MND present with progressive pure motor weakness. MMN only has LMN weakness, and the progression of weakness is typically slower than in MND. Additionally, NCS will differentiate between MND and MMN: in MMN there will be a conduction block, however motor nerve conduction velocities are preserved in MND
- Inflammatory myopathies, e.g. inclusion-body myopathy – muscle biopsy and EMG will differentiate these from MND. EMG can confirm the presence of a myopathy and identify a muscle biopsy site. Additionally, patients with MND, depending on the pattern of weakness (UMN vs LMN), will show abnormal electrical activity in their muscles, e.g. fasciculations, which will be recorded on an EMG
Staging and management of MND
There is no formal staging for MND. However bulbar presentations have been associated with a poorer prognosis as respiratory muscles are involved earlier, and patients are generally dependent on parenteral nutrition and have a high risk of aspiration. Death is usually within 1 to 5 years of diagnosis.
Management is guided by a multidisciplinary team. Discussions around the ceiling of care should be had early, including patient preference for the use of non-invasive ventilation. Additionally discussions surrounding long-term feeding options are also best had early in the disease course. Long-term PEG (percutaneous endoscopic gastrostomy) or RIG (radiologically inserted gastrostomy) feeding is often recommended, especially if the patient has bulbar weakness.
Riluzone is the only pharmacological treatment currently licensed for MND and has been shown to increase average survival by 2-3 months.
References
- McDermott C J, Shaw P J. Diagnosis and management of motor neurone disease BMJ 2008; 336 :658 doi:10.1136/bmj.39493.511759.BE
- Brooks BR, Miller RG, Swash M, et al; World Federation of Neurology Research Group on Motor Neuron Diseases. El Escorial revisited: revised criteria for the diagnosis of amyotrophic lateral sclerosis. Amyotroph Lateral Scler Other Motor Neuron Disord. 2000;1:293-299
- Yedavalli VS, Patil A, Shah P. Amyotrophic lateral sclerosis and its mimics/variants: a comprehensive review. J Clin Imaging Sci. 2018. 8:53
- Oskarsson B, Gendron TF, Staff NP. Amyotrophic lateral sclerosis: an update for 2018. Mayo Clin Proc. 2018 Nov. 93 (11):1617-28
- Wais V, Rosenbohm A, Petri S, et al. The concept and diagnostic criteria of primary lateral sclerosis. Acta Neurol Scand. 2017 Sep. 136 (3):204-11
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

