


 Close
 30th December 2024
Presentation and management of immune-mediated toxicities
Presentation of immune-mediated toxicities
Immune-mediated toxicity can affect any organ system and can range in severity from mild to life threatening. Presenting features are, therefore, broad. It may be easiest to consider presentation by organ system – see the subsections below for more detail.
Of note, the risk of immune-mediated toxicity increases in cases where patients are treated with dual ICI therapy.
Immune-mediated toxicity triggered by ICIs is not a direct consequence of ICIs interacting with organ systems. It instead results from an ICI sensitising the body’s immune system and the sensitised immune system, in turn, interacting with an organ to cause side effects. Therefore, symptoms may be delayed and removal of the ICI does not necessarily translate to cessation of symptoms. It is essential to remember that toxicity can occur any time during treatment and can even occur up to one year after cessation of an ICI.
Broad principles of management of immune-mediated toxicities
When assessing immune-mediated toxicity, the oncologist first grades the severity of the reaction by taking a full history and examination. The broad management depends on the severity of symptoms. Generally speaking, management can be summarised as follows:
- Mild reactions (minimally symptomatic)
- Treatment with the ICI may be allowed to continue
- Add treatments for symptomatic relief
- Moderate reactions (limiting activities of daily living)
- Withhold ICI
- Corticosteroids, usually oral prednisolone 0.5-1 mg/kg
- Severe or life-threatening reactions or non-responding moderate reactions
- Withhold or permanently discontinue ICI
- Inpatient treatment with IV methylprednisolone 1-2 mg/kg
- If deteriorating despite this may require other immunosuppressants such as infliximab, mycophenolate mofetil (MMF) or tacrolimus
- Specialty referral
- Consider intensive care admission if organ support required
- In any grade of reaction, monitor closely for deterioration or non-response to treatment; escalate treatment as necessary
- Once symptoms have improved, wean steroids gradually, with the exception of hypophysitis which will require long term oral steroid replacement
- If prescribing high-dose steroids, consider gastroprotection, bone protection and PCP (pneumocystis pneumonia) prophylaxis
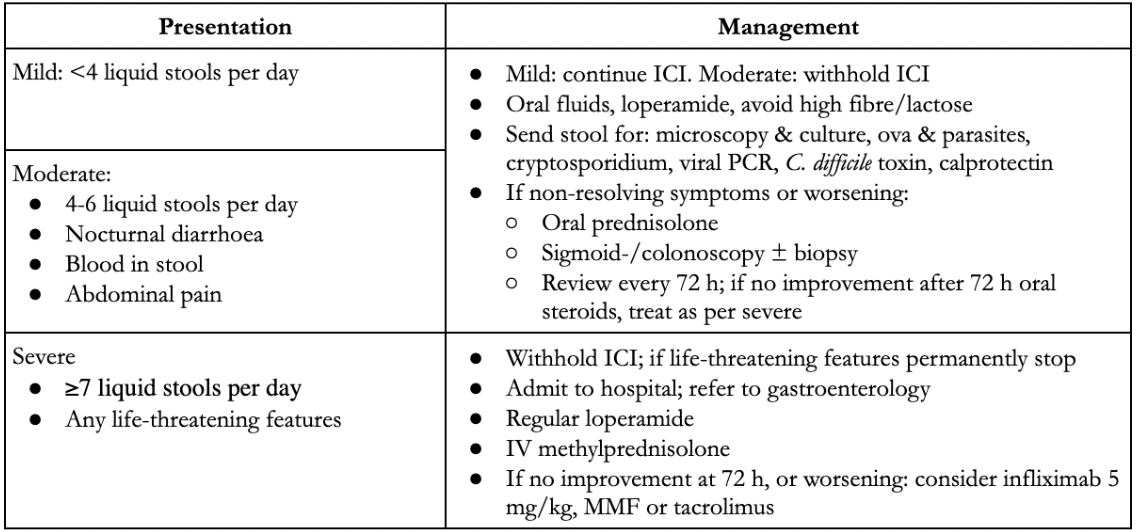
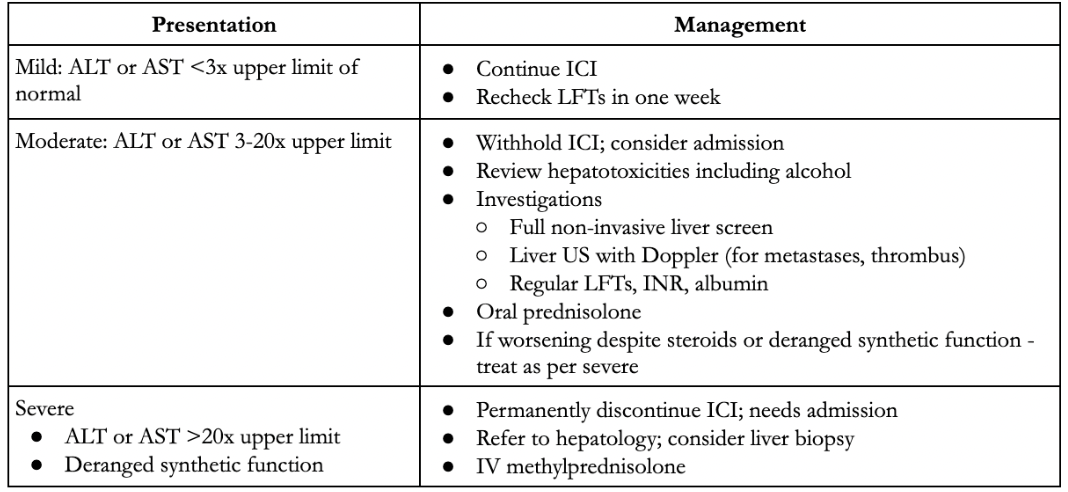
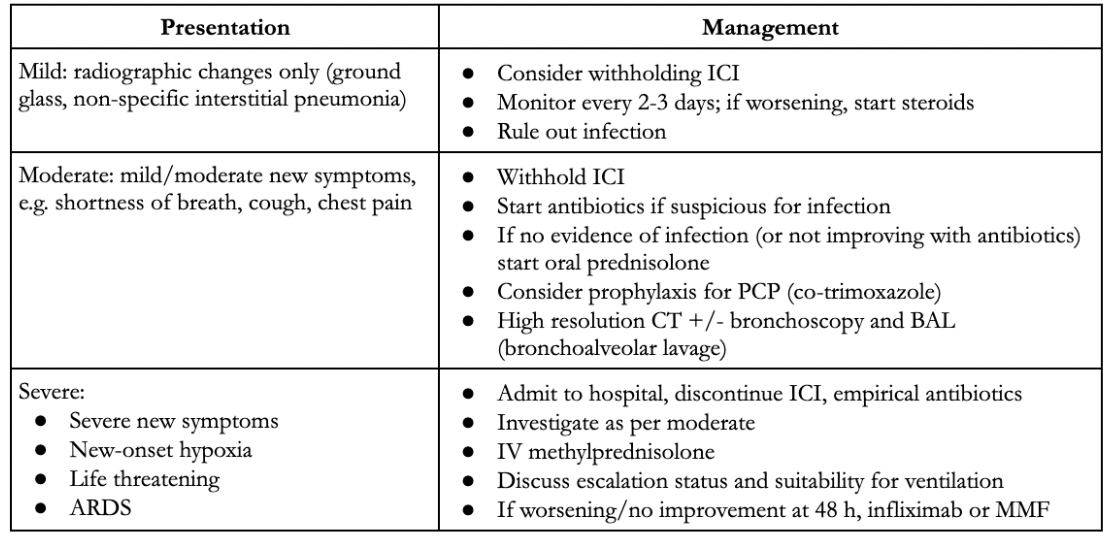
The European Society for Medical Oncology (ESMO) has released comprehensive guidelines to aid in the detection, investigation and management of immune mediated toxicities. The presentation, pertinent investigations and management are summarised by organ system in figures 16-21 below.
Skin toxicities
Skin toxicity presents with a rash, most commonly maculopapular. It may be itchy or painful.
Rarely, severe reactions such as Steven Johnson Syndrome (SJS), toxic epidermal necrolysis (TEN) or bullous dermatitis may occur. These can be life threatening.
| Presentation | Management |
|---|---|
| Mild: <30% body surface area |
|
| Moderate: >30% body surface area, may limit ADLs |
|
Severe:
|
Endocrine toxicities
Endocrinopathies resulting from immune-mediated toxicity can be varied. It is essential to detect and treat hypophysitis early, as otherwise the resultant hypoadrenalism can result in an Addisonian crisis. Thyroid disturbance is common and may occur in 5-10% of patients.
Baseline TSH, T3 are and free T4, pituitary axis bloods (9 am cortisol, ACTH, TSH [thyroid stimulating hormone], T4, LH [luteinising hormone], FSH [follicle-stimulating hormone], oestradiol/testosterone, IGF [insulin-like growth factor]-1, prolactin) and glucose are checked prior to commencing an ICI. TFTs are then monitored regularly throughout treatment and, in some instances, monitored even after cessation of ICI (delayed hypothyroidism/hypophysitis may occur).
| Presentation | Management |
|---|---|
Hypothyroidism
|
If TSH >10 or symptomatic hypothyroidism, start levothyroxine, even with normal T4 |
Thyroiditis
|
|
Hypophysitis
|
|
Diabetes
|
|
Gastrointestinal toxicities (colitis)
Gastrointestinal toxicity is common, with up to 30% of patients experiencing diarrhoea. Severe, high-grade colitis may occur in as many as 1% of patients. This can be life threatening, resulting in perforation or death. It is, therefore, essential to ask about diarrhoea with each cycle and monitor symptoms closely if they occur. Always rule out infection in patients presenting with diarrhoea.
Hepatic toxicities (hepatitis)
Hepatic toxicity or hepatitis is common; 5-10% of patients may present with ICI-induced hepatitis, rising to 30% in patients receiving combined therapy. LFTs are, therefore, measured with each treatment cycle. Severity is determined by the degree of transaminase derangement and presence of derangement in INR or albumin.
Respiratory toxicities (pneumonitis)
Respiratory toxicity, or pneumonitis, is common and can be life threatening. ICIs may be withheld even in mild immune-mediated pneumonitis.
Rare immune-mediated toxicities
It is important to be aware that immune-mediated toxicity can occur in any organ system and to consider immune-mediated toxicity in any patient with almost any symptom! Generally, management is still based on severity. Most instances of these rare toxicities require referral to the specialist team for ongoing management and advice.
| Neurological |
|
|
| Rheumatological |
|
|
| Renal |
|
|
| Cardiac |
|
|
| Ocular |
|
|
| Haematological |
|
|
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

