


 Close
 23rd May 2025
Pseudohypoparathyroidism
Pseudohypoparathyroidism is caused by insensitivity of target tissue to the action of PTH in the background of normal renal function. This results in hypocalcaemia, hyperphosphataemia and increased PTH concentration.
Causes
Pseudohypoparathyroidism is a rare disorder caused by genetic mutations. There different types are as follows:
- Type 1a has an autosomal dominant inheritance, inherited from the mother. It presents with hormone resistance and a characteristic skeletal phenotype.
- Type 1b is usually less severe, and it may be due to a sporadic mutation, or inherited in an autosomal dominant fashion.
- Type 1c is like type 1a with hormone resistance and Albright’s hereditary osteodystrophy.
- Type 2’s cause has not yet been identified.
Pseudo-pseudohypoparathyroidism is caused by the same mutation as type 1a and 1b but the mutations are inherited from the paternal side rather than maternal. Paternal inheritance leads to no hormone resistance but presents with the same skeletal phenotype.
Presentation
- Asymptomatic
- Signs of hypocalcaemia
- Muscle cramps
- Paraesthesia lips, fingers, toes – common early symptoms
- Muscle twitches, spasms, or tetany – severe hypocalcaemia
- Stridor
- Lethargy and anxiety
- Confusion, convulsions, arrhythmias
- Clinical signs: Chvostek’s sign and Trousseau’s sign
- Hyperphosphataemia
- Nephrolithiasis
- Cataracts because of calcium phosphate deposition in the eye
- Types 1a and 1c have characteristic skeletal phenotype of Albright’s hereditary osteodystrophy
- Short stature (height <10th percentile)
- Round face
- Dental hypoplasia
- Brachymetacarpals
- Brachymetatarsals
- Developmental delay
- Soft tissue calcification/ossification
- Diagnostic sign: metacarpal shortening classically affecting III, IV and V metacarpals which produces dimpling over the knuckles
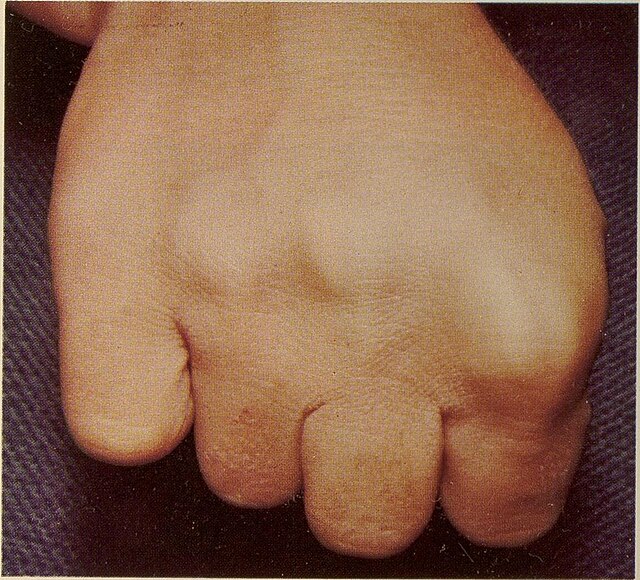
Hands of an adult with Albright’s hereditary osteodystrophy showing knuckle dimpling with clenched fists
Investigations
- Hypocalcaemia, hyperphosphatemia and elevated PTH concentrations with normal Vitamin D strongly point towards pseudohypoparathyroidism.
- Magnesium should be checked to exclude hypomagnesaemia.
- Imaging such as plain radiograph of the hands to reveal metacarpal shortening if skeletal phenotype of Albright’s hereditary osteodystrophy is suspected
- Genetic testing and analysis of GNAS1 gene can confirm diagnosis
Management
The main management involves normalising levels of calcium and phosphate.
Symptomatic hypocalcaemia should be treated as a medical emergency with IV calcium gluconate and ECG monitoring.
Long-term management of hypocalcaemia is with oral calcium supplements such as calcium carbonate or calcium acetate.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

