


 Close
 10th May 2025
Long QT Syndrome
Long QT syndrome (LQTS) is a disease of ventricular repolarization identified by the prolongation of the QT interval on ECG. Normal QT interval is <440 msec in male and <460 msec in female when corrected for heart rate of 60/min.
Diagnostic criteria
- Corrected QT interval (QTc) ≥ 480ms
- LQTS score >3 (See modified long QT syndrome diagnostic score)
- In the presence of cardiac arrest or syncope, a QTc ≥ 460 ms
- Pathogenic genetic mutation irrespective of QT interval
Classification
- Congenital:
- Autosomal recessive: Jervell and Lange-Nielsen syndrome (associated with deafness)
- Autosomal dominant: Also known as Romano Ward Syndrome (has 3 main phenotypes: LQT1, LQT2 and LQT3)
- Acquired: Caused by drugs or electrolyte imbalance
| Drugs |
|---|
|
| Electrolyte disturbance |
|
Table 3: Acquired causes of LQTS
Clinical features
- Asymptomatic
- Sudden cardiac death
- Syncope
- Aborted ventricular arrhythmia including Torsades de pointes (Figure-2)
- Patients with LQT 1 are triggered by physical exercise, specially swimming
- Patients with LQT2 are triggered by noise
- Patients with LQT3 are triggered during sleep
ECG findings
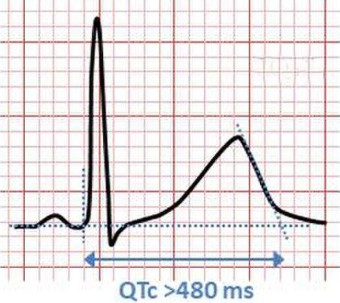
Image Source: Wikimedia Commons (2020). ECG, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/w/index.php?search=long+qt+ecg&title=Special:MediaSearch&go=Go&type=image (Accessed 7 May 2025).
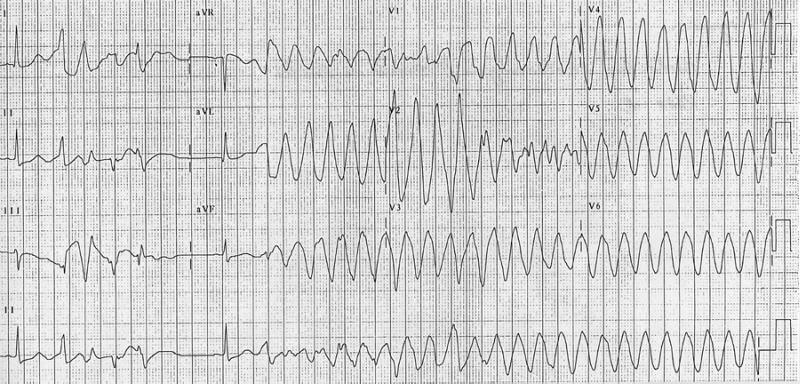
Image Source: Wikimedia Commons (2010). Torsade ECG, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/w/index.php?search=torsade+pointes+ecg&title=Special:MediaSearch&go=Go&type=image (Accessed 7 May 2025).
Management
- Torsades de pointes should be terminated by intravenous Magnesium sulfate. Alternatives are, overdrive pacing and intravenous isoprenaline. Although, isoprenaline should be avoided in congenital long QT syndrome.
- Avoidance of QT prolonging drugs, electrolyte imbalance and genotype specific triggers in all patients
- Asymptomatic congenital LQTS are advised to be treated with beta blockers
- Implantable cardioverted defibrillator (ICD) implantation should be considered in patients with previous cardiac arrest, syncope despite beta blockers and in asymptomatic cases with QTc >500 msec
- Left cardiac sympathetic denervation can be considered in patients who remain symptomatic.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

