


 Close
 23rd May 2025
Acromegaly
Acromegaly is an insidious chronic and progressive disorder caused by the overproduction of GH and characterised by features of gigantism. It is usually caused by a somatotroph adenoma in the adenohypophysis. The incidence of acromegaly is between 40-130 cases per million adults. An excess of GH leads to increased secretion of insulin-like-growth factor-1 (IGF-1) leading to multi-systemic symptoms.
Clinical effects
- Facial: Frontal bossing, macroglossia, prognathism, large nose
- Skin: Hyperhidrosis, increased skin thickness
- Respiratory: Sleep apnoea
- Joint: Osteoarthritis, arthropathy, bone enlargement
- Cardiovascular: Hypertension, arrhythmias, valvular heart disease, congestive cardiac failure, ischaemic heart disease
- Metabolic and electrolyte: diabetes mellitus, impaired glucose tolerance, hypercalciuria
- Organomegaly
- Increased height
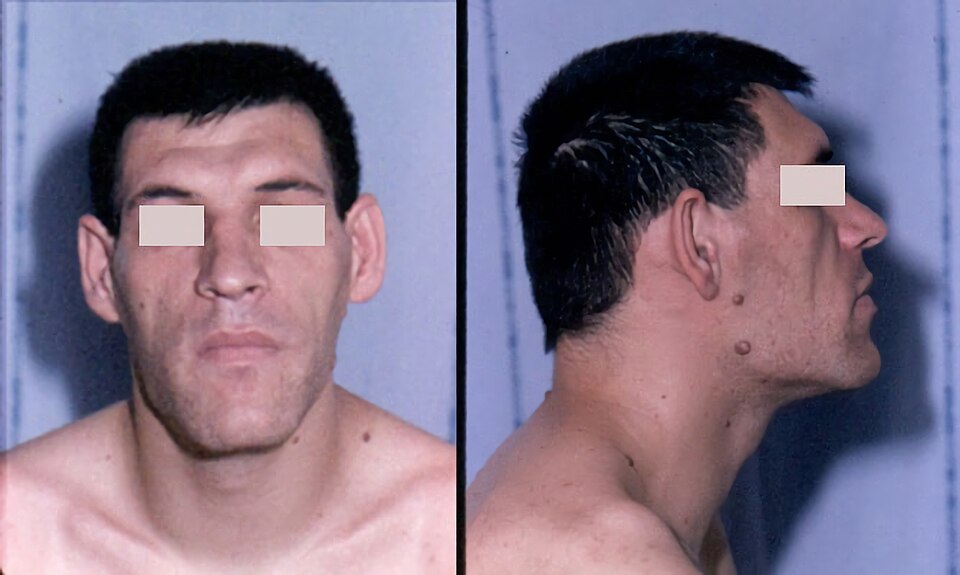
Image Source: Wikimedia Commons (2008). Acromegaly facial Features, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/w/index.php?curid=15072125 (Accessed 13 May 2025).
Investigations
Biochemical
- Excluded in most cases of normal IGF-1 levels
- Random GH >1 microgram/L or >2.5 micrograms/L
- Glucose tolerance test with 75g oral glucose and measuring plasma glucose and GH every 30 mins for 2 hrs. Lack of GH suppression <1 microgram/L (<1 nanogram/mL) suggestive of acromegaly
- Other pituitary hormone plasma levels: cortisol, prolactin, thyroid-stimulating hormone and free thyroxine, follicle-stimulating hormone, luteinising hormone, oestradiol, or testosterone
- Consider genetic testing for AIP
Imaging
- MRI with contrast of pituitary gland
- In <1% of the cases, the above is negative. In this case a CT Thorax, Abdo, Pelvis will likely be needed to locate ectopic hormones producing GH/GHRH
Management
- Transsphenoidal surgery is first-line for enclosed somatotroph microadenomas (< 10mm diameter) and macroadenomas (>10mm diameter)
- If surgery fails, or the tumour is unresectable, somatostatin analogues (SSAs) are used e.g., octreotide with an initial dose of 20mg every month
- If there is mixed GH/PRL release, or IGF-1 levels are <1.5 the upper limit of normal a dopamine agonist, e.g., cabergoline, can be used as an additional treatment
- Pegvisomant, a growth hormone receptor antagonist, is considered in patients who are unsuitable or who have not responded to the above
- If medical and surgical treatments fail, radiotherapy can be attempted
Monitoring
Lifelong monitoring of GH and IGF-1 will be required
Complications
- Cardiovascular (including HTN) (30-40%)
- Sleep apnoea (60-80%)
- Joint (70%)
- Endocrine (50%)
- Pre-cancerous polyps
- Carpal tunnel (64%)
- Hypopituitarism
Prognosis
Surgery is effective in 70-90% of microadenomas and 30-60% of macroadenomas. SSAs control disease in 30-40% of cases.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

