


 Close
 23rd May 2025
Hyperthyroidism
It is important to differentiate between thyrotoxicosis and hyperthyroidism, as these terms are not synonymous:
- Thyrotoxicosis is a referral to hypermetabolic state or symptoms caused by excessive thyroid hormone levels which is usually due to gland hyperactivity (i.e., hyperthyroidism).
- Overt hyperthyroidism is usually the experience of thyrotoxicosis symptoms with the presence of low serum TSH level and high T3 and T4.
- Subclinical hyperthyroidism is notation of asymptomatic patients who will show low serum levels of TSH but normal T3 and T4 levels.
Any condition which results in increased levels of circulating T3/T4 may result in the following clinical signs and symptoms:
- Ocular signs:
- Lid lag
- Lid retraction
- Exophthalmos (Graves’ disease)
- Extraocular signs:
- Cardiovascular:
- ↑ Heart rate (HR)
- Palpitations and irregular pulse, with abnormal heart beats (e.g., atrial fibrillation (AF))
- Hypertension with widened pulse pressure
- Chest pain
- Neuromuscular and psychiatric signs:
- Anxiety and restlessness
- Insomnia
- Fine tremors
- Hyperreflexia
- Myopathy (proximal muscle weakness with normal creatinine kinase (CK) levels
- Osteoporosis
- Reproductive:
- Oligo/amenorrhoea
- Gynaecomastia, infertility problems and decreased libido (50% of men may have sexual dysfunction)
- Metabolic and dermatological:
- Heat intolerance
- Weight loss with increased appetite
- Fatigue
- Warm moist skin
- Excessive sweating
- Pretibial myxoedema (infiltrative dermopathy)
- Fine hair with loss
- Onycholysis
- Palmar erythema
- Gastrointestinal:
- Increased bowel movements
- Cardiovascular:
Thyrotoxicosis
As mentioned above, thyrotoxicosis is the description of the hypermetabolic state caused by increased levels of circulating thyroid hormones. This can occur as a result of hyperthyroidism (i.e. over-activity of the thyroid gland), or due to other causes, detailed below:
| Associated with hyperthyroidism | Excessive thyroid stimulation:
|
Endogenous thyroid-hormone secretion:
|
|
| Other causes | Thyroiditis (see section below):
|
Exogenous thyroid hormone excess:
|
|
Ectopic thyroid tissue:
|
|
Table 1: Causes of thyrotoxicosis
Graves’ disease
- Grave’s disease is an autoimmune thyroid condition that is associated with hyperthyroidism. It is due to TSH receptor autoantibodies that lead to overstimulation of thyroid gland, and excessive thyroid hormone production. It is the most common cause for hyperthyroidism in iodine sufficient parts of the world, affecting females more and of peak age between 20-40 years old.
- 50% of the patients will report having a family history of other autoimmune disorders such as T1DM or pernicious anaemia. There is also association with human leukocytic antigen (HLA-DR3, HLA-B8) alleles.
- Grave’s disease occurs due to B and T cell autoimmunity, and an increase in the production of stimulating IgG against TSH receptors, leading to an increase in the thyroid gland size and function with manifest hyperthyroidism and goitre.
Associated conditions
- Endocrine: T1DM, Addison’s disease,
- Dermatological: Vitiligo, Alopecia areata
- Haematological: Pernicious anaemia
- Neurological: Myasthenia gravis
- Gastrointestinal: Coeliac disease
- Other autoimmune conditions occur with HLA-DR3
Risk factors
- Female sex
- Smoking
- Drug-induced (alemtuzumab used for multiple sclerosis)
- Infection with Yersinia enterocolitica and Borrelia burgdorferi
- Pregnancy (due to overstimulation by high levels of hCG and TSH receptor antibodies (TRAb) during 1st trimester)
- Stress (due to cortisol mediated immune suppression followed by rebound immunologic hyperactivity)
Clinical picture
In addition to the thyrotoxic picture described above, patients also present with triad of: Diffuse goitre, Graves ophthalmopathy and dermopathy.
- Diffuse goitre which is smooth, uniformly enlarged, and non-tender. Sometimes bruit can be heard over the superior poles due to increased vasculature.
- Ophthalmopathy occurs due to activated B and T cells lymphocytic infiltration retro-orbitally, that leads to a cascade of immunological reactions occurring and cytokine release (TNF-α and INF-γ). Accordingly, fibroblast proliferation leads to an increase in the hyaluronic acid, glycosaminoglycans (GAGs) and adipocytes causing an increase in intra-orbital fat and muscle tissue volume. These changes are manifested as exophthalmos, ophthalmoplegia, lid retraction and exposure conjunctivitis and keratopathy.
- Other manifestations of Grave’s disease can be pretibial myxoedema which is a non-pitting oedema on both lateral and anterior aspects of the leg.
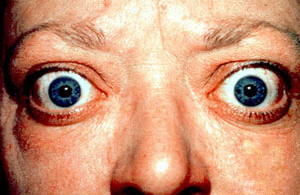
Image Source: Wikimedia Commons (2022). Graves Opthalmopathy, Licensed under a Creative Commons licence. Available for free at: https://en.wikipedia.org/w/index.php?title=Graves%27_ophthalmopathy&oldid=1130342091 (Accessed 13 May 2025).
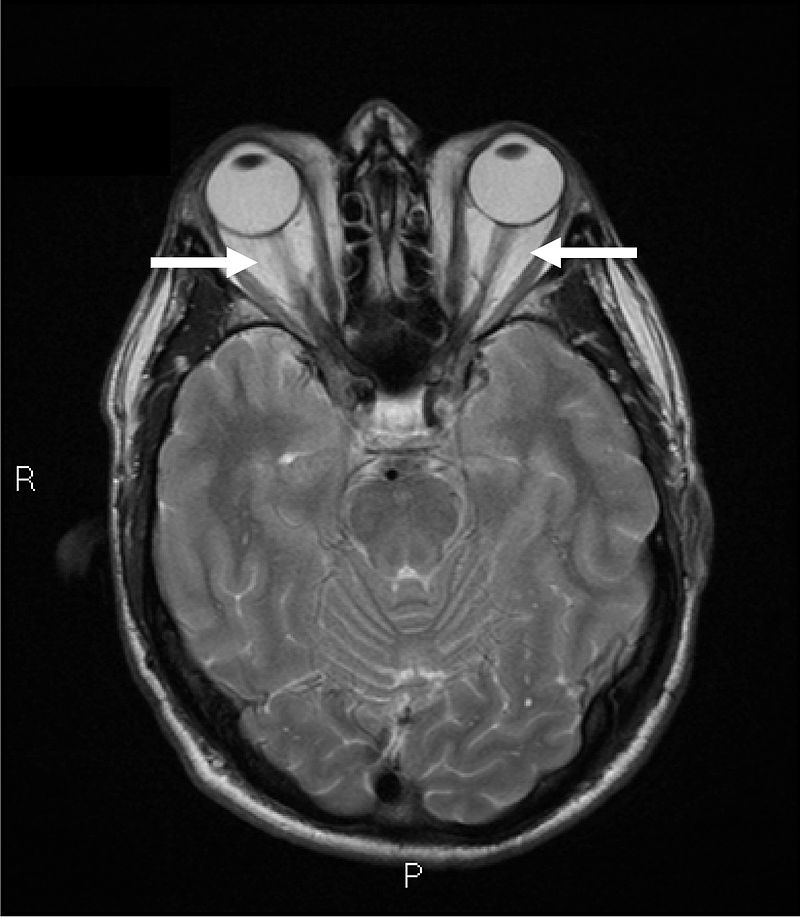
Image Source: Wikimedia Commons (2022). Graves Opthalmopathy, Licensed under a creative commons licence. Available for free at: https://en.wikipedia.org/w/index.php?title=Graves%27_ophthalmopathy&oldid=1130342091 (Accessed 13 May 2025).
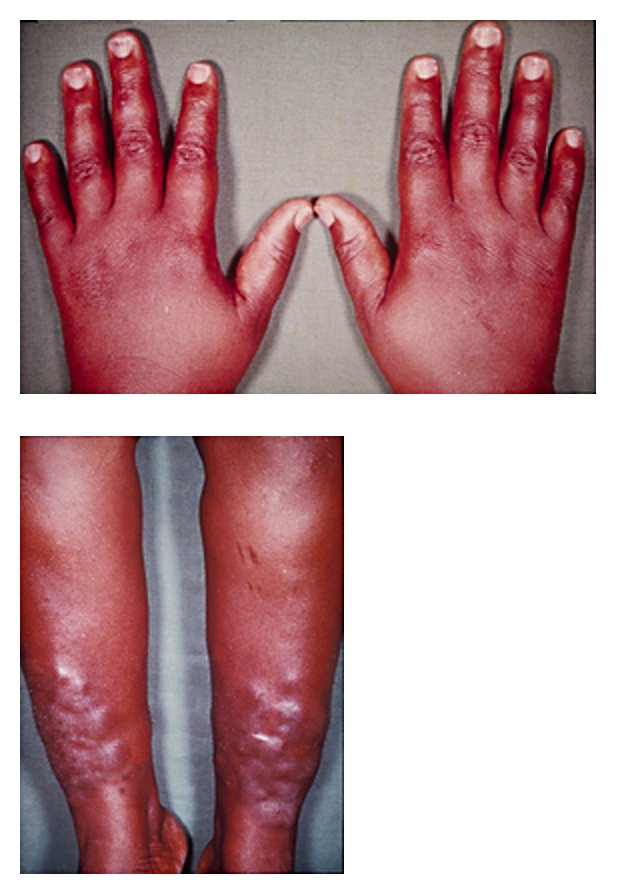
Image Source: Wikimedia Commons (2008). Pretibial Myxedema, Licensed under a creative commons licence. Available for free at: https://commons.wikimedia.org/wiki/Category:Pretibial_myxedema#/media/File:Myxedema.jpg (Accessed 13 May 2025).
Investigations
Diagnosis is based on the clinical picture and is confirmed through thyroid function tests (TFTs) and antibody findings.
- TFTs: low or undetectable TSH with high T3 and T4
- Thyroid antibodies can be specific such as high TRAbs, or non-specific as high Antithyroid peroxidase (anti-TPO) antibodies, and Thyroglobulin (anti-Tg) antibodies.
- Thyroid ultrasound which shows enlarged hypervascular thyroid. Can be used in pregnancy if TRAbs are low.
Management
Goals and principles:
- Induce remission.
- Monitor for any relapse, Monitoring initially is 6-8 weekly for the 1st 6 months, then 6-monthly for 2 years. Afterwards, annually depending on the symptoms.
- For relapse, radiotherapy or surgery are considered as definitive treatment.
- Treatment is usually subdivided into hyperthyroidism state control and symptomatic control.
NICE guidelines recommends the following management:
- Hyperthyroidism state control via Antithyroid drugs (ATDs)
| Medication | Mechanism | Indication | Side effects | Contraindication |
|---|---|---|---|---|
| Carbimazole |
|
|
|
|
| Propylthiouracil (PTU) |
|
|
Table 2: Antithyroid (ATDs) drugs mechanism of action and indications
Two treatment regimens are identified; dose titration and block and replace regimes.
- Dose titration regime:
A relatively high dose of ATDs is started and dose is titrated according to TFTs (TSH particularly) that are performed every 4-8 weeks. It continues for 18 weeks. Some cases of relapses can be seen after discontinuing the therapy. Hence, Long-term therapy at a low dose can be an option. This regime has lower SE compared to block and replace regime.
2. Block and replace regime:
After achieving euthyroid state on carbimazole, Levothyroxine is started. This regime I can continue for 6 months. It allows fewer visits to the hospital for multiple TFTs.
- Hyperthyroidism state control via Radioactive ablation:
Intention is ablation of the gland then commencing thyroxine replacement therapy. It is becoming introduced more to children >10 years old. Sometimes ATDs are started after radioiodine administration and tapered down gradually as per TFTs. There is no risk of thyroid malignancy post-treatment.
Indications for radioactive ablation can be as 1st line after failure of ATDs or surgery. Multinodular goitre or adenoma or relapsed Grave’s disease are other indications. Side Effects of radioactive ablation are radiation induced-thyroiditis, transient hypothyroidism and rarely rebound thyroid storm.
Contraindications for radioactive ablation are pregnancy and lactation. Women of childbearing age should avoid pregnancy for a minimum of 6 months post-treatment. Similarly for men should avoid fathering for minimum of 4 months post-radiation. Other contraindications are Graves ophthalmopathy (due to risk of symptoms worsening), or young children (due to risk of thyroid carcinogenesis).
- Hyperthyroidism state control via Surgery:
Prior to surgery, ATDs, are used to achieve euthyroidism. Rarely, potassium iodide is needed. Β-blockers are needed to prevent an unwanted liberation of thyroid hormones during surgery.
Indications for surgical management are usually preserved for suspicious/malignant thyroid nodules. pregnant women with post-ATDs failure or complications. Surgery is done in the 2nd trimester. Patients who have poor compliance to medical treatment, refuse radiation therapy, have either relapsed Graves’ disease, severe Graves’ ophthalmopathy, or large goitres with have low-radioiodine uptake and with local compressive symptoms are also offered surgical management.
Thyroidectomy can lead to nerve damage, hypoparathyroidism, local haemorrhage or wound infection, hypothyroidism, or keloid formation.
- Symptomatic control
One of the common symptoms that requires treatment in hyperthyroidism is AF. Rate control medications particularly propranolol is commonly used. Propranolol is non-selective β-Blocker which not only has HR control effect but also, inhibits the conversion of T4 to T3 peripherally. Anticoagulation should also be considered.
Nodular thyroid disease
Thyroid nodules are abnormal growths within the thyroid gland that are subdivided into benign ( ~ 95% of the cases) and malignant ones which are less common. Types of thyroid nodules are shown in Table 3.
| Benign nodules | Malignant Nodules |
|---|---|
Thyroid adenomas
Thyroid cyst
|
|
Table 3: Types of nodular thyroid disease
Thyroid nodules are present in 50% of the population but only palpable in 5-10% of the population. They are more predominant in females and are more prevalent in inland regions where iodine content in food and water is low. Less than 5% of these nodules can be malignant.
Clinical picture
The clinical picture depends on the activity and the virulence of the nodule. For example, the follicular type is considered an inactive nodule. whereas toxic adenoma and toxic multinodular goitre are considered active nodules, and patients present with symptoms of hyperthyroidism. These nodules are usually painless.
Thyroid cysts are due to cystic degeneration in the thyroid tissue or involution of adenoma. They usually present with a palpable nodule that can be tender due to haemorrhage inside the cyst or may cause compressive symptoms such as hoarseness and dysphagia. Pemberton’s sign (facial erythema and jugular venous distension on raising the arms) is a sign of Superior Vena Cava (SVC) obstruction by a substernal mass. Thyroid nodules in pregnancy have shown increase in size and number with increase in malignancy risk. As a result, surgical removal can be indicated in the 2nd trimester or post-partum.
Malignancy should be suspected in patients <20 or >60 years old. Other red flags for malignancy can be male gender, history of radiation to the head and neck, rapidly growing nodules with compression symptoms, and firm fixed nodules that may be associated with cervical lymphadenopathy. Some genetic associations increasing risk of malignancy are:
- MEN2 syndrome
- Gardner syndrome
- Cowden syndrome
- Family history of thyroid malignancy.
Investigations
- Fine needle aspiration biopsy (FNAC).
- Serum TSH: High levels are associated with higher risk of malignancy.
- Imagining can be thyroid US or thyroid scintigraphy (which shows cold nodules are associated with malignancy, hot nodules are less likely to be malignant).
- Investigation of complications: e.g., symptoms suggestive of SVC obstruction from a goitre require CT imaging
Management
NICE guidelines recommend management of nodular goitre depending on the activity of the nodules and virulence.
Management of non-toxic multinodular goitre may involve:
- Surgery
- Compressive symptoms
- Cosmetic reasons
- Solitary nodule with FNAC suggestive of malignancy
- Radioiodine
- Indications same as for surgery, in patients not fit enough to undergo surgery
- Medical treatment
- Not generally used, but T4 replacement may be useful if TSH is detectable
Management of toxic multi-nodular goitre:
- Radioiodide management
- 1st line definitive treatment.
- That might be due to the accumulation of 131 I preferentially in the hot nodules , not the normal thyroid tissue causing an euthyroid state as a result
- Surgery
- Aims to remove the nodular tissue.
- For symptomatic relief
- Post-operative monitoring of the TFTs is advised as patients at risk of becoming hypothyroid and may require thyroxine replacement.
- It is considered the 2nd line of management if ATDs fail if a patient is pregnant or fathering a child in 6 months.
- ATDs such as Carbimazole
- Effective for hyperthyroidism, but are not curative treatments
- There is a risk of recurrence when the medications are stopped.
Thyroiditis
Thyroiditis refers to a transient state of thyrotoxicosis followed by hypothyroidism features. It occurs due to gland inflammation. It is more common in women, with a peak incidence of 30-50 years old.
Causes of thyroiditis include:
- Hashimoto’s disease (discussed later on in this chapter)
- Post-partum thyroiditis
- Usually occurs within 6 months of giving birth.
- It occurs in about 30-52% of patients of +ve TPO antibodies.
- Is associated with type 1 diabetes
- Most patients show complete remission with fewer incidence of permanent hypothyroidism as a complication.
- Drug-induced e.g., amiodarone, lithium, interleukin 2 or interferon-α(due to thyroid peroxidase antibodies formation in 15% of the cases).
- Subacute (De Quervain’s thyroiditis)
- May occur due to granuloma formation, usually associated with viral upper respiratory tract infection (mumps, coxsackie, influenza, adenovirus, and echovirus).
- May also occur due to lymphocytic infiltration, which may occur in the post-partum period, in association with autoimmune disease, or as a side effect of a drug.
- Has a triphasic picture:
- The thyrotoxic phase occurs due to the inflammatory damage of the follicular cells, releasing thyroid hormones (pre-formed colloid).
- The hypothyroid phase follows due to the depletion of the thyroid hormones and reduced synthesis as a result of follicular cell damage.
- The euthyroid phase is achieved where, a recovery of the thyroid gland occurs with pathological changes and the thyroid function normalises
- Riedel’s thyroiditis
- A rare condition characterised by extensive thyroid gland fibrosis and the surrounding structure.
- One third of the patients have associated extracervical manifestations for example: pulmonary, sclerosing cholangitis, mediastinal, and retroperitoneal fibrosis. Parathyroid glands fibrosis is rare.
- Patients are usually in euthyroid state. 30% of the patients develop hypothyroidism eventually with extensive fibrosis.
- Malignancy should be excluded.
- Radiation
- Pyogenic
- e.g., Staphylococcus aureus, streptococci, Escherichia coli, tuberculosis, fungal.
- Usually caused by another septic focus.
- Piriform sinus infection should be excluded.
Clinical picture
The clinical picture depends on the cause of thyroiditis:
- Patients may present with features consistent with hypothyroidism or hyperthyroidism
- In suppurative and subacute causes, painful tender glands and fever is common.
- With subacute thyroiditis, there is usually a prior history of upper respiratory tract infection, generalised malaise, and arthralgia.
- Hashimoto’s disease, as will be described later, is usually associated with goitrous appearance and a clinical picture of hypothyroidism.
- With Riedel’s thyroiditis, a hard woody consistency of the thyroid may be noted. Patients are usually euthyroid in Riedel’s thyroiditis.
Investigations
- Erythrocyte sedimentation rate (ESR) or C-reactive protein (CRP) are raised in a state of inflammation.
- TFTs will show either a picture of hyper or hypothyroidism depending on the cause of the thyroiditis.
- Anti-TPO might be elevated.
- Thyroid scintigraphy
- Radionuclide uptake is reduced in subacute thyroiditis (due to follicular cell damage).
- Inconclusive in acute and chronic conditions.
- Thyroid US
- Some nodular pattern and cobblestone appearance are seen in subacute thyroiditis (due to reduced vascularity and hypoechoic regions)
- FNAC
- Can show lymphocytic or granulomatous picture in subacute thyroiditis. Aspiration culture should be sent in acute cases.
Management
- When it comes to treatment of thyroiditis, two aspects are considered: generic management of symptoms and acute thyroid function change; and management of the underlying cause of the thyroiditis. Patients should have their thyroid function monitored regularly, with the frequency of this depending on the underlying cause.
- In terms of general management, as was discussed previously, the management of hyperthyroidism entails treatment of the hyperactivity as well as treating thyrotoxic symptoms. If hypothyroidism is prevalent, T4 replacement is required.
Management of the different causes of the thyroiditis is summarised in Table 4.
| Type of thyroiditis | Management |
|---|---|
| Riedel’s thyroiditis | Surgery to relieve obstruction, and in suspected malignancy.
Tamoxifen has shown some benefit. Corticosteroids are of limited benefit. |
| Pyogenic thyroiditis | Antibiotic therapy is usually required
Incision and drainage/excision in case of presence of abscess, sinus, or tract formation respectively. |
| Subacute thyroiditis | Mild cases can benefit from non-steroidal anti-inflammatory drugs (NSAIDs) and paracetamol for analgesia.
Severe cases are treated with glucocorticoids (prednisolone 20-40mg/day). Treatment is given till T4 returns to normal. Once a patient is in a hypothyroid state, they are given T4 replacement. ATDs are not indicated. |
| Drug induced thyroiditis | Stopping of the offending agent. |
Table 4: Thyroiditis management
Thyrotoxic crisis (storm)
- A thyrotoxic crisis is a rare but life-threatening exacerbation of thyrotoxicosis. Mortality can reach 30-50%. Some data shows higher predominance in females especially in pubertal children.
- It occurs as a response to stressful conditions e.g., infection, DKA, gland trauma, pregnancy, surgical treatments or during radioiodine treatment. Other causes can be excessive thyroid hormone ingestion or non-compliance with ATDs.
Clinical picture
Patients with thyroid storms are generally unwell, presenting with fever, altered mental status with tachycardia or tachyarrhythmias. Multisystem decompensation can occur, which can be fatal. This entails cardiac failure/arrhythmias, respiratory distress, congestive hepatomegaly (causing jaundice), dehydration and pre-renal failure (due to vomiting and diarrhoea). Patients may also exhibit neurological dysfunction in the form of severe agitation, delirium, seizures, and coma.
Investigations
The diagnosis of a thyroid crisis is based on clinical features, not on laboratory findings. So, in suspicion of a thyroid storm, treatment should not be delayed whilst awaiting blood results.
- ECG: will show AF which is the commonest form of arrhythmia occurring in thyroid storms.
- Full blood count (FBC): Can show signs of infection.
- Biochemical screen: Electrolyte disturbance and renal failure may be seen. Raised liver transaminases and bilirubin and raised Ca+2.
- TFTs: Thyroid hormones are elevated, with suppressed TSH. Thyroid antibodies can be present.
Management
Treating thyroid storm must address two aspects: stabilisation of the patient; and management of the underlying thyroid pathology:
- Resuscitation, supportive therapy, and treatment of the cause which involves:
- Best management is delivered in ITU for better monitoring of the cardiorespiratory status and fluid balance.
- Electrolyte imbalance should be corrected.
- If the patient develops AF, arrhythmia management and anticoagulation should be considered.
- Usually, high dose propranolol 160-480mg/day is given in divided doses as PO or IV.
- Cardio-selective β-blockers can be used as alternatives in patients with reactive airway disease.
- Calcium channel blockers are another alternative.
- In a state of infection, broad spectrum antibiotics should be started.
- Chlorpromazine (50-100mg IM) has shown effect in treating agitation and hyperpyrexia. Hyperthermia can be treated by applying ice packs and cooling blankets.
- Treatment of the thyrotoxic state, which aims to inhibit thyroid hormone synthesis completely. Hence, the following should be given:
- Propylthiouracil 200-300mg 6 hourly via NG.
- It has the ability to block peripheral conversion of T4 to T3.
- High dose carbimazole NG 45-60mg/d can be an alternative.
- Potassium iodide 60mg NG 6 hourly and started after 6 hours from the propylthiouracil.
- It inhibits thyroid hormone release.
- High dose of glucocorticoids (Prednisolone 60mg/day or hydrocortisone 400mg IM QDS)
- Blocks T4 to T3 conversion.
- Cholestyramine (3g TDS)
- Improves thyrotoxicosis by reducing enterohepatic circulation of thyroid hormones.
- Propylthiouracil 200-300mg 6 hourly via NG.
Thyrotoxicosis in pregnancy
Thyrotoxicosis occurs in ~0.2% of pregnancies, where Grave’s disease is the most prevalent clinical thyrotoxic picture. It is considered the 2nd most common endocrine complication to occur in pregnancy after diabetes. Other risk factors for developing gestational hyperthyroidism are hyperemesis gravidarum and trophoblastic neoplasia.
Clinical picture and investigations
- Physiological changes in pregnancy, like increased basal metabolic rate and cardiovascular changes, can mimic hyperthyroidism. The most suggestive symptoms of thyrotoxicosis in pregnancy are failure to gain weight despite adequate intake and tachycardia. Grave’s ophthalmopathy can occur in 1/3 of cases. Symptoms are more severe in the 1st trimester and post-partum periods.
- Diagnosis is confirmed with the lab findings of suppressed TSH and elevated T3 and T4. Normally in pregnancy, T3 and t4 increase in the 1st trimester with low/normal TSH. In the 2nd and 3rd trimester TSH normalises and T3 and T4 are slightly lower.
Complications
Potential complication due to untreated gestational hyperthyroidism can be either affecting the mother or the foetus:
- Maternal complications
- Pregnancy-induced hypertension
- Preterm delivery
- Congestive heart failure
- Thyroid storm
- Miscarriage
- Abruptio placentae
- Accidental haemorrhage
- Foetal complications
- Hyperthyroidism
- Neonatal hyperthyroidism
- Intrauterine growth retardation
- Small-for-gestational age
- Prematurity
- Stillbirth
- Craniosynostosis
Management
- The aim of treatment is alleviation of thyroid symptoms and normalisation of thyroid function. Patients should have their TFTs monitored every 4-8 weeks. The block-and-replace regimen is not used due to the risk of foetal hypothyroidism. ATDs used can be PTU (preferably in the 1st trimester as it can cause child hepatotoxicity). Dosage depends on the TFTs done at 2-4 weeks intervals, aiming to maintain free thyroid hormone in the upper third of the reference range. β-blocker can be used to alleviate the high BMR state, but only prescribed for a few weeks.
- Iodides and radioiodine are contraindicated in pregnancy. Surgical management is reserved for refractory cases and better done in the 2nd trimester. Breastfeeding is preferred to continue while the mother is on the lowest possible dose of carbimazole. As mentioned before, PTU has greater risk of child hepatotoxicity.
Complete Guide to Clinical Genetics ST3 Application and Recruitment (2027)
Written by Medibuddy. Last updated: October 2026. Clinical Genetics is

Complete Guide to Clinical Radiology ST3 Application and Recruitment (2027)
Recruitment paused: NHS England is not running Clinical Radiology ST3+ recru

Complete Guide to Paediatric Surgery ST3 Application and Recruitment in United Kingdom (2026)
Written by Medibuddy. Last updated: October 2026. If you’re planning


Take your subscriptions with you
Our mobile app allows you to access your interview and exam question banks wherever you are.

