Paediatric Surgery ST3 Interview Question Bank | Medibuddy
Paediatric Surgery ST3 • 2027 Interview

The 2027 Paediatric Surgery ST3 Interview Revision Platform: Question Bank, Live Practice and Mocks with Other Candidates

The Medibuddy Paediatric Surgery ST3 Question Bank includes over 50 scenarios that closely mirror the real interview, each with a model answer written/edited by high-scoring candidates who sat the Paediatric Surgery ST3 interview in 2026.

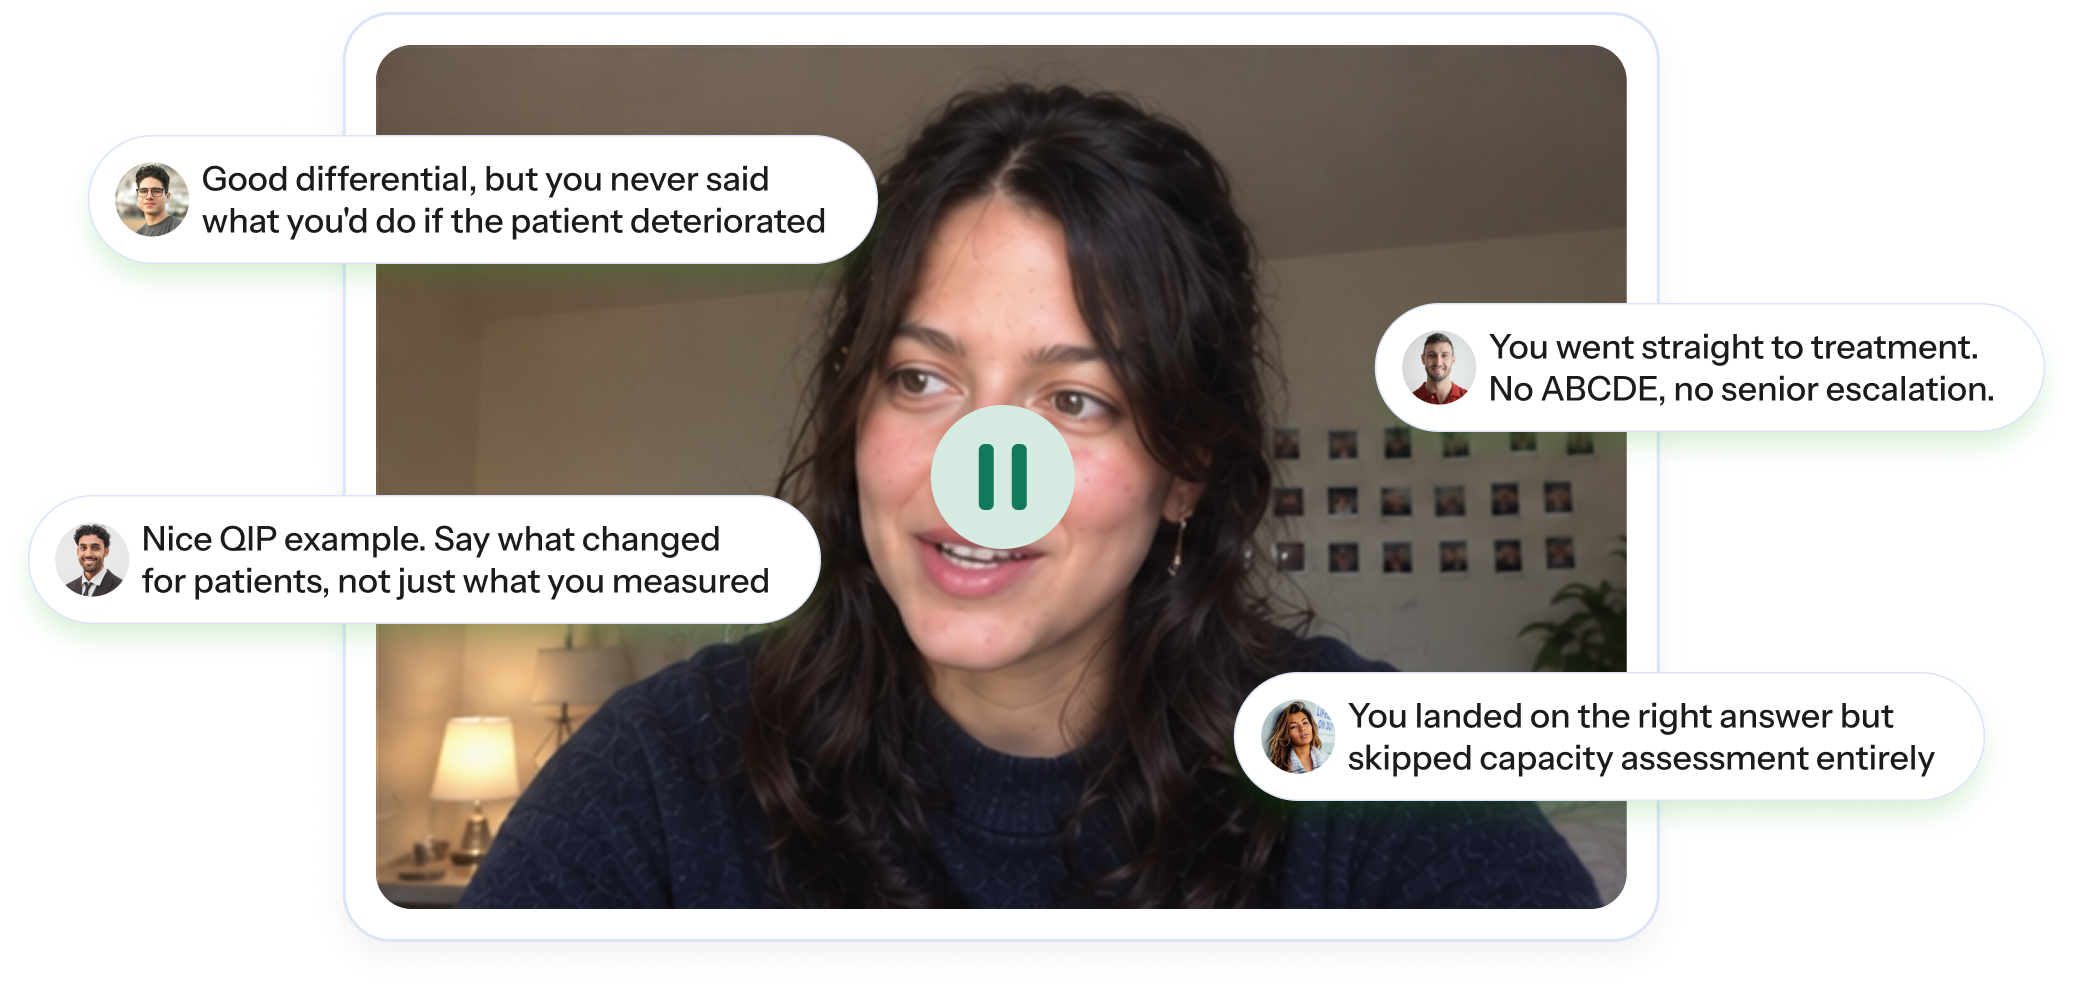
However, knowing a strong answer isn't the same as delivering it well under pressure, which is why we provide:

10 years’ experience preparing doctors for interviews

Users of the Medibuddy Paediatric Surgery ST3 Revision Platform have secured some of the most competitive training jobs in recent rounds. Ask around, there's a good chance the trainees in the year above you used us too.

Always up to date

Did you know the interviews change every year? That's why we review and update every Question Bank on the platform twice a year, so you know you're always practising with scenarios based on the latest interview structure.

Network and practise real interview scenarios with other candidates

Question Bank

See every scenario, and how to answer it well

Over 50 scenarios across all four stations, which tell you exactly how to respond to each question.
Study Groups

Connect with candidates across the country
Most people only ever practise with one or two friends. Study Groups connect you with candidates right across the country sitting the same Paediatric Surgery ST3 interview.
Live MocksBeta

Practise interview technique with different candidates

Arrange or get matched on demand with other candidates and run real scenarios out loud under interview conditions. Those who practise with the widest range of people tend to score the highest.
Peer FeedbackBeta

Reviewed by candidates across the platform
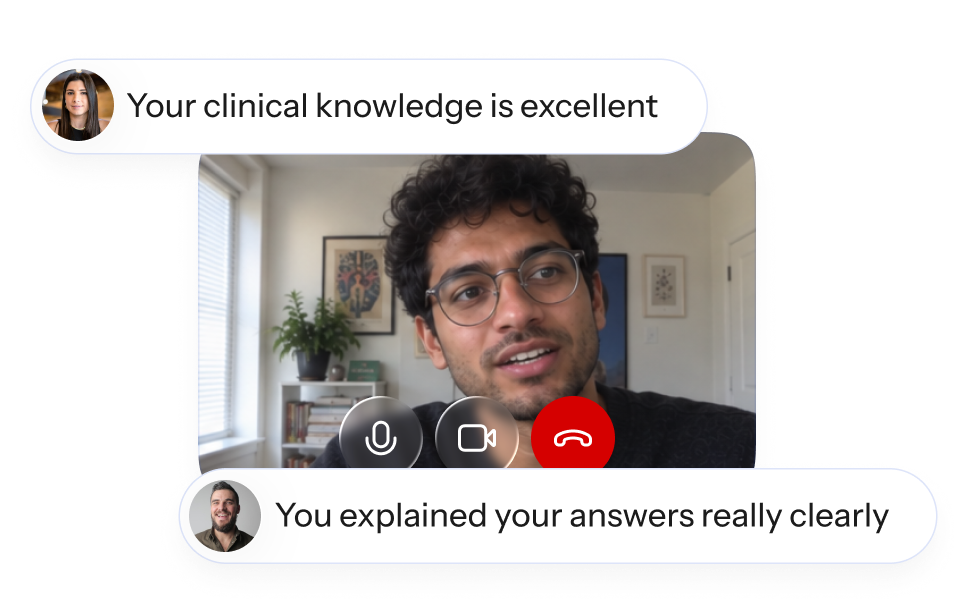
Submit your recorded mocks to candidates across the platform and get honest, varied feedback. Reviewing other people's mocks teaches you just as much.

The question bank, and other candidates to practise with, all in one platform.

Paediatric Surgery ST3 Revision Platform • £144.99

Gain access to over 50 scenarios across all four stations, and collaborate with other candidates through Study Groups, Live Mocks and Peer Feedback.
Get instant access
What candidates say

Scored well, secured their post

A few of the candidates who prepared with us for the Paediatric Surgery ST3 interview.

Verified candidateInterviewed 2026
"The clinical scenarios were pitched exactly right. Having a structure ready meant I could work through a surgical emergency calmly under pressure."
Secured first-choice deanery
Verified candidateInterviewed 2026
"Practising the academic and career progression stations out loud with other candidates was the single most useful thing I did before the day."
Ranked highly
Part 1 • See the questions

The Medibuddy 2027 Paediatric Surgery ST3 Question Bank

The interview is a four-station online panel taking around 40 minutes of assessed time, and each station is tightly timed, so you have a limited window to deliver the high-scoring answers you need to do well. That means every point has to land, and knowing how to structure each answer is essential. That's why each of our 50-plus scenarios comes with a model answer, written by candidates who scored highly in the 2026 Paediatric Surgery ST3 interview, so you know exactly how to approach every question the interviewers throw your way.
What's inside

What's included in the Paediatric Surgery ST3 Question Bank

There's nothing worse than getting to the interview and being handed a scenario you've never seen before. The panel draws on clinical, academic, career and communication themes across the four stations, so the safest approach is to revise across all of them. We provide scenarios for every part of the interview, including the common ones and the more unusual cases that have come up before, so you don't get caught out.

Clinical Scenarios

Paediatric surgical cases and emergencies where you play the registrar: assess, reason and manage safely, each with a worked answer showing how to structure your response.

Academic & Presentation

The academic station and the presentation sent a week beforehand, covering research methodology and critical appraisal, with guidance on delivering a clear academic argument.

Career Progression

Questions on your training trajectory, commitment to paediatric surgery and the reasoning behind your decisions, with model answers so you can evidence sustained engagement.

CARE Communication

The piloted communication station, with worked scenarios showing how to communicate clearly and sensitively with children, families and colleagues.
Reflecting the current structure
The interview is a four-station online panel marked against the 2026 person specification, and includes a piloted CARE communication station. Our scenarios are built around exactly this format.
Try it

Try an example Paediatric Surgery ST3 question

You are the paediatric surgery ST3 registrar on call. A 13-year-old boy is brought to A&E at 2am with a three-hour history of sudden right scrotal pain that woke him from sleep. He is vomiting and rates the pain 9 out of 10.

On examination the right testis is high-riding and transversely orientated, with significant tenderness and an absent cremasteric reflex on the right. There is no history of trauma or urinary symptoms.

How would you approach this?

Question
What is your working diagnosis, and how would you assess him urgently?
Example answer
This is testicular torsion until proven otherwise, a surgical emergency needing immediate action.
  • Confirm the history: sudden onset, the duration of symptoms (ischaemia time is critical), nausea and vomiting, and any previous similar episodes suggesting intermittent torsion.
  • Examine both sides: a high-riding, transversely lying testis, an absent cremasteric reflex and extreme tenderness are classical.
  • Note the contralateral testis for a bell-clapper deformity, which raises the risk of bilateral torsion.
  • Do not wait for imaging: the diagnosis is clinical, and imaging must never delay theatre.
Question
What is the role of scrotal Doppler ultrasound here?
Example answer
Doppler can show absent or reduced flow, but its role is limited and must never delay operative exploration when the diagnosis is clear.
  • It is operator-dependent and imperfect, and a normal-looking scan does not exclude torsion, especially early or partial torsion.
  • It has a role only when the diagnosis is genuinely uncertain, for example if the picture could equally be epididymo-orchitis, and where theatre can still be reached in a safe window.
  • In this boy, with a three-hour history, an absent cremasteric reflex and a high-riding testis, he should go straight to theatre, and requesting a scan would risk unacceptable delay.
Question
How does ischaemia time relate to salvage, and how does that affect your decision?
Example answer
Salvage rates fall the longer the testis is torted.
  • Under 6 hours: roughly 90 to 100%.
  • 6 to 12 hours: roughly 50 to 70%.
  • 12 to 24 hours: roughly 20 to 50%.
  • Over 24 hours: under 10%.
With a three-hour history his salvage rate is high, which reinforces the urgency of immediate theatre as the next emergency case. The degree of twist also matters, and I would set realistic expectations with the family.
Question
How would you consent him, and what are your operative steps?
Example answer
I would consent for exploration of the right scrotum, with detorsion and bilateral orchidopexy if the testis is viable, or orchidectomy and contralateral orchidopexy if it is not.
  • Under general anaesthesia, supine, make a scrotal incision on the affected side and deliver the testis, identifying the degree and direction of torsion.
  • Detorse it and assess viability, wrapping it in a warm swab for 5 to 10 minutes.
  • A clearly viable testis is fixed with non-absorbable sutures (orchidopexy); a frankly non-viable one is removed.
  • Explore the contralateral side and perform prophylactic orchidopexy regardless, as the bell-clapper deformity is often bilateral.
Question
After detorsion and warming the testis looks dusky but not frankly necrotic. How do you decide, and what are the priorities if it is removed?
Example answer
This is a genuinely difficult intraoperative judgement, often made with the consultant.
  • After adequate warming, reassess for returning pink perfusion, pulsation and bleeding on a small nick in the tunica; any reasonable evidence of perfusion favours fixing it, as endocrine function may be preserved even if fertility is lost.
  • An entirely black, non-perfused testis with no recovery should be removed, as leaving necrotic tissue risks sepsis.
If it is removed, the priorities are analgesia and scrotal support, wound and haematoma checks, confirming the contralateral orchidopexy, and counselling the boy and family: the option of a prosthesis later, follow-up of the remaining testis, fertility counselling at an appropriate age, and clear safety-netting that any future sudden scrotal pain is an emergency.
Question
A 2-day-old neonate has a hard, painless, discoloured left hemiscrotum. How does neonatal torsion differ?
Example answer
Neonatal torsion is a distinct entity.
  • It is almost always extravaginal, as the gubernaculum is not yet fixed, unlike the intravaginal torsion in adolescents.
  • It may be antenatal, where the testis is often already non-viable at birth, or postnatal, which is more likely to be salvageable.
  • Current consensus still favours urgent scrotal exploration, with orchidectomy of the affected side and contralateral orchidopexy, because the risk of a later contralateral torsion causing anorchia justifies surgery.
  • The neonatal anaesthetic risk means the consultant and anaesthetic team must be involved immediately, and the family counselled about anorchia and possible hormone replacement.

That's one scenario. There are over 50 more.

Paediatric Surgery ST3 Revision Platform • £144.99

Includes every scenario in the Question Bank, and access to Study Groups, Live Mocks with other candidates and Peer Feedback.
Get instant access
Actively maintained

How we keep our Question Banks up to date

The Paediatric Surgery ST3 interview changes from year to year, and the biggest fear for any candidate is getting to interview day and realising you've revised with a question bank that's totally outdated.

That's why we review and update every Question Bank twice a year, so you know you're revising with scenarios that are likely to come up. We do this in April after the previous year's interviews, and again in the autumn when the new recruitment guidance is published.

For 2027, this process kept the Question Bank aligned with the current four-station online format, including the piloted CARE communication station, so you always practise with the format the panel is using now.
Updated for 2027 Interviews
Part 2 • Practise them live

The only interview resource where you can practise live with other candidates from across the country

Our Paediatric Surgery ST3 Question Bank tells you exactly how to answer real interview scenarios. But how you practise with them will determine how many marks you score. Simply reading answers off a screen won't prepare you for the intense scrutiny you'll face in the interview. And only practising with the same few colleagues or friends limits the amount of feedback you'll get. Medibuddy gives you unique access to Paediatric Surgery ST3 candidates across the country, so you can learn from a variety of perspectives and hear a far wider range of feedback than your own circle could ever give you.
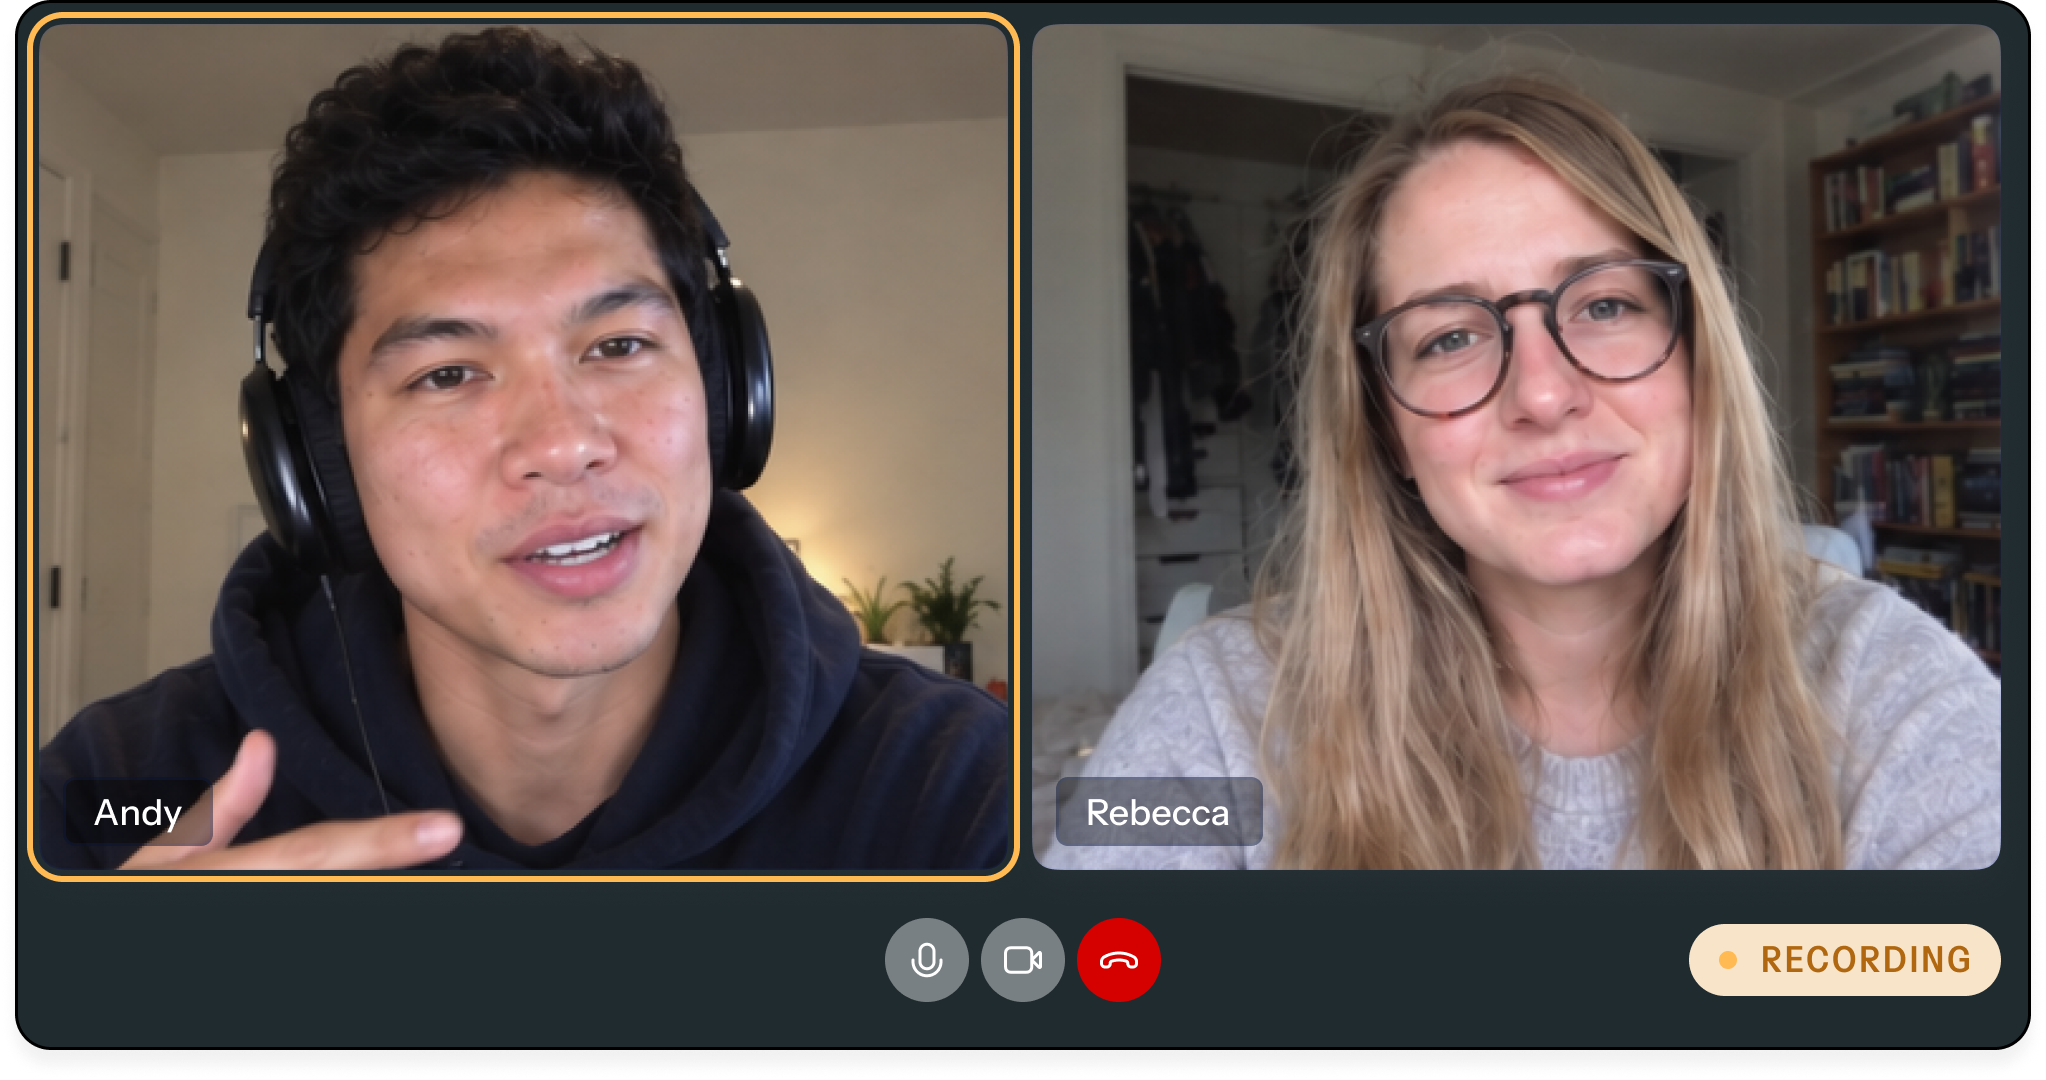
Study Groups
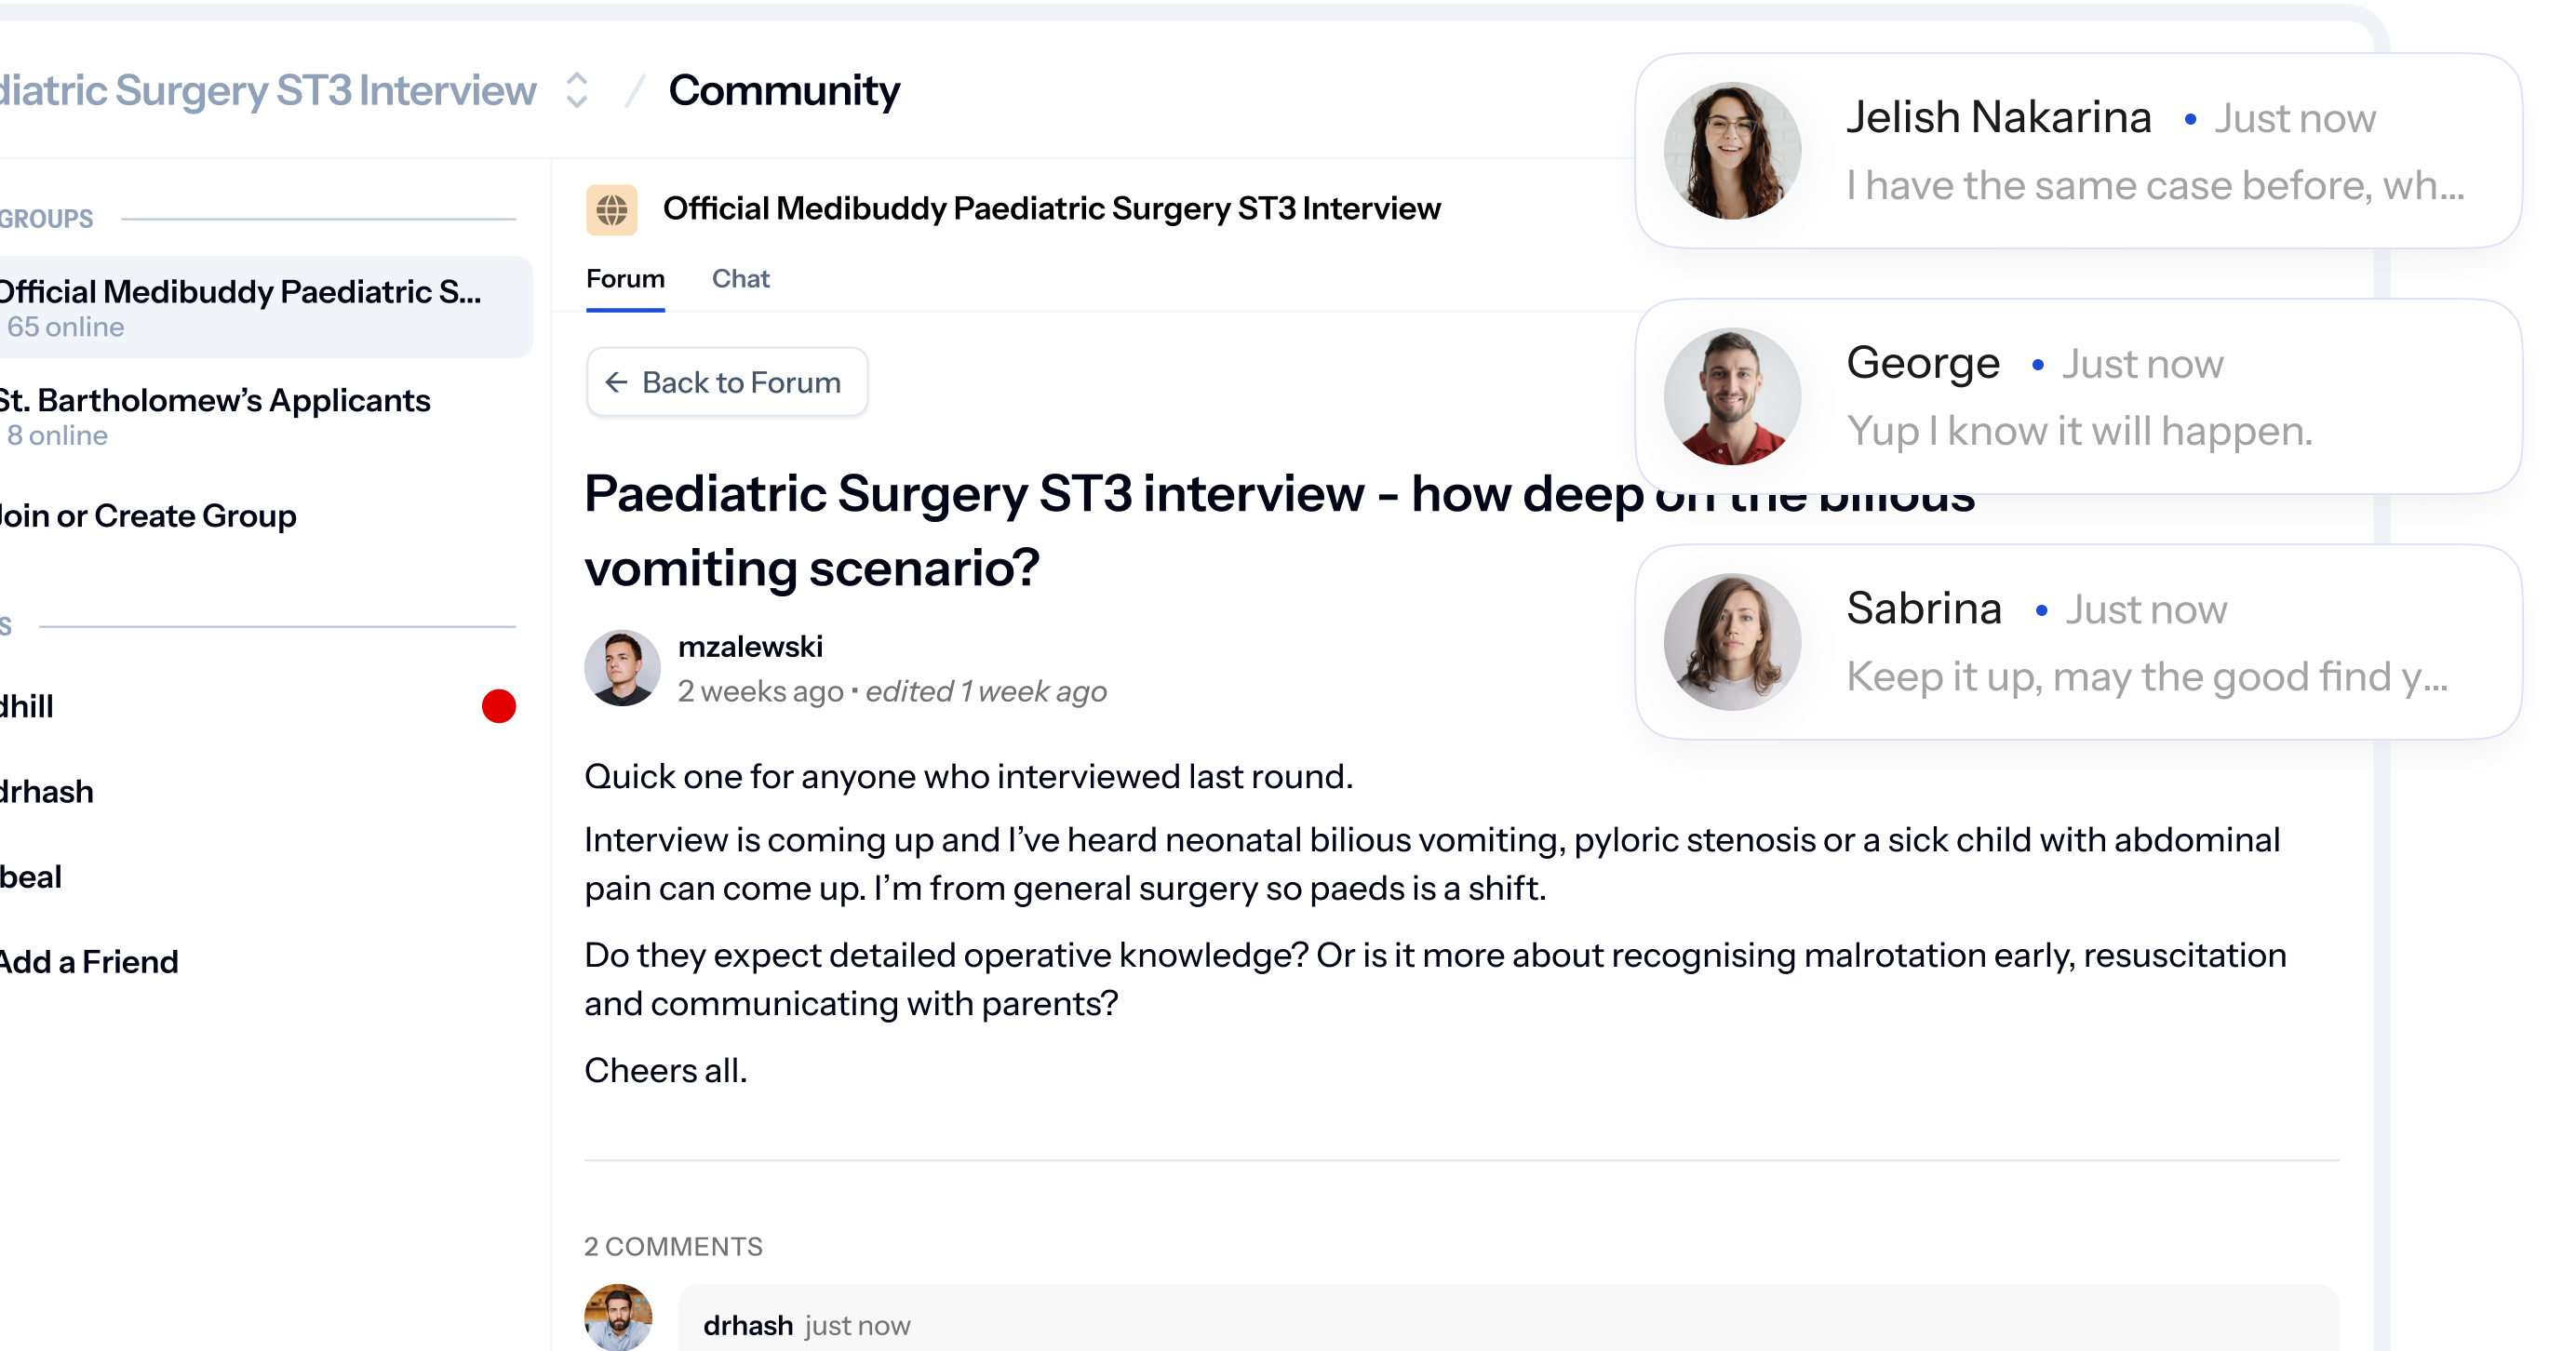
When you prepare in isolation, you're relying on your own interpretation of the interview process, which is one of the quickest ways to get found out on the day. Study Groups connect you with other doctors across the country who are also applying to Paediatric Surgery ST3, so you can engage and network with people preparing for the same interview as you. Everyone brings different experience from different hospitals and deaneries, meaning you won't ever miss out on the key bits of information that could swing the interview in your favour.
Live MocksBeta
Candidates who don't take part in mocks often struggle to adapt to the pressure of the interview. Your knowledge might be correct, but without convincing delivery the interviewers will score you poorly. The best way to improve your delivery is to take part in as many live mocks as possible, which is why we haven't put a cap on how many you can do. We also know how difficult it can be to organise mocks with other people, so all you have to do is join the waiting room and we'll match you with a different Paediatric Surgery ST3 candidate each time. Take turns as both the interviewer and candidate on real Question Bank scenarios, so you can see exactly how other candidates perform in real time, while refining your own interview technique.
Peer FeedbackBeta
Preparing alone means you won't know how you're coming across during the interview. And preparing with the same few candidates means you'll miss opportunities to improve, which is why it's so important to get as many opinions as possible on your performance. With Medibuddy, you can record a mock and submit it for feedback from other candidates on the platform, so you receive a wider range of feedback and refine your answers with each person you practise with. Reviewing other people's mocks is just as valuable, as it shows you how strong candidates handle the same scenarios, which is one of the fastest ways to improve.
The interview

What to expect from the Paediatric Surgery ST3 interview

Paediatric surgery is one of the most competitive specialties, and strong applicants are often separated by narrow margins at interview.

The interview is a four-station online panel, taking around 40 minutes of assessed time, marked against the 2026 person specification.

Station

Clinical

A paediatric surgical scenario, with reading time beforehand, assessing your clinical judgement and safe, structured management as the registrar.
Station

Academic

Tests your academic experience alongside a presentation whose topic is sent a week before, probing research methodology, critical appraisal and clear communication of an argument.
Station

Career Progression

Explores your training trajectory, commitment to paediatric surgery and the reasoning behind your decisions, looking for sustained engagement with the specialty.
Station

CARE Communication

A piloted communication station, testing how clearly and sensitively you communicate with children, families and colleagues.

How the interview is scored

The stations are marked against the Paediatric Surgery ST3 person specification. Our model answers are structured against those criteria, so you know exactly what a strong, well-organised answer looks like at each station.
Get ready

How to prepare for the Paediatric Surgery ST3 interview

Start with the Question Bank

Work through over 50 scenarios across all four stations, each with a worked answer from a candidate who scored well in the 2026 interview. Start by reading how a strong answer is formed, then think about how you'd deliver it.

Talk the hard ones through in Study Groups

Study Groups are your biggest opportunity to network and connect with other candidates sitting the same interview as you. Everyone on the platform is in the same boat, so don't be scared to get involved and ask questions. Someone in your study group might just help you work through a scenario you've been struggling with.

Rehearse out loud in Live Mocks

Live mocks are where you begin to put everything you've learned into practice, and we know from experience that those who practise with a wide range of candidates usually do the best. Organise mocks with people from one of your study groups, or get matched with a random Paediatric Surgery ST3 candidate, then take turns as interviewer and candidate using real scenarios until answering out loud under pressure feels normal.

Get reviewed with Peer Feedback before the day

Once you've recorded a mock, you can have other community members review it. This lets you see how you come across to other people, and gives you time to refine your delivery as you revise, rather than being caught out on the day. Reviewing other people's mocks is just as crucial, as you see how other candidates navigate the same scenarios.
Questions

Frequently asked questions

What does the Paediatric Surgery ST3 interview involve?
A four-station online panel, taking around 40 minutes of assessed time: Clinical, Academic (with a presentation topic sent a week beforehand), Career Progression, and a piloted CARE Communication station. Each is marked against the 2026 person specification.
How competitive is the Paediatric Surgery ST3 interview?
Paediatric surgery is one of the most competitive specialties, and strong candidates are frequently separated by small margins at interview, which is why a structured, well-rehearsed approach matters.
What is the academic station?
It tests your academic experience alongside a presentation whose topic you are sent about a week before the interview, probing research methodology and critical appraisal. Our Question Bank includes guidance on preparing and delivering it.
Who writes the model answers?
High-scoring candidates who sat the Paediatric Surgery ST3 interview in 2026, so the answers reflect what came up and what scored this year.
Can I practise with other candidates?
Yes. Every Revision Platform purchase gives you the opportunity to connect with other candidates through Study Groups, Live Mocks and Peer Feedback.
How do the Live Mocks work?
All you have to do is join the waiting room, and we match you with another Paediatric Surgery ST3 candidate. You then take turns as interviewer and candidate on real Question Bank scenarios, so you gain experience answering out loud to a real person before you ever sit in front of the panel.
What are Study Groups and how do they help?
Study Groups are community forums for doctors across the country preparing for the same Paediatric Surgery ST3 interview. You can ask questions, share what you're struggling with, and compare how you'd approach a scenario.
Can I get feedback on my interview performance?
Yes. After you've recorded a mock, you can ask other members to review it, so you can see which part of your answer needs fine-tuning.
How do you keep the Paediatric Surgery ST3 Question Bank up to date?
We review and update it twice a year: in April after that year's interviews, and again in the autumn when the new recruitment guidance is published, so you always practise with the current four-station format.
How long do I get access for?
Access runs for 12 months from the purchase date.

Start preparing for the Paediatric Surgery ST3 interview

The Revision Platform gives you over 50 scenarios to practise and refine with other candidates through Study Groups, Live Mocks and Peer Feedback. Ten years preparing doctors for interviews, with the questions, this year's model answers and live practice, all in one place.

Paediatric Surgery ST3 Revision Platform • £144.99

Buy Now